$200 Off All 2027 Early Bird Discount

Settle the mind, restore the body & soul back to health. Our deeply restorative 5-day retreat is for midlife women 40+ who are ready to receive abundance, feel rested, strong, clear & back in alignment with their intentions. 

The Neuroscience of Meditation: How Stillness Rewires the Midlife Brain

Marisol sat down to meditate for the first time in a decade the week her period didn’t come. She was forty-six, and the app on her phone promised ten minutes would clear her head. It didn’t. Her mind ran through the grocery list, an unanswered email, the strange heat that had started climbing her neck at odd hours, and a meeting she’d mishandled that morning because she’d lost her train of thought mid-sentence in front of her own team.

She opened her eyes at minute four, certain she was doing it wrong. She wasn’t doing it wrong. She had the wrong expectation. Marisol, like most people, assumed meditation meant successfully making the mind go blank, and by that standard, she failed every single session for weeks.

What she didn’t know, and what almost nobody tells you when you download a meditation app, is that the brain never actually goes empty. Not for monks with forty years of practice, not for anyone. The goal was never silence. The goal was training, and Marisol had been grading herself against a target that doesn’t exist.

That distinction, between meditation as a feeling and meditation as a mechanism, is where the real neuroscience starts. Brain imaging research over the past two decades has moved meditation from the wellness aisle into some of the most rigorously studied cognitive training available, and what it shows has real relevance for a midlife brain specifically, one that’s navigating hormonal shifts to attention, memory, and emotional regulation whether it meditates or not.

Important: This article is educational and does not replace individualized medical or psychiatric advice. Women with a history of significant trauma, dissociation, or certain psychiatric conditions should work with a qualified professional before starting an intensive meditation practice.

What Is Meditation Actually (It’s Not “Clearing Your Mind”)?

Meditation covers a family of mental training techniques built around intentionally directing attention and awareness. Across traditions and techniques, most forms combine some mix of attention regulation, body awareness, breath awareness, and conscious self-observation.
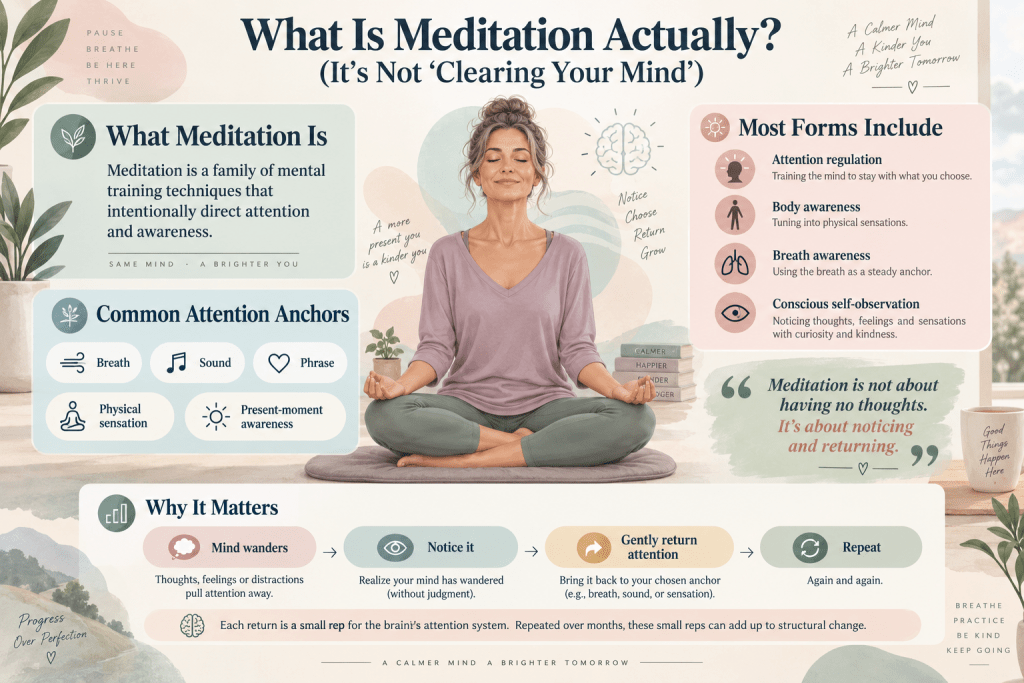
Meditation attention and awareness infographic

Rather than letting the mind drift unchecked from thought to thought, meditation repeatedly guides attention back to a chosen anchor, whether that’s the breath, a sound, a phrase, a physical sensation, or simple present-moment awareness.

That return, noticing the mind has wandered and gently redirecting it, sounds almost too simple to matter. Neurologically, it’s the entire mechanism. Every single redirection is a small rep for the brain’s attention system, and small reps, repeated over months, add up to structural change.

“The number one thing I tell clients starting a meditation practice is that the wandering mind isn’t the failure. The wandering mind is the exercise. Every time you notice you’ve drifted and bring yourself back, that’s the rep. People quit because they think they’re bad at it, when actually the noticing is the entire point.”

Terry Tateossian, Founder of The House of Rose

What Are the Main Types of Meditation, and What Does Each One Train?

Meditation isn’t one single technique, and different forms recruit overlapping but distinct brain circuits.

  • Focused attention meditation: Anchors attention to a single object, such as the breath, a candle flame, or a repeated word. When the mind drifts, attention is gently returned. This form builds sustained attention and executive control most directly.
  • Open monitoring, or mindfulness meditation: Widens awareness to observe thoughts, emotions, and sensations without judging or reacting to them, rather than narrowing focus onto one object.
  • Loving-kindness and compassion practices: Deliberately generate feelings of warmth toward oneself and others, and appear to strengthen circuits involved in empathy and emotional regulation.
  • Mantra meditation: Repeats a sound or phrase, using rhythm to quiet spontaneous mental chatter and build attentional stability. THOR covers this specific practice in depth in the Aham Mantra and Sanskrit Mantras Guide, including how to select and work with a mantra.
  • Body scan meditation: Systematically moves awareness through different regions of the body, building interoception and autonomic self-regulation.
  • Walking meditation: Pairs movement with present-moment awareness, engaging motor control, balance, and attention simultaneously.

It’s tempting to treat “meditation” as one interchangeable activity, but a woman using focused-attention practice to sharpen concentration before a demanding workday is training a different circuit than a woman using loving-kindness practice to soften self-criticism after a hard year. Matching the technique to the goal, attention, emotional regulation, or self-compassion, produces faster, more noticeable results than picking a technique at random.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Is the History of Meditation as Humanity’s Oldest Mental Training?

Meditation is among the oldest documented practices for training the mind. Seated figures in postures resembling meditation appear in artifacts from the Indus Valley Civilization dating back more than 4,000 years, though their precise purpose remains debated among historians.

The earliest widely accepted written references to contemplative discipline appear in the Rig Veda, composed roughly 1500 to 1200 BCE, which introduces ideas of focused attention, sacred chanting, and inner concentration that later traditions would build on directly.

Several centuries later, the Upanishads (roughly 800 to 300 BCE) shifted the emphasis from external ritual toward internal exploration of consciousness, describing structured stages including breath regulation, sensory withdrawal, concentration, meditation, and deep absorption.

Patanjali’s Yoga Sutras, compiled sometime between 200 BCE and 400 CE, organized centuries of existing contemplative knowledge into the Eight Limbs of Yoga, with meditation positioned as the second-to-last stage before complete absorption.

Around the same era, Siddhartha Gautama refined existing contemplative techniques into what became Buddhist mindfulness and insight meditation, built around present-moment awareness and non-judgmental observation.

Independently, early Daoist traditions in China developed their own breath and internal-awareness practices. Different cultures, working independently, arrived at a shared conclusion: repeated attention training reshapes the mind. Modern neuroscience is now confirming, with brain imaging rather than philosophy, that they were onto something real.

What Happens in the Brain During Meditation?

One of the most consistent findings across meditation neuroscience is that practice changes communication between large-scale brain networks, not just activity in a single region.
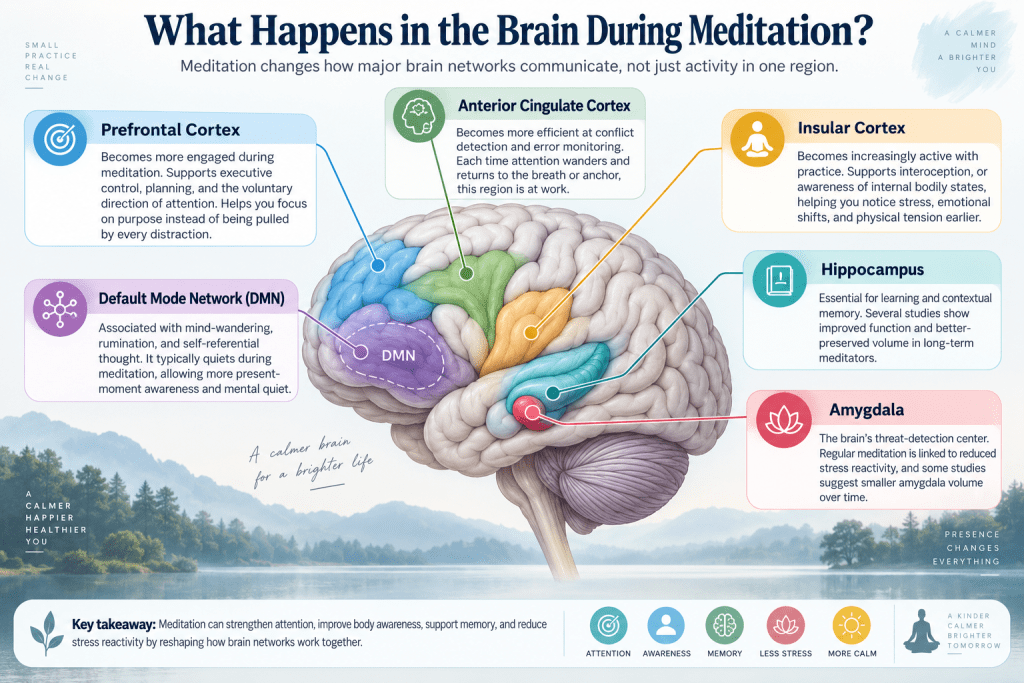
Brain changes during meditation infographic
  • The prefrontal cortex: Becomes more engaged during meditation, supporting executive control, planning, and voluntary direction of attention. Instead of every thought or distraction automatically capturing focus, the frontal lobes become better able to direct awareness on purpose.
  • The anterior cingulate cortex: Detects conflict and monitors errors and becomes more efficient. Each time attention wanders and gets redirected back to the breath or anchor, this region is doing the work.
  • The insular cortex: Central to interoception (the sense of internal bodily states), becomes increasingly active with practice. Improved interoceptive awareness often means recognizing stress, emotional shifts, or physical tension earlier, before it builds into something overwhelming.
  • The hippocampus: Essential for learning and contextual memory, shows improved function and better-preserved volume in several studies of long-term meditators, a finding with direct relevance for women managing the memory and word-retrieval changes common in perimenopause.
  • The amygdala: The brain’s threat-detection center responsible for fear and stress reactivity, shows reduced activation during stressful situations among regular meditators, and some studies report smaller amygdala volume with sustained practice, suggesting genuine remodeling of stress circuitry over time.
  • The default mode network (DMN): The system active during mind-wandering, rumination, and self-referential thought, typically quiets down during meditation. Instead of looping through repetitive internal narratives, the brain shifts toward processing present-moment information, which is what most people describe as “mental quiet.”

Important: None of these changes happen after a single session. They reflect the cumulative effect of consistent practice over weeks and months, the same way a single workout doesn’t build visible muscle but a consistent training block does.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Do EEG Studies Show About Brain Waves During Meditation?

Electroencephalography (EEG) studies show that meditation shifts brain wave activity, though the specific pattern depends on the technique and the practitioner’s experience level.

  • Alpha wave activity: Tends to increase, reflecting relaxed wakefulness and reduced sensory interference.
  • Theta wave activity: Often rises during deeper meditative states, associated with internal attention, memory processing, and emotional integration.
  • Gamma wave synchrony: Highly experienced practitioners have shown increases in gamma wave synchrony, linked to conscious awareness and large-scale coordination across cortical regions.

The takeaway is that meditation isn’t a passive dip in brain activity. It’s an organized shift toward more efficient, more coordinated neural processing, closer to focused training than to rest.

What Changes After Years of Meditation Practice?

The most striking findings come from studies comparing long-term meditators to non-meditators. Consistent practitioners often show increased cortical thickness in regions tied to attention, emotional regulation, and self-awareness, including the prefrontal cortex, anterior cingulate cortex, and insula. White matter connectivity, the wiring between distant brain regions, often appears stronger too, suggesting faster and more coordinated communication across the brain.

These differences reflect years of repeated practice, not a single session. The same way physical training gradually reshapes skeletal muscle, meditation appears to progressively reshape the neural networks responsible for attention and emotional regulation.

What a realistic timeline looks like:

Practice Stage Typical Duration What Tends to Change First
Weeks 1-4 Daily 5-10 min sessions Noticing the wandering mind faster; small shifts in reactivity
Months 2-4 Consistent daily practice Easier return to focus; reduced rumination in daily life
Months 6-12 Sustained regular practice Measurable stress-reactivity changes; better sleep onset
Year 1+ Long-term consistent practice Structural changes documented in research (cortical thickness, connectivity)

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Does Meditation Affect the Autonomic Nervous System?

Meditation influences the autonomic nervous system directly, generally shifting the balance toward increased parasympathetic activity through improved vagal tone. Heart rate frequently decreases, breathing slows, heart rate variability often improves, and stress hormone output may decline with consistent practice.
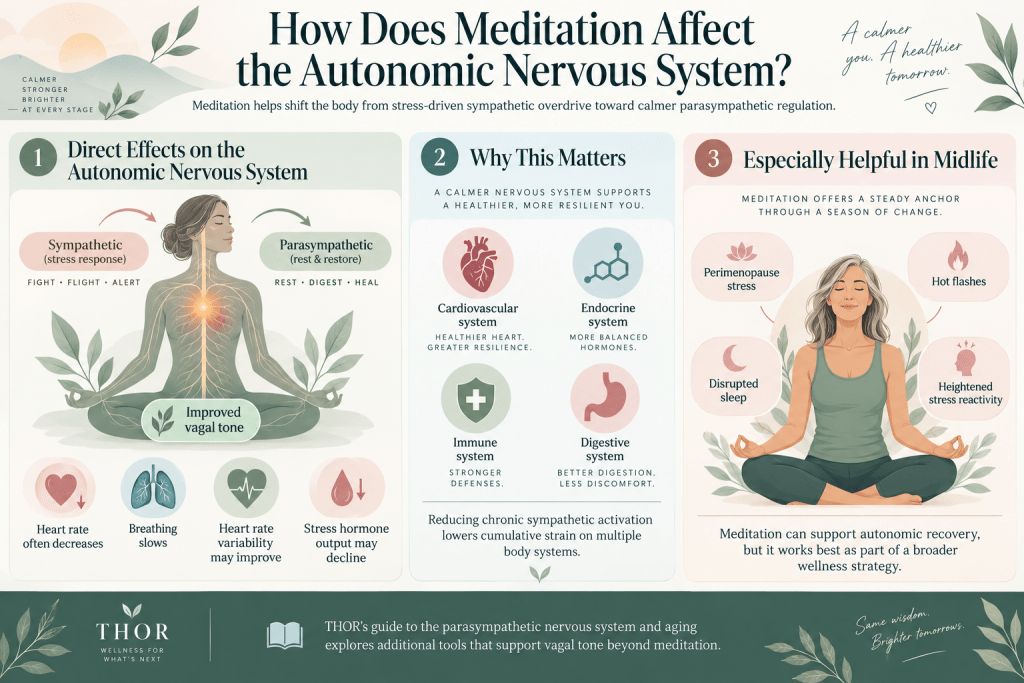
Meditation effects on the autonomic nervous system.

Lowering chronic sympathetic activation reduces the cumulative strain placed on the cardiovascular, endocrine, immune, and digestive systems. For women dealing with the sympathetic overdrive that often accompanies perimenopause, hot flashes, disrupted sleep, and heightened stress reactivity among them, meditation functions as one piece of a broader autonomic recovery strategy rather than a stand-alone fix.

THOR’s guide to the parasympathetic nervous system and aging covers this autonomic balance in more depth, including other tools beyond meditation that support vagal tone.

Why Does Meditation Matter More in Perimenopause and Menopause?

Estrogen has a direct relationship with several of the same brain regions meditation appears to influence, particularly the prefrontal cortex, hippocampus, and amygdala. As estrogen fluctuates and then declines through the menopause transition, many women notice exactly the symptoms tied to these regions: harder-to-sustain focus, more effortful word retrieval, increased emotional reactivity, and a startle-prone or hypervigilant stress response that wasn’t there a decade earlier.

This is part of why the timing matters. A woman navigating perimenopausal brain fog is dealing with a nervous system that’s already working harder to do what it used to do more easily. Meditation doesn’t reverse hormonal change, but it trains the exact systems, attention regulation, stress reactivity, emotional control, that hormonal shifts are placing under extra load. That overlap is why this deserves more attention in midlife wellness content than it typically gets.

“I was diagnosed with early-onset menopause at 41, and the brain fog was the symptom that scared me most, more than the hot flashes, more than the sleep disruption. Meditation didn’t erase it, but it gave me back a sense that my attention was something I could still direct on purpose, even on the days my hormones weren’t cooperating. That’s not a small thing when you’re running a company and raising two kids.”

Terry Tateossian, Founder of The House of Rose

For women managing cortisol-driven symptoms alongside cognitive changes, THOR’s 7 Tiny Stress Habits for Midlife Women pairs well with a meditation practice as a set of smaller, situational tools for the moments a full sit-down session isn’t practical.

What Does the Research Support, and Where Is the Evidence Still Early?

Because meditation trains attention and emotional regulation circuits, it has shown measurable benefit across a range of conditions. The strongest evidence currently exists for stress-related disorders, generalized anxiety, recurrent depression, chronic pain, insomnia, elevated blood pressure, and burnout.

Meditation has also shown benefit for emotional resilience in post-traumatic stress disorder when introduced carefully under professional guidance, though intensive practice can temporarily worsen symptoms in some trauma survivors if introduced too aggressively without support.

In chronic pain, benefit tends to come less from reducing pain signals directly and more from changing how the brain interprets and emotionally reacts to those signals. Mindfulness-based approaches have also shown benefit for irritable bowel syndrome, fibromyalgia, migraine, and quality of life during cancer treatment.

Research into meditation as a complementary approach for mild cognitive changes, attention difficulties, and general midlife cognitive resilience is newer and still developing, but the underlying neurological rationale, that meditation strengthens attention, autonomic regulation, and stress resilience, is well established even where the specific downstream applications are still being studied.

Important: Meditation is a complement to appropriate medical care, not a replacement for it, particularly for diagnosed anxiety, depression, or chronic pain conditions that warrant professional treatment.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Why Isn’t Meditation One-Size-Fits-All?

Meditation is safe for most people, but it isn’t universally appropriate in the same form for everyone. Women with significant trauma histories, dissociative symptoms, or certain psychiatric conditions may need a modified approach under professional supervision, since prolonged silent sitting can occasionally surface uncomfortable material before it resolves into benefit.
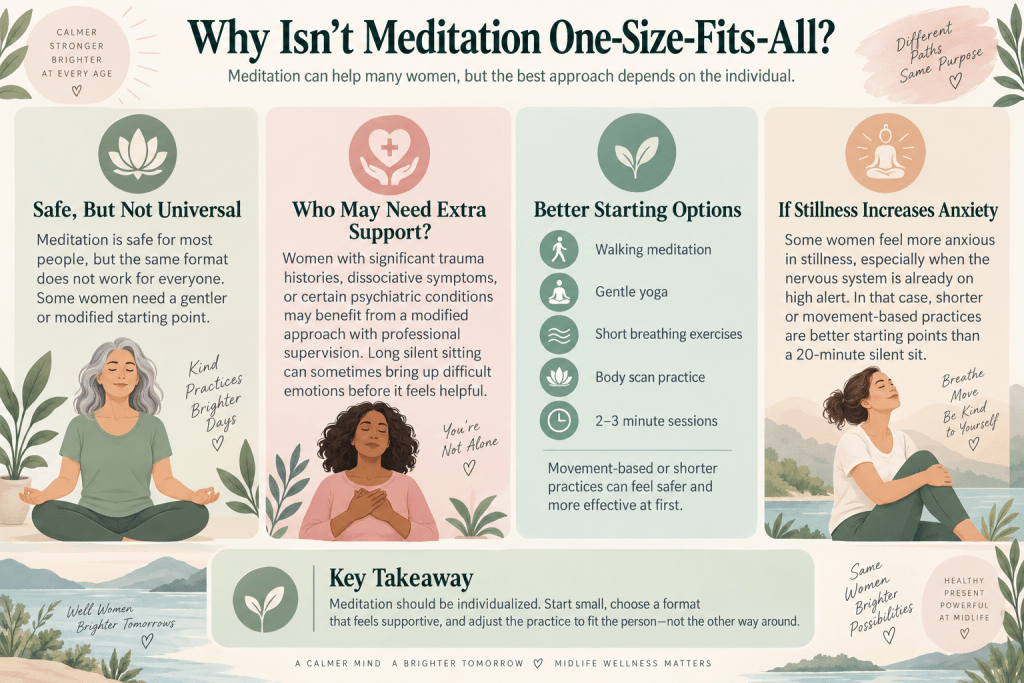
Meditation options for different needs

Some people do better starting with movement-based practices, like walking meditation or gentle yoga, or short breathing exercises rather than long silent sessions. Just as an exercise plan should be individualized to the person, a meditation practice should be matched to the individual too, rather than assuming one format fits everyone.

Some women find that sitting in stillness actually increases anxiety rather than easing it, at least at first, especially if the nervous system is already in a heightened state. If that’s your experience, walking meditation, body scan practice, or shorter 2 to 3 minute sessions are more effective starting points than a 20-minute silent sit. THOR’s guide on nervous system regulation when stillness makes it worse covers this exact situation and eighteen alternative tools in depth.

What Are Your Next Steps?

  1. Start with 5 minutes of focused-attention meditation daily for two weeks before judging whether it’s “working.”
  2. If sitting still increases anxiety, try walking meditation or a body scan instead of a longer silent sit.
  3. Pair meditation with THOR’s 7 Tiny Stress Habits for Midlife Women for situational tools between sessions.
  4. If mantra-based practice appeals to you, review THOR’s Aham Mantra and Sanskrit Mantras Guide for a specific starting technique.
  5. Track your protein and overall nutrition alongside a meditation practice using THOR’s free macro calculator, since sleep, stress, and nutrition all interact with the same nervous system this article covers.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

Does meditation really change brain structure, or is that overstated?

Structural changes, including cortical thickness and white matter connectivity, have been documented in multiple studies of long-term meditators using MRI, though these changes reflect months to years of consistent practice rather than a few sessions.

How long before I’d notice any difference?

Many people notice small shifts in stress reactivity and attention within a few weeks of consistent daily practice, while more substantial changes, including structural brain differences, are typically studied over 8 weeks to several years of practice.

Is 5 minutes a day actually enough to matter?

Short, consistent sessions are generally more effective than occasional long sessions. Five to ten minutes daily builds the habit and the underlying attention circuit more reliably than an hour once a week.

What’s the difference between meditation and just relaxing?

Relaxation is a state; meditation is a trained skill involving active attention regulation. The two often feel similar in the moment, but meditation involves repeated, intentional redirection of attention, which is the mechanism behind its brain-level effects.

Can meditation help with menopause brain fog specifically?

Meditation trains the same attention and stress-regulation circuits that tend to feel taxed during perimenopause and menopause. It doesn’t reverse hormonal change, but it can support the systems working harder during this transition.

Do I need to sit cross-legged on the floor to meditate correctly?

No. Posture matters less than consistency. Sitting in a chair, lying down (if it doesn’t induce sleep), or even walking meditation are all valid formats.

What if my mind wanders the entire time?

That’s normal and, as covered above, is actually the mechanism of the practice rather than a sign of failure. Every redirection back to the anchor is the “rep” that builds the underlying attention circuit.

Is mindfulness meditation the same as focused attention meditation?

No. Mindfulness (open monitoring) involves broad, non-judgmental awareness of whatever arises, while focused attention narrows in on one specific anchor point. Both train related but distinct circuits.

Can meditation replace anti-anxiety medication?

No. Meditation is a complementary tool with real evidence behind it, but decisions about medication should be made with a physician or psychiatrist, not replaced by a meditation practice alone.

Does the type of meditation app or teacher matter?

Less than consistency does. A basic free app used daily will build the underlying skill more effectively than an expensive program used sporadically.

Is it too late to start meditating in my 50s or 60s?

No. Research on meditation training in older adults, including women well into midlife and beyond, shows measurable benefits to attention and stress regulation regardless of when practice begins.

How does meditation affect sleep specifically?

By increasing parasympathetic activity and lowering physiological arousal before bed, meditation can support easier sleep onset, which is particularly relevant for women experiencing menopause-related sleep disruption.

Can meditation make anxiety worse for some people?

In rare cases, particularly with unresolved trauma or certain psychiatric conditions, intensive silent meditation can temporarily increase distress. Shorter sessions, movement-based practice, or professional guidance can help work through this.

What’s the single most important factor for meditation to actually work?

Consistency. The research behind every brain change described in this article reflects regular, sustained practice, not occasional or one-off sessions.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.

References

  • Brewer, J. A., Worhunsky, P. D., Gray, J. R., Tang, Y. Y., Weber, J., & Kober, H. (2011). Meditation experience is associated with differences in default mode network activity and connectivity. Proceedings of the National Academy of Sciences, 108(50), 20254-20259.
  • Davidson, R. J., & McEwen, B. S. (2012). Social influences on neuroplasticity: Stress and interventions to promote well-being. Nature Neuroscience, 15(5), 689-695.
  • Fox, K. C. R., et al. (2014). Is meditation associated with altered brain structure? A systematic review and meta-analysis of morphometric neuroimaging in meditation practitioners. Neuroscience & Biobehavioral Reviews, 43, 48-73.
  • Goyal, M., et al. (2014). Meditation programs for psychological stress and well-being: A systematic review and meta-analysis. JAMA Internal Medicine, 174(3), 357-368.
  • Hölzel, B. K., et al. (2011). Mindfulness practice leads to increases in regional brain gray matter density. Psychiatry Research: Neuroimaging, 191(1), 36-43.
  • Lutz, A., Slagter, H. A., Dunne, J. D., & Davidson, R. J. (2008). Attention regulation and monitoring in meditation. Trends in Cognitive Sciences, 12(4), 163-169.
  • Tang, Y. Y., Hölzel, B. K., & Posner, M. I. (2015). The neuroscience of mindfulness meditation. Nature Reviews Neuroscience, 16(4), 213-225.
  • Travis, F., & Shear, J. (2010). Focused attention, open monitoring and automatic self-transcending: Categories to organize meditations from Vedic, Buddhist and Chinese traditions. Consciousness and Cognition, 19(4), 1110-1118.
  • Vago, D. R., & Silbersweig, D. A. (2012). Self-awareness, self-regulation, and self-transcendence: A neurobiological model of the mechanisms of mindfulness. Annals of the New York Academy of Sciences, 1262(1), 1-35.
  • Young, K. S., et al. (2018). The impact of mindfulness-based interventions on brain activity: A systematic review of functional magnetic resonance imaging studies. Neuroscience & Biobehavioral Reviews, 84, 424-433.
  • National Institute of Mental Health patient education materials on mindfulness and anxiety disorders.
  • Mayo Clinic patient education materials on meditation, stress reduction, and mind-body practices.
  • Cleveland Clinic patient education materials on meditation and the nervous system.
  • American Psychological Association resources on estrogen, cognition, and the menopause transition.
  • North American Menopause Society clinical guidance on cognitive changes during perimenopause and menopause.

Disclaimer: This article is educational and does not constitute medical or mental health advice. Meditation can support attention, stress regulation, sleep, and emotional well-being, but it is not a substitute for medical or psychiatric treatment. If you have a history of significant trauma, dissociation, severe anxiety, depression, or another psychiatric condition, consult a qualified healthcare or mental health professional before beginning an intensive meditation practice.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How to Increase Bone Density After 40: 6 Exercises That Work (Videos)

Denise’s mother broke her hip getting out of a bathtub. No stairs. No major fall. Her foot caught the mat, and at sixty-eight, an emergency-room X-ray revealed bone loss that had been progressing quietly for years.

Denise is fifty-one now, and her own DEXA scan shows osteopenia at the hip. She was told to do “weight-bearing exercise,” so she started walking more. A good start, but not a complete plan.

Bone is constantly remodeling. During the menopause transition, falling estrogen can allow bone breakdown to outpace bone formation, increasing the importance of exercise that gives the skeleton enough mechanical stimulus to adapt.

And not all movement does that equally. Walking supports cardiovascular health, but on its own, it usually does not provide enough load to meaningfully improve bone density. This guide covers six exercise categories supported by research, how they load bone, and how to progress them safely over time.

Important: This article is educational and does not replace individualized medical advice. Women with osteoporosis, a prior fragility fracture, or significant balance concerns should speak with a physician or physical therapist before starting a new exercise program, especially higher-impact exercise.

Why Doesn’t Walking Alone Build Bone?

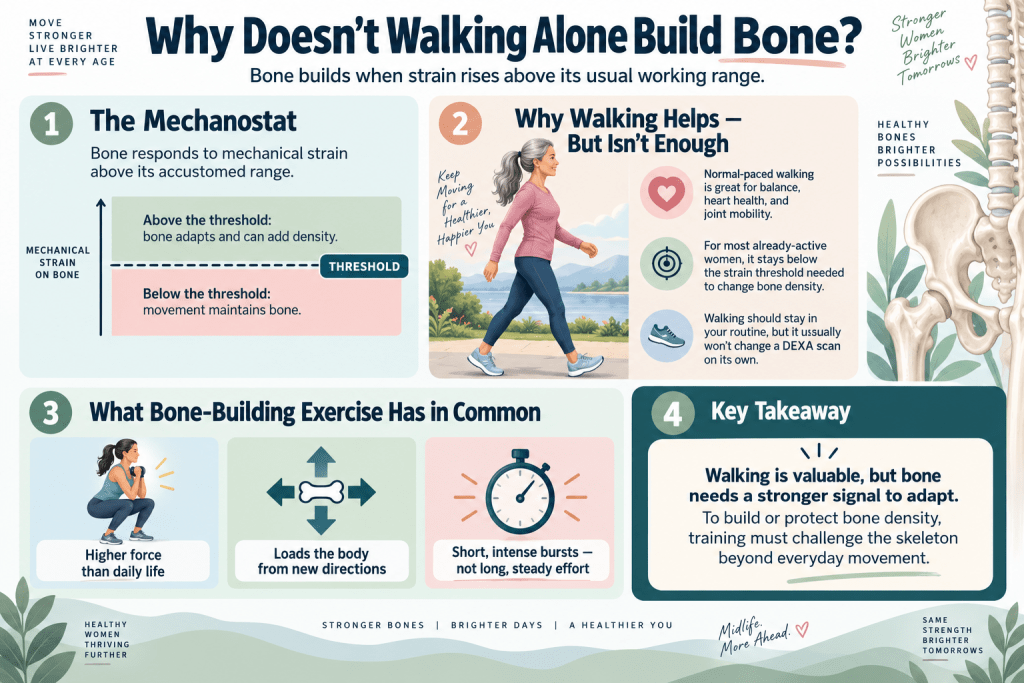
Bone responds to mechanical strain above its accustomed working range, a concept researchers call the mechanostat. Below a certain threshold of strain, a movement maintains bone. Above that threshold, bone adapts by adding density.

Why walking alone doesn’t build bone density

Walking at a normal pace, for most already-active women, sits below that threshold. It’s excellent for balance, cardiovascular health, and joint mobility, and it should stay part of any weekly routine, but it isn’t the lever that changes a DEXA scan on its own.

The exercises that do change bone density share three features: they load the skeleton with more force than daily life requires, they load it from directions the body isn’t used to, and they load it in short, intense bursts rather than long, steady efforts. The six categories below cover all three.

“I hear ‘I already walk 10,000 steps a day, isn’t that enough?’ constantly in coaching sessions. Walking is a wonderful habit and I’ll never discourage it, but if bone density is the specific goal, walking needs a partner, not a replacement. I learned this the hard way managing my own bone health after an early menopause diagnosis at 41. Cardio alone did nothing for my scan. Loading did.”

Terry Tateossian, Founder of The House of Rose

What Are the 6 Best Exercises for Building Stronger Bones After 40?

A complete bone-strengthening routine needs more than walking or light resistance work. These six exercise categories combine impact, progressive resistance, power, loaded movement, balance, and multi-directional loading to challenge the skeleton in different ways while also improving the strength and stability that help reduce fracture risk.

Six bone-strengthening exercises for women over 40

Exercise 1: High-Impact Loading (Jumping and Rebounding)

Why It Works

Ground reaction force, the force that travels back up through the skeleton on landing, is one of the most direct bone-building stimuli available. Jumping and rebounding generate that force in a low-injury-risk way because the landing is absorbed across both legs and, on a rebounder, across a surface with some give.

How to Do It

  • Start with 10-20 small jumps or rebounder bounces, feet staying close to the mat or floor
  • Progress to jumping jacks, higher-amplitude rebounder bounces, or jump rope as tolerance builds
  • Aim for 2-3 sessions per week, 5-10 minutes per session
  • Land softly through the whole foot, not just the toes, to protect the ankles and knees

Research on jump training protocols in postmenopausal women has found measurable hip bone density improvements from as few as 10-20 jumps performed several times per week over multiple months, with minimal injury risk when landings were performed correctly.

Important: Women with a current osteoporosis diagnosis, a recent fracture, or significant knee or hip joint damage should get clearance from a physician before beginning any jumping or rebounding protocol.

For a gradual progression from gentle health bounces to longer rebounder sessions, THOR’s rebounding guide provides a structured starting point for women in midlife.

Why Does the Rebounder Specifically Work for Sensitive Joints?

A mini trampoline absorbs a portion of the landing force before it reaches the joints, which lowers impact on the knees and hips relative to jumping on a hard floor while still generating enough ground reaction force to register as a bone-loading stimulus. This makes it a reasonable starting point for women who want the impact-loading benefit without the joint stress of running or floor-based jumping.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Exercise 2: Heavy Progressive Resistance Training

Why It Works

Muscle attaches to bone through tendon, and every contraction pulls on that attachment point. Heavier loads recruit more muscle fibers and pull harder on bone, which is why resistance training with real, progressively increasing weight outperforms light-weight, high-repetition training for bone density specifically.

How to Do It

  • Focus on compound, multi-joint movements: squats, deadlift patterns, rows, presses
  • Work in the 6-10 repetition range with a weight that feels truly challenging by the last 2 reps
  • Progress load every 2-3 weeks as the current weight starts to feel easier
  • Train 2-3 times per week, allowing 48 hours between sessions for the same muscle groups

A weight that feels “fine” for 15 easy repetitions isn’t doing the same job on bone as a weight that makes rep 8 hard. This is one of the most common mistakes in home workout routines: not lifting heavy enough to register as a novel stimulus.

Creatine monohydrate can help support the strength and training adaptations that make resistance exercise more effective, indirectly strengthening the bone-loading side of the equation.

For a deeper look at the research, dosing, and midlife-specific benefits, THOR’s guide to creatine for women over 40 breaks down the evidence, while Thorne Creatine provides a straightforward creatine monohydrate option for adding it to your daily routine.

Worked Example: Choosing a Starting Weight

Woman

Current Fitness

Starting Squat Load

Target Rep Range

New to resistance training

Never lifted weights

Bodyweight or empty barbell (bar only)

8-10 reps, focus on form

Some experience

Lifts occasionally, unsure of loads

Weight that feels moderate for 12 reps

8-10 reps, add 5 lbs when easy

Regular lifter

Trains 2x/week already

Weight that’s truly hard by rep 8

6-8 reps, progressive overload

Load Approach

Typical Rep Range

Bone-Building Signal

Light resistance bands, high reps

15-25 reps

Low, insufficient mechanical strain

Moderate dumbbells, muscle endurance focus

12-15 reps

Low to moderate

Heavy compound lifts, progressive overload

6-10 reps

High, this is the target zone

Bodyweight only, no added load

Varies

Low unless combined with impact or power work

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Exercise 3: Power-Based Training (Speed of Force)

Why It Works

Power, defined as force produced quickly rather than slowly, appears to matter for bone and for fall prevention in a way that slow strength training alone doesn’t fully replicate. Moving a weight or your own bodyweight explosively, even a small amount of weight, creates a different rate of loading on bone than moving it slowly.

How to Do It

  • Sit-to-stand transfers: Perform as quickly as control allows, 3 sets of 8-10.
  • Step-ups: Perform with an explosive push off the working leg, 3 sets of 8 per side.
  • Medicine ball chest passes: Perform against a wall, 3 sets of 10, focusing on speed of release.
  • Begin with bodyweight versions: Progress to external load once control and technique are established.

This category is frequently skipped entirely in midlife fitness routines because it looks less like traditional “toning” work, but the missing piece is often speed, not weight.

Understanding the difference between power and strength helps explain why lifting heavier is only part of the equation. Power training focuses on producing force quickly, which supports faster reactions, more responsive movement, and the ability to recover from an unexpected stumble.

“Clients are often surprised that ‘explosive’ doesn’t mean advanced or dangerous. A sit-to-stand performed a little faster than usual, with good form, is a completely appropriate starting point. I’ve coached hundreds of women through this exact progression, and the ones who stick with power work are almost always the ones who feel steadiest walking down stairs a few months later.”

Terry Tateossian, Founder of The House of Rose

Exercise 4: Axial Loading (Carries and Loaded Walking)

Why It Works

Carrying weight while walking loads the spine and hips through a vertical, compressive path, which is exactly the direction hip and spine fractures tend to occur from bone weakness. This category is under-used in most fitness programming despite being simple to add to an existing walking habit.

How to Do It

  • Farmer’s carries: Hold a moderately heavy dumbbell or kettlebell in each hand, walk 30-40 steps, rest, and repeat for 3-4 rounds.
  • Weighted vest walking: Start with 5-10% of bodyweight added and walk your normal route.
  • Single-arm suitcase carries: Use these to add a rotational stability demand.
  • Progress load gradually: Increase the load the same way as any resistance exercise.

Worked Example

A 150-pound woman starting weighted vest walking might begin with a 10-12 pound vest for two 20-minute walks per week, adding roughly 2-3 pounds every few weeks as the current load stops feeling challenging by the walk’s second half.

Bodyweight

Starting Vest Load (5-8%)

Progression Pace

130 lbs

7-10 lbs

+2 lbs every 3-4 weeks

150 lbs

8-12 lbs

+2-3 lbs every 3-4 weeks

170 lbs

9-14 lbs

+3 lbs every 3-4 weeks

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Exercise 5: Balance and Fall-Prevention Training

Why It Works

Bone density is only half of fracture risk. The other half is whether a fall happens at all. Balance training doesn’t build bone directly, but it reduces the single largest risk factor for the fractures that bone density work is trying to prevent, which makes it inseparable from a real bone health plan.

How to Do It

  • Single-leg stance: Work toward 30 seconds per side without support.
  • Tandem walking: Walk heel-to-toe across a room for 3-4 passes.
  • Standing on an unstable surface: Use a folded towel or balance pad while holding light support.
  • Practice near a counter or wall: Use nearby support for safety as difficulty increases.

THOR has a full testing and improvement protocol at Single-Leg Stance Test for Women Over 40, including how to track progress over time.

Why Does Balance Training Belong in a Bone Density Article?

It’s tempting to treat balance work as a separate category from “real” bone-building exercise, but the research on fracture prevention treats fall risk and bone strength as two sides of the same equation. A woman with excellent bone density who falls hard still fractures. A woman with lower bone density who never falls often doesn’t. Both matter, and neither replaces the other.

Exercise 6: Multi-Directional Loading

Why It Works

Most daily movement and most traditional exercise happens in a single plane, forward and back. Bone that’s only ever loaded in one direction adapts to that one direction and stays vulnerable to forces from the side, which is how many hip fractures actually happen, from a sideways stumble rather than a forward fall.

How to Do It

  • Lateral lunges: Perform 2-3 sets of 8-10 per side.
  • Diagonal step-and-reach patterns: Step at a 45-degree angle while reaching the opposite arm.
  • Side-stepping with a resistance band: Place the band around the ankles and perform 2-3 sets of 10 steps in each direction.
  • Curtsy lunges: Add these once basic lateral lunges feel controlled.

Muscle groups that support these multi-directional movements, particularly the hip abductors and rotators, are covered in Muscles That Matter Most for Aging Well.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

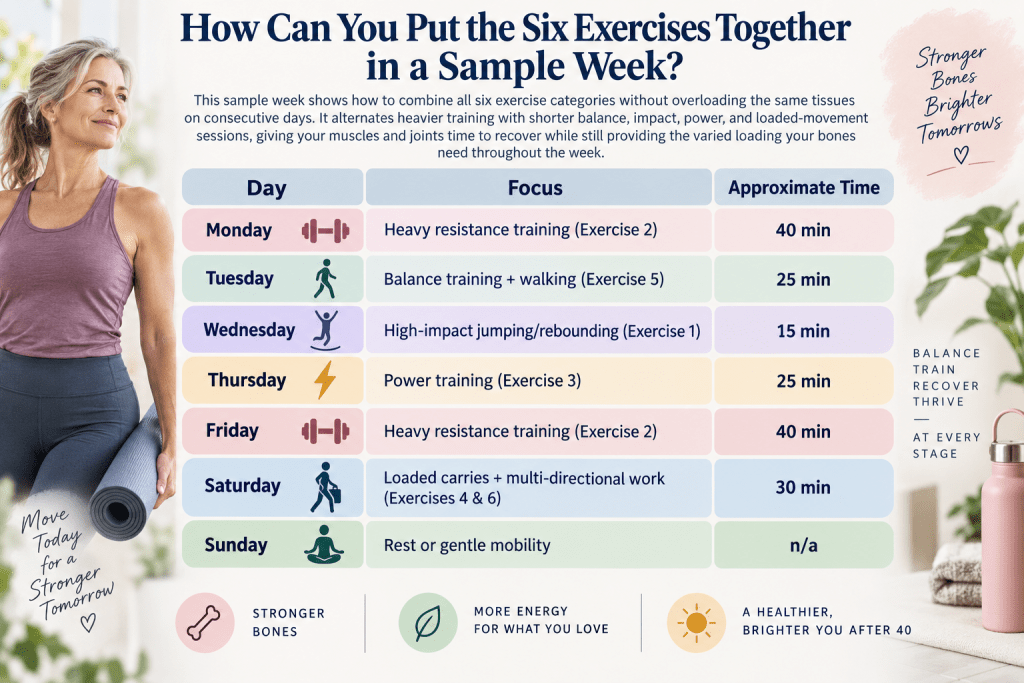
How Can You Put the Six Exercises Together in a Sample Week?

This sample week shows how to combine all six exercise categories without overloading the same tissues on consecutive days. It alternates heavier training with shorter balance, impact, power, and loaded-movement sessions, giving your muscles and joints time to recover while still providing the varied loading your bones need throughout the week.

Weekly bone-strength exercise plan for women over 40.

Day

Focus

Approximate Time

Monday

Heavy resistance training (Exercise 2)

40 min

Tuesday

Balance training + walking (Exercise 5)

25 min

Wednesday

High-impact jumping/rebounding (Exercise 1)

15 min

Thursday

Power training (Exercise 3)

25 min

Friday

Heavy resistance training (Exercise 2)

40 min

Saturday

Loaded carries + multi-directional work (Exercises 4 & 6)

30 min

Sunday

Rest or gentle mobility

n/a

This isn’t the only way to sequence these six categories, but it spaces heavy resistance days 48 hours apart and keeps impact work to days when joints feel fresh.

“I tell clients to think of this as a rotation, not a checklist to finish in one workout. Two categories done well on a given day beats all six done poorly. That’s the same principle I build every retreat program around at our Smoky Mountain property: fewer things, done with real intent, beats a packed schedule nobody can sustain once they go home.”

Terry Tateossian, Founder of The House of Rose

What Does the Research Actually Show?

Bone density research in midlife and postmenopausal women consistently points toward a few conclusions worth stating plainly, without overselling them:

  • Multi-component programs: Combining resistance training, impact loading, and balance work shows more consistent bone density benefits at the hip and spine than any single exercise type alone.
  • Loss rates during the menopause transition: These are real and measurable, but exercise-based interventions have shown the ability to slow that loss and, in some studies, modestly increase density at specific sites, particularly the hip.
  • Consistency over months and years: This matters more than any single “best” exercise. Bone remodeling is slow, and meaningful DEXA-detectable change typically takes 6-12 months of consistent training, not weeks.
  • Exercise does not replace medical evaluation: For women already diagnosed with osteoporosis, it’s a complement to, not a substitute for, whatever a physician recommends based on individual fracture risk and bone density scores.

Nutrition also plays a supporting role alongside training. Adequate protein intake supports the muscle side of the muscle-bone connection, and THOR’s free macro calculator can help set a personalized protein target to train against.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
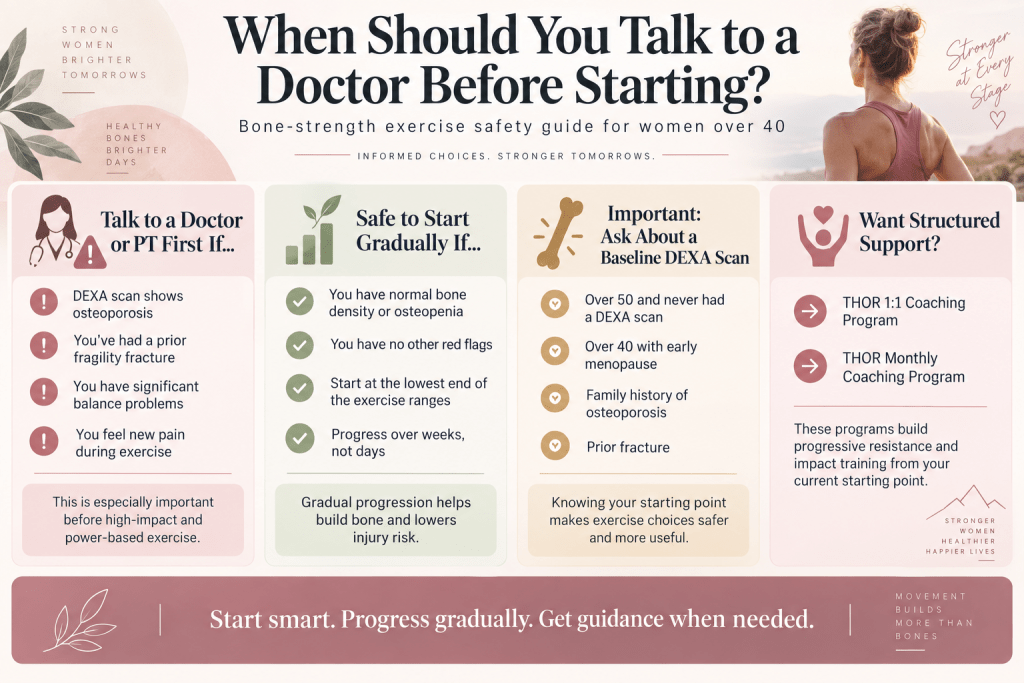
When Should You Talk to a Doctor Before Starting?

A DEXA scan showing osteoporosis, a prior fragility fracture, significant balance problems, or any new pain during exercise are all reasons to loop in a physician or physical therapist before starting a program like this one, particularly the high-impact and power categories.

When to see a doctor before bone exercise

For women with normal bone density or osteopenia and no other red flags, these categories are generally considered safe to begin gradually, but “gradually” is doing real work in that sentence. Starting at the lowest end of any of the ranges above and progressing over weeks, not days, is the difference between building bone and getting hurt.

Important: If you have never had a DEXA scan and are over 50, or over 40 with early menopause, a family history of osteoporosis, or a prior fracture, ask your doctor whether a baseline scan makes sense before starting a new training program. Knowing your starting point makes every exercise choice in this article more useful.

What Are Your Next Steps?

  1. If you’re over 50, or over 40 with early menopause or a family history of osteoporosis, ask your doctor about a baseline DEXA scan before starting.
  2. Pick two of the six exercise categories to start with this week, ideally one resistance-based and one impact or balance-based.
  3. Use THOR’s free macro calculator to set a protein target that supports the muscle-bone connection.
  4. Build toward the sample week above over 4-6 weeks, adding one category at a time rather than all six at once.
  5. Revisit this article every few months to check your progression against the load and rep ranges listed for each exercise.

Building bone density is not a single workout, it’s a rotation practiced consistently over months. For a done-for-you approach to structuring these six categories into a weekly plan tailored to your current fitness level, THOR’s 1:1 coaching program builds progressive resistance and impact training safely from wherever you’re starting.

Supporting nutrients for bone health, including calcium, vitamin D, and vitamin K2, are covered in THOR’s Advanced Bone Support formula, and pairing a training plan with real food is easiest with THOR’s Macro Miracle Mediterranean Cookbook, which was built around the same protein-forward approach this article recommends.

If you’re weighing a longer-term reset, THOR’s women’s yoga retreats build guided strength and movement programming, including several of the six categories above, into a supported week away.

Important: This article is educational and does not replace individualized medical advice. Please consult a physician before beginning a new exercise program, especially if you have an existing bone density diagnosis, a prior fracture, or a cardiovascular or joint condition.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Frequently Asked Questions

Can you really increase bone density after 40, or only slow the loss?

Both are possible, though slowing loss is the more common and more reliably documented outcome. Increases in bone density have been shown in research at specific sites, most consistently the hip, with consistent multi-component training over 6-12 months or longer.

Is rebounding as good as running for bone density?

Rebounding provides meaningful ground reaction force with lower impact on the joints than running on pavement, making it a reasonable substitute for women with joint concerns. Running on a hard surface may provide a stronger stimulus for some, but the injury tradeoff should factor into the decision.

How long before I’d see a difference on a DEXA scan?

Most research protocols run 6-12 months before rescanning, since bone remodeling is a slow process. A single month of consistent training won’t show up on a scan, but it’s still the month that starts the process.

Do I need weights, or can bodyweight exercises build bone density?

Bodyweight exercise can work for the impact and power categories (jumping, sit-to-stand speed work), but the heavy resistance category generally requires external load, since bodyweight alone stops providing a new stimulus once a woman is already strong enough to perform the movement easily.

Is walking with a weighted vest enough on its own?

It’s a strong addition to a walking habit and covers the axial loading category well, but it works best alongside resistance training and impact work rather than as a complete stand-alone bone density program.

What’s the difference between osteopenia and osteoporosis?

Osteopenia is a bone density measurement lower than normal but not low enough to meet the diagnostic threshold for osteoporosis. It’s often described as an early warning stage where lifestyle intervention, including the exercises in this article, has the most opportunity to change the trajectory before density drops further.

Can I do these exercises if I already have osteoporosis?

Some can be adapted, but high-impact jumping and certain power movements may need modification or physician clearance first, particularly if there’s been a prior fragility fracture. A physical therapist familiar with osteoporosis exercise guidelines can help tailor the six categories safely.

Does menopause hormone therapy affect how much exercise helps?

Hormone therapy addresses the estrogen side of bone loss directly, while exercise addresses the mechanical loading side. The two work through different pathways and are generally considered complementary rather than substitutes for one another, though any decision about hormone therapy should be made with a physician.

How many days a week is realistic for a beginner?

Three focused sessions a week, combining one resistance day, one impact or power day, and one balance-focused day, is a reasonable and sustainable starting point for someone new to structured bone-loading exercise.

Is it too late to start if I’m already in my sixties or seventies?

No. Research on exercise interventions in older postmenopausal women, including women in their seventies, has shown bone and fall-risk benefits from starting a structured program, though starting loads and progression pace should be more conservative and ideally supervised.

Do I need special equipment to get started?

A rebounder, a pair of moderate dumbbells, and a resistance band cover most of the six categories. None of it requires a full home gym, though a gym membership with access to a squat rack and heavier dumbbells allows more progression room over time.

What role does protein play in bone density specifically?

Protein supports the muscle mass that pulls on and loads bone during resistance and power training, making adequate intake a supporting factor rather than a direct bone-building mechanism on its own. THOR’s free macro calculator can help set a personalized target.

Should I do cardio at all if I’m focused on bone density?

Cardiovascular exercise remains important for heart health and should stay in a weekly routine, but it should sit alongside, not instead of, the six loading categories in this article if bone density is a specific goal.

Can supplements replace exercise for bone density?

No. Supplements such as calcium, vitamin D, and vitamin K2 support the raw materials bone needs to remodel, but without a mechanical loading stimulus from exercise, those raw materials have less signal telling the body where to direct them.

References

  • Finkelstein, J.S., et al. “Bone mineral density changes during the menopause transition in a multiethnic cohort of women.” Journal of Clinical Endocrinology & Metabolism.
  • Frost, H.M. “Bone’s mechanostat: a 2003 update.” The Anatomical Record.
  • Bailey, C.A., & Brooke-Wavell, K. “Optimum frequency of exercise for bone health: randomised controlled trial of a high-impact unilateral intervention.” Bone.
  • Multicomponent exercise interventions and bone mineral density outcomes in postmenopausal women, systematic review data.
  • Watson, S.L., et al. “High-intensity resistance and impact training improves bone mineral density and physical function in postmenopausal women with osteopenia and osteoporosis: the LIFTMOR randomized controlled trial.” Journal of Bone and Mineral Research.
  • Power training versus traditional strength training outcomes in fall risk and functional performance in older adults, comparative training studies.
  • Farmer’s carry and axial loading biomechanics research on spinal and hip compressive load patterns.
  • Sherrington, C., et al. “Exercise for preventing falls in older people living in the community.” Cochrane Database of Systematic Reviews.
  • National Osteoporosis Foundation clinician’s guide to prevention and treatment of osteoporosis.
  • Mayo Clinic patient education materials on osteoporosis exercise recommendations and safety guidelines.
  • Cleveland Clinic patient education materials on bone density and weight-bearing exercise.
  • Vainionpää, A., et al. “Effect of impact exercise on bone mineral density in premenopausal women: a 10-year follow-up study.” Osteoporosis International.
  • Beck, B.R., et al. “Exercise and bone health in postmenopausal women.” Journal of Science and Medicine in Sport.
  • Zhao, R., et al. “Efficiency of jumping exercise in improving bone mineral density among premenopausal women: a meta-analysis.” Sports Medicine.
  • Giangregorio, L.M., et al. “Too Fit To Fracture: exercise recommendations for individuals with osteoporosis or osteoporotic vertebral fracture.” Osteoporosis International.
  • National Institute on Aging patient guidance on exercise, balance, and fall prevention in older adults.

Disclaimer: This article is educational and does not constitute medical advice. Bone-loading exercises such as jumping, rebounding, heavy resistance training, power movements, and weighted carries require appropriate progression and may not be suitable for everyone. If you have osteoporosis, osteopenia with additional risk factors, a prior fragility fracture, significant balance problems, cardiovascular or joint conditions, or new pain with exercise, consult a physician or physical therapist before starting the framework in this article.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Get 11 Sample Recipes from Our Bestselling Mediterranean Cookbook. 

Get our 11 Sample Recipes from our Best Selling Mediterranean Protein Friendly Cookbook. These are the most delicious recipes our retreat guests love the most. Easy, simple with few ingredients per meal.  Make delicious heart-friendly and healthy meals you enjoy every day. 

5 Science-Backed Ways to Lose Weight That Don’t End in a Binge, a Plateau, or a Rebound

Almost every weight loss plan runs into the same three walls, in roughly the same order, regardless of which diet a person started with. First, hunger climbs, quietly and then not so quietly, until it starts driving decisions the plan never accounted for.

Then progress stalls, the same eating pattern that produced steady loss for weeks suddenly produces nothing at all, for reasons that feel arbitrary but are not. And eventually, for a large share of people, some or all of the lost weight finds its way back, often with a side of guilt that has nothing to do with what actually happened in the body.

Most weight loss content treats each of these three moments as a personal failure: not enough discipline, not enough willpower, the wrong mindset. That framing gets the story backward.

Hunger climbing, progress stalling, and weight returning are not signs that a plan failed because a person lacked resolve. They are the predictable, well-documented output of specific physiological mechanisms, and each one has a specific, evidence-based countermeasure.

This article walks through five approaches built directly around those three collision points, so that hitting one of them can be treated as expected terrain to work through, not a verdict on your character.

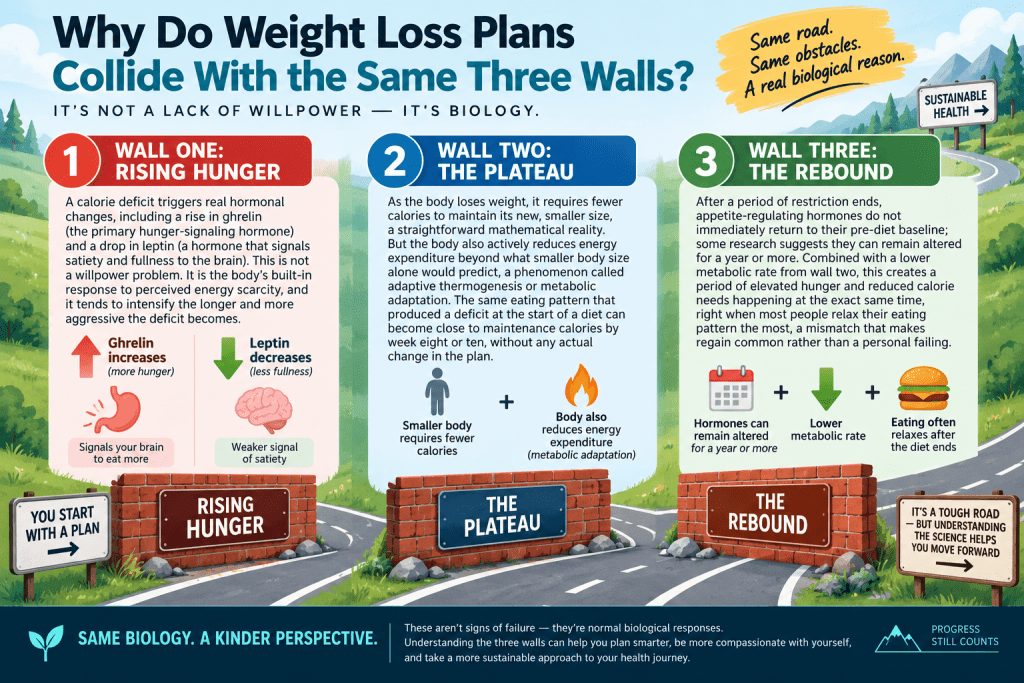
Why Do Weight Loss Plans Collide With the Same Three Walls?

Three common weight loss barriers: hunger, plateau, and rebound.
  • Wall One: Rising Hunger. A calorie deficit triggers real hormonal changes, including a rise in ghrelin (the primary hunger-signaling hormone) and a drop in leptin (a hormone that signals satiety and fullness to the brain). This is not a willpower problem. It is the body’s built-in response to perceived energy scarcity, and it tends to intensify the longer and more aggressive the deficit becomes.
  • Wall Two: The Plateau. As the body loses weight, it requires fewer calories to maintain its new, smaller size, a straightforward mathematical reality. But the body also actively reduces energy expenditure beyond what smaller body size alone would predict, a phenomenon called adaptive thermogenesis or metabolic adaptation. The same eating pattern that produced a deficit at the start of a diet can become close to maintenance calories by week eight or ten, without any actual change in the plan.
  • Wall Three: The Rebound. After a period of restriction ends, appetite-regulating hormones do not immediately return to their pre-diet baseline; some research suggests they can remain altered for a year or more. Combined with a lower metabolic rate from wall two, this creates a period of elevated hunger and reduced calorie needs happening at the exact same time, right when most people relax their eating pattern the most, a mismatch that makes regain common rather than a personal failing.

Each of the five ways below targets one or more of these three walls directly, rather than offering another version of “eat less, move more” that ignores why the first attempt at exactly that advice already stopped working.

Why Use Diet Breaks, Not Diet Endings?

  • The Mechanism: Continuous, uninterrupted caloric restriction appears to produce more pronounced metabolic adaptation than restriction broken up by planned periods of eating at maintenance calories. A structured diet break, typically one to two weeks at maintenance intake every six to ten weeks of active dieting, gives appetite hormones and metabolic rate a chance to partially normalize before the next restriction phase begins.
  • The Research Behind It: A notable Australian study (sometimes referred to as the “MATADOR” study) compared continuous dieting to a matched intermittent approach with two-week maintenance breaks built in. The intermittent group lost significantly more fat over the same total dieting time, with less of the metabolic slowdown seen in the continuous group, supporting diet breaks as a legitimate performance strategy rather than a compromise.
  • How to Use It: Plan a maintenance-calorie break of 7 to 14 days after every 6 to 10 weeks of active caloric restriction, using this time to eat at your estimated maintenance calories (not to binge or abandon structure entirely) before resuming your deficit. This turns what many people experience as an uncontrolled binge, driven by accumulated restriction, into a planned, structured part of the process instead.

Get 11 Sample Recipes from Our Bestselling Mediterranean Cookbook. 

Get our 11 Sample Recipes from our Best Selling Mediterranean Protein Friendly Cookbook. These are the most delicious recipes our retreat guests love the most. Easy, simple with few ingredients per meal.  Make delicious heart-friendly and healthy meals you enjoy every day. 

How Can Protein and Fiber Blunt the Hunger Climb?

  • The Mechanism: Protein is the most satiating macronutrient per calorie, both through direct effects on satiety hormones and through a well-documented pattern where inadequate protein intake can drive continued eating, of any food, until a target protein intake is met, even after calorie needs are otherwise satisfied. Fiber adds to this effect by slowing digestion, increasing stomach distension, and supporting the release of additional satiety signals.
  • The Research Behind It: Multiple controlled studies comparing higher-protein to lower-protein diets at matched calorie levels show measurably lower hunger ratings and reduced spontaneous calorie intake in the higher-protein groups, supporting protein intake as a direct lever against wall one rather than simply a muscle-preservation strategy.
  • How to Use It: Prioritize 25 to 40 grams of protein per meal across three to four meals daily, and pair it with fibrous vegetables at most meals. This can help manage hunger during a calorie deficit more effectively than simply cutting calories further, which tends to make wall one worse rather than better. Your personalized macro targets can give you a clearer daily protein goal based on your body, activity level, and objectives.

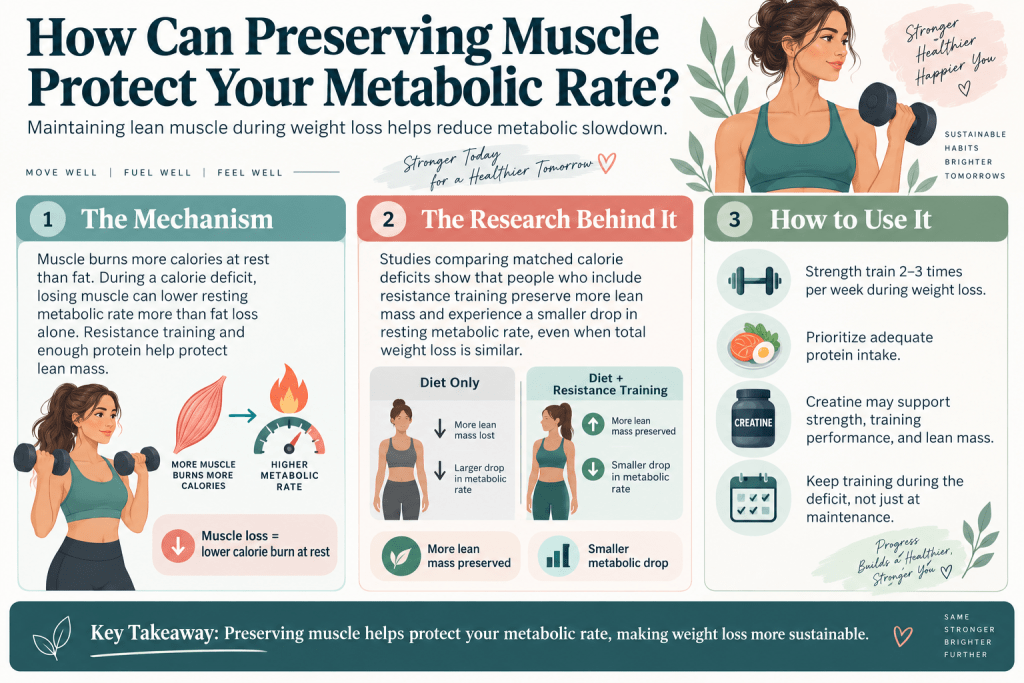
How Can Preserving Muscle Protect Your Metabolic Rate?

Preserving muscle helps protect metabolic rate during weight loss.
  • The Mechanism: Muscle tissue is metabolically active, meaning it burns more calories at rest than fat tissue does. A calorie deficit without adequate resistance training and protein intake tends to draw a meaningful share of the total weight lost from muscle rather than fat, which directly lowers resting metabolic rate beyond what fat loss alone would produce, accelerating wall two.
  • The Research Behind It: Studies comparing weight loss with and without resistance training, at matched calorie deficits, consistently show that the resistance training groups preserve significantly more lean mass and experience a smaller drop in resting metabolic rate, even when total weight lost is similar between groups.
  • How to Use It: Keep resistance training in your routine two to three times per week throughout a weight loss phase, not just once you reach maintenance. Consistent strength training after 40 helps preserve lean muscle while you lose weight, which is especially important when addressing the metabolic slowdown described in wall two. Pairing that training with creatine can provide additional support for strength, training performance, and lean mass during a calorie deficit.

“For years I thought a plateau meant I needed to eat even less. It took understanding the actual mechanism, that the body slows down partly in response to lost muscle, not just lost weight, to realize I had it backward. Protecting muscle during a deficit through resistance training and enough protein is not a nice-to-have on top of weight loss. It is one of the most direct ways to keep your metabolism from working against you.”

Terry Tateossian, Founder of The House of Rose

Get 11 Sample Recipes from Our Bestselling Mediterranean Cookbook. 

Get our 11 Sample Recipes from our Best Selling Mediterranean Protein Friendly Cookbook. These are the most delicious recipes our retreat guests love the most. Easy, simple with few ingredients per meal.  Make delicious heart-friendly and healthy meals you enjoy every day. 

Why Should You Plan the Maintenance Phase Before You Need It?

  • The Mechanism: Wall three, the rebound, is made significantly worse when a period of restriction ends abruptly, with an immediate jump back to prior eating habits, right at the moment when hunger hormones are still elevated and metabolic rate is still suppressed from the diet just completed. A gradual, planned increase in calories back toward true maintenance, rather than an abrupt stop, allows the body’s systems to recalibrate in step with the returning food intake instead of being overwhelmed by a sudden shift.
  • The Research Behind It: This is the foundational logic behind reverse dieting, a structured, gradual increase in calorie intake following a diet phase, and it is supported by the broader body of research on metabolic adaptation and post-diet weight regain, which consistently points to abrupt, unplanned transitions out of a deficit as a major contributor to rapid regain.
  • How to Use It: Rather than treating the end of a diet as a finish line, transition back toward maintenance gradually by increasing calories in small, measured steps and monitoring how your weight, energy, hunger, and training respond. Understanding the basics of reverse dieting can help you structure that transition, while a more detailed reverse diet after 50 provides a practical week-by-week framework for midlife women.

Why Should You Build the Habit Layer Before You Cut Calories?

  • The Mechanism: Adherence to any eating plan depends heavily on factors most diet plans never address directly: sleep quality, chronic stress and cortisol, environmental food cues, and the underlying emotional relationship with food. A calorie target layered on top of poor sleep, high unmanaged stress, and an environment full of easy defaults toward less helpful choices is fighting an uphill battle regardless of how well-designed the macros are.
  • The Research Behind It: Research on sleep deprivation shows direct effects on next-day hunger hormones and food choices, independent of any calorie target. Similarly, chronic stress and elevated cortisol are associated with increased preference for calorie-dense, highly palatable foods, meaning the “willpower” framing common in diet culture often obscures a genuine physiological headwind rather than a character issue.
  • How to Use It: Before or alongside starting a calorie deficit, strengthen the foundational habits that make the plan easier to sustain. Prioritize consistent, adequate sleep by building a practical midlife sleep routine, and weave a few tiny stress-management habits into your day rather than relying on occasional recovery efforts. It also helps to understand how cortisol affects midlife weight, especially when stress, disrupted sleep, hunger, and changing hormones are working against your weight-loss efforts. This groundwork gives the first four strategies in this article a more stable foundation to work from.

Get 11 Sample Recipes from Our Bestselling Mediterranean Cookbook. 

Get our 11 Sample Recipes from our Best Selling Mediterranean Protein Friendly Cookbook. These are the most delicious recipes our retreat guests love the most. Easy, simple with few ingredients per meal.  Make delicious heart-friendly and healthy meals you enjoy every day. 

How Can You Put the Five Ways Together in a Sample Framework?

Phase

Duration

Focus

Foundation

Weeks 1-2

Establish sleep, stress, and protein habits (Way 5) before adding a significant deficit

Active Phase 1

Weeks 3-8

Moderate calorie deficit, protein and fiber prioritized (Way 2), resistance training 2-3x/week (Way 3)

Diet Break

Weeks 9-10

Return to maintenance calories, continue resistance training (Way 1)

Active Phase 2

Weeks 11-16

Resume deficit, same structure as phase 1

Reverse Diet / Maintenance Transition

Weeks 17-20+

Gradual calorie increase back to maintenance over several weeks (Way 4)

This is a framework to adapt to your own timeline and goals, not a fixed prescription, but it illustrates how the five ways function as a connected system rather than five separate, unrelated tips.

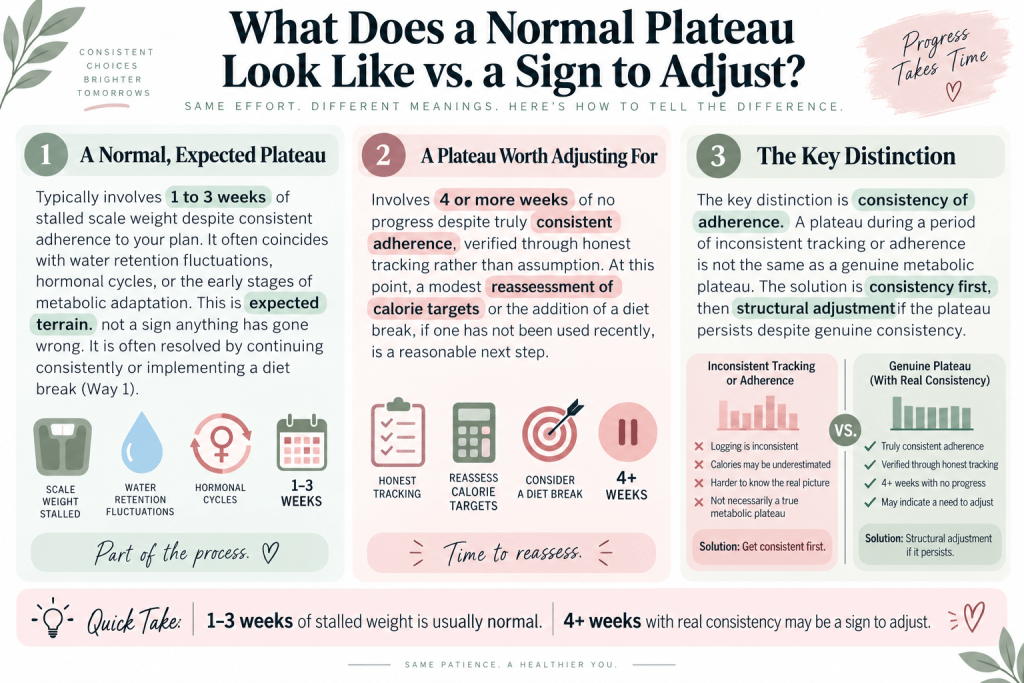
What Does a Normal Plateau Look Like vs. a Sign to Adjust?

Normal weight loss plateau vs. when to adjust.
  • A normal, expected plateau: Typically involves 1 to 3 weeks of stalled scale weight despite consistent adherence to your plan, often coinciding with water retention fluctuations, hormonal cycles, or the early stages of metabolic adaptation described in Section 1. This is expected terrain, not a sign anything has gone wrong, and is often resolved by continuing consistently or implementing a diet break (Way 1).
  • A plateau worth adjusting for: Involves 4 or more weeks of no progress despite truly consistent adherence, verified through honest tracking rather than assumption. At this point, a modest reassessment of calorie targets (accounting for a lower body weight and any metabolic adaptation) or the addition of a diet break, if one has not been used recently, is a reasonable next step.
  • The key distinction: Is consistency of adherence. A plateau during a period of inconsistent tracking or adherence is not the same phenomenon as a genuine metabolic plateau, and addressing the two requires different responses: consistency first, then structural adjustment if the plateau persists despite genuine consistency.

Get 11 Sample Recipes from Our Bestselling Mediterranean Cookbook. 

Get our 11 Sample Recipes from our Best Selling Mediterranean Protein Friendly Cookbook. These are the most delicious recipes our retreat guests love the most. Easy, simple with few ingredients per meal.  Make delicious heart-friendly and healthy meals you enjoy every day. 

Why Does This Matter More in Perimenopause and Menopause?

The three walls described in Section 1 do not appear only in midlife, but several factors make them more pronounced during the menopause transition specifically.

  • Declining estrogen affects fat distribution and insulin sensitivity: As estrogen changes through perimenopause and menopause, body fat tends to shift toward the abdomen while glucose regulation and insulin sensitivity can also change. These metabolic shifts help explain why weight loss can feel different in midlife, making the broader pattern of perimenopause weight gain important to understand when adjusting nutrition, movement, and recovery strategies.
  • Sleep disruption from night sweats and hormonal shifts compounds Way 5 directly: Since disrupted sleep independently worsens hunger hormone regulation on top of whatever a calorie deficit is already doing.
  • Muscle loss becomes increasingly important through the menopause transition: Declining estrogen and age-related changes in muscle function can make preserving lean mass more challenging in midlife, which makes Way 3—resistance training to protect muscle and metabolic health—especially important during this stage of life.
  • Cortisol and stress patterns often shift during this period: Adding another layer to Way 5 that a midlife dieter is more likely to be navigating than a dieter in their twenties.

None of this means weight loss is not achievable in midlife. It means the five ways in this article, particularly Ways 3 and 5, deserve more emphasis, not less, during this specific life stage.

What Common Mistakes Undo These Strategies?

Common mistakes that can stall weight loss progress.
  • Treating a diet break as a free-for-all: A diet break means eating at maintenance calories with the same food quality standards, not abandoning structure entirely for one to two weeks.
  • Cutting protein first when trying to reduce calories further: Protein is the macronutrient most protective against wall one; reducing it to create a larger deficit tends to backfire by increasing hunger faster than it reduces calories.
  • Skipping resistance training “to save energy” during a deficit: This is precisely backward; resistance training during a deficit is what protects the metabolic rate that makes continued progress possible.
  • Ending a diet abruptly instead of reverse dieting: As covered in Way 4, this is one of the most common and most preventable contributors to rapid regain.
  • Ignoring sleep and stress as “separate issues” from the diet itself: As covered in Way 5, these are not separate from weight loss; they are foundational inputs that determine whether the other four ways can work as intended.

This article is educational and is not a substitute for personalized medical or nutritional advice. Consult a physician or registered dietitian before making significant changes to your eating pattern, particularly if you have an existing health condition.

Get 11 Sample Recipes from Our Bestselling Mediterranean Cookbook. 

Get our 11 Sample Recipes from our Best Selling Mediterranean Protein Friendly Cookbook. These are the most delicious recipes our retreat guests love the most. Easy, simple with few ingredients per meal.  Make delicious heart-friendly and healthy meals you enjoy every day. 

Frequently Asked Questions

Why does weight loss always seem to hit a plateau?

Plateaus result from a combination of a smaller body needing fewer calories to maintain itself and adaptive thermogenesis, where the body actively reduces energy expenditure beyond what smaller size alone predicts. This is a normal, well-documented physiological response, not a sign that your plan or effort has failed.

How long should a diet break last?

Most research-supported protocols use 7 to 14 days at maintenance calories, taken after every 6 to 10 weeks of active caloric restriction.

Why do I get hungrier the longer I diet?

Caloric restriction triggers a rise in ghrelin (hunger hormone) and a drop in leptin (satiety hormone), an evolved response to perceived energy scarcity. This tends to intensify with the length and aggressiveness of the deficit, which is part of why moderate, sustainable deficits combined with adequate protein tend to outperform very aggressive ones over time.

Is weight regain after dieting inevitable?

No, but it is common, particularly when a diet ends abruptly rather than transitioning gradually into a planned maintenance phase (reverse dieting). Regain is best understood as a predictable risk to plan around, not an inevitability.

Why is resistance training important for weight loss, not just muscle building?

Muscle tissue is metabolically active, and preserving it during a calorie deficit protects your resting metabolic rate. Weight loss without resistance training tends to come from a mix of fat and muscle, which lowers metabolic rate more than fat loss alone would.

What is reverse dieting?

Reverse dieting provides a structured way to transition out of a prolonged calorie deficit by gradually increasing food intake toward maintenance. Following a reverse dieting approach can help you make those increases in small, measured steps while monitoring hunger, energy, weight trends, and training performance along the way.

How much protein do I need to reduce hunger during a diet?

Research generally supports 25 to 40 grams of high-quality protein per meal, across three to four meals daily, as an effective target for supporting satiety during a caloric deficit.

Does stress really affect weight loss?

Yes. Chronic stress and elevated cortisol are associated with increased preference for calorie-dense, highly palatable foods and can influence fat storage patterns, making stress management a genuine, evidence-based part of a sustainable weight loss approach rather than a secondary concern.

Is it harder to lose weight during perimenopause and menopause?

Several factors, including declining estrogen’s effects on fat distribution and insulin sensitivity, accelerated muscle loss, and sleep disruption from hormonal changes, can make weight loss more challenging during this transition, which is part of why muscle preservation and sleep management (Ways 3 and 5) deserve extra emphasis during this life stage.

What should I do if I’ve been consistent but still haven’t seen progress in a month?

After verifying genuine consistency (through honest tracking, not assumption), a reasonable next step is reassessing your calorie target to account for your current, lower body weight and any accumulated metabolic adaptation, or implementing a diet break if you have not used one recently.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.

References

  • Byrne, N. M., Sainsbury, A., King, N. A., Hills, A. P., & Wood, R. E. (2018). Intermittent energy restriction improves weight loss efficiency in obese men: The MATADOR study. International Journal of Obesity, 42(2), 129-138.
  • Sumithran, P., Prendergast, L. A., Delbridge, E., Purcell, K., Shulkes, A., Kriketos, A., & Proietto, J. (2011). Long-term persistence of hormonal adaptations to weight loss. New England Journal of Medicine, 365(17), 1597-1604.
  • Weigle, D. S., Breen, P. A., Matthys, C. C., Callahan, H. S., Meeuws, K. E., Burden, V. R., & Cummings, D. E. (2005). A high-protein diet induces sustained reductions in appetite, ad libitum caloric intake, and body weight despite compensatory changes in diurnal plasma leptin and ghrelin concentrations. American Journal of Clinical Nutrition, 82(1), 41-48.
  • Trexler, E. T., Smith-Ryan, A. E., & Norton, L. E. (2014). Metabolic adaptation to weight loss: Implications for the athlete. Journal of the International Society of Sports Nutrition, 11, 7.
  • Josse, A. R., Atkinson, S. A., Tarnopolsky, M. A., & Phillips, S. M. (2011). Increased consumption of dairy foods and protein during diet- and exercise-induced weight loss promotes fat mass loss and lean mass gain in overweight and obese premenopausal women. Journal of Nutrition, 141(9), 1626-1634.
  • Wing, R. R., & Phelan, S. (2005). Long-term weight loss maintenance. American Journal of Clinical Nutrition, 82(1 Suppl), 222S-225S.
  • Spiegel, K., Tasali, E., Penev, P., & Van Cauter, E. (2004). Brief communication: Sleep curtailment in healthy young men is associated with decreased leptin levels, elevated ghrelin levels, and increased hunger and appetite. Annals of Internal Medicine, 141(11), 846-850.
  • Tomiyama, A. J. (2019). Stress and obesity. Annual Review of Psychology, 70, 703-718.
  • Wright, K. E., Skinner, S., & Zhu, S. (2023). The musculoskeletal syndrome of menopause. Climacteric, 26(4), 366-371.

Disclaimer: This article is educational and does not constitute medical or nutritional advice. Weight loss strategies involving calorie restriction, diet breaks, protein targets, resistance training, or changes in eating patterns should be individualized based on your health, medications, activity level, and nutritional needs. If you have a medical condition, a history of disordered eating, are pregnant or breastfeeding, or experience persistent fatigue, dizziness, weakness, or other concerning symptoms while attempting weight loss, consult a physician or registered dietitian before following the strategies in this article.

Get 11 Sample Recipes from Our Bestselling Mediterranean Cookbook. 

Get our 11 Sample Recipes from our Best Selling Mediterranean Protein Friendly Cookbook. These are the most delicious recipes our retreat guests love the most. Easy, simple with few ingredients per meal.  Make delicious heart-friendly and healthy meals you enjoy every day. 

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Sarcopenia: The Capacity Crisis Starts Small

Denise is fifty-eight and manages an office on the third floor of a building with no working elevator. Somewhere over the past year, the stairs started to feel different. Not painful, not injured, just harder, enough that she began timing her arrival to avoid climbing them right before a meeting.

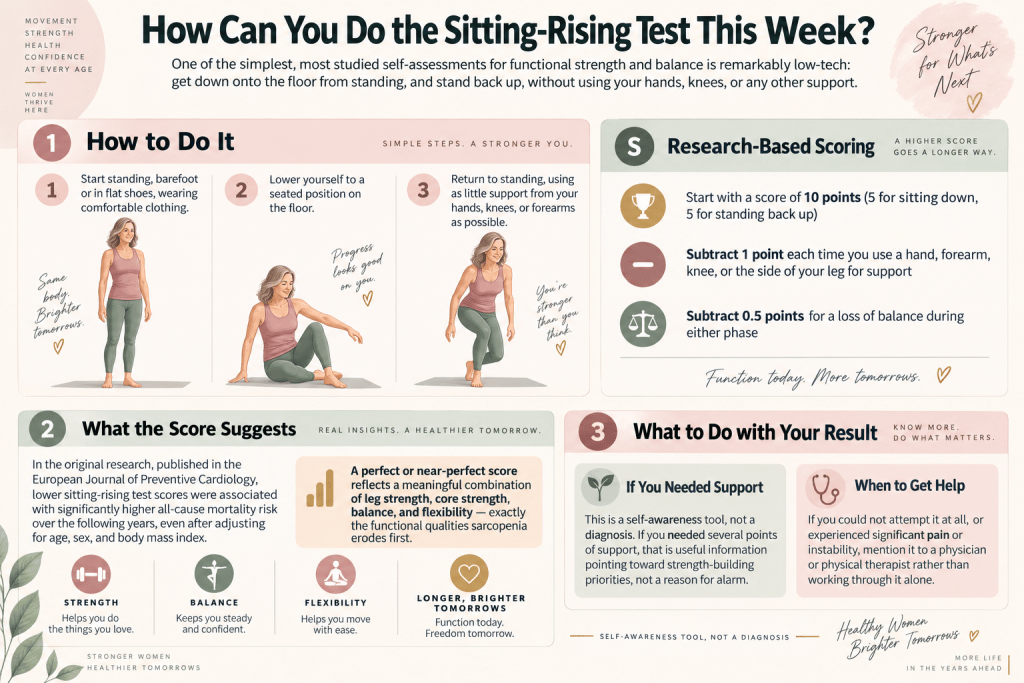
Around the same time, she noticed she was choosing parking spots closer to the store entrance without really deciding to, and she had quietly stopped getting down on the living room floor to play with her grandchildren, telling herself she preferred the couch anyway. None of these felt like anything. Each one had a perfectly reasonable explanation on its own.

Denise did not have an injury. She did not have a diagnosis. What she had, without knowing the name for it, was the opening chapter of sarcopenia, the slow, largely painless loss of muscle mass and strength that begins for most people in their forties, not their eighties, and quietly narrows the range of what a body can do, one small accommodation at a time.

This is a word that deserves far more attention than it gets, precisely because it does not announce itself. It does not show up as an injury or a diagnosis you can point to. It shows up as a series of small, easy-to-explain-away choices, avoided stairs, closer parking, a preference for the couch over the floor, that quietly compound into something much larger: a shrinking capacity for independent living, years before most people think to worry about it.

What Is Sarcopenia?

Sarcopenia is the age-related, involuntary loss of skeletal muscle mass, strength, and function. The term comes from Greek roots meaning “poverty of flesh,” and it was formally defined as a distinct clinical condition (rather than just a vague part of aging) in the 1990s, with diagnostic criteria refined significantly since then by international working groups.

Sarcopenia muscle loss infographic

Sarcopenia is not simply “getting weaker with age” in a vague sense. It is a specific, measurable process involving the loss of muscle fibers, a shift in the ratio of fast-twitch to slow-twitch fibers, reduced nerve signaling to muscle tissue, and a decline in the body’s ability to build new muscle protein in response to exercise and nutrition, all happening gradually and mostly without symptoms severe enough to prompt a doctor’s visit until the losses have already accumulated substantially.

The reason the name matters is that most people encounter sarcopenia, if they encounter the word at all, in the context of frailty in very elderly patients. That framing is exactly backward. The condition that becomes visible and disabling in someone’s eighties began decades earlier, quietly, in the exact way it began for Denise.

Why Does Sarcopenia Start in Your 40s, Not Your 80s?

Muscle mass generally peaks in the late twenties to early thirties. From roughly age 40 onward, most adults lose muscle mass at a rate of approximately 1 to 2 percent per year if no deliberate intervention (primarily resistance training and adequate protein intake) counteracts it. That rate of loss tends to accelerate further after age 60.

This means the muscle available to you at 70 is substantially determined by what happens in your 40s and 50s, not by anything that starts at 70 itself. By the time frailty becomes clinically obvious, in the form of difficulty rising from a chair, a slow walking pace, or a fall, the underlying muscle loss has typically been building for twenty to thirty years.

This is the central, underappreciated fact about sarcopenia: it is not an old-age problem that you will eventually need to deal with later. It is a midlife problem with an old-age price tag, and the years when it is most possible to prevent or reverse are the exact years, like Denise’s, when nothing feels wrong enough yet to act on.

“The thing that struck me most researching this topic is how ordinary the early signs are. Nobody in their forties or fifties thinks ‘I am experiencing early sarcopenia’ when they start parking closer to the store or avoiding a second flight of stairs. They think they are just busy, or tired, or getting older in the completely normal way everyone does. The problem is that ‘normal’ and ‘preventable’ are not the same thing, and this is one of the clearest cases I have found where the two get confused, with real consequences decades down the line.”

Terry Tateossian, Founder of The House of Rose

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
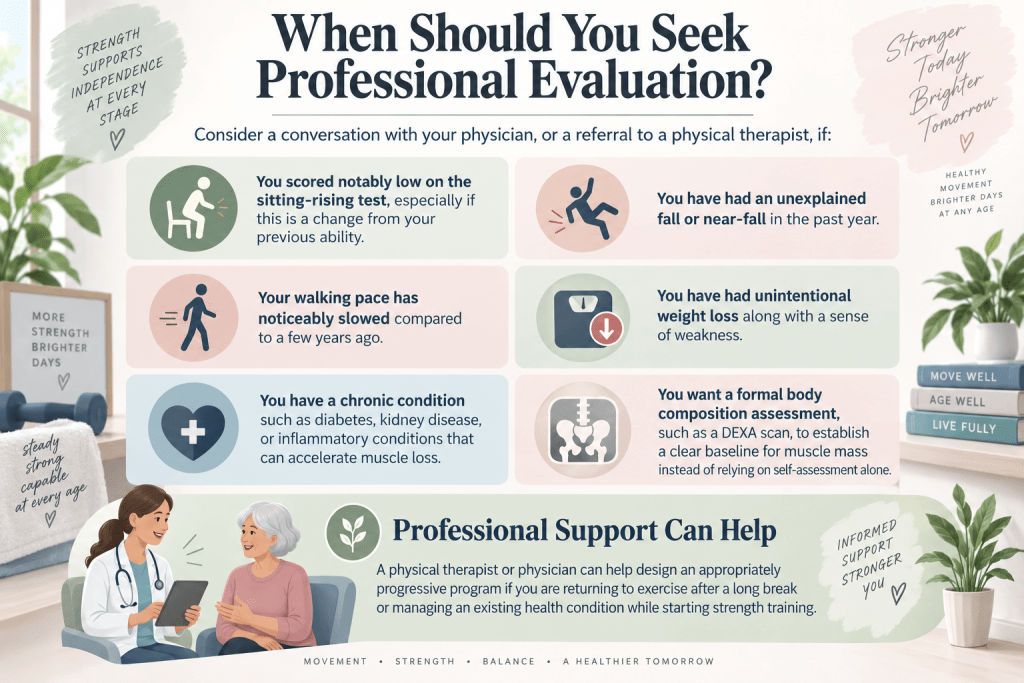
How Does Frailty Creep Instead of Crash?

One of the most important things to understand about sarcopenia is the shape of its progression. It does not announce itself with a dramatic event. It advances through an accumulation of small, individually forgettable adjustments, each one reasonable on its own, that only reveal their true significance when looked at together, in hindsight, the way Denise’s story only made sense once she noticed the pattern across the stairs, the parking, and the floor.

This creeping pattern is precisely why sarcopenia is so often missed until it has already progressed significantly. There is no single moment that triggers concern. There is a slow, almost invisible narrowing of what feels comfortable and possible, until one day an ordinary task, a flight of stairs, a low chair, a full grocery bag, requires a level of effort or a workaround that would have seemed absurd a decade earlier.

Understanding this pattern is itself a form of protection. If you know that early sarcopenia looks like small, explainable avoidances rather than a dramatic loss of function, you can recognize those avoidances in your own life for what they might actually be, rather than dismissing each one individually the way most people, understandably, do.

What Is the Metabolic Role of Muscle Beyond Movement?

Skeletal muscle is often thought of purely in mechanical terms, the tissue that lets you walk, lift, and climb. Its role in the body is considerably larger than that, which is part of why its loss carries consequences well beyond physical movement.

Muscle metabolic role infographic showing glucose, myokines, and recovery.

Muscle Is the Body’s Largest Reservoir for Glucose Disposal

After eating, skeletal muscle is where a substantial share of blood glucose is taken up and stored. Less muscle mass means less capacity to clear glucose from the bloodstream efficiently, directly connecting sarcopenia to insulin resistance and metabolic health, an underappreciated link for a condition usually discussed only in terms of strength and mobility.

Muscle Functions as an Endocrine Organ

Contracting muscle releases signaling molecules called myokines, which influence inflammation, immune function, and communication with other organs, including the brain. A shrinking muscle mass means a reduced signal from one of the body’s most metabolically active tissues.

Muscle Is a Reserve Capacity for Illness and Injury

This is perhaps the least discussed but most consequential role muscle plays. During illness, surgery recovery, or an extended period of bed rest, the body draws on muscle protein reserves to support immune function and healing. Someone with a larger muscle reserve going into an illness has considerably more capacity to withstand that draw without a lasting functional decline.

Someone already running a muscle deficit has far less room to absorb the same hit, which is precisely why a bout of flu or a minor surgery can trigger a permanent drop in baseline function for one person and barely register for another of the same age.

This last point deserves particular emphasis, because it reframes what muscle actually is for. It is not simply about looking a certain way or performing well in a gym. It is a buffer against the unpredictable physical demands life places on the body, and a shrinking buffer means a shrinking margin for error.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
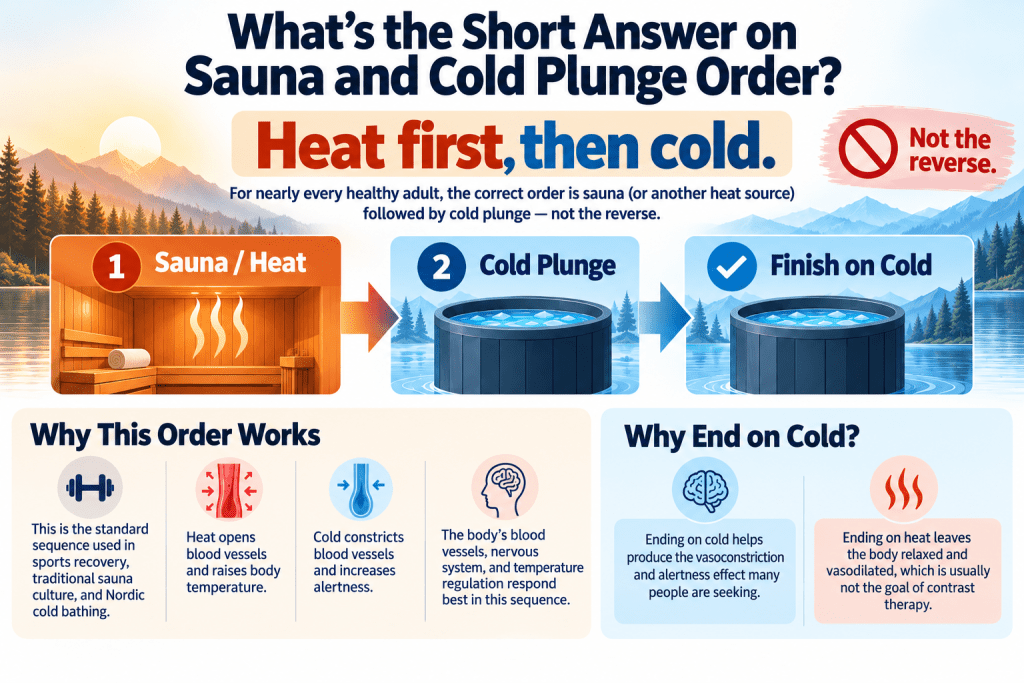
Why Do Midlife Women Face Added Risk?

The Menopause Transition Accelerates Muscle Loss Beyond the Baseline Rate

Estrogen plays a supportive role in muscle protein synthesis and maintenance. Its decline through perimenopause and menopause is associated with an acceleration of muscle loss beyond the general age-related rate that affects both sexes, meaning the “1 to 2 percent per year” figure in Section 2 likely understates the rate many women experience specifically through this transition.

Historical Underrepresentation in Strength Training

Women have historically been less likely than men to engage in resistance training, often steered instead toward cardio-focused exercise for decades of fitness culture.

Cardio exercise offers real cardiovascular benefits but does not provide the same targeted stimulus for building and preserving muscle mass that resistance training does, meaning many women reach midlife with less accumulated muscle reserve to draw on in the first place.

Bone and Muscle Loss Compound Each Other

Menopause-related bone density decline (osteopenia and osteoporosis) and sarcopenia frequently occur together, sometimes described as “osteosarcopenia,” and each condition makes the consequences of the other more serious: weaker bones increase fracture risk from a fall, and weaker muscles increase the likelihood of the fall itself.

Underdiagnosis

Sarcopenia in women is frequently underrecognized in clinical settings, partly because standard body weight and BMI measurements do not distinguish between muscle and fat mass, meaning a woman who is not classified as underweight or who has stable body weight can still be losing meaningful muscle mass without it being flagged by routine measurements.

What Are the Warning Signs Nobody Names?

Because sarcopenia progresses gradually, the early warning signs tend to look exactly like ordinary life adjustments rather than symptoms:

  • Avoiding stairs when a similar route without stairs is available, even if it takes longer
  • Choosing closer parking spots than you used to, without a specific reason
  • A growing reluctance to get down onto the floor, or difficulty getting back up without using your hands or furniture for support
  • Needing two trips to carry groceries that used to take one
  • A noticeably slower walking pace compared to a few years ago, or being the person who consistently lags behind in a group
  • Difficulty opening jars, twisting off tight lids, or other grip-strength-dependent tasks
  • A general sense of “I used to be able to do that more easily” about ordinary physical tasks, without a specific injury to explain it

None of these signs, on their own, is alarming. That is exactly the point. The value of naming them is not to create anxiety about ordinary tasks, but to help you notice a pattern across several of them, the way Denise eventually did, rather than writing off each one individually as unrelated to anything.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How Can You Do the Sitting-Rising Test This Week?

One of the simplest, most studied self-assessments for functional strength and balance is remarkably low-tech: get down onto the floor from standing, and stand back up, without using your hands, knees, or any other support.


Woman demonstrating the sitting-rising test and scoring guide.

How to Do It

Start standing, barefoot or in flat shoes, wearing comfortable clothing. Lower yourself to a seated position on the floor, then return to standing, using as little support from your hands, knees, or forearms as possible.

A more formal, research-based scoring version, developed by Brazilian physician Dr. Claudio Gil Araújo and colleagues, works like this:

  • Start with a score of 10 points (5 for sitting down, 5 for standing back up)
  • Subtract 1 point each time you use a hand, forearm, knee, or the side of your leg for support
  • Subtract 0.5 points for a loss of balance during either phase

What the Score Suggests

In the original research, published in the European Journal of Preventive Cardiology, lower sitting-rising test scores were associated with significantly higher all-cause mortality risk over the following years, even after adjusting for age, sex, and body mass index.

A perfect or near-perfect score reflects a meaningful combination of leg strength, core strength, balance, and flexibility, exactly the functional qualities sarcopenia erodes first.

What to Do with Your Result

This is a self-awareness tool, not a diagnosis. If you needed several points of support, that is useful information pointing toward the strength-building priorities in Section 11, not a reason for alarm.

If you could not attempt it at all, or experienced significant pain or instability, that is worth mentioning to a physician or physical therapist rather than working through alone.

What Does the Research Show About Midlife Strength and Later Independence?

  • Midlife grip strength predicts later disability: Multiple long-term cohort studies have found that grip strength measured in midlife is a meaningful predictor of disability, hospitalization, and mortality decades later, making it one of the most studied simple biomarkers of overall physiological resilience.
  • Resistance training reverses, not just slows, muscle loss: Unlike many age-related processes, sarcopenia remains highly responsive to intervention at any age, including in adults in their seventies, eighties, and nineties. Studies on resistance training in older adults have documented meaningful increases in muscle mass, strength, and functional capacity, even in very advanced age, which is a fundamentally hopeful finding: this is not a one-way, irreversible decline if addressed with the right intervention.
  • Muscle mass and metabolic health are closely linked: Research connecting skeletal muscle mass to insulin sensitivity and glucose metabolism supports the mechanism described in Section 4, showing that preserving muscle mass has metabolic benefits that extend well beyond strength and mobility alone.
  • The “anabolic resistance” of aging muscle: Research on aging muscle physiology has documented a phenomenon sometimes called anabolic resistance, where aging muscle requires a larger protein stimulus to trigger the same amount of muscle protein synthesis compared to younger muscle. This is part of why the nutrition guidance in Section 12 differs somewhat from general population protein recommendations.
  • Functional decline is not linear, and neither is recovery potential: Longitudinal research on functional decline in aging populations shows that while the trajectory can accelerate over time if unaddressed, intervention at any point, including after a period of decline, produces meaningful functional improvement in the majority of studied populations, reinforcing that midlife action matters, but so does action taken later.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How Does Sarcopenia Compound Through the One-Way Ratchet?

Sarcopenia’s most dangerous property is not the muscle loss itself in any single year, but the way it interacts with ordinary life events to compound over time, a pattern sometimes described as a one-way ratchet.

The Illness-Bed Rest-Decline Cycle

As introduced in Section 4, a period of illness or injury draws on the body’s muscle reserve. For someone with adequate reserve, that draw is absorbed and largely recovered from once the illness resolves.

For someone already running a deficit, the same illness can produce a drop in baseline function, reduced walking speed, reduced ability to climb stairs, that does not fully recover, becoming the new normal rather than a temporary dip.

Reduced Activity Following a Functional Drop Reinforces Further Loss

Once climbing stairs or getting up from the floor becomes noticeably harder, the natural response is to do it less, which further accelerates muscle loss, creating a feedback loop that becomes progressively harder to interrupt the longer it continues.

Each Cycle Narrows the Margin for the Next One

This is the ratchet mechanism: each illness-decline cycle leaves a slightly lower baseline than before, meaning the next illness or injury has to overcome less resistance to produce another drop.

Over twenty or thirty years, a series of individually modest declines compounds into the significant frailty that eventually becomes visible and disabling.

The Good News: The Ratchet Can Be Interrupted, Not Just Slowed

Unlike some other age-related processes, this cycle is not purely one-directional if resistance training and adequate nutrition are introduced, which is precisely why the sections ahead focus on concrete action rather than simply describing the problem.

What Actually Works to Reverse the Trend?

Five strategies to reverse muscle loss and improve strength.
  • Resistance training is the single most effective intervention: No other intervention, not cardio exercise, not any supplement, not any passive therapy, comes close to progressive resistance training for building and preserving muscle mass and strength at any age. This is the foundational, non-negotiable piece of addressing sarcopenia.
  • Consistency matters more than intensity for beginners: Two to three resistance training sessions per week, sustained over months and years, produces far more benefit than sporadic, intense efforts. For someone starting from a significant deficit, even light resistance training performed consistently produces measurable improvement.
  • Protein intake must support the training stimulus: As covered in Section 12, resistance training without adequate protein intake produces a smaller muscle-building response than the two combined, making nutrition a genuine partner to training rather than a separate consideration.
  • Power training, not just strength training, matters for fall prevention specifically: Strength helps you produce force, but power training teaches your body to produce that force quickly. That faster response becomes especially important during a stumble, when you need to react immediately to regain your footing rather than simply rely on how much weight you can lift.
  • Balance and mobility work supports the same goal from a different angle: Practices such as tai chi walking train controlled weight shifts, coordination, and body awareness, while the single-leg stance challenges the stability needed to stay upright when your base of support narrows. Together, these skills complement strength and power training by addressing the balance and coordination side of fall prevention.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How Can You Build a Sarcopenia-Resistant Strength Routine?

  • Frequency: 2 to 3 resistance training sessions per week: targeting all major muscle groups across the week rather than the same muscles every session.
  • Focus on compound movements first: Squats, hip hinges (deadlift variations), presses, and rows recruit multiple muscle groups simultaneously and produce more functional carryover to daily tasks like rising from a chair or carrying groceries than isolated single-muscle exercises.
  • Include the specific movement pattern from Section 7: Practicing controlled sit-to-stand movements, from a chair initially, progressing toward the floor-based version over time, directly trains the exact functional pattern the sitting-rising test measures.
  • Add a power component: A small number of faster, more explosive repetitions (such as a quicker tempo on the upward phase of a squat) trains the fast-twitch muscle fibers most responsible for catching a stumble before it becomes a fall.
  • Progressive overload over time: Gradually increasing resistance, repetitions, or difficulty over weeks and months is what continues to stimulate muscle adaptation; a routine that never becomes more challenging eventually stops producing further improvement.
  • Start wherever you are: For someone new to resistance training or returning after a long break, bodyweight exercises and light resistance are a completely legitimate and effective starting point. The goal is consistent progression over time, not an advanced starting point.

For a more structured approach, a complete strength training framework can help you build a routine around progressive resistance, compound movements, and consistent weekly training.

What Role Does Nutrition Play in Protein and Muscle Preservation?

  • Aging muscle needs more protein per meal, not just more protein overall: As referenced in Section 8, anabolic resistance means older muscle requires a larger protein dose per meal to trigger the same muscle-building response compared to younger muscle, making protein distribution across the day, not just total daily intake, a meaningful consideration.
  • A general target of 25 to 35 grams of high-quality protein per meal: is commonly recommended in the sarcopenia and muscle-aging research literature to help overcome this reduced sensitivity, spread across three or more meals rather than concentrated in a single large dose.
  • Leucine-rich protein sources appear particularly effective at triggering muscle protein synthesis: Leucine, an amino acid found in high concentrations in dairy, eggs, meat, and fish, plays an outsized role in triggering the cellular signaling that initiates muscle protein synthesis.
  • Creatine supplementation has a substantial research base supporting muscle preservation, particularly alongside resistance training: Adding creatine for women over 40 to a consistent strength routine can support muscle strength, training performance, and recovery, with creatine monohydrate remaining the most extensively studied form.
  • Adequate overall energy intake matters: Chronic under-eating, common among midlife women focused on weight management, can undermine muscle preservation efforts even when protein and training are otherwise well managed, since the body needs sufficient overall energy availability to prioritize muscle building rather than survival-mode conservation.

For a more personalized target, the protein calculator for women over 40 can help estimate how much protein you need based on your body, activity level, and goals, giving you a clearer foundation for supporting muscle maintenance and metabolic health.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
What Are the Common Mistakes and Misconceptions About Sarcopenia?

  1. Mistake: Waiting for a diagnosis before taking action. Sarcopenia is rarely formally diagnosed until it has progressed significantly. Waiting for a clinical label before addressing the underlying muscle loss means waiting far too long.
  2. Mistake: Assuming cardio alone is sufficient. Cardiovascular exercise offers genuine, important benefits, but it does not provide the specific mechanical loading stimulus that builds and preserves muscle mass the way resistance training does.
  3. Mistake: Believing muscle loss cannot be reversed at an older age. As covered in Section 8, research consistently shows meaningful muscle and strength gains are achievable even in very advanced age with appropriate resistance training, making “it’s too late” one of the most costly misconceptions on this topic.
  4. Mistake: Underestimating protein needs due to outdated general guidelines. Many people are still working from general population protein recommendations that do not account for the increased needs and anabolic resistance associated with aging muscle.
  5. Mistake: Treating the warning signs in Section 6 as isolated, unrelated inconveniences. As covered throughout this article, the value of recognizing these signs comes from seeing the pattern across several of them, not dismissing each one individually.

When Should You Seek Professional Evaluation?

Signs to seek professional evaluation

Consider a conversation with your physician, or a referral to a physical therapist, if:

  • You scored notably low on the sitting-rising test in Section 7, particularly if this represents a change from previous ability
  • You have experienced an unexplained fall or near-fall in the past year
  • Your walking pace has noticeably slowed compared to a few years ago
  • You have experienced unintentional weight loss alongside a sense of weakness
  • You have a chronic condition (diabetes, kidney disease, inflammatory conditions) known to accelerate muscle loss
  • You want a formal body composition assessment (such as a DEXA scan) to establish a clear baseline for muscle mass rather than relying on self-assessment alone

A physical therapist or physician can also help design an appropriately progressive program if you are returning to exercise after a long break or managing an existing health condition alongside a new strength training practice.

This article is educational and is not a substitute for professional medical advice. Consult your physician before beginning a new exercise program, particularly if you have an existing health condition.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Frequently Asked Questions

What is sarcopenia?

Sarcopenia is the age-related, involuntary loss of skeletal muscle mass, strength, and function. It typically begins around age 40, progresses gradually, and accelerates further after age 60 if not counteracted by resistance training and adequate nutrition.

What are the early symptoms of sarcopenia?

Early signs tend to look like ordinary life adjustments rather than obvious symptoms: avoiding stairs, choosing closer parking, reluctance to get down on the floor, needing extra trips to carry groceries, or a general sense that ordinary physical tasks require more effort than they used to.

Can sarcopenia be reversed?

Yes, at nearly any age. Research consistently shows that resistance training produces meaningful increases in muscle mass, strength, and function even in adults in their seventies, eighties, and nineties, making this a highly responsive condition rather than a fixed, one-way decline.

What is the sitting-rising test?

A simple self-assessment where you lower yourself from standing to sitting on the floor, then stand back up, ideally without using your hands, knees, or other support. Lower scores on validated versions of this test have been associated with higher long-term mortality risk in research studies, making it a useful, low-tech gauge of overall functional strength and balance.

At what age should I start worrying about sarcopenia?

The most useful framing is not worry but action: since muscle loss typically begins around age 40 and the years of easiest prevention are in midlife, starting resistance training and adequate protein intake in your 40s and 50s, well before any noticeable decline, is the most effective window for prevention.

How much protein do I need to prevent sarcopenia?

Research on aging muscle generally supports 25 to 35 grams of high-quality protein per meal, spread across three or more meals daily, higher than general population recommendations, to help overcome the reduced protein sensitivity (anabolic resistance) associated with aging muscle.

Is sarcopenia worse for women than men?

Women face some added risk factors, including accelerated muscle loss during the menopause transition due to declining estrogen, historically lower rates of resistance training participation, and a compounding relationship with menopause-related bone density loss, though sarcopenia affects both sexes.

What exercises are best for preventing sarcopenia?

Progressive resistance training focused on compound movements (squats, hip hinges, presses, rows) 2 to 3 times per week is the most effective intervention, ideally combined with some power-focused training and balance work.

Can I have sarcopenia even if my weight is normal or I’m not underweight?

Yes. Standard body weight and BMI measurements do not distinguish between muscle and fat mass, meaning someone at a stable or even overweight body weight can still be losing significant muscle mass without it being reflected on a scale.

Does cardio exercise prevent sarcopenia?

Cardiovascular exercise offers real, important health benefits, but it does not provide the specific mechanical loading stimulus that resistance training provides for building and preserving muscle mass. Cardio and resistance training address different physiological needs and work best in combination, not as substitutes for each other.

How is sarcopenia diagnosed?

Formal diagnosis typically involves a combination of measures: muscle strength (often grip strength), physical performance (such as walking speed), and, in some settings, muscle mass measurement via DEXA scan or similar imaging. In practice, sarcopenia is often underdiagnosed since these measurements are not part of routine checkups for most midlife adults.

References

  • Rosenberg, I. H. (1997). Sarcopenia: Origins and clinical relevance. The Journal of Nutrition, 127(5), 990S-991S.
  • Cruz-Jentoft, A. J., Bahat, G., Bauer, J., Boirie, Y., Bruyère, O., Cederholm, T., Cooper, C., Landi, F., Rolland, Y., Sayer, A. A., Schneider, S. M., Sieber, C. C., Topinkova, E., Vandewoude, M., Visser, M., Zamboni, M., & the Writing Group for the European Working Group on Sarcopenia in Older People 2 (EWGSOP2). (2019). Sarcopenia: Revised European consensus on definition and diagnosis. Age and Ageing, 48(1), 16-31.
  • Araújo, C. G. S., de Souza e Silva, C. G., Laukkanen, J. A., Fiatarone Singh, M., Kunutsor, S. K., Myers, J., Franca, J. F., & Castro, C. L. (2022). Successful 10-second one-legged stance performance predicts survival in middle-aged and older individuals. British Journal of Sports Medicine, 56(17), 975-980.
  • Brito, L. B. B., Ricardo, D. R., Araújo, D. S. M. S., Ramos, P. S., Myers, J., & Araújo, C. G. S. (2014). Ability to sit and rise from the floor as a predictor of all-cause mortality. European Journal of Preventive Cardiology, 21(7), 892-898.
  • Cruz-Jentoft, A. J., & Sayer, A. A. (2019). Sarcopenia. The Lancet, 393(10191), 2636-2646.
  • Volpi, E., Nazemi, R., & Fujita, S. (2004). Muscle tissue changes with aging. Current Opinion in Clinical Nutrition and Metabolic Care, 7(4), 405-410.
  • Wright, K. E., Skinner, S., & Zhu, S. (2023). The musculoskeletal syndrome of menopause. Climacteric, 26(4), 366-371.
  • Fielding, R. A., Vellas, B., Evans, W. J., Bhasin, S., Morley, J. E., Newman, A. B., Abellan van Kan, G., Andrieu, S., Bauer, J., Breuille, D., Cederholm, T., Chandler, J., De Meynard, C., Donini, L., Harris, T., Kannt, A., Keime Guibert, F., Onder, G., Papanicolaou, D., Rolland, Y., Rooks, D., Sieber, C., Souhami, E., Verlaan, S., & Zamboni, M. (2011). Sarcopenia: An undiagnosed condition in older adults. Journal of the American Medical Directors Association, 12(4), 249-256.
  • Peterson, M. D., Rhea, M. R., Sen, A., & Gordon, P. M. (2010). Resistance exercise for muscular strength in older adults: A meta-analysis. Ageing Research Reviews, 9(3), 226-237.
  • Rubio-Ruiz, M. E., Guarner-Lans, V., Pérez-Torres, I., & Soto, M. E. (2019). Mechanisms underlying metabolic syndrome-related sarcopenia and possible therapeutic measures. International Journal of Molecular Sciences, 20(3), 647.

Disclaimer: This article is educational and does not constitute medical advice, diagnosis, or treatment. Sarcopenia, weakness, balance changes, and loss of physical function can have multiple causes and may require professional evaluation. Resistance and power training should be progressed appropriately for your current strength, mobility, and health status. If you have significant joint or balance problems, cardiovascular concerns, chronic medical conditions, recent injuries or surgery, unexplained weakness or weight loss, or a history of falls, consult a healthcare provider or physical therapist before beginning the exercises, self-tests, or nutrition strategies described in this article.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Sauna and Cold Plunge Together: What’s the Right Order and Protocol for Midlife Women?

Angela is fifty. She had read enough about cold plunging to be excited to try it, so on her first visit to a wellness studio that offered both a sauna and a cold tub, she did what felt logical: cold first, to “wake up,” then sauna, to warm back up and relax afterward.

She left feeling worse than when she arrived, lightheaded, oddly shaky, and cold in a way that didn’t resolve for the rest of the afternoon. She assumed contrast therapy just was not for her body.

It turned out Angela had the order backward, and the order is not a minor detail. Sauna and cold plunge are not interchangeable halves of a routine you can sequence however feels intuitive in the moment.

Each step prepares the body for the next in a specific physiological way, and doing it in reverse does not simply produce a weaker version of the same benefits. It can produce a noticeably different, less comfortable, and in some cases less safe experience, which is exactly what happened to Angela.

This article answers the question directly and completely: what is the right order, how long should each phase last, how many rounds make sense, and what does a full contrast therapy protocol look like specifically for a midlife woman’s body.

What’s the Short Answer on Sauna & Cold Plunge Order?

For nearly every healthy adult, the correct order is heat first, then cold: sauna (or another heat source) followed by cold plunge, not the reverse.

Sauna first, then cold plunge infographic

This is the standard sequence recommended across sports medicine, recovery science, and traditional practices like Finnish sauna culture and Nordic cold bathing, and it is not a matter of preference or intuition.

It reflects how the body’s blood vessels, nervous system, and temperature regulation actually respond to heat and cold, covered in detail in the next section. The full session typically ends on cold, not heat, which is the opposite of what many beginners assume.

Ending on a short, final cold exposure produces the vasoconstriction and alertness effect most people are seeking from the practice, while ending on heat leaves the body still in a relaxed, vasodilated state that is not what most contrast therapy protocols are designed to produce.

Why Does the Order Matter, and What’s Happening in Your Body?

Heat Dilates. Cold Constricts

When you sit in a sauna, your blood vessels widen (vasodilation) to help release heat, increasing blood flow to your skin and muscles. When you enter cold water, your blood vessels rapidly narrow (vasoconstriction), pushing blood back toward your core to protect vital organs.

Alternating between these two states, in the right order, creates a kind of pumping action in your circulatory system, sometimes described as a “vascular workout,” that neither heat nor cold alone can fully produce.

Starting With Heat Prepares the Body for Cold in a Way That Reduces Shock

Entering a sauna first raises your core and skin temperature and increases blood flow to your extremities.

This means that when you then move to cold water, your body has a larger temperature buffer to work with, and the cold exposure, while still intense, tends to feel more tolerable and produces a cleaner, more complete vasoconstriction response.

Starting With Cold First Removes That Buffer

If you begin with cold water while your body is still at a normal or lower baseline temperature, the shock to your system is more abrupt, your body has less thermal reserve to draw on, and the experience (as Angela discovered) can leave you feeling depleted, lightheaded, or unable to warm back up efficiently, rather than invigorated.

Ending on Cold Produces the Effect Most People Want From the Practice

The alertness, mental clarity, and mood lift many people associate with contrast therapy is strongly tied to the physiological response of the final cold exposure: a surge of norepinephrine and a shift toward sympathetic nervous system activation.

Ending on heat instead leaves the body in a more parasympathetic, relaxed state, which is a fine goal in its own right but is a different goal than what most people mean when they ask about “the protocol.”

“I made the exact same mistake Angela did when I first started, cold before heat, because it felt like the more intense way to begin. It took feeling completely depleted afterward, more than once, before I actually looked into the physiology and understood why the order matters as much as it does. Heat first gives your body a running start. Skipping that step does not make the practice more hardcore. It just makes it harder on your system for no real benefit.”

Terry Tateossian, Founder of The House of Rose

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
What Is Contrast Therapy, and Why Is It More Than Sauna Plus Cold Plunge?

Contrast therapy is the deliberate practice of alternating between heat and cold exposure in a structured sequence, rather than simply moving from a sauna to a cold plunge once.

A full contrast therapy protocol typically includes multiple rounds of heat and cold. This repeated alternation creates a stronger cycle of vasodilation and vasoconstriction, producing a more pronounced circulatory “pumping” effect than a single heat-to-cold transition.

For example, one sauna session followed by one cold plunge is still a valid form of heat and cold exposure, but it is better described as a single transition. A complete contrast therapy session generally involves two or more rounds, with each period of heat followed by a controlled period of cold.

If you currently sauna once, cold plunge once, and finish there, you can still gain benefits from combining the two. However, gradually progressing to multiple rounds creates the structured alternating pattern that defines a full contrast therapy protocol.

What Is the Complete Contrast Therapy Protocol, Step by Step?

Step-by-step contrast therapy protocol infographic
  • Step 1: Warm up briefly before the sauna (optional but helpful): A few minutes of light movement or a warm shower can help your body ease into the heat more comfortably, especially if you are new to sauna use.
  • Step 2: Complete your first sauna round: Stay in the sauna long enough to become comfortably warm, allowing your core temperature and heart rate to rise while blood flow increases toward the skin.
  • Step 3: Move directly into the cold plunge: Transition from the sauna to cold water with minimal delay, ideally within about a minute. This preserves the heat-to-cold contrast and creates the rapid shift from vasodilation to vasoconstriction that defines contrast therapy.
  • Step 4: Take a brief recovery period: After the cold plunge, rest for a short period and allow your breathing and heart rate to settle before beginning the next cycle.
  • Step 5: Repeat for two to three total rounds: Complete two to three full sauna-to-cold cycles, adjusting the number of rounds to your experience level and how your body responds that day.
  • Step 6: Finish with cold exposure: Complete your final cycle with the cold plunge rather than returning to the sauna. This leaves the body in the cooler, more alert state commonly associated with finishing a contrast session.
  • Step 7: Rehydrate and recover: Drink water or an electrolyte beverage after the session and give your body several minutes to return toward baseline before resuming normal activity.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How Long, How Hot, and How Cold Should Each Phase Be?

Sauna Temperature and Duration

A traditional sauna is typically kept between 150 and 195 degrees Fahrenheit. For contrast therapy specifically, 10 to 15 minutes per round is a reasonable range for most healthy adults, shorter (5 to 8 minutes) for beginners or anyone new to sauna use.

Cold Plunge Temperature and Duration

Cold plunge temperatures for contrast therapy typically range from 50 to 59 degrees Fahrenheit. Duration is intentionally much shorter than the heat phase: 1 to 3 minutes per round is standard, and beginners often start with as little as 30 to 60 seconds.

There is no benefit to staying in cold water longer once the vasoconstriction response has occurred; longer is not better here, and pushing duration too far increases risk without added benefit.

The Heat-to-Cold Time Ratio

As a general guideline, heat exposure per round should be noticeably longer than cold exposure, often on the order of five to ten times longer. This reflects both physiological need (heat takes longer to produce its full vasodilation effect) and safety (extended cold exposure carries more risk than extended heat exposure for most people).

How Many Rounds Should You Do?

  • Beginners: one to two rounds. If you are new to either sauna or cold plunge individually, or new to combining them, start with a single heat-cold cycle and assess how your body responds before adding more.
  • Intermediate practitioners: two to three rounds: This is the range most commonly recommended in recovery science and among experienced practitioners, providing meaningful compounding benefit without excessive physical demand.
  • Advanced practitioners: three to four rounds: Some highly experienced practitioners extend to four rounds, though additional rounds beyond three tend to produce diminishing returns relative to the added physical demand, and this range is not necessary for most people to experience the core benefits of the practice.
  • More rounds is not automatically better: As with cold plunge duration, there is a point of diminishing return, and pushing round count higher primarily increases physical strain rather than proportionally increasing benefit.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
What Should You Do Between Rounds?

Sauna and cold plunge between-round tips
  • Keep transitions brief: A gap of more than a minute or two between sauna and cold plunge allows your body to lose some of the thermal buffer built up during the heat phase, reducing the effectiveness of the following cold exposure.
  • Breathe steadily, especially entering the cold: A controlled, slightly extended exhale as you enter cold water helps manage the initial gasp reflex and keeps your nervous system from spiking into full alarm mode.
  • Rest 2 to 5 minutes between full rounds, at normal room temperature: This allows your heart rate and breathing to settle somewhat before beginning the next heat phase, without losing so much of the accumulated effect that each round feels like starting over.
  • Stay upright and move gently between phases: Especially for beginners, standing and walking slowly between the sauna and the cold plunge (rather than lying down) supports healthy blood pressure regulation during a practice that asks a lot of your circulatory system in a short period.

When Is It Okay to Reverse the Order?

The heat-then-cold sequence is the standard recommendation for the alertness- and circulation-focused version of contrast therapy described throughout this article, but there are a few legitimate exceptions worth knowing.

If Your Only Goal Is Deep Relaxation and Sleep Preparation, Ending on Heat Can Make Sense

A single sauna session, with or without a preceding brief cold exposure, ending on heat rather than cold, tends to produce a more parasympathetic, sleepy, relaxed state. This is a different goal than the alert, activated feeling most contrast therapy protocols are built around, and it is a perfectly valid way to use heat and cold for an evening wind-down routine rather than a morning or midday energizing practice.

If Cold Plunge Alone (With No Sauna) Is Your Practice, the “Order” Question Does Not Apply

Cold plunging can also be used on its own without pairing it with sauna. A standalone cold plunge practice can be built gradually around appropriate water temperature, exposure time, recovery, and individual tolerance, especially during perimenopause and menopause.

If You Are Using Cold Specifically for Acute Inflammation or Injury, Timing May Follow Different Clinical Guidance

Using cold water immersion for a specific injury or acute inflammation is a different application than general wellness contrast therapy, and in that context, timing relative to heat exposure should follow guidance from a physical therapist or physician familiar with your specific situation.

Outside of these specific cases, heat first, cold last, remains the standard, evidence-supported sequence for general wellness contrast therapy.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How Does Contrast Therapy Apply to Midlife Women Specifically?

Cardiovascular Considerations

Regular sauna use in midlife has been associated with benefits for blood pressure, vascular function, and overall cardiovascular health, which becomes especially relevant as cardiovascular risk shifts through the menopause transition.

Pairing sauna with cold plunge adds a more abrupt cycle of vasodilation and vasoconstriction, placing a stronger acute demand on the cardiovascular system than either practice alone. Because cold immersion can temporarily increase heart rate and blood pressure, it is best to build contrast therapy gradually rather than starting with an advanced protocol.

Hot Flashes and Temperature Regulation

Some women in perimenopause and menopause find the intensity of alternating heat and cold either deeply soothing, offering a structured, controlled experience of temperature extremes rather than the unpredictable nature of hot flashes, or, for others, an uncomfortable amplification of an already sensitive temperature regulation system.

This is highly individual, and starting with shorter, gentler rounds is the best way to find out which category you fall into.

Bone Density and Joint Considerations

The temperature and pressure changes involved in contrast therapy are generally well tolerated by the joints and skeletal system, though anyone with significant osteoporosis or joint conditions should consult their physician regarding any new intense physical practice, including this one.

Stress and Cortisol

The controlled, voluntary stress of contrast therapy differs meaningfully from chronic, unwanted stress, and many practitioners describe it as a way of practicing nervous system resilience in a structured setting.

That said, for anyone already dealing with significant chronic stress or cortisol dysregulation, starting gently and paying close attention to how your body responds is more important than pushing for an advanced protocol quickly.

What Common Mistakes Undermine the Protocol?

Common contrast therapy mistakes infographic
  • Doing cold first: As covered throughout this article, this is the single most common sequencing mistake and the one most likely to leave beginners feeling worse rather than better.
  • Staying in the cold plunge too long, chasing a feeling of toughness: Longer cold exposure past the 1 to 3 minute range does not meaningfully increase benefit and increases physical strain and risk.
  • Skipping hydration: Both heat and cold exposure are physically demanding and can affect fluid balance. Skipping hydration before and after a session is a common and easily avoidable mistake.
  • Jumping straight to an advanced protocol: Starting with three or four rounds and long cold exposures before your body has adapted to a single round is one of the most common reasons beginners have a negative first experience and abandon the practice.
  • Doing it on an empty stomach or severely fatigued: Contrast therapy places real demand on the body, and attempting a full protocol while significantly under-fueled or exhausted increases the risk of lightheadedness or fainting.
  • Ignoring warning signs: Dizziness, confusion, chest discomfort, or an inability to warm back up after the session are signals to stop and seek medical attention if they do not resolve quickly, not signals to push through.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Should You Build a Weekly Contrast Therapy Routine?

  • Beginners: 1 to 2 sessions per week: Allow your body time to adapt between sessions, particularly in the first month of practice.
  • Established practitioners: 2 to 4 sessions per week: This range is common among regular practitioners and allows for consistent benefit without excessive physical demand.
  • Listen to your body over any fixed schedule: Days of significant fatigue, illness, or unusual stress are reasonable days to skip or shorten a planned session, since contrast therapy adds physical demand rather than reducing it in the moment.

Who Should Not Do Contrast Therapy?

Consult a physician before starting if you have:

  • Any diagnosed heart condition, arrhythmia, or history of heart attack or stroke
  • Uncontrolled high or low blood pressure
  • Raynaud’s disease or another significant circulatory condition
  • A pacemaker or other implanted cardiac device
  • Are pregnant
  • Have a seizure disorder
  • Have any condition affecting your ability to sense temperature accurately (certain types of neuropathy, for example)

Use particular caution, and consider starting with heat or cold alone before combining them, if you:

  • Are new to both practices individually
  • Have a history of fainting or lightheadedness
  • Are currently dealing with significant illness, dehydration, or exhaustion

Never practice contrast therapy alone if you are new to cold water immersion, particularly cold plunge, given the small but real risk of an unexpected physical response in unfamiliar cold water. Practicing with another person present, at least during your first several sessions, is a reasonable safety precaution.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
What Does the Research Say?

Research on sauna, cold plunge, and contrast therapy.
  • Vascular response to alternating temperature: Research on vascular physiology supports this “pumping” mechanism, showing that repeated shifts between vasodilation and vasoconstriction can produce measurable changes in blood flow beyond those created by heat or cold exposure alone.
  • Sauna and cardiovascular health: As detailed in our companion sauna article, regular sauna use has documented associations with reduced cardiovascular disease risk and improved markers of vascular function, particularly from large longitudinal studies conducted in Finland.
  • Cold water immersion and inflammation, mood, and recovery: Research on cold water immersion has documented effects on inflammatory markers, perceived recovery, and mood, including increases in norepinephrine that may help explain the heightened alertness many people report after cold exposure.
  • Limited research on the combined practice specifically: While both sauna and cold water immersion have meaningful independent research bases, rigorous studies on the combined, sequenced contrast therapy protocol specifically are more limited than the individual-practice research, and much of the sequencing guidance in this article reflects established physiological principles and practitioner consensus rather than large-scale controlled trials on the combined protocol itself.

What Are Your Next Steps?

If you are new to heat or cold exposure, start by learning the basics of sauna use in midlife or building a safe cold plunge practice before combining the two. This gives you time to understand how your body responds to each stressor individually before moving into contrast therapy.

For a more immersive recovery experience, THOR’s Smoky Mountains retreat brings together restorative movement, nervous system support, bodywork, and recovery practices, with options including infrared sauna and cold-water exposure.

If you want help fitting contrast therapy into a larger exercise and nutrition routine, personalized coaching can provide structured training, nutrition guidance, regular check-ins, and ongoing support around your broader midlife wellness goals.

This article is educational and is not a substitute for professional medical advice. Consult your physician before beginning any new heat or cold exposure practice, particularly if you have a cardiovascular condition or other relevant health history.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

Should I do sauna before or after cold plunge?

Sauna first, cold plunge second, for nearly all healthy adults practicing general wellness contrast therapy. This order allows your body to build a thermal buffer that makes the cold exposure more tolerable and produces a more complete physiological response than doing it in reverse.

How long should I stay in the sauna before cold plunging?

10 to 15 minutes per round for most healthy adults, shorter (5 to 8 minutes) for beginners.

How cold should the water be, and for how long?

Typically 50 to 59 degrees Fahrenheit for 1 to 3 minutes per round. Beginners often start with 30 to 60 seconds.

How many rounds of sauna and cold plunge should I do?

Two to three rounds is standard for most practitioners. Beginners should start with one round and build up gradually.

Is it ever okay to do cold plunge before sauna?

For general wellness contrast therapy focused on circulation and alertness, no, heat first is the recommended sequence. The main exception is if you are practicing cold plunge as a fully separate, standalone practice with no sauna involved, in which case the “order” question does not apply.

Can contrast therapy help with menopause symptoms?

Some women find contrast therapy helpful for stress management, sleep, and a sense of structured control over their body’s temperature regulation, though individual response varies, and it should be approached as a complementary wellness practice rather than a treatment for menopause symptoms specifically.

Is contrast therapy safe for someone with high blood pressure?

Anyone with uncontrolled high blood pressure or another cardiovascular condition should consult a physician before beginning contrast therapy, given the acute cardiovascular demand of alternating heat and cold exposure.

What should I eat or drink before a contrast therapy session?

Stay well hydrated and avoid attempting a session on a completely empty stomach or in a significantly fatigued state, both of which increase the risk of lightheadedness.

Can I do contrast therapy every day?

Most practitioners do well with 2 to 4 sessions per week rather than daily practice, allowing the body time to recover between sessions, particularly for anyone newer to the practice.

What if I feel dizzy or unwell during or after a session?

Stop the session, sit or lie down safely, and rehydrate. If dizziness, confusion, or chest discomfort does not resolve quickly, seek medical attention.

Do I need a professional facility, or can I do this at home?

Both are viable. A home setup (a personal sauna and cold plunge tub or a cold shower alternative) works well once you understand the protocol, though a supervised facility can be a good way to learn the practice safely for your first several sessions.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.

References

  • Laukkanen, T., Khan, H., Zaccardi, F., & Laukkanen, J. A. (2015). Association between sauna bathing and fatal cardiovascular and all-cause mortality events. JAMA Internal Medicine, 175(4), 542-548.
  • Bleakley, C. M., & Davison, G. W. (2010). What is the biochemical and physiological rationale for using cold-water immersion in sports recovery? A systematic review. British Journal of Sports Medicine, 44(3), 179-187.
  • Šrámek, P., Šimečková, M., Janský, L., Šavlíková, J., & Vybíral, S. (2000). Human physiological responses to immersion into water of different temperatures. European Journal of Applied Physiology, 81(5), 436-442.
  • Kox, M., van Eijk, L. T., Zwaag, J., van den Wildenberg, J., Sweep, F. C., van der Hoeven, J. G., & Pickkers, P. (2014). Voluntary activation of the sympathetic nervous system and attenuation of the innate immune response in humans. Proceedings of the National Academy of Sciences, 111(20), 7379-7384.
  • Wright, K. E., Skinner, S., & Zhu, S. (2023). The musculoskeletal syndrome of menopause. Climacteric, 26(4), 366-371.
  • Hussain, J., & Cohen, M. (2018). Clinical effects of regular dry sauna bathing: A systematic review. Evidence-Based Complementary and Alternative Medicine, 2018, 1857413.

Disclaimer: This article is educational and does not constitute medical advice. Sauna and cold plunge contrast therapy places significant demands on your cardiovascular and temperature-regulation systems and should be approached gradually. If you have heart disease, blood pressure concerns, circulation problems, a history of fainting or seizures, are pregnant, have reduced temperature sensation, or have another relevant medical condition, consult a healthcare provider before starting the protocols in this article.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

18 Ways to Regulate Your Nervous System When Stillness Makes You Worse

Dana followed the instructions exactly. Quiet room, cushion, timer set for ten minutes, eyes closed, attention on the breath, the same instructions from the same app that seemed to work fine for her sister. Within ninety seconds her heart was pounding harder than it had been before she sat down.

Her thoughts, instead of settling, sped up and got louder, circling the same three worries faster and faster with nothing else to compete for her attention. By minute four she gave up, opened her eyes, and sat there feeling worse than when she started, plus a new layer of guilt for being, in her words, “bad at meditating.”

Dana is not bad at meditating. What happened to her has a name and a real physiological explanation, and it is far more common than most meditation content ever admits. For a meaningful number of people, particularly those carrying a lot of chronic stress, unprocessed activation, or a nervous system that has spent years running hot, sudden stillness does not calm the system down.

It removes the noise and movement that had been quietly discharging some of that activation, and it turns the volume up on internal sensations the body had not been ready to sit with yet. The result is not relaxation. It is often the opposite.

This article is for exactly that experience. It does not ask you to try harder at stillness. It offers eighteen other real, workable ways to regulate your nervous system, most of which involve moving, not sitting, because for a body like Dana’s, moving is often the faster and safer road back to calm.

Why Can Stillness Backfire? The Real Physiology

Standard meditation advice assumes a nervous system that is ready to slow down and turn inward. For many people, that assumption holds. For others, particularly those living with chronic stress, high sympathetic activation, or a nervous system shaped by past overwhelm, it does not, and understanding why is the key to everything else in this article.

Why stillness can increase anxiety and how movement helps regulate the nervous system.

How Does Movement Quietly Discharge Hidden Activation?

Movement is often quietly discharging activation you cannot see. A body under chronic stress accumulates physical activation: muscle tension, a faster resting heart rate, a general state of readiness for action. Ordinary daily movement, fidgeting, pacing, tension in the shoulders, even restless leg movement, provides a small, continuous outlet for some of that activation without you noticing.

Remove all movement at once, as stillness-based meditation asks you to, and that activation has nowhere to go. It often shows up instead as a louder, more physically present version of the anxiety that was already there, just quieter and better distributed a moment before.

Why Can Stillness Increase Interoceptive Awareness?

Stillness increases interoceptive attention, and that is not neutral for everyone. Interoception is your awareness of internal body sensations, heartbeat, breath, muscle tension, gut sensations. Meditation deliberately increases interoceptive attention, which is helpful for many people.

But for someone whose baseline internal state already includes a racing heart, shallow breath, or gut tension from chronic stress, turning up the volume on noticing those sensations, without also giving the body a way to respond to them, can intensify distress rather than ease it.

Can Meditation and Mindfulness Sometimes Increase Anxiety?

This is a known, documented phenomenon, not a personal failure. Researchers and clinicians increasingly recognize that meditation and mindfulness practices, while broadly beneficial on average, can produce increased anxiety, and in some cases more significant distress, in a meaningful minority of practitioners, particularly those with a trauma history or a nervous system already running in a highly activated state.

If stillness has made things worse for you, that is a real, studied pattern, not evidence that you are doing meditation wrong or are somehow unfit for self-regulation.

Why Does the Nervous System Respond Well to Movement?

The nervous system responds well to movement precisely because movement is its native language for discharging activation. This is the foundation the rest of this article builds on.

Instead of asking an already-activated system to override its need for movement with stillness, these techniques work with that need, using movement, sensation, and voice to help the nervous system complete its own natural process of settling down.

How Can You Know If This Is You?

Not everyone who finds meditation difficult has this specific pattern, but a few signs tend to point toward it clearly.

  • Sitting still and closing your eyes makes your heart rate or breathing noticeably worse, not better
  • Your thoughts get faster and louder during stillness, rather than quieter
  • You feel a strong physical urge to move, get up, or open your eyes within the first few minutes
  • You feel more anxious, panicky, or unsettled after a meditation or relaxation session than before it started
  • Lying still (as in savasana or a body scan) feels more agitating than restful
  • You have been told stillness practices “just take practice,” but repeated attempts have consistently made things worse rather than gradually better
  • You generally feel calmer after movement (a walk, a workout, cleaning the house) than after trying to sit quietly

If several of these sound familiar, the tools in this article are built specifically for you.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Why Does Regulation Not Require Stillness?

Nervous system regulation simply means helping your body move from a state of high alert or shutdown back toward a calm, settled baseline. Stillness-based meditation is one path to that outcome, but it is not the only one, and it is not the right starting point for every nervous system.

A concept from somatic (body-based) therapy called titration is useful here: rather than asking the body to go from high activation straight to full stillness, a titrated approach works in smaller, more manageable steps, often using brief bursts of movement or sensation to help the body discharge some activation first, before stillness becomes accessible or even desirable. Many of the tools below are built on exactly this principle.

The eighteen tools that follow are organized into four groups: movement-based tools that help discharge physical activation directly, sensory and grounding tools that use your senses to anchor you in the present without requiring stillness, voice, breath, and pressure-based tools that use sound and touch to signal safety to the nervous system, and a final section on how to build toward stillness gradually, for anyone who eventually wants that option available to them as well.

“For years I assumed I was simply bad at meditating, because every time I tried to sit still and breathe, I felt worse, not better. It took me a long time to learn that this is an actual, documented pattern, not a personal failing. Once I started using movement first, a short walk, some shaking out of my hands, even just cleaning a counter with real attention, stillness became something I could access afterward instead of something that set me off. The lesson underneath all of this is that regulation is the goal, not stillness. Stillness is just one door into that goal, and it is not the only one.”

Terry Tateossian, Founder of The House of Rose

What Are Movement-Based Regulation Tools?

Movement-based regulation tools for calming the nervous system
  • Shake it out: Stand up and shake your hands, arms, and legs for 60 to 90 seconds, loosely and without much structure, similar to how animals physically shake after a stressful event. This is a simple, direct way to discharge stored physical activation and is one of the fastest tools on this list.
  • Take a brisk outdoor walk: Ten to fifteen minutes at a pace slightly faster than a stroll, ideally outside. The combination of rhythmic movement, changing scenery, and fresh air engages multiple regulation pathways at once and is one of the most consistently effective tools for people who find stillness activating.
  • Rebound on a mini trampoline: Gentle bouncing for three to five minutes provides rhythmic, full-body movement that keeps the body engaged rather than requiring complete stillness. Starting with a simple rebounding practice can offer a low-impact way to add movement, circulation, balance work, and a calming rhythm to your day.
  • Put on music and move freely: Two or three songs of unstructured movement, dancing, swaying, stretching, whatever your body wants to do, gives activation somewhere to go while also engaging the part of the brain associated with pleasure and reward.
  • Do a short burst of vigorous exercise: Twenty to thirty jumping jacks, a fast set of bodyweight squats, or a minute of running in place can rapidly discharge high activation, particularly useful in moments of acute anxiety or panic rather than as a daily baseline practice.
  • Clean or organize something with full attention: This may sound unconventional, but purposeful physical activity, folding laundry, wiping down counters, organizing a drawer, done with real attention rather than as background noise, combines movement with a sense of completion and control that many people find deeply settling.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Are Sensory and Grounding Tools?

  • The 5-4-3-2-1 senses check: Name five things you can see, four things you can hear, three things you can touch, two things you can smell, and one thing you can taste. This grounds attention in the present moment and the external environment, rather than turning attention inward the way stillness-based meditation does, making it a safer starting point for many people.
  • Hold something cold: An ice pack, a cold water bottle, or running your hands under cool water for thirty seconds provides a strong, clear sensory signal that tends to interrupt spiraling thoughts and anchor attention in the body without requiring stillness.
  • Splash cool water on your face: This engages what is sometimes called the mammalian dive reflex, a natural physiological response that can help slow heart rate. It is quick, requires no equipment beyond a sink, and is a well-established calming technique used in several clinical approaches to acute distress.
  • Orient to the room: Slowly turn your head and look around the space you are in, naming a few objects out loud or silently. This is different from closing your eyes and turning inward; it is a grounding technique that uses the environment itself to signal safety to the nervous system.
  • Self-massage or fascia work: A few minutes of hands-on pressure, working your own shoulders, forearms, or scalp, or using a gua sha tool as described in our Complete Gua Sha Routine, provides calming touch input and gentle movement together.

What Are Voice, Breath, and Pressure-Based Tools?

  • Hum or sing: Humming, gentle chanting, or singing along to a song engages the vagus nerve through vibration in the throat and chest, a well-documented regulation tool that involves sound and gentle vibration rather than silent stillness.
  • Try active, extended-exhale breathing while moving: Rather than sitting still and focusing inward on the breath, try a longer exhale than inhale (for example, a four-count inhale and a six- to eight-count exhale) while walking or standing, so the breath work is paired with movement instead of stillness.
  • Apply firm, even pressure to your body: A weighted blanket, a firm self-hug with crossed arms and a squeeze, or pressing your palms firmly together for ten seconds all provide what is sometimes called proprioceptive input, deep pressure and body awareness that many people find calming in a way gentle, passive stillness does not achieve.
  • Push against something solid: Press your palms against a wall, push your feet firmly into the floor, or do a few isometric holds (like a wall sit for 20 to 30 seconds). This is an active, engaged form of stillness, using muscular effort rather than passive quiet, which some people find far more accessible than sitting with nothing to do.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Can You Build Toward Stillness Gradually?

For some readers, the eventual goal is still to access a calm, seated stillness practice, simply not as a starting point. These final three tools offer a gradual bridge.

Three ways to build toward stillness gradually
  • Try titrated stillness: Instead of committing to ten minutes of stillness, try 30 to 60 seconds, then check in with your body, then decide whether to continue. This short, low-commitment approach prevents the overwhelm that often comes with an all-or-nothing block of forced stillness.
  • Pair brief stillness with movement on either side: Try a short walk or shake-out, followed by 60 to 90 seconds of stillness, followed by another short burst of movement. This “movement, stillness, movement” pattern, sometimes called pendulation in somatic therapy circles, allows the nervous system to test stillness in small, safe doses with an easy exit available on both sides.
  • Choose active stillness over passive stillness at first: Sitting upright with your eyes open, gently focused on a fixed point in the room, tends to feel more available than lying down with eyes closed for people whose nervous system finds passive stillness activating. This is a legitimate, complete practice in its own right, not simply a lesser version of “real” meditation.

How Can You Choose the Right Tool in the Moment?

  • If you feel highly activated (racing heart, panic, restlessness): Start with movement-based tools. These discharge activation directly and tend to produce the fastest shift.
  • If you feel spacey, foggy, or disconnected rather than activated: Sensory and grounding tools tend to work better, since they anchor attention in the present moment and the body.
  • If you are somewhere in between, or looking for a quick reset during a normal day: Voice, breath, and pressure-based tools are often the easiest to use discreetly, at a desk, in a car, or in public.
  • If your goal is eventually building a seated practice: Use a gradual, low-pressure approach that does not require you to force it before your nervous system is ready.

There is no single right tool for every person or every moment. Part of building real regulation skill is learning, through practice, which tools work best for your particular nervous system in a particular kind of moment.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Can You Build a Personal Regulation Toolkit?

  • Try several tools when you are calm, not only in crisis: It is much easier to learn what works for your body during a low-stakes moment than during acute distress. Spend a few days trying two or three different tools from this list during ordinary moments of mild stress.
  • Notice what actually shifts your state, not just what you think should work: Some people are surprised to discover that a technique they expected to dislike (cold water, for example) works far better for them than one that sounds more appealing on paper.
  • Keep a short personal list: Once you know which three or four tools reliably help you, write them down somewhere accessible (a note on your phone, a card in your bag) so you are not trying to remember or choose under stress.
  • Layer tools rather than relying on just one: A brisk walk followed by a few minutes of humming, for example, often works better than either alone, since it combines discharge (movement) with a vagal, voice-based signal of safety (humming).
  • Expect this to be a practice, not a one-time fix: Like any regulation skill, these tools tend to become more effective and more automatic with repeated use over weeks and months, not from a single try.

When Should You Seek Additional Support?

The tools in this article are general wellness strategies, not a treatment for a diagnosed mental health condition. Consider reaching out to a qualified mental health professional, ideally one with training in trauma-informed or somatic approaches, if:

Signs it may be time to seek professional mental health support.
  • Anxiety, panic, or distress is significantly interfering with your daily functioning, work, relationships, or sleep
  • You experience frequent panic attacks or intense physical symptoms of anxiety
  • You have a history of trauma that you suspect is connected to this pattern
  • These tools provide only brief or minimal relief and the underlying distress remains persistent
  • You are having thoughts of harming yourself, in which case immediate support from a crisis line or emergency service is the right next step, not a self-help tool

Somatic and body-based therapy approaches, including Somatic Experiencing and polyvagal-informed therapy, are specifically designed to work with exactly the pattern described in this article, and a trained therapist can offer guided, personalized support well beyond what any article can provide.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Does Research Say About Somatic Regulation?

  • Meditation-related adverse effects are a real, documented phenomenon: Research examining the effects of mindfulness and meditation practices has identified a subset of practitioners who experience increased anxiety, distress, or other difficult effects, particularly among those with pre-existing high anxiety or trauma histories, supporting the honest framing throughout this article that stillness is not universally calming.
  • Movement and rhythmic activity support nervous system regulation: A substantial body of research on exercise and mental health documents reductions in anxiety and stress markers following both acute bouts and regular movement, consistent with the movement-based tools in Section 4.
  • Vagal tone and voice-based practices: Research on the vagus nerve, which plays a central role in regulating the parasympathetic (rest-and-digest) nervous system, supports the connection between vocalization (humming, chanting, singing) and increased vagal activity, consistent with the tools in Section 6.
  • Cold exposure and the dive reflex: Research on facial cold water exposure has documented measurable reductions in heart rate through activation of the mammalian dive reflex, supporting this as a legitimate, quick regulation tool rather than folk advice.
  • Deep pressure and proprioceptive input: Research in both clinical and occupational therapy literature supports deep pressure and proprioceptive input (weighted blankets, firm pressure, pushing against resistance) as effective calming tools for a range of populations, including those with high baseline anxiety.
  • Polyvagal theory as a helpful framework: Polyvagal theory, developed by Dr. Stephen Porges, offers a widely referenced framework for understanding how the autonomic nervous system moves between states of safety, activation, and shutdown, and has substantially influenced the somatic and trauma-informed therapy approaches this article draws from. It is worth noting that some specific claims within polyvagal theory remain debated among researchers, and it is best understood as a useful clinical framework rather than a fully settled scientific consensus.

This article is educational and is not a substitute for professional mental health care. If you are in crisis or having thoughts of harming yourself, please contact a crisis line or emergency services immediately.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

Why does meditation make my anxiety worse instead of better?

For some people, particularly those with chronic stress or a trauma history, sudden stillness removes the outlet that ordinary movement was providing for stored physical activation, while also increasing attention to internal body sensations before the body is ready to sit with them calmly. This is a documented pattern, not a personal failure at meditating.

Is it normal to feel worse after trying to sit still and breathe?

Yes, for a meaningful subset of people. Research on mindfulness and meditation has identified increased anxiety and distress as a real, if less commonly discussed, effect for some practitioners, particularly those with high baseline anxiety or a trauma history.

What is nervous system dysregulation?

Nervous system dysregulation refers to a state where the autonomic nervous system has difficulty moving smoothly between activation and calm, often getting stuck in high alert (fight-or-flight) or shutdown (freeze) states rather than flexibly returning to a settled baseline.

Do I have to eventually learn to sit still and meditate?

No. While Section 7 offers a gradual path toward stillness for those who want it, movement-based and sensory regulation tools are complete, legitimate practices in their own right, not lesser substitutes for “real” meditation.

How quickly do these tools work?

Many people notice a shift within a few minutes of trying movement-based or sensory tools, though individual response varies. Consistency in practicing several tools over time tends to make them more effective and more automatic.

Can I use these tools alongside therapy?

Yes. These tools work well as a complement to professional mental health support, particularly trauma-informed or somatic therapy approaches, which can offer more personalized, guided work with exactly this pattern.

What is polyvagal theory, and do I need to understand it to use these tools?

Polyvagal theory is a framework for understanding how the nervous system moves between states of safety, activation, and shutdown. It is not necessary to understand the full theory to benefit from the practical tools in this article, though it is a helpful lens if you want to go deeper.

Are these tools only for people with anxiety?

No. They are useful for anyone experiencing everyday stress, overstimulation, or a general sense of being “wired” or unable to settle, not only for those with a diagnosed anxiety condition.

Can children or teenagers use these techniques?

Many of the sensory and movement-based tools (shaking out, the 5-4-3-2-1 exercise, cold water on the face) are commonly used in child and adolescent therapy settings and can be appropriate with age-suitable guidance from a parent or professional.

What if none of these tools seem to help?

If you have tried several tools consistently and are not noticing meaningful relief, or if distress is significantly affecting your daily life, this is a good signal to seek support from a qualified mental health professional rather than continuing to rely on self-guided tools alone.

References

  • Britton, W. B., Lindahl, J. R., Cooper, D. J., Canby, N. K., & Palitsky, R. (2021). Defining and measuring meditation-related adverse effects in mindfulness-based programs. Clinical Psychological Science, 9(6), 1185-1204.
  • Farias, M., & Wikholm, C. (2016). Has the science of mindfulness lost its mind? BJPsych Bulletin, 40(6), 329-332.
  • Porges, S. W. (2011). The Polyvagal Theory: Neurophysiological Foundations of Emotions, Attachment, Communication, and Self-Regulation. W. W. Norton & Company.
  • Levine, P. A. (2010). In an Unspoken Voice: How the Body Releases Trauma and Restores Goodness. North Atlantic Books.
  • Rebar, A. L., Stanton, R., Geard, D., Short, C., Duncan, M. J., & Vandelanotte, C. (2015). A meta-meta-analysis of the effect of physical activity on depression and anxiety in non-clinical adult populations. Health Psychology Review, 9(3), 366-378.
  • Vickhoff, B., Malmgren, H., Åström, R., Nyberg, G., Ekström, S. R., Engwall, M., Snygg, J., Nilsson, M., & Jörnsten, R. (2013). Music structure determines heart rate variability of singers. Frontiers in Psychology, 4, 334.
  • Kox, M., van Eijk, L. T., Zwaag, J., van den Wildenberg, J., Sweep, F. C., van der Hoeven, J. G., & Pickkers, P. (2014). Voluntary activation of the sympathetic nervous system and attenuation of the innate immune response in humans. Proceedings of the National Academy of Sciences, 111(20), 7379-7384.
  • Chen, H. Y., Yang, H., Chi, H. J., & Chen, H. M. (2013). Physiological effects of deep touch pressure on anxiety alleviation: The weighted blanket approach. Journal of Medical and Biological Engineering, 33(5), 463-470.
  • Krauss, K. E. (1987). The effects of deep pressure touch on anxiety. American Journal of Occupational Therapy, 41(6), 366-373.

Disclaimer: This article is educational and does not constitute medical or mental health advice. Nervous system regulation techniques can affect people differently, particularly those with anxiety, panic symptoms, trauma histories, cardiovascular concerns, balance problems, or recent injuries. Some practices in this article involve vigorous movement, cold exposure, breathwork, or strong sensory input, so use them gradually and stop if symptoms worsen. If distress is persistent, significantly affects daily life, or includes thoughts of self-harm, seek support from a qualified healthcare or mental health professional.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

That Ridge on Your Nail Might Be Telling You Something: What Nail Ridges Really Mean

Renee is forty-eight. She was filing her nails one evening, the way she does most Sundays, when her thumbnail caught on something. Not a snag, not a hangnail, but a fine, raised line running from the base of the nail to the tip, the kind of thing you can feel more easily than you can see.

She held her hand up to the light and noticed something else: nearly every nail had the same faint ridges, running the same direction, evenly spaced like the grooves in a vinyl record. She had never really looked this closely before. Once she started, she could not stop looking, and she could not stop wondering what it meant.

What Renee found, once she looked into it, is a small piece of anatomy that turns out to be far more interesting than it looks: your nails are not static. They are a slow-motion record of your body’s health, growing at a steady, measurable rate, and any real disruption to that growth process, whether from age, illness, or something as simple as a nutrient shortfall, tends to show up as a visible change in the nail itself. A ridge is not a flaw. It is information.

This article walks through exactly what nail ridges are, the real difference between the two main types, what each one can and cannot tell you about your health, and when a ridge is worth mentioning to a doctor.

What Is a Nail Ridge?

Your fingernails are made of a hardened protein called keratin, the same protein that makes up your hair. Nails grow continuously from a small area at the base of the nail, hidden just under the skin, called the nail matrix.

Nail ridge types and nail growth infographic

As new nail cells form in the matrix, they push the older cells forward and out, which is why a nail slowly grows from base to tip over a period of months.

A ridge is simply a change in the surface texture of the nail, a raised or grooved line rather than a perfectly flat surface. Ridges form when something disrupts the normally smooth, even process of nail cell production in the matrix, either briefly or over a longer period of time.

Because nails grow at a fairly predictable rate, roughly 3 millimeters per month for fingernails, a ridge can sometimes act like a timestamp, marking roughly when a disruption occurred based on where the ridge currently sits on the nail.

There are two fundamentally different types of ridges, and they are not the same story at all.

What Are Vertical Ridges?

Vertical ridges run lengthwise, from the base of the nail (the cuticle) to the free edge (the tip). They look like fine, raised lines running parallel to each other, and they are extremely common, especially as people get older.

The honest headline here: vertical ridges are, in the large majority of cases, a normal part of aging, not a sign of disease. They tend to become more noticeable through the 40s, 50s, and beyond, in much the same way skin develops fine lines. Nearly everyone develops some degree of vertical ridging eventually.

That said, vertical ridges are not always purely cosmetic. In some cases, they can become more pronounced with certain nutrient deficiencies, thyroid changes, or general nail dryness, all covered in the sections ahead.

The key distinction to hold onto is that vertical ridges alone, especially mild ones that have been present and stable for a long time, are rarely a reason for concern on their own.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Are Horizontal Ridges (Beau’s Lines)?

Horizontal ridges run across the nail, from one side to the other, perpendicular to the direction of growth. In medicine, these are called Beau’s lines, named after the French physician Joseph Honoré Simon Beau, who first described them in the 1800s.

Beau’s lines are a different story from vertical ridges, and this is the distinction most popular content online tends to blur. A horizontal ridge represents a temporary but real interruption in nail growth, meaning the nail matrix briefly slowed or stopped producing new cells at a normal rate.

That kind of interruption does not typically happen from ordinary aging. It usually happens because something significant occurred in the body: a high fever, a serious illness, a major nutrient deficiency, certain medications (including chemotherapy), a significant injury to the nail itself, or a period of major physical stress on the body.

This is the part of the story that makes nail ridges more than just a cosmetic curiosity: a horizontal ridge is, in a real sense, a small physical record of something your body went through, showing up weeks or months later as a visible line.

“I did not know the difference between vertical and horizontal nail ridges until I started researching this article, and once I understood it, I looked back at my own nails differently. The vertical lines I have had for years are just part of getting older, nothing more. But I remembered a single deep horizontal groove that showed up on one nail a few months after a bad flu a couple of years back, and suddenly that made complete sense. Your body keeps quiet records in strange places. This is one of them.”

Terry Tateossian, Founder of The House of Rose

How Can You Tell Vertical and Horizontal Nail Ridges Apart?

This distinction matters enough to spell out clearly.

Vertical and horizontal nail ridges comparison
  • Vertical ridges: Run from the cuticle to the nail tip, are usually present on most or all nails at once, tend to be fine and closely spaced, develop gradually over months or years, and are typically stable rather than appearing suddenly.
  • Horizontal ridges (Beau’s lines): Run across the width of the nail, may appear on one nail or several, are often a single distinct groove rather than multiple fine lines, can appear more suddenly (though they take time to grow into visibility, as explained in Section 7), and are more likely to be associated with a specific triggering event.

If you are looking at your own nails right now, direction is the fastest way to tell these apart: does the line run the long way (vertical, usually normal) or the short way, across the nail (horizontal, worth a closer look)?

What Causes Vertical Ridges?

  • Aging: The most common cause by far. As the nail matrix ages, its cell turnover process becomes slightly less smooth and even, producing the fine ridged texture so many people notice from midlife onward.
  • Reduced moisture retention in the nail: Nails, like skin, lose some of their natural moisture and elasticity with age, which can make existing ridges more visible and nails somewhat more prone to fine cracking at the tips.
  • Mild, common nutrient shortfalls: Iron, zinc, and B vitamins all play roles in healthy nail cell production, and mild shortfalls in any of these can subtly affect nail texture over time, discussed further in Section 8.
  • Skin conditions affecting the nail matrix: Conditions such as eczema or psoriasis, when they affect the skin around the nail matrix, can sometimes contribute to a ridged or otherwise irregular nail texture.
  • Genetics: Some people simply have a family tendency toward more pronounced vertical ridging than others, independent of any health factor.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Causes Horizontal Ridges (Beau’s Lines)?

  • Significant illness or high fever: Any illness serious enough to place real physiological stress on the body, particularly one involving a sustained high fever, can temporarily slow nail matrix activity.
  • Major nutrient deficiency: A significant, not mild, deficiency in nutrients like zinc or protein can interrupt normal nail growth enough to produce a visible line.
  • Certain medications: Chemotherapy drugs are one of the most well documented causes of Beau’s lines, given their direct effect on rapidly dividing cells, which includes the cells of the nail matrix.
  • Direct injury to the nail or nail matrix: A significant trauma to the base of the nail, such as a heavy object dropped on a finger, can produce a Beau’s line as the matrix recovers.
  • Uncontrolled diabetes: Poorly controlled blood sugar can affect circulation and cell turnover broadly throughout the body, including in the nail matrix.
  • Severe emotional or physical stress: While milder everyday stress is not generally considered a cause, an unusually severe period of physical or psychological stress, particularly if it disrupts sleep, nutrition, and overall physiological function significantly, has been associated with Beau’s lines in some clinical reports.
  • Certain skin and autoimmune conditions: Conditions that cause significant inflammation near the nail matrix, including some autoimmune conditions, can occasionally produce this pattern.
  • Peripheral vascular issues: Conditions that meaningfully reduce blood flow to the fingers or toes can, in some cases, disrupt nail matrix function enough to cause a horizontal ridge.

Can You Read a Timeline From a Beau’s Line?

This is one of the more useful, practical facts about Beau’s lines, and it is the reason a clinician might ask when you notice a particular ridge.

Because fingernails grow at a fairly predictable average rate of about 3 millimeters per month, and because a Beau’s line marks the exact moment nail growth was disrupted, you can estimate roughly how long ago the disrupting event happened by measuring how far the ridge has moved from the cuticle.

Beau’s line nail growth timeline infographic

For example, a Beau’s line sitting about halfway up the nail on a finger where the full nail is roughly 12 to 15 millimeters long suggests the disrupting event happened somewhere around two to three months earlier, based on typical growth rates.

Toenails grow more slowly than fingernails, roughly 1 millimeter per month, so the same measurement approach on a toenail would suggest a considerably longer timeframe.

This is not a precise science, since growth rate varies somewhat by individual, by finger, and by age, but it is accurate enough that many people are able to look back and connect a Beau’s line to a specific illness, medication, or stressful period a few months prior, once they do the rough math.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Can Vitamin or Mineral Deficiencies Cause Nail Ridges?

Nail health depends on an adequate supply of several specific nutrients, and meaningful shortfalls in any of them can affect nail texture, though it is worth being precise about how strong this connection actually is.

  • Iron: Iron deficiency is one of the more well documented nutritional causes of nail changes, including ridging and, in more advanced cases, a spoon-shaped nail concavity called koilonychia. Iron deficiency is also one of the most common nutrient deficiencies in midlife women, particularly those with heavy menstrual cycles during perimenopause.
  • Zinc: Zinc plays a direct role in cell division and protein synthesis, both essential to healthy nail growth, and deficiency has been associated with both vertical ridging and, in more severe cases, horizontal ridging.
  • B vitamins, particularly B7 (biotin) and B12: Biotin is widely marketed for nail health, and while the evidence for biotin supplementation improving nail strength in people who are not actually deficient is limited, a genuine biotin or B12 deficiency can measurably affect nail texture and strength.
  • Protein: Since nails are made of protein, inadequate overall protein intake can affect the quality of new nail growth, contributing to ridging, brittleness, or both.
  • The honest caveat: Mild vertical ridging in an otherwise healthy person eating a reasonably balanced diet is far more likely to reflect ordinary aging than any specific deficiency. Nutrient-related nail changes tend to be more noticeable, often more brittle and fragile rather than simply lined, and tend to improve once the underlying deficiency is corrected, which is a meaningfully different pattern than the gradual, stable ridging most people develop with age.

Can Nail Ridges Be Related to Thyroid Health?

The thyroid gland regulates metabolism throughout the body, including the rate of cell turnover in tissues like skin, hair, and nails.

Both an underactive thyroid (hypothyroidism) and an overactive thyroid (hyperthyroidism) have been associated with nail changes, including increased brittleness, ridging, and, in some hypothyroid cases, thickened or slow-growing nails.

This connection is particularly relevant for midlife women, since thyroid conditions become more common with age and are diagnosed more frequently in women than men.

If nail ridging appears alongside other potential thyroid symptoms, including fatigue, changes in weight, hair thinning, temperature sensitivity, or mood changes, it is worth mentioning the full picture to a doctor rather than focusing on the nails in isolation.

Why Do Nail Ridges Become More Common in Midlife?

Several midlife-specific factors make nail ridging, particularly vertical ridging, more common and often more noticeable during the perimenopause and menopause transition.

  • Estrogen’s role in nail health: Estrogen supports circulation and tissue hydration broadly throughout the body, and its decline through perimenopause and menopause is associated with the same kind of general tissue dryness that affects skin, and can affect nail texture and moisture as well.
  • Increased prevalence of thyroid conditions: As covered above, thyroid conditions become more common with age, adding another potential contributing factor during this life stage specifically.
  • Nutrient demands and absorption changes: Nutrient absorption and dietary patterns can shift with age, and as covered in Section 8, several key nail-supporting nutrients are worth paying particular attention to during this transition.
  • Cumulative effect, not sudden change: Most midlife nail ridging develops gradually rather than appearing suddenly, consistent with an aging-related process rather than a single triggering event, which is an important distinction from the more sudden appearance typical of Beau’s lines.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Can You Do About Vertical Ridges?

For most people, vertical ridges do not require treatment, since they are a normal part of aging rather than a problem to solve. That said, several practical steps can improve the appearance and texture of ridged nails for those who want to address them cosmetically or support overall nail health.

Tips for caring for vertical nail ridges
  • Keep nails and cuticles well moisturized: Applying a nourishing cuticle oil or hand cream regularly helps maintain nail flexibility and can reduce the visible prominence of fine ridges.
  • Buff gently, not aggressively: A gentle nail buffer can smooth the visible texture of mild vertical ridges, though over-buffing can thin and weaken the nail, so this should be done sparingly, no more than once every few weeks.
  • Support your nutrient intake: Adequate protein, iron, zinc, and B vitamin intake supports healthy ongoing nail growth, particularly relevant for midlife women given the factors covered in Sections 8 and 10.
  • Stay hydrated: As with skin, adequate hydration supports the overall health and flexibility of nail tissue.
  • Consider a ridge-filling base coat: For those who want a purely cosmetic solution, ridge-filling base coats are widely available and effectively smooth the visual appearance of the nail surface before polish application.
  • Be patient: Since nails grow slowly, any nutritional or lifestyle change will take several months to show up as a visible improvement in new nail growth, consistent with the growth-rate math covered in Section 7.

When Should You See a Doctor About Nail Ridges?

  • Mild, gradual vertical ridging with no other symptoms. Generally does not require medical attention and is a normal part of aging.
  • A distinct, new horizontal ridge (Beau’s line), particularly across multiple nails at once. Is worth mentioning to a doctor, especially if you cannot connect it to an obvious recent illness or injury, since it can occasionally point to an underlying condition worth investigating.
  • Ridging accompanied by other symptoms: (fatigue, unexplained weight change, hair thinning, changes in nail color or shape, pain, swelling around the nail) is worth a medical evaluation of the fuller picture rather than the nail change alone.
  • Sudden changes across all nails at once. Particularly in someone with a known chronic health condition or on new medication, are worth discussing with a physician, since medication side effects and systemic illness are common causes.
  • Nails that are also discolored, separating from the nail bed, unusually thick, or accompanied by pain. Warrant evaluation regardless of ridging, since these can indicate infection or other nail-specific conditions outside the scope of this article.

As with the earlobe crease discussed in a related THOR article, the most useful response to noticing a nail change is not alarm. It is simply paying attention, tracking whether it is new or long-standing, and mentioning it to your doctor as one data point among your overall health picture if anything feels off.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Other Nail Changes Are Worth Knowing About?

Nail ridges are one of several nail changes that can carry health-related significance. A brief, honest overview of a few others, without turning this article into a full nail pathology guide:

  • Pitting: Small, shallow depressions scattered across the nail surface, most commonly associated with psoriasis or other inflammatory skin conditions affecting the nail matrix.
  • Spoon nails (koilonychia): A concave, scooped-out nail shape, most classically associated with significant iron deficiency anemia.
  • Clubbing: A rounding and thickening of the fingertip and nail, associated with certain chronic lung and heart conditions, generally a more clinically significant finding than ridging.
  • White spots (leukonychia): Small white marks on the nail, most commonly caused by minor trauma to the nail as it was growing, rarely a sign of any deficiency despite a persistent popular myth linking it to calcium or zinc levels.
  • Yellowing: Can result from nail polish staining, fungal infection, or, less commonly, certain systemic conditions, and is worth evaluating separately from ridging.

What Are the Most Common Misconceptions About Nail Ridges?

Common myths and facts about nail ridges.
  1. Misconception: “Ridges always mean I’m deficient in something.” False for the vast majority of vertical ridging, which is simply a normal part of aging rather than a sign of deficiency.
  2. Misconception: “White spots on nails mean I need more calcium.” A long-standing popular myth without solid evidence behind it. White spots are almost always the result of minor trauma to the nail during growth, not a mineral deficiency.
  3. Misconception: “A single horizontal line is nothing to think about.” Not necessarily true. While an isolated Beau’s line is often traceable to a specific, already-resolved illness or injury, particularly if it appears on multiple nails at once, it is worth understanding rather than dismissing, especially if you cannot identify what caused it.
  4. Misconception: “Buffing or filing can permanently remove ridges.” False. Buffing can temporarily smooth the visible texture of existing nail, but since ridges originate at the nail matrix, they will continue to be present in new growth unless the underlying cause changes.
  5. Misconception: “Biotin supplements fix all nail ridging.” Partially false. Biotin supplementation has documented benefit specifically for people with an actual biotin deficiency, but has limited evidence for improving nail texture in people who are not deficient, which describes the majority of people with ordinary age-related vertical ridging.

This article is educational and is not a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of a qualified healthcare provider with any questions regarding a medical condition.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

Are nail ridges normal?

Vertical nail ridges are extremely common and, in the large majority of cases, a normal part of aging rather than a sign of a health problem. Horizontal ridges (Beau’s lines) are less common and more often associated with a specific illness, deficiency, medication, or injury.

What is the difference between vertical and horizontal nail ridges?

Vertical ridges run from the cuticle to the nail tip and are usually a normal age-related change. Horizontal ridges, called Beau’s lines, run across the width of the nail and represent a temporary interruption in nail growth, often linked to illness, major stress, or nutrient deficiency.

What vitamin deficiency causes nail ridges?

Iron, zinc, biotin, and B12 deficiencies have all been associated with nail texture changes, including ridging. That said, most ordinary vertical ridging in healthy adults is related to aging rather than deficiency.

Can stress cause ridges in nails?

Ordinary daily stress is not generally considered a cause of nail ridging. However, an unusually severe period of physical or psychological stress, particularly one that disrupts overall physiological function, has been associated with Beau’s lines in some clinical reports.

Do nail ridges mean I have a thyroid problem?

Not necessarily, but thyroid conditions can contribute to nail changes, including ridging and increased brittleness. If ridging appears alongside other possible thyroid symptoms like fatigue or unexplained weight change, it is worth mentioning to your doctor.

Can you get rid of nail ridges?

Vertical ridges cannot be permanently removed since they originate at the nail matrix and will continue in new growth, though gentle buffing and a ridge-filling base coat can improve their appearance. Since nails grow continuously, once an underlying cause (like a deficiency) is corrected, new nail growth will reflect that improvement over the following months.

How fast do nails grow, and why does that matter?

Fingernails grow at roughly 3 millimeters per month on average, and toenails grow more slowly, at roughly 1 millimeter per month. This growth rate is what allows a Beau’s line’s position on the nail to serve as a rough timestamp for when a disrupting event occurred.

Is it normal for nail ridges to get worse with age?

Yes. Vertical ridging tends to become more pronounced from midlife onward as part of the same general tissue-aging process that affects skin.

Should I worry about a single horizontal line on one nail?

Usually not, particularly if you can connect it to a recent illness, fever, or minor injury. If it appears on multiple nails at once, or you cannot identify a cause, it is reasonable to mention it to your doctor.

Do biotin supplements help with nail ridges?

Biotin supplementation has clear benefit for people with an actual biotin deficiency, but limited evidence for improving nail texture in people who are not deficient, which is the case for most people with ordinary age-related ridging.

Can nail polish or gel manicures cause ridges?

Frequent gel manicures and the buffing that often accompanies them can thin the nail plate over time and may make existing ridges more visible, though they are not typically considered a direct cause of new ridging.

What do white spots on nails mean?

Despite a common myth linking them to calcium or zinc deficiency, white spots on nails are most often the result of minor trauma to the nail during growth and are rarely a sign of any nutritional deficiency.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free Subscription.

Research and References

  • Beau, J. H. S. (1846). Recherches sur les causes et sur les caractères de plusieurs modifications qui surviennent dans la structure des ongles. Archives Générales de Médecine.
  • Fawcett, R. S., Linford, S., & Stulberg, D. L. (2004). Nail abnormalities: Clues to systemic disease. American Family Physician, 69(6), 1417-1424.
  • Singal, A., & Arora, R. (2015). Nail as a window of systemic diseases. Indian Dermatology Online Journal, 6(2), 67-74.
  • Cashman, M. W., & Sloan, S. B. (2010). Nutrition and nail disease. Clinics in Dermatology, 28(4), 420-425.
  • Tosti, A., Piraccini, B. M., & de Farias, D. C. (2009). Dealing with melanonychia. Seminars in Cutaneous Medicine and Surgery, 28(1), 49-54.
  • Iorizzo, M., Pazzaglia, M., Piraccini, B. M., Tullo, S., & Tosti, A. (2006). Brittle nails. Journal of Cosmetic Dermatology, 3(3), 138-144.
  • de Berker, D. (2009). Nail anatomy. Clinics in Dermatology, 27(5), 509-514.
  • Wright, K. E., Skinner, S., & Zhu, S. (2023). The musculoskeletal syndrome of menopause. Climacteric, 26(4), 366-371.

Disclaimer: This article is educational and does not constitute medical advice, diagnosis, or treatment. Nail ridges can have many causes, ranging from normal age-related changes to nutritional deficiencies, illness, medication effects, or other health conditions. Do not use nail appearance alone to diagnose a deficiency or medical problem. If you develop sudden horizontal ridges, changes across multiple nails, discoloration, pain, swelling, nail separation, or other concerning symptoms, consult a qualified healthcare provider for evaluation.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

The Aham Mantra: A Simple Guide to Sanskrit Mantras, How to Use Them & How to Change Yours

Marisol is forty-six. Most mornings, she sits in her car in the driveway for five extra minutes before going inside to start the day, because it is the only quiet she gets. She has tried three different meditation apps. Each one gives her a soft voice, a timer, and a vague instruction to “just notice your breath,” and each time her mind wanders off within thirty seconds, chasing her to-do list, a text she needs to answer, something she said in a meeting last week. She has started to think meditation just is not for her.

What Marisol had not tried yet was a mantra. Not a phrase she made up, not a positive affirmation printed on a mug, but one of the oldest tools in meditation: a short sound, repeated on purpose, that gives a busy mind something simple to hold onto instead of nothing at all. The first one she learned was aham, and it took her about a week to understand why something this small could work when a guided app could not.

This article explains aham, where it comes from, how to use it, what a few other well-known Sanskrit mantras mean, and how to know if it is time to try a different one. Nothing here requires a background in Sanskrit or a lifetime of yoga study. It is written to be as clear and simple as possible.

What Is a Mantra, Really?

A mantra is a word or sound you repeat on purpose during meditation. That is the whole idea. It sounds almost too simple, but the simplicity is exactly why it works.

The word “mantra” comes from Sanskrit, an ancient language from India used in many spiritual and yogic texts. It combines two smaller Sanskrit parts: man, which relates to the mind, and tra, which relates to a tool or instrument. Put together, a mantra is literally a tool for the mind.

Here is why that matters. Most people who try to meditate are told to “clear their mind” or “think of nothing,” which is one of the hardest instructions a human brain can follow. Minds are built to think. A mantra gives your mind a small, repeating job to do instead of fighting it into silence. Instead of trying to think of nothing, you gently think of one thing, on purpose, over and over, until your mind settles down around it the way a glass of shaken water settles when you stop shaking it.

Sanskrit mantras are not magic words. Their value comes from a combination of sound, meaning, and repetition, all working together to give a busy mind something steady to hold.

What Is the Aham Mantra, and What Does It Mean?

Aham (pronounced like the word “aha,” with a soft “m” sound at the end) is one of the simplest and oldest mantras used in meditation.

In Sanskrit, aham means “I” or “self.” Not your name, not your job title, not the version of you that answers emails. It points to something quieter and older than all of that: the simple sense of being a self at all, the “I am” that sits underneath every thought you have ever had.

When you repeat aham slowly, again and again, something interesting happens with the meaning. Said twice in a row, it starts to sound like “aham-aham,” or “I am I.” That repetition is not an accident. It is designed to turn your attention away from your busy thoughts and back toward the simple fact of being aware in the first place, the “I” behind everything you think, feel, and notice.

This is different from most meditation instructions you may have tried. Instead of pushing thoughts away, aham gently asks a question underneath all your thoughts: who, or what, is aware of all this? That question, repeated softly, is the entire practice.

Where Does Aham Come From?

Aham comes from a branch of Indian spiritual philosophy called tantra, which is often misunderstood in Western pop culture but, in its original form, is a serious and old tradition focused on awareness, energy, and the relationship between the two.

In this tradition, aham is explained through its three sounds, and each one carries its own simple meaning.

  • The “a” sound represents pure awareness, sometimes called Shiva in this tradition. Think of this as the open, quiet background of your mind, the part of you that notices things, before it labels or judges them.
  • The “ha” sound represents energy, movement, and expression, sometimes called Shakti. Think of this as everything that shows up inside that quiet background: your thoughts, feelings, plans, and the busy stream of daily life.
  • The “m” sound represents the point where those two things meet and become one, sometimes called the bindu, a Sanskrit word that simply means “point” or “drop”. Picture the small dot placed over certain Sanskrit letters. It stands for unity, the coming together of quiet awareness and active energy into a single, whole experience.

Put simply: aham is a tiny word that contains a big idea. It says that the quiet part of you and the busy part of you are not actually two separate things. They are one whole self, and the word aham reminds you of that every time you say it.

You do not need to memorize any of this philosophy to use the mantra. It is here so the word has meaning to you, not just sound.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Does Aham Connect With Your Breath?

Here is one of the most useful things to understand about aham: you are already saying it, all day, every day, without noticing.

Aham mantra breath meditation infographic

When you breathe in, the shape your throat and mouth naturally make produces something close to the “a” sound. When you breathe out, the natural exhale produces something close to the “ham” sound. Put the two together, and your ordinary breath is already whispering “aham, aham, aham,” quietly, in the background, for your entire life.

This is part of why the mantra feels natural once you try it. You are not adding something foreign to your body. You are simply noticing something your breath has been doing all along, and paying attention to it on purpose instead of letting it happen unnoticed.

Some meditation teachers describe this as your breath quietly declaring “I am” with every cycle, a small, constant reminder that you exist, are aware, and are alive, happening thousands of times a day whether you notice it or not.

“The first time someone explained to me that aham was already hiding inside my own breathing, it changed how the whole practice felt. It stopped being one more thing I had to do correctly, and started feeling like something I got to notice instead. That shift, from effort to noticing, is honestly the heart of most good meditation practices, not just this one.”

Terry Tateossian, Founder of The House of Rose

How Do You Practice the Aham Mantra Step by Step?

You do not need any equipment, an app, or prior experience. Find a quiet spot, sit comfortably, and follow these steps.

  • Step 1: Get comfortable: Sit somewhere you will not be disturbed for 5 to 15 minutes. You can sit cross-legged on the floor or in a chair with your feet flat on the ground. Keep your spine reasonably tall but not stiff.
  • Step 2: Settle your attention low in your body: Bring your attention to the area just below your belly button, slightly toward your spine. In yogic anatomy this spot is called the manipura chakra, a Sanskrit term for an energy center associated with personal power and steadiness. You do not need to feel anything special here. Simply resting your attention in this area is enough.
  • Step 3: Notice your natural breath: Do not change how you are breathing. Just notice the breath rising and falling.
  • Step 4: Add the mantra: As you breathe in, silently think the sound “a.” As you breathe out, silently think the sound “ham.” Do not say it out loud. Just think it, matched gently to the natural rhythm of your breath.
  • Step 5: Notice the pauses: Pay attention to the small, natural gaps that happen right after a full inhale and right after a full exhale. You do not need to do anything with these gaps. Just notice they are there.
  • Step 6: Let the words fade: After a few minutes, stop actively thinking the syllables. Instead, simply listen, as if the sound of aham were happening on its own, in the background, with each breath.
  • Step 7: Rest: Once your mind feels a little quieter, let go of tracking the breath altogether. Simply rest in a relaxed, alert stillness for the remaining time.

Fifteen minutes is a reasonable goal for beginners, but even five minutes done consistently is still worthwhile. Consistency matters far more than length.

What Should You Do If Your Breath Gets Very Quiet?

Something can happen during mantra practice that surprises a lot of beginners: your breath may become very slow, very soft, or seem to pause for a moment on its own.

This is normal, and it is not something to force or chase. If it happens, do not try to make it happen again on purpose, and do not try to hurry your breath back to normal either. Simply let it be exactly as quiet or as still as it wants to be, and stay gently aware. When the breath naturally returns to its normal rhythm, let it, without any effort on your part.

If this never happens for you, that is also completely normal. Many people meditate for years and simply notice a calm, steady breath rather than any dramatic pause, and that is a full, complete practice on its own.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Are Some Other Popular Sanskrit Mantras?

Aham is one of many Sanskrit mantras used in meditation. Here is a simple, honest guide to a few of the most common ones, what they mean, and what each one tends to be used for.

  • So Hum (pronounced “so hum”): This mantra means “I am That,” where “That” refers to the vast, universal awareness behind all existence, rather than your individual sense of self. It uses the same breath-based approach as aham: “so” on the inhale, “hum” on the exhale. Many teachers consider it a close companion to aham, with a slightly more expansive, less personal feel. If aham points inward to “I am,” so hum points outward to “I am part of everything.”
  • Om (pronounced “aum,” a single, long syllable): Considered by many traditions to be the original sound of the universe itself, often chanted aloud rather than repeated silently. It is one of the most recognized sounds in yoga and meditation worldwide and works well as an opening or closing sound for a practice, or as a full mantra on its own for those who enjoy chanting.
  • Om Namah Shivaya (pronounced “om nah-mah shee-vah-yah”): This means roughly “I bow to my true, highest self,” using the word Shiva here to refer to the inner divine self rather than only the deity of the same name. It is one of the most widely used devotional mantras and works well for anyone drawn to a slightly longer phrase with a reverent, humble tone.
  • Om Mani Padme Hum (pronounced “om mah-nee pahd-may hum”): A Buddhist mantra, not originally Sanskrit but Tibetan in common use, associated with compassion. Its literal translation is debated among scholars, but it is widely understood to invoke compassion for oneself and others. A good option for anyone whose meditation goal centers on kindness rather than self-inquiry.
  • Lokah Samastah Sukhino Bhavantu (pronounced “loh-kah sah-mah-stah soo-key-noh bah-vahn-too”): A longer Sanskrit phrase meaning roughly “May all beings everywhere be happy and free.” It is less commonly repeated silently and more often chanted or recited once or twice at the start or end of a practice, functioning more like a dedication or intention than a repeated mantra.
  • Sat Nam (pronounced “saht nahm”): Common in Kundalini yoga practices, meaning roughly “truth is my identity” or “true name.” Popular for beginners because it is short, rhythmic, and pairs easily with simple hand movements or breath.

None of these mantras is objectively “better” than another. They simply carry different meanings and different emotional tones, which is exactly why it is worth trying more than one before settling on the mantra that feels right for you.

How Do You Choose the Right Mantra for You?

There is no single correct way to pick a mantra, but a few simple questions can help.

How to choose the right mantra infographic
  • What are you looking for right now?: If you want to feel more grounded in your own sense of self, aham is a strong starting point. If you want to feel more connected to something bigger than yourself, so hum may resonate more. If you are drawn to compassion and kindness practices, om mani padme hum may fit better.
  • Does the sound feel comfortable to say?: A mantra you find awkward to pronounce or uncomfortable to repeat will quietly work against you. Say a few candidates out loud a handful of times and notice which one feels natural in your mouth and calming in your body.
  • Do you want a short, breath-paired mantra or a longer, spoken one?: Aham and so hum are built for quiet, breath-paired repetition. Longer phrases like lokah samastah work better as a spoken opening or closing line rather than a repeated inner mantra.
  • Trust a gentle sense of rightness: Many longtime meditators describe simply feeling drawn to one mantra over another, without a fully logical reason. That instinct is worth trusting. There is no wrong choice among genuine, traditional mantras.

Can You Change Your Mantra, and How Do You Do It?

This is one of the most common questions beginners ask, and the honest answer is simple: yes, you can change your mantra, and doing so does not undo any progress you have already made.

Why People Change Mantras

Some people start with one mantra because it was the first one they learned, then later discover that a different one fits their current season of life better. Someone going through grief, for example, may feel more drawn to a compassion-centered mantra like om mani padme hum than the more self-inquiry-focused aham.

Someone working on connecting with a larger sense of purpose may move from aham toward so hum. Needs change over time, and it is completely normal for a mantra practice to change along with them.

When It Makes Sense to Change

A good sign that it may be time to try something new is when your current mantra starts to feel flat, mechanical, or disconnected from what you actually need right now, rather than calming or centering the way it once did. This is not failure. It is simply a signal that your practice is ready to grow.

When It Does Not Make Sense to Change

If your mantra still feels calming and useful but your mind is simply having a distracted day, that is not a sign to switch mantras. Minds wander during meditation regardless of which mantra you use, and switching mantras every time a session feels hard can prevent you from building the deeper familiarity that makes a mantra more meaningful over time.

How to Make the Switch

There is no formal ritual required. Simply choose your new mantra, learn its meaning the way this article has explored aham, and begin using it in the same way: paired gently with the breath, repeated without force, and allowed to grow quieter over time.

Some people like to mark the change with a small moment of intention, such as a few minutes of silence before beginning the new practice, but this is a personal preference rather than a requirement.

You Can Also Use More Than One Mantra

Some practitioners keep two mantras in rotation. For example, you might use aham in the morning to center yourself for the day and a compassion-focused mantra like om mani padme hum in the evening to soften and unwind. There is no rule against this. The right structure is the one that genuinely supports your life.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Common Mistakes Do Beginners Make?

  • Trying too hard to “do it right”: Mantra meditation is not a performance. A wandering mind, an inconsistent pace, or an imperfect pronunciation does not ruin the practice.
  • Forcing the breath to slow down or stop: As covered in Section 6, any natural quieting of the breath should be allowed to happen, never forced.
  • Switching mantras too often: As covered in Section 9, real familiarity with a mantra takes time. Switching every few days prevents that familiarity from developing.
  • Expecting instant results: Like most practices, mantra meditation tends to deepen gradually. A single session rarely produces a dramatic experience, and that is completely normal.
  • Skipping the meaning: Repeating a sound with no idea what it means still has some calming value, purely from the rhythm and repetition, but understanding what you are actually saying (as this article has tried to explain clearly for aham) tends to deepen the practice considerably.
  • Only meditating when life feels calm: The real value of a mantra practice often shows up most clearly on difficult days, not easy ones. A consistent practice, even five minutes on a hard day, tends to matter more than a long practice reserved only for peaceful mornings.

How Can You Build a Simple Daily Mantra Habit?

Daily mantra habit tips infographic
  • Start small: Five minutes a day, at a consistent time, beats twenty minutes done occasionally. Consistency is what builds familiarity with a mantra over time.
  • Anchor it to something you already do: Right after you wake up, right before brushing your teeth, or right after your morning coffee are all natural anchor points that make a new habit easier to remember.
  • Keep a simple written note nearby the first few weeks: A small card with the mantra, its meaning, and the basic steps (like the ones in Section 5) can help while you are still building familiarity.
  • Do not skip days out of guilt: If you miss a day, simply begin again the next day. A mantra practice built on guilt tends not to last; one built on gentle consistency does.
  • Notice small shifts, not dramatic ones: Most people notice subtle changes first: slightly steadier reactions during a stressful moment, a little more patience by the end of a hard day, a small sense of returning to yourself faster after being pulled in a dozen directions. These small shifts are the practice working.

What Does Research Say About Mantra Meditation?

  • Stress and the nervous system: Research on mantra-based meditation practices has documented reductions in markers of stress and improvements in measures of relaxation and parasympathetic (rest-and-digest) nervous system activity, consistent with the calming effects many practitioners describe anecdotally.
  • Attention and focus: Studies on repetitive, sound-based meditation techniques have found associated improvements in sustained attention and a reduced tendency for the mind to wander, supporting the practical mechanism described throughout this article: giving the mind one simple, repeated thing to hold onto.
  • Anxiety: Several studies on mantra-based meditation approaches have found associated reductions in self-reported anxiety symptoms, though as with most meditation research, effects vary by individual and by the consistency of practice.
  • Honest limitations: Much of the research in this area involves relatively small studies, and mantra meditation should be understood as a supportive practice for general well-being and stress management rather than a treatment for diagnosed anxiety disorders or other mental health conditions, which deserve care from a qualified professional.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Can You Bring This Practice Into the Broader THOR Framework?

A mantra practice can fit naturally alongside other THOR tools that support stress relief, nervous system regulation, and deeper restorative practices.

  • Pair it with nervous system support: Use mantra meditation alongside simple breathing and vagus nerve exercises to help create a calmer, more grounded daily routine. Explore these vagus nerve reset exercises for additional techniques.
  • Build it into your stress routine: A five-minute mantra practice can become one small, repeatable habit for managing everyday stress. These tiny stress habits offer other practical ways to support that routine.
  • Take the practice deeper in person: Guided meditation can help you become more comfortable with mantra practice and refine how you use it. THOR’s Deeply Restorative Yoga and Nature Retreat in the Smoky Mountains includes guided meditation as part of a more immersive restorative experience.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

What does aham mean?

Aham is a Sanskrit word meaning “I” or “self.” As a mantra, it points to the simple, quiet sense of being aware, the “I am,” that sits underneath all of your individual thoughts and feelings.

How do you pronounce aham?

Like the word “aha,” followed by a soft “m” sound. Some teachers pronounce it closer to “ah-hum.”

Is aham a religious practice?

Aham comes from a spiritual and philosophical tradition (tantra) with roots in Hindu thought, but it is widely practiced today as a secular meditation tool, without requiring any particular religious belief. Many people from many different backgrounds use it simply as a calming, centering practice.

Do I need to know Sanskrit to use a mantra?

No. You only need to know how to pronounce the sound and understand its basic meaning, both of which this article explains in plain language.

How long should I meditate with a mantra?

Five to fifteen minutes is a reasonable range for most beginners. Consistency matters far more than length. A short daily practice is more valuable than an occasional long one.

Can I say the mantra out loud instead of silently?

Yes. Both approaches are traditional and valid. Silent, breath-paired repetition (as described in Section 5) tends to be easier for beginners to sustain, while spoken or chanted repetition can feel more expressive and is common with mantras like om.

Is it okay to switch mantras?

Yes. As covered in Section 9, changing mantras as your needs change is completely normal and does not undo any benefit from your previous practice.

What is the difference between aham and so hum?

Aham means “I” and points inward, toward your individual sense of self and awareness. So hum means “I am That” and points outward, toward a sense of connection with something larger than the individual self. Many people use aham first and move toward so hum later, though there is no required order.

Can mantra meditation help with anxiety?

Some research supports mantra meditation as a helpful tool for managing everyday stress and anxiety symptoms, though it should be treated as a supportive practice, not a replacement for professional mental health care when needed.

What if I forget the mantra or lose my place while meditating?

Simply notice this happened, without frustration, and gently return to the mantra. Losing your place and returning is part of the practice itself, not a mistake to avoid.

Do I need any special equipment to practice a mantra?

No. A quiet space and a few minutes of time are the only requirements. A cushion or chair for comfortable sitting is helpful but not necessary.

Can children or teenagers use mantra meditation?

Simple, short mantras can be appropriate for older children and teenagers as an introduction to mindfulness, though guidance from a parent, teacher, or qualified instructor is recommended when introducing meditation to younger practitioners.

References

  • Lynch, J., Prihodova, L., Dunne, P. J., Carroll, Á., Walsh, C., McMahon, G., & White, B. (2018). Mantra meditation for mental health in the general population: A systematic review. European Journal of Integrative Medicine, 23, 101-108.
  • Bormann, J. E., Thorp, S. R., Wetherell, J. L., Golshan, S., & Lang, A. J. (2013). Meditation-based mantra intervention for veterans with posttraumatic stress disorder: A randomized trial. Psychological Trauma: Theory, Research, Practice, and Policy, 5(3), 259-267.
  • Wolf, D. B., & Abell, N. (2003). Examining the effects of meditation techniques on psychosocial functioning. Research on Social Work Practice, 13(1), 27-42.
  • Manocha, R., Black, D., Sarris, J., & Stough, C. (2011). A randomized, controlled trial of meditation for work stress, anxiety and depressed mood in full-time workers. Evidence-Based Complementary and Alternative Medicine, 2011, 960583.
  • Feuerstein, G. (1998). Tantra: The Path of Ecstasy. Shambhala Publications.
  • Muktibodhananda, S. (1998). Hatha Yoga Pradipika. Yoga Publications Trust.

Disclaimer: This article is educational and does not constitute medical or mental health advice. Mantra meditation can be a supportive practice for relaxation, focus, and everyday stress, but it is not a treatment for anxiety disorders or other mental health conditions. Do not force your breathing, hold your breath, or try to create breath pauses during meditation. If meditation causes dizziness, significant discomfort, panic, or emotional distress, stop the practice and consult a qualified healthcare or mental health professional.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.