$200 Off All 2027 Early Bird Discount

Settle the mind, restore the body & soul back to health. Our deeply restorative 5-day retreat is for midlife women 40+ who are ready to receive abundance, feel rested, strong, clear & back in alignment with their intentions. 

The 5-Minute Meditation (or 5-Second) Practice That Sticks

Diane signed up for a meditation app in January, the kind with the soothing narrator and the streak counter. She was consistent for eleven days. Then her mother had a fall, her work calendar filled back in, and the app notification became one more thing she swiped away without opening. By March she’d deleted it, and she told me she felt like she’d failed at the one thing that was supposed to make the rest of her life easier to carry.

She hadn’t failed. The model had failed her. Thirty uninterrupted minutes on a cushion is a real practice and a real privilege, and it assumes a version of a day that most women in their 40s and 50s, managing a household, a job, aging parents, and a body going through its own upheaval, simply do not have. What Diane needed wasn’t more discipline. She needed a version of the practice that could survive contact with her actual life.

That version exists, and it has a name: micro-meditations, brief conscious pauses dropped into the middle of ordinary activity rather than scheduled around it. This guide covers what they are, the real behavioral science behind why brief, cue-triggered practices tend to stick better than long, unanchored ones, and a full working set of examples you can start using today.

What Is a Micro-Meditation?

A micro-meditation is a short period of focused, conscious attention, anywhere from a single breath to five minutes, performed in the middle of your day rather than set apart from it. It can happen while you’re doing something else entirely: showering, driving, waiting for a kettle to boil, walking from your car to a building. The defining feature isn’t length. It’s that the practice travels with you instead of requiring you to stop your life to access it.
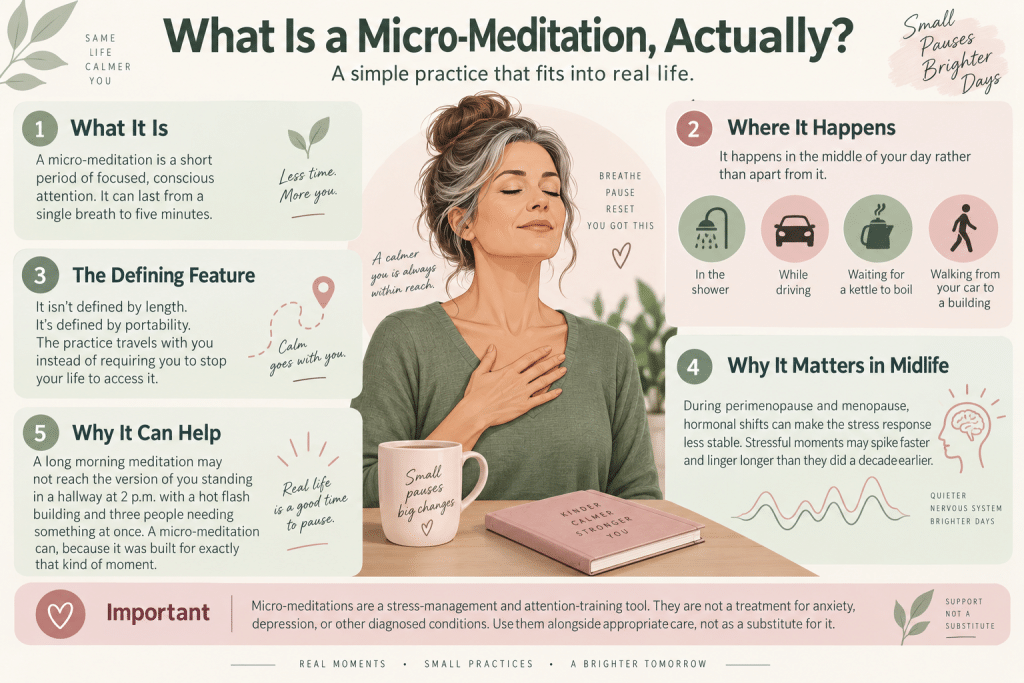
Midlife woman practicing a micro-meditation.

This matters more in midlife than most meditation content acknowledges. Hormonal shifts during perimenopause and menopause are associated with a measurably less stable stress response, meaning a stressful moment can spike and linger longer than it did a decade earlier.

A single long morning session, however good, doesn’t reach the version of you standing in a hallway at 2 p.m. with a hot flash building and three people needing something from you at once. A micro-meditation can, because it was built to live inside exactly that kind of moment.

Important: Micro-meditations are a stress-management and attention-training tool, not a treatment for anxiety, depression, or other diagnosed conditions. Use them alongside appropriate care, not as a substitute for it.

“I hear the same story from almost every woman I coach: she tried meditation, it didn’t stick, and she decided she’s ‘just not someone who can meditate.’ What actually happened is she was handed a format that assumes a spacious, uninterrupted life. Give her a version that fits into the fifteen seconds she has between hanging up one call and starting the next, and something completely different happens.”

Terry Tateossian, Founder of The House of Rose

Why Do Short, Cue-Triggered Practices Stick Better?

There’s a real behavioral science reason micro-meditations tend to outlast the thirty-minutes-a-day resolution, and it has nothing to do with willpower.

Habits form most reliably when a specific, existing cue in your environment gets linked to a specific, small response, a principle behavior researcher BJ Fogg built an entire habit-design method around: attach the new behavior to something you already do every day, and make the new behavior small enough that it doesn’t require motivation to execute.

A widely cited 2010 study on habit formation found that behaviors performed consistently in response to a stable daily cue became automatic, meaning they stopped requiring conscious effort, in an average of about 66 days, though the range across participants and behaviors was wide, from 18 days for simpler habits to well over 200 for more complex ones. The mechanism that made the difference wasn’t intensity. It was consistency tied to a reliable trigger.

That’s the exact structure a micro-meditation practice uses. Instead of relying on remembering to carve out thirty free minutes, a specific daily moment you already experience, your first sip of coffee, the walk from your car, the sound of your phone unlocking, becomes the cue, and a ten-second pause becomes the response. Over weeks, the pause stops requiring a decision. It becomes part of what that moment already means to you.

Longer seated practice can help build the same attentional skills through sustained stillness, which the neuroscience of meditation helps explain in more depth. Here, the focus is on carrying that quality of attention into everyday life, especially when your surroundings, schedule, and responsibilities refuse to stay still.

$200 Off All 2027 Early Bird Discount

Settle the mind, restore the body & soul back to health. Our deeply restorative 5-day retreat is for midlife women 40+ who are ready to receive abundance, feel rested, strong, clear & back in alignment with their intentions. 

What Are Some Micro-Meditations for Your Morning?
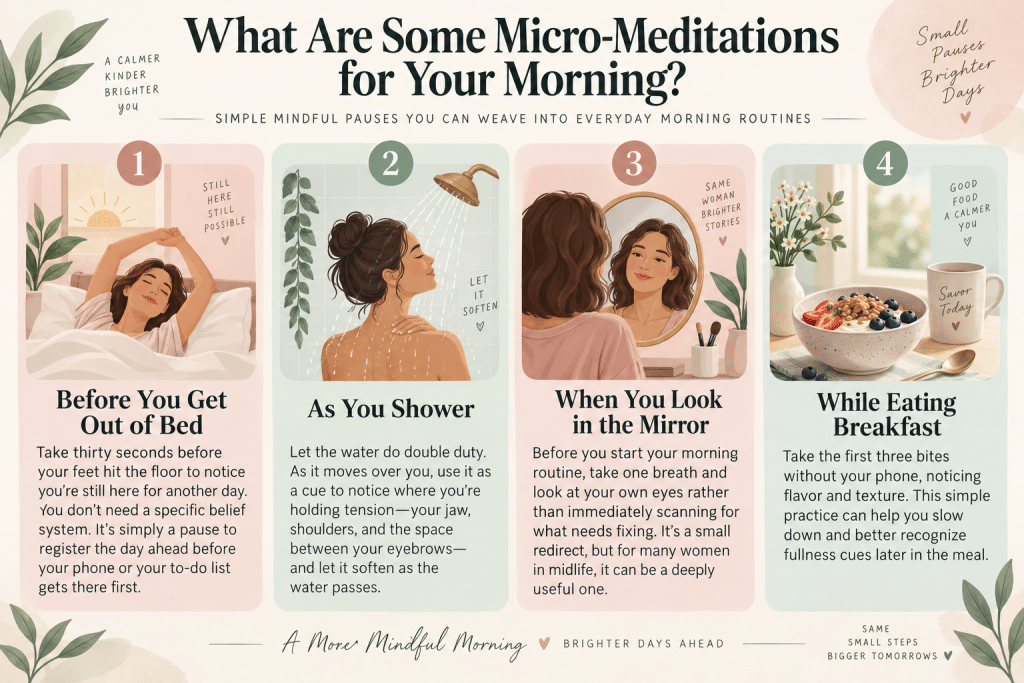
Morning micro-meditation ideas for women
  • Before you get out of bed: Take thirty seconds before your feet hit the floor to notice you’re still here for another day. You don’t need a specific belief system for this one. It’s simply a pause to register the day ahead before your phone or your to-do list gets there first.
  • As you shower: Let the water do double duty. As it moves over you, use it as a physical cue to notice where you’re holding tension, jaw, shoulders, the space between your eyebrows, and let it soften as the water passes. This takes the same amount of time as an ordinary shower; it just adds a layer of attention to something you were doing anyway.
  • When you look in the mirror: Before you start your morning routine, take one breath and look at your own eyes rather than immediately scanning for what needs fixing. It’s a small redirect, and for many women in midlife, whose relationship with the mirror has gotten complicated, an actually useful one.
  • While eating breakfast: Take the first three bites without your phone, noticing flavor and texture specifically. This one has a practical bonus beyond the meditative value: eating the first portion of a meal with attention is associated with better recognition of fullness cues later in the meal.

What Are Some Micro-Meditations for Work and Transitions?

  • Before answering the phone or starting a call: Take one breath before you say hello. It costs you less than two seconds and it changes the tone you lead with, especially on a day that’s already stacked with back-to-back calls.
  • As you start your car: Before you pull out of the driveway, take one breath and set an intention for how you want to show up in whatever is next, rather than immediately replaying whatever just happened.
  • When you sit down to start work: Take a moment to notice your posture and your breath before opening your first email or message. This is the moment most likely to get skipped entirely, which makes it one of the more valuable ones to anchor deliberately.
  • Between meetings or appointments: Use the gap, even sixty seconds, as a hard reset rather than an extension of the last conversation or a preview of the next one. Close your eyes if you can, take three slow breaths, and let your shoulders drop before you move to whatever’s next.

$200 Off All 2027 Early Bird Discount

Settle the mind, restore the body & soul back to health. Our deeply restorative 5-day retreat is for midlife women 40+ who are ready to receive abundance, feel rested, strong, clear & back in alignment with their intentions. 

What Are Some Micro-Meditations for Movement and the Body?

  • During a workout: Let a few minutes of your session become moving meditation. Notice that your legs are moving, your lungs are expanding, and your heart is working, largely without your conscious direction, the same way digestion happens without you managing it. You don’t have to control the process to benefit from paying attention to it.
  • After a workout: Before you rush to the next task, take sixty seconds to simply sit in what your body just did, rather than immediately moving into recovery logistics or the rest of your to-do list.
  • When you get home: Before you walk through the door into whatever’s waiting, whether it’s kids, a partner, or an empty house that has its own demands, take thirty seconds in the car or on the porch to arrive fully in your body before you arrive in the house.

What Are Some Micro-Meditations for Hard Emotions?
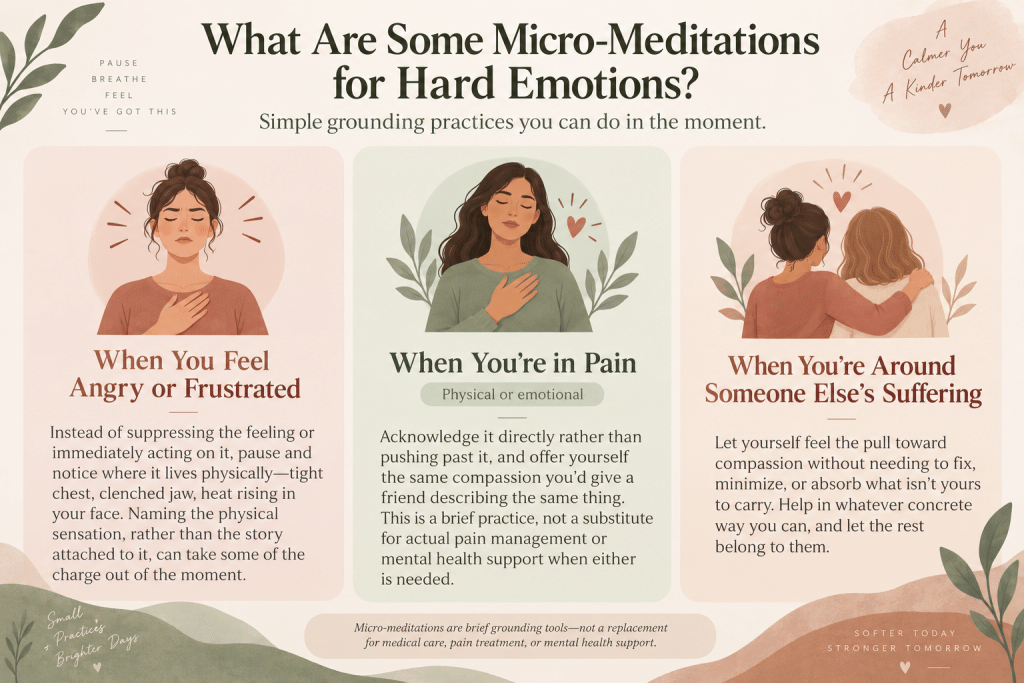
Micro-meditations for hard emotions
  • When you feel angry or frustrated: Instead of suppressing the feeling or immediately acting on it, pause and notice where it lives physically, a tight chest, a clenched jaw, heat rising in your face. Naming the physical sensation, rather than the story attached to it, tends to take some of the charge out of the moment.
  • When you’re in pain, physical or emotional: Acknowledge it directly rather than pushing past it, and extend yourself the same compassion you’d offer a friend describing the same thing. This is a brief practice, not a substitute for actual pain management or mental health support when either is needed.
  • When you’re around someone else’s suffering: Let yourself feel the pull toward compassion without needing to fix, minimize, or absorb what isn’t yours to carry. Help in whatever concrete way you’re able to, and let the rest be theirs.

$200 Off All 2027 Early Bird Discount

Settle the mind, restore the body & soul back to health. Our deeply restorative 5-day retreat is for midlife women 40+ who are ready to receive abundance, feel rested, strong, clear & back in alignment with their intentions. 

What Are Some Micro-Meditations for Connection and Evening?

  • When hugging someone you love: Stay in the hug two seconds longer than usual, and actually notice that you’re there, rather than already mentally moving to the next thing.
  • When watching a sunset, or any view that stops you: Let yourself take it in without reaching for your phone to photograph it first. The moment is available to you directly; the photo is a record of it after the fact.
  • When lying down to sleep: Take a moment to register the day that just happened, without reviewing every item on the to-do list you didn’t finish. One thing that went right is enough.

How Can You Build Triggers So You Remember?

The single biggest obstacle to this practice isn’t the practice itself. It’s forgetting. A full day can pass before you notice you haven’t taken one conscious breath, and that’s not a personal failing, it’s what happens by default in an environment designed to keep your attention elsewhere.
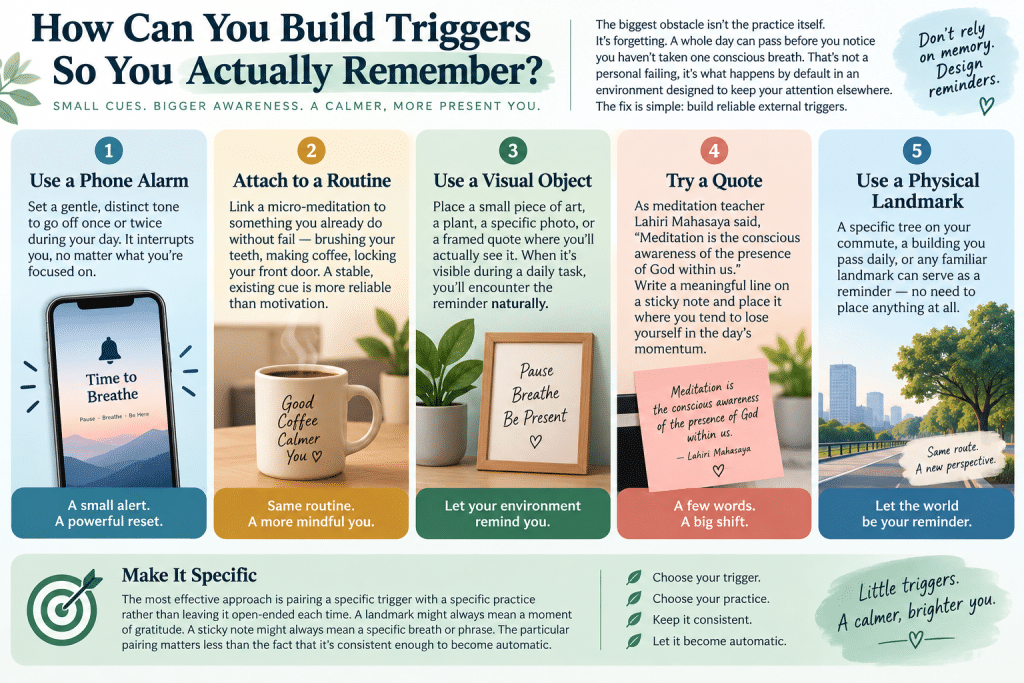
Building simple triggers for daily mindfulness.

The fix is building reliable external triggers rather than relying on remembering. A phone alarm with a distinct, calming tone set to go off once or twice during your day works well because it interrupts you regardless of what you’re focused on. Attaching a micro-meditation to a routine you already do without fail, brushing your teeth, making coffee, locking your front door, works for the same reason the 2010 habit research pointed to: a stable, existing cue is more reliable than motivation.

A visual object placed somewhere you’ll actually see it, a small piece of art, a plant, a specific photo, a framed quote, can work as well; keeping one where it’s visible during a task you do daily means you’ll encounter the reminder without having to remember to look for it.

As the meditation teacher Lahiri Mahasaya put it, “Meditation is the conscious awareness of the presence of God within us,” a line worth writing on a sticky note near wherever you tend to lose yourself in the day’s momentum, whatever word you’d use in place of God. A physical landmark on a regular route, a specific tree on your commute, a building you pass daily, can serve the same function without you having to place anything at all.

The most effective approach is pairing a specific trigger with a specific practice rather than leaving it open-ended each time. A landmark might always mean a moment of gratitude. A sticky note might always mean a specific breath or phrase. The particular pairing matters less than the fact that it’s consistent enough to become automatic, the same principle that made the habit-formation research findings hold up across such a wide range of behaviors.

$200 Off All 2027 Early Bird Discount

Settle the mind, restore the body & soul back to health. Our deeply restorative 5-day retreat is for midlife women 40+ who are ready to receive abundance, feel rested, strong, clear & back in alignment with their intentions. 
What Are Your Next Steps?

  1. Pick one trigger to start with. Don’t try to install all fourteen examples at once; choose one moment you already experience daily and attach a single micro-meditation to it this week.
  2. Set one phone reminder. A single daily alarm with a calming tone is enough to start building the habit loop described in Section 2.
  3. Give it the full runway. Based on the habit-formation research cited above, expect it to take weeks, not days, before the pause starts happening without you deciding to do it.
  4. Pair it with a longer practice if you want one. Micro-meditations can complement a seated practice by helping you carry mindful attention into the rest of your day, while understanding the neuroscience of meditation can give you more context for what longer periods of stillness add.
  5. Bring the practice into a retreat setting. THOR’s women’s yoga, hiking & wellness retreats weave guided moments of mindfulness and restorative practice throughout the day, giving you a supportive way to experience cue-based attention before building your own routine at home.

$200 Off All 2027 Early Bird Discount

Settle the mind, restore the body & soul back to health. Our deeply restorative 5-day retreat is for midlife women 40+ who are ready to receive abundance, feel rested, strong, clear & back in alignment with their intentions. 
Frequently Asked Questions

What’s the difference between a micro-meditation and regular mindfulness?

Mindfulness is the broader skill of paying attention on purpose; a micro-meditation is one specific, brief way of practicing it, anchored to a particular moment or trigger rather than an open-ended state you try to maintain all day.

How long should a micro-meditation last?

Anywhere from a single breath to about five minutes. The length matters less than the consistency of the trigger you attach it to.

Do I need to sit down or close my eyes?

No. Many of the examples in this guide happen while you’re doing something else entirely, showering, driving, working out. Eyes-closed stillness is one option, not a requirement.

Can micro-meditations replace a longer meditation practice?

Micro-meditations can stand on their own, and for many women they’re the only practice that consistently survives a busy season. They also pair well with longer seated sessions, where the neuroscience of meditation helps explain the additional benefits of sustained attention and stillness beyond what brief pauses can provide.

How do I remember to do this?

Build a trigger rather than relying on memory: a phone alarm, a visual cue placed somewhere you’ll see it, or attaching the practice to a routine you already do without fail. Section 8 covers this in depth.

How long does it take before this becomes a real habit?

Based on habit-formation research, expect an average of around 66 days of consistent practice before it starts happening automatically, though this varies widely by person and by how simple the specific practice is.

Is this connected to any particular religion?

No specific religious belief is required. The language in this guide uses words like Presence or Spirit in places, and you’re welcome to substitute whatever term fits your own framework, including a purely secular one focused on attention and the present moment.

Can micro-meditations help with hot flashes or menopause-related stress spikes?

There’s no research isolating micro-meditations specifically for hot flashes. What’s reasonably well supported is that brief attention and breath practices can help you meet a stress spike, including the kind that can accompany a hot flash, without adding a layer of panic on top of the physical sensation.

What if I try a trigger and it doesn’t work?

Switch it. Not every cue sticks for every person. If a phone alarm gets ignored, try attaching the practice to a physical routine instead, or vice versa.

Can I do this with kids or a busy household around me?

Yes, several of the examples, the shower pause, the pre-call breath, the post-workout moment, work specifically because they don’t require a quiet room or uninterrupted time.

Is a single breath really enough to count as meditation?

A single conscious breath, done with genuine attention, meets the definition used in this guide. Depth of attention matters more than duration.

What if I forget for several days in a row?

Start again without treating the gap as a failure. The habit-formation research this guide draws on is about consistency over time, not an unbroken streak.

Do I need a meditation app or special equipment?

No. Every example in this guide uses something you already have: your breath, an ordinary daily activity, and a trigger you set up yourself.

Can this practice be combined with sound-based practices like a singing bowl?

Yes. A singing bowl or a few minutes of humming can become both the cue and the practice itself, making sound an easy trigger for a brief mindful pause. A simple singing bowl and voice practice can help you turn that idea into a repeatable routine without needing a long meditation session.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.

References

  • Fogg, B.J. (2019). Tiny Habits: The Small Changes That Change Everything. Houghton Mifflin Harcourt.
  • Lally, P., van Jaarsveld, C.H.M., Potts, H.W.W., & Wardle, J. (2010). How Are Habits Formed: Modelling Habit Formation in the Real World. European Journal of Social Psychology, 40(6), 998-1009.
  • Wood, W., & Neal, D.T. (2007). A New Look at Habits and the Habit-Goal Interface. Psychological Review, 114(4), 843-863.
  • Cahn, B.R., & Polich, J. (2006). Meditation States and Traits: EEG, ERP, and Neuroimaging Studies. Psychological Bulletin, 132(2), 180-211.
  • Robinson, E., Aveyard, P., Daley, A., et al. (2013). Eating Attentively: A Systematic Review and Meta-Analysis of the Effect of Food Intake Memory and Awareness on Eating. American Journal of Clinical Nutrition, 97(4), 728-742.
  • National Center for Complementary and Integrative Health (NCCIH). Meditation and Mindfulness: What You Need to Know.
  • Gordon, J.L., Girdler, S.S., Meltzer-Brody, S.E., et al. (2015). Ovarian Hormone Fluctuation, Neurosteroids, and HPA Axis Dysregulation in Perimenopausal Depression. American Journal of Psychiatry, 172(3), 227-236.
  • Kabat-Zinn, J. (1994). Wherever You Go, There You Are: Mindfulness Meditation in Everyday Life. Hyperion.
  • Jha, A.P., Krompinger, J., & Baime, M.J. (2007). Mindfulness Training Modifies Subsystems of Attention. Cognitive, Affective, & Behavioral Neuroscience, 7(2), 109-119.
  • Creswell, J.D. (2017). Mindfulness Interventions. Annual Review of Psychology, 68, 491-516.
  • Gardner, B., Lally, P., & Wardle, J. (2012). Making Health Habitual: The Psychology of Habit-Formation and General Practice. British Journal of General Practice, 62(605), 664-666.
  • American Psychological Association. Mindfulness Meditation: A Research-Proven Way to Reduce Stress.

Disclaimer: This article is educational and does not constitute medical or mental health advice. Micro-meditations are intended as stress-management and attention-training practices, not as treatment for anxiety, depression, chronic pain, hot flashes, or other diagnosed conditions. Use these practices alongside appropriate professional care when needed, and avoid closing your eyes or doing any exercise that distracts you while driving, operating equipment, or performing activities that require your full attention.

$200 Off All 2027 Early Bird Discount

Settle the mind, restore the body & soul back to health. Our deeply restorative 5-day retreat is for midlife women 40+ who are ready to receive abundance, feel rested, strong, clear & back in alignment with their intentions. 
$200 Off All 2027 Early Bird Discount

Settle the mind, restore the body & soul back to health. Our deeply restorative 5-day retreat is for midlife women 40+ who are ready to receive abundance, feel rested, strong, clear & back in alignment with their intentions. 
How Sound Healing Recalibrates the Nervous System

In Norway in the early 1980s, a special-education researcher named Olav Skille was working with children who had severe developmental disabilities, many of them nonverbal, several with limited ability to tolerate typical sensory environments. Skille began experimenting with low-frequency sound played through speakers built directly into chairs and mats, so the children could feel the vibration through their bodies rather than only hear it through their ears.

He documented something his colleagues hadn’t expected: children who struggled to stay regulated in ordinary environments visibly calmed, their muscle tension easing, during and after these low-frequency sessions. Skille went on to coin the term “vibroacoustic therapy” for the approach, and it has since been studied, in a small but real body of clinical literature, for muscle tension, pain, and general relaxation.

I open with Skille’s work because it’s the most rigorously documented piece of a much bigger claim you’ll see all over the sound healing world: that a singing bowl, a gong, or a sound bath can “recalibrate your nervous system.”

That phrase gets used constantly, and it’s usually followed by a bundle of six different claims stacked on top of each other, some backed by real research, some backed by almost nothing beyond how convincing they sound.

Medical disclaimer: This article is for educational purposes and does not replace medical or mental health care, including trauma-focused therapy. Sound-based practices are a complement to treatment, not a substitute for it. If you have epilepsy, a seizure disorder, or a diagnosed trauma history, talk with a qualified provider before starting a new sound-based practice.

How Does the Sympathetic-to-Parasympathetic Shift Work?

Your autonomic nervous system runs on two main branches. The sympathetic branch mobilizes you, raising heart rate, redirecting blood flow to muscle, sharpening alertness, useful when you need to act fast and counterproductive when you’re just sitting in traffic. The parasympathetic branch does close to the opposite: slowing heart rate, supporting digestion, and signaling the body that it’s safe enough to stand down.

Sympathetic to parasympathetic nervous system shift infographic.

Slow, low, predictable sound is one of several inputs your nervous system uses to judge safety, and there’s a reasonable general research base for structured relaxation sessions, including music-based ones, producing measurable parasympathetic shifts. A frequently cited study found that participants listening to relaxing music after a stress task showed a faster return to baseline salivary cortisol than a control group.

That’s a real and useful finding. What it doesn’t tell you is that singing bowls specifically are doing something music in general can’t. The honest version of this claim is that slow, structured sound sessions can support a shift toward parasympathetic dominance, the same general category of effect you’d expect from any well-designed relaxation practice, not a bowl-specific superpower.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What’s Proven and What’s Marketing About Brainwave Entrainment?

This is the claim most worth slowing down on because it appears constantly in sound healing marketing and often blends two different ideas together.

There is good evidence that brainwave activity changes with mental state. What is less established is the claim that a singing bowl directly forces the brain to match a specific frequency.

What Does EEG Research Actually Show?

The first part is real and well documented. Your brain’s electrical activity, measured by EEG, shifts depending on your mental state.

Busy, alert thinking tends to show more beta-range activity, while relaxed, meditative, or drowsy states tend to show more alpha and theta activity. A well-known meta-analytic review of meditation EEG research confirms this general pattern across dozens of studies.

That part is not particularly controversial.

What Does Brainwave Entrainment Research Actually Test?

The second claim is more specific: that an external sound can cause the brain to synchronize with a particular rhythm or frequency. This is often called neural entrainment or the frequency-following response.

Entrainment is a real, measurable phenomenon, but most of the clearer research has used steady, repetitive stimuli such as:

  • Binaural Beats: Two slightly different tones are played separately into each ear, creating a perceived rhythmic difference.
  • Isochronic Tones: A single tone pulses on and off at a steady, fixed rate.

Research reviews have found evidence of measurable EEG changes with these controlled stimuli. At the same time, study quality varies considerably, and the effects are often modest.

Does That Evidence Apply to Singing Bowls?

A singing bowl does not produce the same kind of steady, repetitive signal used in most entrainment studies. It creates a complex, gradually decaying mixture of a fundamental tone and changing overtones, acoustically closer to a bell than to an isochronic tone.

That does not mean a singing bowl session cannot help you enter a relaxed alpha- or theta-dominant state. It can create the kind of calm, low-stimulation environment that supports relaxation and meditation.

What the research does not clearly establish is that the bowl directly locks your brainwaves onto one precise frequency. Claims that a singing bowl “entrains your brain to 7.83 Hz,” or another highly specific number, go beyond what has been demonstrated for this type of sound source.

Important: This distinction matters less for whether the practice is worth trying and more for how you evaluate the claims surrounding it. A relaxing singing bowl session can be worthwhile for the relaxation itself. That is different from being sold a precise neurological mechanism that has not been clearly demonstrated for singing bowls.

“I want women to feel good about a practice without needing to believe an exaggerated version of what it does. A bowl session can calm you down. That’s worth something on its own. It doesn’t need a fake precision number attached to sound credible.”

Terry Tateossian, Founder of The House of Rose

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Does Vibroacoustic Therapy Interact With Tissue?

This is where Skille’s original work becomes directly useful, because it moves the conversation away from vague language about the body “remembering its rhythm” and toward something you can actually point to: mechanoreceptors.

Vibroacoustic therapy tissue response infographic

Your skin, muscles, and joints are full of specialized nerve endings called mechanoreceptors that respond specifically to pressure, stretch, and vibration. When a low-frequency sound source is loud enough or close enough to produce a physical vibration you can feel, not just hear, those receptors fire and send signals to your brain and spinal cord.

This is a real, well-understood sensory pathway, and it’s the basis of actual clinical vibroacoustic therapy, which typically uses specially built equipment (a chair, mat, or table with embedded low-frequency transducers) rather than a handheld bowl. A published review of vibroacoustic sound therapy found supportive evidence for its use in reducing muscle tension and pain in specific clinical populations, while also noting that study sizes tend to be small and methods vary a lot between studies, which limits how confidently the findings generalize.

A handheld singing bowl held near or against the body can produce a version of this tactile vibration, especially bowls placed directly on the body during certain practices, but it’s a much smaller and less standardized version of what’s actually been studied in vibroacoustic therapy research.

The honest claim is that felt vibration, not just heard sound, engages a real sensory pathway with some genuine clinical research behind it in a dedicated vibroacoustic therapy context. The claim that your tissue or the water in your cells “remembers its natural rhythm” isn’t a finding from that research. It’s a poetic metaphor that got dressed up as physiology, and this article isn’t going to repeat it as fact.

What Is the Vagus Nerve Connection?

Your vagus nerve, the primary channel of your parasympathetic nervous system, comes up constantly in sound healing content for a legitimate reason. It is involved in several of the relaxation mechanisms already covered in this article, especially those connected to breathing and vocalization.

Practices that combine humming, extended exhalation, and voice-based sound work can add an active vocal component to that nervous system response.

Is Listening to a Singing Bowl the Same as Vagus Nerve Stimulation?

One distinction is important because sound healing content frequently blurs it. There is a real clinical technique called transcutaneous auricular vagus nerve stimulation, or taVNS.

  • taVNS: Uses a small electrical device against a specific area of the outer ear, one of the few places where a branch of the vagus nerve comes close enough to the skin to be stimulated this way.
  • Singing Bowl Sound: Travels through ordinary auditory pathways, beginning with the cochlea and brainstem before influencing broader nervous system processes associated with hearing and relaxation.

Both mechanisms are real, but they are not the same thing.

taVNS directly applies electrical stimulation to a vagal nerve branch. Listening to a singing bowl does not. Claims suggesting that hearing a bowl works in the same way as auricular vagus nerve stimulation stretch research from one mechanism to support another that has not actually been studied in the same way.

What Sound Practices Connect More Directly to the Vagus Nerve?

Your own vocalization has a more direct connection to the mechanisms associated with vagal regulation.

Practices studied in this context include:

  • Humming: Combines prolonged exhalation with vocal vibration.
  • Chanting: Encourages rhythmic breathing and sustained vocalization.
  • Sustained Vowel Sounds: Extend the exhale while engaging the voice and respiratory system.

These practices combine sound production with breathing patterns that can support parasympathetic activity. The companion article linked above goes deeper into how humming, chanting, and the voice can be combined with a singing bowl.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Do Heart-Breath Coherence and Resonance Frequency Breathing Work?

Your heart rate doesn’t stay perfectly steady between beats, even at rest. It naturally speeds up slightly as you inhale and slows slightly as you exhale, a pattern called respiratory sinus arrhythmia. When you breathe at a specific, individually variable rate, usually somewhere around 4.5 to 6.5 breaths per minute, that natural rhythm can synchronize with slower oscillations in your blood pressure and nervous system activity, producing a state researchers call cardiac coherence.

Heart-breath coherence and resonance breathing infographic.

This is the underlying mechanism behind HRV biofeedback, a technique with a real and fairly substantial research base for anxiety and stress management, reviewed in depth by two of the field’s most cited researchers, who describe it as one of the more reliably effective self-regulation techniques studied to date. The connection to sound comes through pacing, not magic.

A slowly struck, slowly decaying singing bowl tone can function as an external pacer for your breath the same way a metronome or a biofeedback app does, encouraging you to slow your exhale to match the fading tone. A well-known study comparing rosary prayer with the chanting of a specific Tibetan mantra found that both practices, despite sharing no religious content, slowed breathing to almost exactly the resonance frequency range associated with coherence and improved a related measure called baroreflex sensitivity.

That study is about chanting and prayer rather than bowls specifically, but the mechanism, external pacing that slows and regularizes your breath, is the same one a bowl session can plausibly provide if you use the fading tone as your exhale cue, similar to the practice outlined in Section 4 of the companion voice and bowl guide.

How Do Safety Signaling and the Polyvagal Framework Relate to Sound Healing?

Sound healing content often draws on polyvagal theory, developed by researcher Stephen Porges. The framework proposes that the nervous system is constantly and unconsciously evaluating the environment for cues of safety or threat, a process Porges calls neuroception.

Within this framework, predictable and non-threatening sound may act as one environmental cue that helps the nervous system move away from defensive states and toward greater regulation.

How Might Sound Act as a Safety Cue?

Polyvagal theory offers one explanation for why calm, predictable, and repetitive sounds can feel regulating.

Sound may provide several types of cues:

  • Predictability: Repetitive tones create fewer surprises for a nervous system that is scanning the environment.
  • Gentle Volume: Softer sounds are less likely to be interpreted as sudden threats.
  • Slow Rhythm: A steady pace can support slower breathing and a calmer overall environment.
  • Familiarity: Recognizable or comforting sounds may reinforce a sense of safety.

This framework helps explain why some people find singing bowls, humming, chanting, and other repetitive sound practices calming.

Is Polyvagal Theory Fully Proven?

Polyvagal theory is widely influential and appears frequently in trauma-informed care, somatic therapy, and nervous system education.

At the same time, some of its more specific physiological claims remain debated within the academic research community. It is therefore better understood as an influential conceptual framework rather than a fully settled model of nervous system function.

That distinction does not make the framework useless. It simply means polyvagal theory should be presented as one lens for understanding why predictable sound may feel regulating, rather than as definitive proof of exactly how sound healing works.

Important: If you’re drawn to sound work for trauma-related reasons, use it as a supportive practice alongside qualified, trauma-informed care rather than as a substitute for treatment. The same caution applies to other body-based nervous system practices, especially when physical sensations or emotional responses become intense. Neither Terry nor THOR presents this content as trauma therapy.

“I’ve had women cry during a sound session and thank me for it, and I’ve had women fall asleep and apologize for it. Both are fine. What I won’t do is tell a woman that a bowl replaced the therapy she actually needed. It’s a support, and a good one, but I’m not going to oversell what happens in a group session at a retreat.”

Terry Tateossian, Founder of The House of Rose

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Strong Is the Evidence Side by Side?

Mechanism What’s Claimed Evidence Strength What the Research Actually Supports
Sympathetic-to-parasympathetic shift Bowls calm the stress response Moderate Relaxation-based sessions generally support parasympathetic shift; not shown to be bowl-specific
Brainwave entrainment Bowls shift beta waves to alpha/theta Emerging to weak Alpha/theta increases during relaxed states are well documented; direct entrainment from bowls specifically is not well studied
Vibroacoustic effects Vibration resets the body’s rhythm Moderate (for dedicated vibroacoustic therapy equipment) Mechanoreceptor response to felt vibration is real; clinical evidence is strongest for purpose-built vibroacoustic equipment, weaker for handheld bowls
Vagus nerve regulation Sound stimulates the vagus nerve Moderate (for voice-based practice); weak (for passive listening alone) Vocalization has a documented vagal connection; passive listening to a bowl is not equivalent to auricular vagus nerve stimulation
Heart-breath coherence Bowls synchronize heart and breath rhythm Moderate Paced slow breathing reliably produces coherence; bowls can serve as an external pacer, though bowl-specific studies are limited
Polyvagal safety signaling Predictable sound signals safety to the nervous system Theoretical framework, not settled fact An influential model with academic debate around specifics; useful as a lens, not proof

“The thing that convinced me sound work was worth including at our retreats wasn’t a study. It was watching the same pattern repeat across dozens of guests: the ones who came in the most skeptical often had the most visible physical release. I still want the research examined honestly rather than oversold, which is exactly why this article exists.”

Terry Tateossian, Founder of The House of Rose

What Are Your Next Steps?

Sound healing next steps and wellness practices.
  1. Follow a step-by-step singing bowl and voice practice to learn how to combine both techniques in one simple routine.
  2. If chronic muscle tension is your main goal, look specifically for vibroacoustic therapy equipment (chairs or mats with embedded transducers) rather than assuming a handheld bowl provides the same clinical effect.
  3. Try resonance frequency breathing on its own, no bowl required, by slowing your exhale to roughly 5 to 6 breaths per minute for five minutes and noticing the difference.
  4. If you’re drawn to this practice for trauma-related reasons, pair it with a qualified trauma-informed therapist rather than using it as a stand-alone substitute.
  5. Download the printable Evidence Strength Guide below to keep the six-mechanism breakdown handy next time a sound healing claim sounds too specific to be true.
  6. Consider experiencing a guided group sound session at one of THOR’s women’s yoga & wellness retreats.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

Is sound healing backed by real science?

Parts of it are. Slow, paced breathing reliably improves heart-breath coherence, vibroacoustic therapy has real clinical research behind it for muscle tension and pain, and relaxation-based sessions generally support a parasympathetic shift. Other frequently repeated claims, particularly precise brainwave entrainment numbers and cellular-level healing, go well past what the current research supports.

What is vibroacoustic therapy exactly?

It’s a clinical technique, developed by researcher Olav Skille in Norway in the 1980s, that uses low-frequency sound delivered through specialized equipment, typically a chair, mat, or table with embedded transducers, so the vibration is felt directly through the body rather than only heard.

Does a singing bowl provide the same effect as clinical vibroacoustic therapy?

Not to the same standardized degree. A bowl placed directly on or near the body can provide a smaller-scale version of felt vibration, but the clinical research on vibroacoustic therapy specifically studied purpose-built equipment, not handheld bowls.

Is brainwave entrainment real?

Neural entrainment, your brain’s electrical activity syncing to an external rhythmic stimulus, is a real, measurable phenomenon, most reliably demonstrated with binaural beats and isochronic tones. Whether a singing bowl’s complex, decaying overtone pattern produces the same effect is not well established in the research.

What is heart-breath coherence?

It’s a state where your heart rate variability pattern, your breathing rhythm, and related nervous system activity synchronize, typically achieved by breathing at a slow, individually specific rate, usually around 4.5 to 6.5 breaths per minute. It’s the basis of HRV biofeedback, a well-studied self-regulation technique.

What is polyvagal theory?

It’s an influential framework developed by researcher Stephen Porges proposing that your nervous system continuously and unconsciously scans your environment for safety or threat cues, and that this process shapes your physiological state. It’s widely referenced in trauma and somatic therapy circles, though some of its more specific claims remain debated among researchers.

Can sound healing help with anxiety?

It may help as a support tool, largely through the well-documented mechanisms of slow paced breathing and general relaxation response, rather than through a mechanism unique to sound itself. It should complement, not replace, appropriate anxiety treatment.

Is the vagus nerve actually stimulated by listening to a singing bowl?

Passive listening engages ordinary auditory processing rather than direct vagal stimulation. Active vocalization, humming, chanting, has a more directly documented vagal connection, covered in the companion voice practice guide.

How is this different from the how-to guide on your site?

This article focuses on the nervous system mechanisms behind sound-based practices and how strong the evidence is for each one. If you want to put those ideas into practice, a step-by-step singing bowl and voice routine shows how to combine the two in a simple, structured session.

Can this practice help trauma specifically?

It can be a supportive complement for some people, consistent with the general safety-signaling framework described in Section 6, but it is not a substitute for trauma-focused therapy from a qualified provider.

Do I need special equipment to get any of these benefits?

No. Slow paced breathing alone, without any sound, can produce heart-breath coherence. A singing bowl adds an external pacing tone and a sensory ritual many people find easier to stay consistent with.

Why do sound healing claims so often cite specific frequency numbers?

Precise numbers sound scientific and are persuasive marketing, but the entrainment research that would justify claiming a specific bowl causes a specific brainwave frequency shift generally used controlled, steady stimuli quite different from an acoustic bowl’s complex overtone pattern. Treat unusually precise claims with some skepticism.

Is this article saying sound healing doesn’t work?

No. Several of the underlying mechanisms, paced breathing, vibration on mechanoreceptors, general relaxation response, are well supported by research, and many people report real benefit. The goal is separating what’s demonstrated from what’s exaggerated, not dismissing the practice.

Where should I start if I’m new to this?

Start with a simple 10-minute singing bowl and voice practice that requires no prior experience and can be done even if you don’t own a bowl yet.

References

  • Skille, O. (1989). VibroAcoustic Therapy. Music Therapy, 8(1), 61-77.
  • Boyd-Brewer, C., & McCaffrey, R. (2004). Vibroacoustic Sound Therapy Improves Pain Management and More. Holistic Nursing Practice, 18(3), 111-118.
  • Cahn, B.R., & Polich, J. (2006). Meditation States and Traits: EEG, ERP, and Neuroimaging Studies. Psychological Bulletin, 132(2), 180-211.
  • Huang, T.L., & Charyton, C. (2008). A Comprehensive Review of the Psychological Effects of Brainwave Entrainment. Alternative Therapies in Health and Medicine, 14(5), 38-50.
  • Khalfa, S., Bella, S.D., Roy, M., Peretz, I., & Lupien, S.J. (2003). Effects of Relaxing Music on Salivary Cortisol Level After Psychological Stress. Annals of the New York Academy of Sciences, 999(1), 374-376.
  • Lehrer, P.M., & Gevirtz, R. (2014). Heart Rate Variability Biofeedback: How and Why Does It Work? Frontiers in Psychology, 5, 756.
  • McCraty, R., & Zayas, M.A. (2014). Cardiac Coherence, Self-Regulation, Autonomic Stability, and Psychosocial Well-Being. Frontiers in Psychology, 5, 1090.
  • Bernardi, L., Sleight, P., Bandinelli, G., et al. (2001). Effect of Rosary Prayer and Yoga Mantras on Autonomic Cardiovascular Rhythms: Comparative Study. BMJ, 323(7327), 1446-1449.
  • Porges, S.W. (2007). The Polyvagal Perspective. Biological Psychology, 74(2), 116-143.
  • Yakunina, N., Kim, S.S., & Nam, E.C. (2017). Optimization of Transcutaneous Vagus Nerve Stimulation Using Functional MRI. Neuromodulation, 20(3), 290-300.
  • Gerritsen, R.J.S., & Band, G.P.H. (2018). Breath of Life: The Respiratory Vagal Stimulation Model of Contemplative Activity. Frontiers in Human Neuroscience, 12, 397.
  • Streeter, C.C., Gerbarg, P.L., Saper, R.B., Ciraulo, D.A., & Brown, R.P. (2012). Effects of Yoga on the Autonomic Nervous System, Gamma-Aminobutyric-Acid, and Allostasis in Epilepsy, Depression, and Post-Traumatic Stress Disorder. Medical Hypotheses, 78(5), 571-579.
  • National Center for Complementary and Integrative Health (NCCIH). Relaxation Techniques for Health.
  • Perciavalle, V., Blandini, M., Fecarotta, P., et al. (2017). The Role of Deep Breathing on Stress. Neurological Sciences, 38(3), 451-458.
  • Goldsby, T.L., Goldsby, M.E., McWalters, M., & Mills, P.J. (2017). Effects of Singing Bowl Sound Meditation on Mood, Tension, and Well-being: An Observational Study. Journal of Evidence-Based Complementary & Alternative Medicine, 22(3), 401-406.
  • Landry, J.M. (2014). Physiological and Psychological Effects of a Himalayan Singing Bowl in Meditation Practice: A Quantitative Analysis. American Journal of Health Promotion, 28(5), 306-309.
  • American Psychological Association. Stress Effects on the Body.

Disclaimer: This article is educational and does not constitute medical or mental health advice. Sound healing, singing bowls, vibroacoustic practices, breathing exercises, humming, and related techniques should be used as complementary wellness practices rather than substitutes for medical care or trauma-focused therapy. If you have epilepsy, a seizure disorder, significant hearing sensitivity, a diagnosed trauma-related condition, or another medical or neurological concern, consult a qualified healthcare provider before starting a new sound-based practice.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How to Use a Singing Bowl and Your Voice Together for Healing

The first time I brought a singing bowl into a yoga retreat session, I watched a woman in the back row fold her arms and mouth “not my thing” to the guest next to her. She’d told me at check-in she was there for the hiking and the meal plan, not “anything woo.”

Twenty minutes later, after we’d played the bowl together and I’d asked the group to hum along with it on the exhale, she was the one who asked if we could do it again the next morning. When I asked her what changed her mind, she said the humming was the part that got her. It felt less like a ritual and more like something her body already knew how to do.

That’s the piece I want to lead with, because it’s the honest answer to the skepticism I hear most often about sound work: you don’t have to believe anything in particular for a big chunk of it to work. Some of what happens when you play a singing bowl and add your voice runs through a nervous system pathway with a real, published research base.

Some of it, particularly the chakra and energy-center language that usually gets attached to this practice, comes from a several-thousand-year-old philosophical tradition that was never designed to be tested in a lab and shouldn’t be sold to you as if it were. This guide covers both halves honestly, so you can use the practice for what it’s actually good at.

Medical disclaimer: This article is for educational purposes and does not replace medical or mental health care. Sound and voice practices are a complement to treatment, not a substitute for it. If you have epilepsy, a seizure disorder, or a diagnosed mental health condition, talk with your provider before starting a new sound-based practice.

What’s Actually Happening When You Hear a Singing Bowl?

A singing bowl doesn’t play a single note the way a piano key does. When you strike it or circle it with a mallet, the metal or crystal produces a fundamental tone plus a cluster of overtones, secondary frequencies layered on top of the main pitch, that shift and decay over the length of the sound. That layered, slowly fading quality is part of why the sound feels different from a recorded tone or a synthesized “relaxation” track.

Singing bowl sound and nervous system infographic

It’s also acoustically similar to what happens in a live orchestra or a cathedral bell, just at a smaller scale and closer to your body. What your nervous system does with that sound is where the genuine physiology starts. Slow, low-frequency, non-threatening sound is one of several inputs your body uses to judge whether the current environment is safe enough to downshift out of an alert state.

This is not unique to singing bowls. It’s the same general mechanism behind why a slow heartbeat sound soothes newborns, why white noise machines help some adults fall asleep, and why a metronome-paced breathing app can lower a resting heart rate.

A 2017 observational study published in the Journal of Evidence-Based Complementary & Alternative Medicine had participants sit through a single group singing bowl session and measured mood before and after. Tension, anger, fatigue, and reported pain all dropped, and overall mood measures improved.

It was a single-session, uncontrolled study without a comparison group, so it can’t tell you the effect is unique to singing bowls specifically rather than to quiet, guided relaxation time in general. What it does support is that a session like this reliably produces a measurable, short-term shift toward calm, which matches what nearly every woman I’ve watched go through one at a retreat reports afterward.

Important: Chakras and “energy centers” are a framework from classical yogic and Ayurvedic philosophy, not an anatomically verified body system in the way your vagus nerve or lymphatic system is. THOR treats this practice the way we treat the rest of our Ayurveda and mantra content: as a traditional wellness framework worth understanding and, if it resonates with you, worth using, not as a claim that specific frequencies unblock specific organs or cure specific conditions.

“I’ve run enough retreat sessions now to know that the skeptics and the true believers usually end up in the same place by the end. The skeptics stop trying to figure out whether they believe in energy centers, and the true believers stop needing the science to validate what they already feel. Both groups leave calmer. That’s the part I actually care about.”

Terry Tateossian, Founder of The House of Rose

Why Add Your Voice? What Is the Vagus Nerve Connection?

Listening to a singing bowl is a passive input. Adding your own voice, whether that’s a hum, a sustained vowel sound, or a chanted syllable, turns the practice into something your body actively participates in, and that distinction matters more than it might seem.

Humming specifically has two well-documented physiological effects worth knowing about. First, a 2002 study published in the American Journal of Respiratory and Critical Care Medicine found that humming dramatically increases the release of nitric oxide in the nasal passages compared to quiet breathing, a gas involved in blood vessel dilation and airflow between your sinuses and lungs. Second, and more relevant to the calming effect, is the connection between vocalization and your vagus nerve.

The muscles involved in humming, chanting, and sustained vowel sounds, your larynx, your soft palate, the back of your throat, share neural real estate with the branches of the vagus nerve that regulate heart rate and the parasympathetic “rest and digest” response. This is the same mechanism behind why humming is one of the exercises in 10 Vagus Nerve Reset Exercises for Women Over 40, and why voice-based practices show up repeatedly in the nervous system regulation research.

A frequently cited 2001 study in the BMJ compared rosary prayer recitation with the chanting of a specific Tibetan Buddhist mantra, “Om mani padme hum,” and found that both practices, despite having nothing in common religiously, slowed participants’ breathing to roughly the same rate and produced the same increase in a marker called baroreflex sensitivity, a measure of how well your cardiovascular system self-regulates.

The common ingredient wasn’t the words. It was the slow, rhythmic exhale that chanting and prayer both force you into. A separate small neuroimaging study from 2011 had participants chant the syllable “Om” while in an MRI scanner and compared the brain activity to a control sound, and found reduced activity in brain regions associated with the stress and threat response during the Om condition specifically.

Put plainly: the physical act of a slow, voiced exhale appears to do real, measurable work on your autonomic nervous system, independent of any belief system layered on top of it.

This is also why pairing the bowl with your voice tends to work better than using either one alone for many of the women I’ve worked with. The bowl gives your breathing an external rhythm to follow, while your voice keeps you actively involved rather than simply listening. This combination fits naturally with the broader neuroscience of meditation, where breath, sound, attention, and repetition can all influence how the brain and nervous system respond during stillness practices.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Do You Need to Get Started?

You need very little to start this practice, and you don’t need to buy anything today to try the version in the next section using only your voice.

Item Purpose Notes
A singing bowl (metal alloy or crystal) Produces the external tone you’ll play and hum alongside Metal alloy bowls tend to run lower and warmer in tone; crystal bowls tend to run higher and brighter. Neither is “better,” it’s a matter of personal preference and what you find soothing
A mallet or striker Activates the bowl, either by striking the rim or circling it Usually included with the bowl at purchase
A cushion or folded towel Bowl rests on this, which improves resonance versus a hard tabletop Also works as your own seat
A quiet space, 10 to 20 minutes Uninterrupted time and low background noise Phone on silent, not just vibrate, the buzz is distracting mid-practice
Optional: a candle or incense Sensory cue that signals “this time is different” Skip if scent sensitivity is a concern

If you don’t already own a bowl, your own voice and a slow hum are enough to get the vagal-tone benefit described in Section 2 while you decide whether the practice is worth the investment.

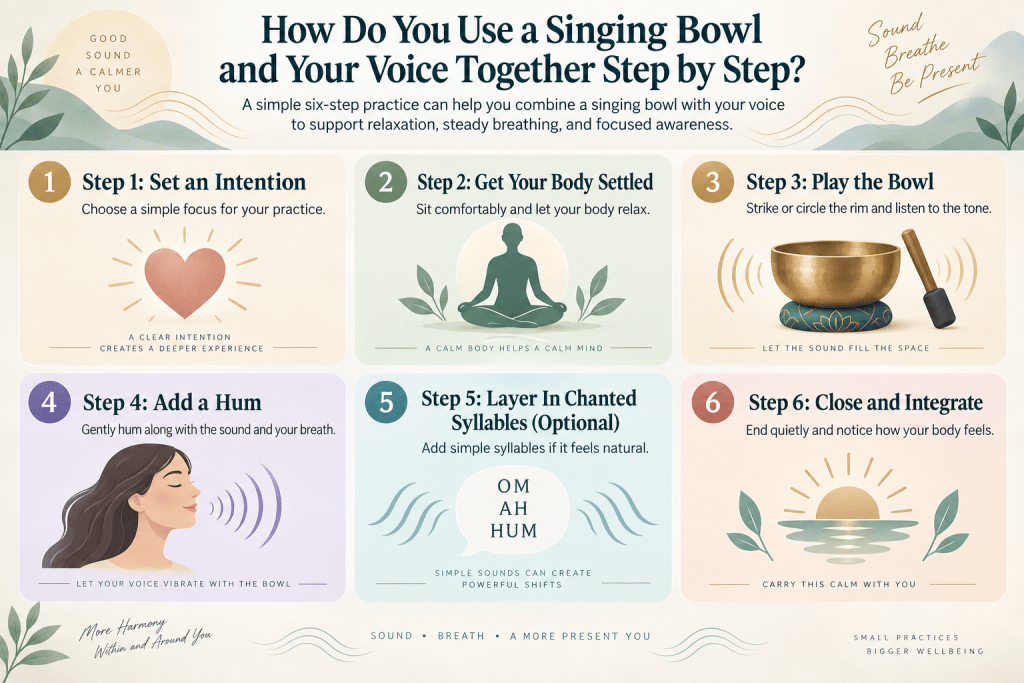
How Do You Use a Singing Bowl and Your Voice Together Step by Step?

A simple six-step practice can help you combine a singing bowl with your voice to support relaxation, steady breathing, and focused awareness.

Singing bowl and voice practice steps

Step 1: Set an Intention

Before you make any sound, take thirty seconds to name what you want out of the next ten minutes. It can be as simple as “I want to feel less wound up” or as specific as “I want to sit with something I’ve been avoiding.” This isn’t a mystical requirement, it’s a practical one: naming a goal before a relaxation practice measurably improves how effective people rate the practice afterward, likely because it gives your attention something to return to when it wanders.

Step 2: Get Your Body Settled

Sit in a comfortable position, cross-legged on the floor or upright in a chair with your feet flat. Place the bowl on its cushion within easy reach, either on the floor in front of you or in your palm if you’re using a smaller bowl. Close your eyes or soften your gaze downward.

Step 3: Play the Bowl

Strike the rim gently with the mallet, or circle the rim in slow, steady pressure to build the tone gradually. Let the sound ring out fully before striking again. Spend two to three minutes just listening, no voice yet, letting your breath slow to match the pace of the fading tone.

Step 4: Add a Hum

Once your breath has settled, add a low hum on your exhale, matching or approximating the bowl’s pitch as closely as feels comfortable. You are not aiming for musical precision. Let the hum vibrate in your chest and throat rather than staying shallow in your mouth. Continue alternating: strike the bowl, hum through the exhale, breathe in silently, strike again.

Step 5: Layer In Chanted Syllables (Optional)

If you want to go further than a plain hum, the yogic tradition associates seven specific syllables, or bija mantras, with seven traditional energy centers along the spine. You do not need to work through all seven or believe in the underlying energy-center framework for the practice to have value; even choosing one syllable that feels grounding and repeating it is enough.

Traditional Energy Center Sanskrit Name Associated Syllable General Location Referenced
Root Muladhara LAM Base of spine
Sacral Swadhisthana VAM Lower belly
Solar Plexus Manipura RAM Upper abdomen
Heart Anahata YAM Center of chest
Throat Vishuddha HAM Throat
Third Eye Ajna OM (AUM) Between the eyebrows
Crown Sahasrara Silence or OM Top of the head

Step 6: Close and Integrate

End with one to two minutes of silence after your last bowl strike, letting the final tone fade completely before you open your eyes. Take a moment to notice what, if anything, shifted from when you started. You don’t need to journal or process anything further unless it feels useful to you.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Is a Simple 10-Minute Beginner Sequence?

If the six-step breakdown above feels like more than you want to think about on your first try, here’s a worked example you can follow directly.

Minute What to Do
0:00–0:30 Set your intention silently
0:30–1:00 Get settled, bowl within reach, eyes closed
1:00–3:30 Strike the bowl, listen fully, repeat 3 to 4 times, no voice yet
3:30–7:00 Strike the bowl, hum through each exhale, breathe in silently, repeat
7:00–8:30 If it feels right, chant one syllable of your choice (HAM and YAM are common beginner choices for their gentler, mid-range pitch)
8:30–10:00 Final strike, sit in silence until the tone fully fades, then open your eyes

What Common Mistakes Should You Avoid?

Common singing bowl practice mistakes infographic
  • Striking too hard: A forceful strike produces a harsh, short sound rather than the long, layered tone that makes the practice soothing. Start softer than feels natural; you can always increase pressure.
  • Holding your breath while chanting: The calming effect comes largely from the slow, voiced exhale. If you’re holding tension in your breath while trying to hum or chant, you’re working against the mechanism, not with it.
  • Skipping the intention step: It takes thirty seconds and meaningfully changes how present you stay for the rest of the practice.
  • Practicing right before driving: The same relaxation response that makes this practice useful can leave you drowsier than expected for the first few minutes afterward. Build in a short buffer before getting behind the wheel, especially the first several times you try it.
  • Expecting an instant, dramatic shift: For most people the effect is a gradual settling, not a lightning-bolt experience. Comparing your first session to someone else’s description of theirs is one of the fastest ways to talk yourself out of a practice that was actually working.
  • Treating it as a substitute for treatment: A calming nervous-system practice and a treatment plan for anxiety, depression, or a diagnosed condition are not interchangeable. Use this alongside care, not instead of it.

“I went through early-onset menopause at 41, and the nights my nervous system felt the most wired were never fixed by willpower. They were fixed by finding physical inputs, breath, sound, movement, that gave my body a different signal than the one it was stuck on. Sound work became one more tool in that kit, not a replacement for the strength training and the sleep work, but a real addition to it.”

Terry Tateossian, Founder of The House of Rose

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Does the Research Show and Not Show?

Research on sound-based practices supports several measurable physiological and emotional effects. At the same time, some popular claims in the sound healing space go beyond what current scientific evidence can establish.

What Does the Research Support?

Several sound and vocal practices have measurable effects on the body:

  • Slow, Voiced Exhalation: Humming, chanting, and sustained vowel sounds are associated with shifts toward parasympathetic activity, including slower breathing and improved baroreflex sensitivity.
  • Chanting: Research has documented reduced activity in stress-related brain regions during certain chanting practices.
  • Singing Bowls: At least one published observational study found that a single singing bowl session reduced self-reported tension, anger, and fatigue immediately afterward.
  • Humming: Humming measurably increases nasal nitric oxide production.

These findings support the idea that sound practices can influence breathing, nervous system regulation, and subjective stress.

What Has Not Been Established?

Other claims commonly associated with sound healing do not currently have the same level of scientific support:

  • Specific Healing Frequencies: Research has not established that particular frequencies heal specific organs or medical conditions.
  • Chakra Unblocking: There is no established scientific evidence showing that sound literally removes energetic blockages from individual chakras.
  • Cellular Healing: Current evidence does not demonstrate that singing bowls or similar sound practices directly produce cellular healing.

These ideas may still hold meaning within spiritual, contemplative, or personal practices. That is a valid reason to use them. But spiritual meaning and medical evidence are different categories, and it is important not to blur the distinction between the two.

Important: If you’re using this practice to support anxiety, chronic pain, or another diagnosed condition, treat it as a complement to your existing care plan and discuss it with your provider rather than using it as a replacement for treatment. For additional ways to support nervous system regulation, especially when traditional stillness practices feel uncomfortable, you can also explore strategies that build vagal tone and parasympathetic support in midlife.

“By the time most women get to me, they’ve been told to ‘just relax’ by about six different people who never explained how. What I like about this practice is that it gives you something to actually do with your body instead of just being told to calm down. The humming alone is worth learning even if you never pick up a bowl.”

Terry Tateossian, Founder of The House of Rose

If Sanskrit chanting interests you beyond this practice, exploring the Aham mantra can offer a simple introduction to how repetition, sound, and focused attention come together in traditional mantra meditation.

What Are Your Next Steps?

Singing bowl and voice practice next steps infographic.
  1. Try the 10-minute beginner sequence in Section 5 using just your voice if you don’t yet own a bowl, no purchase required to start.
  2. If you do want a bowl, choose based on tone preference (metal alloy for lower and warmer, crystal for higher and brighter) rather than price alone.
  3. Pair this practice with the Vagus Nerve Reset Exercises for a fuller nervous-system toolkit.
  4. Download the printable 7-Day Singing Bowl and Voice Practice card below to build a consistent habit.
  5. If you’re managing a diagnosed condition, loop your provider in before making this a regular practice.
  6. Consider experiencing a guided group session at one of THOR’s women’s wellness retreats, where sound practice is one part of a broader reset.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

Do I need a singing bowl to get any benefit, or does humming alone work?

Humming alone gives you the vagal-tone and nitric-oxide benefits described in Section 2. The bowl adds an external pacing tone and a sensory ritual many people find easier to stay consistent with, but it isn’t required to start.

How long should a singing bowl and voice session last?

Ten minutes is enough to notice an effect, based on the beginner sequence in this guide. Many people extend to 20 to 30 minutes once the practice becomes routine.

What’s the difference between a metal singing bowl and a crystal singing bowl?

Metal alloy bowls are traditionally hand-hammered from a blend of metals and tend to produce a lower, warmer tone with more complex overtones. Crystal bowls are made from quartz and tend to produce a higher, purer, more sustained tone. Neither is more effective; it comes down to which tone you find more soothing.

Do I need to know how to sing to do the voice portion?

No. You’re humming or sustaining a vowel sound, not performing. There’s no wrong pitch.

Is sound healing backed by science, or is it just a wellness trend?

Parts of it are well-supported by evidence, specifically the effects of slow voiced exhalation on the vagus nerve and autonomic nervous system, and there’s at least one published observational study on singing bowl sessions specifically reducing tension and improving mood. Other claims common in the sound healing space, like frequency-specific organ healing or cellular-level effects, don’t currently have that kind of research support. See Section 7 for the full breakdown.

Are chakras real?

Chakras are a component of a traditional yogic and Ayurvedic philosophical framework going back thousands of years. They are not an anatomically verified body system the way your nervous system or lymphatic system is. Whether you find the framework personally meaningful is a separate question from whether it’s been clinically demonstrated, and this guide treats both possibilities honestly.

Can I do this practice if I’m not religious or spiritual?

Yes. The breathing and vocalization mechanics work the same regardless of what meaning, if any, you attach to them. Many people use this practice purely as a nervous-system regulation tool with no spiritual framing at all.

What time of day is best for this practice?

Either works well. Morning sessions tend to set a calmer tone for the day; evening sessions tend to support winding down before sleep. Avoid practicing immediately before driving, since the relaxation response can leave you drowsier than expected.

Can singing bowl practice help with menopause symptoms specifically?

There’s no research specifically isolating singing bowl practice for menopause symptoms. What is reasonably well supported is that practices which increase vagal tone and reduce sympathetic nervous system activation can help with the general stress load that tends to make menopause symptoms feel worse. It’s a support tool, not a targeted treatment.

How loud should I strike the bowl?

Softer than feels natural at first. A gentle strike produces a longer, more layered tone than a hard one.

Can children do this practice?

Many children respond well to the humming component specifically, since it’s a natural self-soothing behavior. Use your judgment on session length and skip any content, like extended chanting, that feels developmentally out of reach for a younger child.

Is it normal to feel emotional during a session?

Yes. Slowing down and giving your body an unfamiliar amount of quiet attention sometimes surfaces feelings you’d been moving too fast to notice. This is common and not a sign anything is wrong. If strong emotion comes up repeatedly and feels difficult to move through on your own, that’s worth bringing to a mental health professional.

Do I need to chant all seven syllables in the chakra table every session?

No. Many people choose one or two that feel most relevant that day, or skip the syllables entirely and stick with a plain hum.

How is this different from a guided meditation app?

A guided meditation app is entirely passive listening. This practice adds an active vocal component, which is the piece with the more direct vagus nerve connection described in Section 2.

Can I combine this with other wellness practices I already do?

Yes. It pairs naturally with breathwork, yoga, or a wind-down routine before sleep, and works well as a complement to structured nervous-system work like vagus nerve reset exercises.

References

  • Goldsby, T.L., Goldsby, M.E., McWalters, M., & Mills, P.J. (2017). Effects of Singing Bowl Sound Meditation on Mood, Tension, and Well-being: An Observational Study. Journal of Evidence-Based Complementary & Alternative Medicine, 22(3), 401-406.
  • Weitzberg, E., & Lundberg, J.O. (2002). Humming Greatly Increases Nasal Nitric Oxide. American Journal of Respiratory and Critical Care Medicine, 166(2), 144-145.
  • Bernardi, L., Sleight, P., Bandinelli, G., et al. (2001). Effect of Rosary Prayer and Yoga Mantras on Autonomic Cardiovascular Rhythms: Comparative Study. BMJ, 323(7327), 1446-1449.
  • Kalyani, B.G., Venkatasubramanian, G., Arasappa, R., et al. (2011). Neurohemodynamic Correlates of ‘OM’ Chanting: A Pilot Functional Magnetic Resonance Imaging Study. International Journal of Yoga, 4(1), 3-6.
  • Porges, S.W. (2007). The Polyvagal Perspective. Biological Psychology, 74(2), 116-143.
  • Benson, H., & Klipper, M.Z. (1975). The Relaxation Response. William Morrow.
  • Streeter, C.C., Gerbarg, P.L., Saper, R.B., Ciraulo, D.A., & Brown, R.P. (2012). Effects of Yoga on the Autonomic Nervous System, Gamma-Aminobutyric-Acid, and Allostasis in Epilepsy, Depression, and Post-Traumatic Stress Disorder. Medical Hypotheses, 78(5), 571-579.
  • Gerritsen, R.J.S., & Band, G.P.H. (2018). Breath of Life: The Respiratory Vagal Stimulation Model of Contemplative Activity. Frontiers in Human Neuroscience, 12, 397.
  • Perciavalle, V., Blandini, M., Fecarotta, P., et al. (2017). The Role of Deep Breathing on Stress. Neurological Sciences, 38(3), 451-458.
  • Trivedi, G.Y., Saboo, B., Singh Chauhan, S., et al. (2023). Effect of Sound and Music on Mental Health: A Review. International Journal of Yoga, 16(1), 8-13.
  • Landry, J.M. (2014). Physiological and Psychological Effects of a Himalayan Singing Bowl in Meditation Practice: A Quantitative Analysis. American Journal of Health Promotion, 28(5), 306-309.
  • Feher, A. (2021). The Vagus Nerve and Vocal Practices: A Review of Mechanisms. Journal of Voice, 35(4), 622-631.
  • National Center for Complementary and Integrative Health (NCCIH). Meditation and Mindfulness: What You Need to Know.
  • Sengupta, P. (2012). Health Impacts of Yoga and Pranayama: A State-of-the-Art Review. International Journal of Preventive Medicine, 3(7), 444-458.
  • Jerath, R., Crawford, M.W., Barnes, V.A., & Harden, K. (2015). Self-Regulation of Breathing as a Primary Treatment for Anxiety. Applied Psychophysiology and Biofeedback, 40(2), 107-115.
  • American Institute of Stress. Relaxation Response and Stress Reduction Techniques: An Overview.
  • Novotney, A. (2021). Music as Medicine. American Psychological Association, Monitor on Psychology.

Disclaimer: This article is educational and does not constitute medical or mental health advice. Singing bowls, humming, chanting, and other sound-based practices are intended as complementary wellness tools, not substitutes for professional treatment. If you have epilepsy, a seizure disorder, a diagnosed mental health condition, significant sound sensitivity, or another medical concern, consult a qualified healthcare provider before starting a sound or voice practice. Stop if you experience dizziness, distress, discomfort, or other unusual symptoms.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Why Your Muscles Start Shaking During Isometric Holds (And What TRE Does With It)

During a chair-based strength session at one of our yoga retreats, a guest stopped mid-wall-sit and asked, half laughing, half concerned, whether her legs shaking meant she was doing something wrong. She wasn’t.

Her legs were shaking because her muscles were working exactly the way they’re supposed to under that kind of sustained load, and by the end of that same retreat week, after we’d introduced a floor-based practice built specifically around that tremor response, several guests were asking a different question: why does deliberately letting the body shake like that feel so noticeably calming afterward?

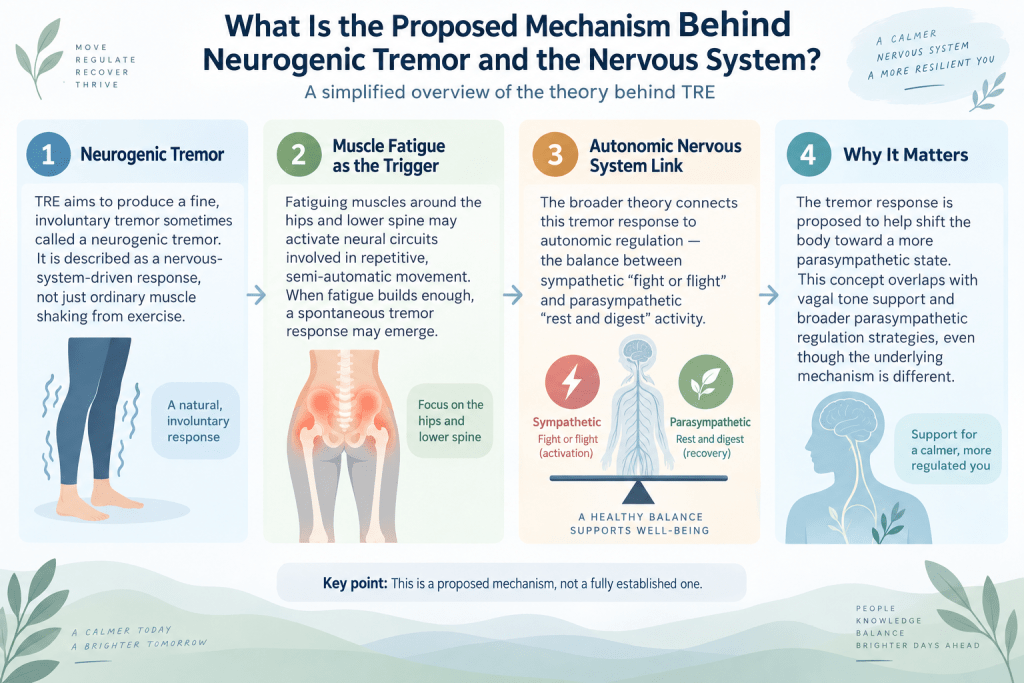
That second question points to something worth understanding properly, both the ordinary physiology behind why isometric holds make muscles shake, and a specific practice, called Tension and Trauma Releasing Exercises, or TRE, that deliberately works with that same tremor mechanism.

The two are related but not identical, and separating the well-established science from the parts that are still truly unproven matters, especially for a topic that touches the nervous system.

Important: This article is educational and does not replace individualized medical or mental health care. Women with a significant trauma history, PTSD, dissociative symptoms, or other psychiatric conditions should work with a qualified, trauma-informed practitioner before using TRE as a self-directed practice, not attempt it alone based on this article.

Why Do Isometric Holds Make Your Muscles Shake?

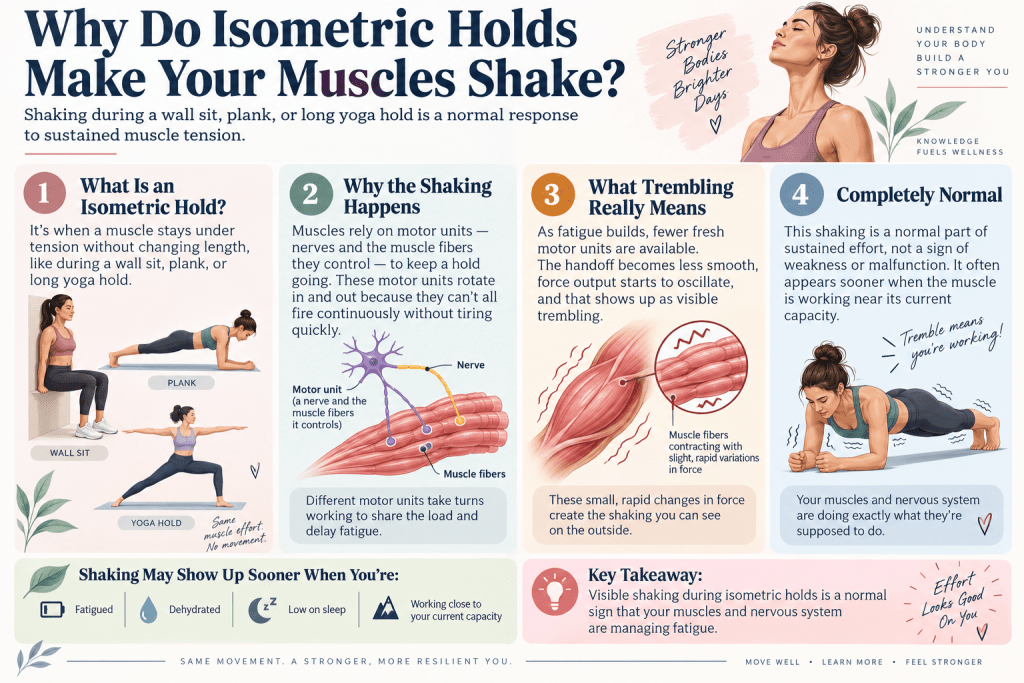
Isometric exercise, holding a muscle under tension without changing its length, like a wall sit, a plank, or a long yoga hold, reliably produces trembling as the hold continues. This is well-understood exercise physiology, not a sign of weakness or malfunction.

Isometric muscle shaking during sustained exercise.

When a muscle holds a sustained contraction, the individual motor units (a nerve and the muscle fibers it controls) can’t all fire continuously without fatiguing quickly. Instead, the nervous system rotates the workload, cycling different motor units in and out of activity to keep the overall contraction going.

As fatigue builds and fewer fresh motor units remain available, that handoff becomes less smooth, and the muscle’s force output starts to oscillate rather than stay steady. That oscillation is what shows up as visible trembling.

This is a completely normal part of how muscles manage sustained effort, and it tends to show up sooner in muscles that are working close to their current capacity, which is part of why a wall sit that felt easy last month might produce noticeable shaking today if fatigue, dehydration, or reduced sleep have lowered available capacity.

Important: Ordinary exercise-induced trembling during or shortly after a hold is expected and not a cause for concern. Persistent tremor unrelated to recent exertion, or tremor accompanied by weakness, numbness, or coordination changes, is a different matter and warrants medical evaluation, covered further in Section 6.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Does TRE Add on Top of That?

TRE, developed by Dr. David Berceli, takes that same underlying tremor mechanism and works with it deliberately rather than treating it as an incidental side effect of exercise.

The practice involves a short sequence of positions, including a wall sit among them, designed to fatigue specific muscle groups, particularly the hip flexors and the muscles surrounding the pelvis, until a spontaneous, fine trembling begins and is allowed to continue for a period of time while lying down, rather than being stopped as soon as the exercise portion ends.

The premise behind TRE is that many mammals visibly shake or tremble after a stressful or threatening event, a pattern often observed in animals returning to a calm state after a startle response, and that humans have largely learned to suppress this same reflex through social conditioning.

TRE is built on the idea that deliberately allowing this tremor response to occur, in a safe, controlled setting, may help the body settle out of a heightened stress state.

“I’ve watched this exact pattern play out at retreats more than once. A guest does a truly challenging hold, hips shaking, clearly fatigued, and instead of immediately standing up and shaking it off with a laugh the way most of us do out of habit, we let them stay with it for a minute longer. Almost every time, they come out of that noticeably calmer than when they went in. I can’t tell you the full mechanism behind that, but I’ve seen the pattern often enough to take it seriously.”

Terry Tateossian, Founder of The House of Rose

What Is the Proposed Mechanism Behind Neurogenic Tremor and the Nervous System?

The specific type of trembling TRE aims to produce is sometimes referred to as neurogenic tremor, a fine, involuntary tremor originating from the nervous system’s own regulatory activity rather than simple muscular fatigue alone.

Neurogenic tremor and nervous system mechanism infographic.

The proposed mechanism is that fatiguing certain muscle groups, particularly around the hips and lower spine, activates neural circuits involved in generating repetitive, semi-automatic movement patterns, and that this activation can extend into a spontaneous tremor response once the muscle is sufficiently fatigued.

The broader theory connects this tremor response to autonomic nervous system regulation, specifically the balance between sympathetic (“fight or flight”) and parasympathetic (“rest and digest”) activity.

The idea is that the tremor response may help shift the nervous system toward a more parasympathetic state. This overlaps conceptually with practices that support vagal tone and broader strategies for strengthening parasympathetic regulation, even though the underlying mechanism is different.

Important: This mechanism, while biologically plausible and consistent with some established principles of stress physiology, has not been definitively confirmed through the same volume or rigor of research as more established nervous-system practices like breathwork or meditation. It should be understood as a reasonable working theory, not settled science.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Do the Actual Exercises Involve?

TRE sessions typically begin with a short series of positions intended to progressively fatigue the hip flexors, inner thighs, and surrounding muscles.

TRE exercise sequence for muscle fatigue and tremor response.

A typical sequence includes:

  • A single-leg calf raise held close to fatigue, on each side.
  • A single-leg hinge or reach position that fatigues the hamstrings and glutes.
  • A standing forward-fold or hamstring stretch.
  • A wall sit, gradually adjusted deeper as fatigue builds.
  • A final reclined position with the hips elevated and knees bent, where the tremor response, once triggered, is allowed to continue for several minutes.

The tremor itself, when it begins, is usually described as a fine trembling, most often starting in the legs and hips, rather than a large or dramatic movement. Sessions are typically kept short for beginners, in the range of a few minutes, with the length increased gradually over weeks as tolerance and familiarity build.

A quick shake of the arms or legs after a tough set is a brief, voluntary movement most people do instinctively. TRE is a more sustained, deliberately extended version of the body’s own tremor response, held for minutes rather than seconds, which is part of why it’s approached as its own structured practice rather than something to casually add to the end of a workout without guidance.

What Does the Evidence Actually Show?

Research specifically on TRE remains limited and preliminary compared to more established mind-body practices. A small number of published pilot studies have examined TRE’s effects on measures like perceived stress and self-reported anxiety in specific populations, with some reporting modest improvements, but sample sizes in this research have generally been small, and independent replication remains limited.

It’s worth being direct about what this means in practice: TRE has a plausible physiological rationale and growing practitioner interest, but its evidence base is still much smaller than that of more established practices such as structured breathwork and mindfulness meditation, which have been studied more extensively across stress regulation, attention, and nervous system function.

Claims connecting TRE to resolution of specific medical conditions should be treated as anecdotal rather than established, since they haven’t been confirmed through controlled research.

Important: TRE is not a substitute for evidence-based treatment of diagnosed anxiety, depression, PTSD, or other psychiatric conditions. It may be a reasonable complementary practice for some people, ideally alongside, not instead of, appropriate professional care.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Do Normal Exercise Tremor, TRE, and Warning Signs Differ?

It’s worth clearly distinguishing three different things that can all look similar from the outside.

Type What It Looks Like What It Means
Ordinary exercise fatigue tremor Shaking during or right after a hold, subsides within minutes Normal motor unit fatigue, not a concern
TRE neurogenic tremor Fine trembling triggered deliberately, continues for minutes in a reclined position Proposed nervous system response, generally considered safe for most people
Concerning tremor Shaking unrelated to recent exertion, or with weakness, numbness, slurred speech, or coordination loss Warrants prompt medical evaluation

Important: Any tremor accompanied by weakness, numbness, difficulty speaking, vision changes, or loss of coordination is a medical concern requiring prompt evaluation and is not something to address through TRE or any self-directed exercise practice.

Who Should Work With a Practitioner First?

TRE’s developer and experienced practitioners consistently recommend working with a trained, trauma-informed practitioner rather than starting alone for anyone who identifies as carrying significant unresolved trauma.

TRE practitioner guidance for trauma safety.

This isn’t an overly cautious footnote, it reflects a real consideration: deliberately working with the nervous system’s stress response can surface difficult material, and doing that without support carries real risk for some people.

Reasonable candidates for a supervised, practitioner-guided introduction rather than a self-directed start include anyone with PTSD or a trauma-related diagnosis, a history of dissociation, or significant unprocessed grief or trauma.

For most people without that history, a cautious, well-informed self-directed start following reputable guided instruction is generally considered reasonable, though starting conservatively is still the right approach.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Can You Try It Safely?

Start with short sessions, a few minutes at most, and stop if anything feels overwhelming rather than simply uncomfortable. There’s a meaningful difference between physical fatigue discomfort and genuine emotional distress, and the second is a reason to pause and seek guidance, not push through.

Safe TRE practice steps infographic
  • Begin with the fatigue-inducing positions (calf raise, hip hinge, wall sit) at a manageable intensity, not maximum effort.
  • Move into the reclined position and allow, rather than force, any trembling that begins.
  • Keep initial sessions to 5 minutes or less, gradually extending over weeks.
  • Practice in a private, quiet space where you feel physically safe.
  • Stop and rest if the sensation becomes distressing rather than simply unfamiliar.
  • Seek a trained practitioner if you have a significant trauma history before continuing further.

Your Next Steps

  1. If you’re simply curious about the physiology, notice the trembling during your next wall sit or long isometric hold and recognize it as a normal response to muscular fatigue rather than something that automatically signals a problem.
  2. If you want to explore TRE specifically, start with short, conservative sessions and reputable guided instruction so you can become familiar with the response gradually.
  3. If you have a significant trauma history or feel easily overwhelmed by body-based practices, consider working with a trained, trauma-informed practitioner rather than experimenting on your own.
  4. Broaden the nervous system side of the practice with simple vagus nerve exercises that support relaxation and parasympathetic activity through breathing and other calming inputs.
  5. Support the muscular demands of isometric training by using the free macro calculator to estimate calorie and protein targets that better match your activity level and training goals.

For a more immersive introduction to body-based nervous system support, THOR’s women’s yoga, hiking & wellness retreats combine guided movement, restorative practices, and nervous system regulation in a structured in-person setting.

Important: This article is educational and does not replace individualized medical or mental health care. Please consult a physician or a trauma-informed practitioner before starting TRE if you have a significant trauma history, a psychiatric diagnosis, or any concerns about how your body might respond.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

Is the shaking during TRE the same as shaking from a hard workout?

They share the same underlying fatigue-related tremor mechanism, but TRE deliberately extends and works with that tremor in a reclined position rather than treating it as an incidental side effect of exercise.

Is TRE scientifically proven?

The evidence base is preliminary. Small pilot studies suggest possible benefits for perceived stress, but the research volume and rigor don’t yet match more established practices like meditation or structured breathwork.

Can TRE cure anxiety, IBS, or autoimmune conditions?

No condition-specific cure has been established through controlled research. Anecdotal reports describing a wide range of effects exist, but they should be treated as unverified individual experiences, not established outcomes.

Is it normal for the tremor to feel strange or unfamiliar at first?

Yes. Most people aren’t used to consciously allowing this kind of movement, since social conditioning generally teaches suppression of visible trembling, so it commonly feels unusual before it feels familiar.

How long should a beginner TRE session last?

A few minutes is a reasonable starting point, with gradual increases over several weeks as familiarity builds, rather than starting with a long session.

Should I do TRE if I have a significant trauma history?

Work with a trained, trauma-informed practitioner rather than starting alone. This is a widely echoed recommendation among TRE practitioners and a reasonable safety precaution.

Can TRE replace therapy or psychiatric treatment?

No. It may be a reasonable complementary practice for some people but should not replace evidence-based treatment for diagnosed mental health conditions.

Why do my legs specifically shake more than other muscle groups during isometric holds?

The hip flexors and leg muscles are large, heavily used, and frequently fatigued muscle groups in everyday movement, which is part of why they’re a common site for both ordinary exercise tremor and the tremor response TRE aims to trigger.

Is shaking during a wall sit a sign I’m not strong enough?

No. Trembling during a challenging isometric hold reflects normal motor unit fatigue and is expected as the hold approaches your current capacity, not a sign of inadequate strength.

Does TRE require any equipment?

No. The exercises use bodyweight and a wall for the wall-sit position, along with a mat or comfortable floor surface for the reclined portion.

How often can TRE be practiced?

Many practitioners suggest starting with a few sessions per week and adjusting frequency based on how the body responds, since individual tolerance varies.

Can men and women both practice TRE, or is it different by sex?

The practice itself isn’t sex-specific, though hormonal factors during perimenopause and menopause may influence baseline nervous system reactivity, which is part of why starting conservatively is a reasonable approach for women navigating this transition.

What if nothing happens during my first session?

This is common and doesn’t mean the practice isn’t working. Response varies significantly between individuals and even between sessions for the same person.

Is TRE the same thing as somatic experiencing or other trauma-focused body therapies?

They share some conceptual overlap (working with the body’s stress response rather than only the mind) but are distinct approaches with different specific techniques and training requirements.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.

References

  • Berceli, D. The Revolutionary Trauma Release Process: Transcend Your Toughest Times. Namaste Publishing (foundational TRE methodology text).
  • Berceli, D., Salmon, M., Bonifas, R., & Ndefo, N. (2014). Effects of self-induced unclassified therapeutic tremors on quality of life among non-professional caregivers: a pilot study. Global Advances in Health and Medicine, 3(5), 45-48.
  • Enders, G. Clinical overview of neurogenic and physiological tremor classification. Movement disorder reference literature.
  • National Institute of Neurological Disorders and Stroke. Patient education materials on tremor types and when to seek evaluation.
  • Porges, S. W. Polyvagal theory and autonomic nervous system regulation, foundational stress physiology framework.
  • American College of Sports Medicine position materials on motor unit recruitment and fatigue during isometric exercise.

Disclaimer: This article is educational and does not constitute medical or mental health advice. Tension and Trauma Releasing Exercises (TRE) intentionally work with the body’s tremor response and may not be appropriate for everyone. If you have PTSD, significant unresolved trauma, dissociative symptoms, a psychiatric condition, or concerns about how your nervous system may respond, consult a qualified trauma-informed practitioner or healthcare provider before trying TRE. Seek medical evaluation for tremors that occur without recent exertion or are accompanied by weakness, numbness, vision or speech changes, or loss of coordination.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Can You Sit Down and Stand Up Without Using Your Hands? What the Sitting-Rising Test Predicts

Every retreat week, there’s a moment during our floor-based movement sessions where I can tell, almost instantly, which guests are going to have the easiest week physically and which ones are going to need extra support getting in and out of certain postures. It’s not when we’re standing.

It’s the transition to and from the mat. Some women drop to the floor and spring back up without a second thought. Others lower themselves in stages, a hand here, a knee there, a small negotiation with gravity at every step, and getting back up takes visible effort and usually a piece of furniture within reach.

I used to think of this as flexibility, or maybe just a quirk of who happened to do yoga more often. After four years of watching this exact pattern repeat across dozens of women’s yoga retreats, I don’t think that anymore. What I was watching, without having the research language for it yet, was a real, measurable marker that clinicians have been studying for over two decades: how a person gets up off the floor predicts far more about their underlying health than it has any right to.

There’s a specific test built around this exact movement, and a body of published research tracking what a person’s score on it says about their long-term health. It started in a single exercise medicine clinic and has since been studied in thousands of people over more than a decade of follow-up. Here’s what it actually shows, how to score yourself, and, more usefully, what to do if your score isn’t where you’d like it to be.

Important: This article is educational and does not replace individualized medical advice. Women with joint replacements, recent surgery, significant balance impairment, or uncontrolled dizziness should consult a physician or physical therapist before attempting this test.

How Does the Sitting-Rising Test Work?

The sitting-rising test (SRT) was developed by Dr. Claudio Gil Araújo, a physician who runs an exercise medicine clinic in Rio de Janeiro, after he noticed a pattern among his patients: the ones who struggled to get down to the floor and back up without support tended to be the same patients whose overall health trajectory looked worse, often well before it showed up in standard lab work.

Sitting-rising test steps and scoring guide.

How to Take It

Stand barefoot on a flat, non-slippery surface, ideally with a carpeted or matted floor for comfort. Without leaning against anything, lower yourself to a seated position on the floor, then stand back up, using as little support as possible. There’s no time limit and no need to rush.

How It’s Scored

You start at 10 points, 5 allotted for sitting down and 5 for standing up. Each time you use a support, a hand on the floor, a forearm, a hand on your knee or thigh, or the side of your leg, you lose one point from that half of the movement. If you wobble or lose your balance at any point, you lose half a point. A perfect, fully unsupported sit and rise scores a 10.

Why Does This One Movement Reveal So Much?

Most fitness assessments test one system at a time. A treadmill test measures cardiovascular capacity. A grip strength test measures upper body strength. A flexibility screen measures range of motion.

Getting down to the floor and back up without support asks several systems to work together at once: leg strength, core strength, balance, flexibility through the hips and ankles, and coordination. If any one of those is significantly compromised, the score reflects it, because there’s no way to compensate for a weak link the way you might on a single-system test.

That’s part of why the test has held up so well across different research populations. It’s not measuring one narrow capacity. It’s measuring whether the whole functional system still works together the way it’s supposed to.

“I’ve watched women who look perfectly healthy standing up struggle to get off a yoga mat, and I’ve watched women who’d never call themselves ‘fit’ pop up like it’s nothing. It has almost nothing to do with how someone looks and almost everything to do with what’s actually happening in their hips, ankles, and core. That’s exactly why I think every woman should know her own score instead of guessing.”

Terry Tateossian, Founder of The House of Rose

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Did the Research Actually Find?

The first major test of the SRT followed just over 2,000 adults aged 51 to 80 for a median of 6.3 years, tracking their SRT scores against all-cause mortality.

Participants who scored in the lowest range, 0 to 3, had a substantially higher mortality risk than those who scored in the highest range, 8 to 10, and the gap between groups was large enough that researchers reported each single-point improvement in SRT score was associated with roughly a 21% reduction in all-cause mortality risk over the follow-up period.

One fewer hand needed on the floor was measurably associated with better long-term survival odds. That study was published in the European Journal of Preventive Cardiology in 2014, and it’s been cited widely since, in part because the test costs nothing, takes under a minute, and requires no equipment.

A larger, more recent follow-up study from the same research group has since extended these findings to a bigger cohort with a longer follow-up period, and has reported that the association holds, including a specific link to cardiovascular mortality, though the precise statistics from that expanded study weren’t independently verifiable at the time of writing and are noted here directionally rather than with specific figures.

Important: An SRT score is a marker associated with mortality risk in population-level research. It is not a diagnosis, and a lower score doesn’t mean a fixed outcome. It’s a signal worth acting on, not a verdict.

How Does the Companion Single-Leg Stance Test Work?

The same research group behind the SRT also studied an even simpler assessment: standing on one leg, unsupported, for 10 seconds. In a study of roughly 1,700 adults aged 51 to 75, published in the British Journal of Sports Medicine in 2022, about one in five participants couldn’t complete the 10-second single-leg stance.

Single-leg stance test infographic for balance and health.

Over a median follow-up of about seven years, those who failed the test had a meaningfully higher risk of all-cause mortality than those who passed, even after adjusting for age, sex, body mass index, and other health conditions.

The single-leg stance test adds another quick way to assess balance, with clear scoring thresholds and a practical progression for improving your result. Together, the SRT and single-leg stance test provide two free, one-minute assessments that can reveal useful information about strength, mobility, and balance without requiring a clinical visit.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Why Can a Simple Floor Test Outperform Some Clinical Measures?

A cardiovascular fitness test can tell you your heart and lungs are working well while saying nothing about whether your ankles have the mobility to get you off the ground. A blood panel can come back completely normal while muscle mass and balance are quietly declining in the background.

SRT showing strength, balance, flexibility, and coordination.

The SRT captures something those measures miss: whether strength, balance, flexibility, and coordination are all still functioning together, under real load, the way they need to for everyday independence.

This overlaps directly with sarcopenia, the age-related loss of muscle mass and function that can become increasingly important in midlife. The SRT offers one practical way to spot early functional changes in strength, mobility, and coordination before they become more obvious through falls, fractures, or difficulty with everyday movement.

Research on the SRT in populations recovering from conditions like stroke has found that rising scores correlate specifically with ankle strength and mobility, since getting up from the floor without using your hands requires meaningful work from the ankles, not just the legs and core.

Ankle mobility is rarely a focus of typical strength training, which is part of why a strong-looking training routine can still leave someone with a lower-than-expected SRT score.

What Does a Good Score Look Like by Age?

Reference data collected from thousands of non-athlete adults, organized by age and sex, gives a useful benchmark for where a given score falls relative to typical values.

Score Range General Interpretation
10 Full, unsupported sit and rise. Common in younger adults, uncommon after 55.
8-9 Strong functional capacity with minor support needed.
6-7 Moderate functional capacity; room for improvement in one or more systems.
4-5 Meaningful functional limitation; worth structured attention.
0-3 Significant functional limitation; consider professional guidance alongside training.

A perfect score of 10 is common among younger adults but becomes uncommon after age 55, and research suggests fewer than roughly 8% of adults over 55 achieve it. The test tends to be most useful for distinguishing meaningful differences in functional capacity roughly between ages 46 and 80, which is precisely the window where catching early decline matters most for long-term independence.

It’s also worth noting that people with a lifelong habit of floor-sitting or squatting, common in some cultures and less common in Western furniture-heavy lifestyles, tend to score higher across all age groups, meaning the test reflects movement habits over a lifetime, not just current-day fitness.

Guest A shows stronger overall function, while Guest B needs more strength, mobility, and balance training.

Guest A Guest B
Age 54 54
SRT Score 9 (used one hand briefly) 4 (needed both hands, a knee, and wobbled)
Likely contributing factors Good ankle mobility, regular strength training Limited hip/ankle mobility, minimal strength training, sedentary work
Suggested focus Maintenance, refine balance Structured strength, mobility, and balance program

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Can You Improve Your Score Based on What’s Actually Holding You Back?

Improving an SRT score isn’t about “exercising more” in a general sense. It’s about identifying which specific system cost you points and training that system directly.

Improve SRT score with strength, mobility, and balance training.
  • If you lost points because you needed a hand on the floor: This usually points to leg strength, particularly the quads and glutes. Focus on squats, step-ups, and sit-to-stand practice from a chair, gradually lowering the chair height or removing it entirely as strength improves.
  • If you lost points because you needed a hand on your knee or thigh: This often points to hip and ankle mobility rather than raw strength. Deep squat holds, ankle dorsiflexion stretches, and hip-opener stretches performed regularly can meaningfully improve this over several weeks.
  • If you lost points because you wobbled or lost balance: This points more directly to the balance system itself. Practicing the single-leg stance gives you a simple, targeted way to work on stability, postural control, and confidence on a narrower base of support.
  • If you lost points across the board: A lower score in several areas usually calls for a broader approach rather than one isolated fix. Combining strength, mobility, and faster force production—and understanding the role of power vs strength – can help address the multiple physical capacities involved in getting down to and up from the floor efficiently.

What Safety Notes Should You Know Before You Try It?

Practice near a sturdy chair or counter the first few times, especially if balance is a known concern.

Woman using chair support during a safe floor test.

If you have a recent joint replacement, significant knee or hip arthritis, uncontrolled dizziness, or a condition affecting balance, check with a physician or physical therapist before attempting a full, unsupported version.

There’s no penalty for using extra support while you’re building capacity; the goal is a safe, honest baseline, not a risky first attempt at a perfect score.

Your Next Steps

  1. Take the sitting-rising test once, safely, near a chair or counter for support if needed, and record your honest score.
  2. Identify which system cost you points—strength, mobility, or balance—using the breakdown above.
  3. If balance was the main issue, use the single-leg stance as a simple way to train stability and postural control directly.
  4. If strength was the broader limitation, understanding the difference between power and strength can help you build a more complete training plan around both force and speed.
  5. Retest in 4 to 8 weeks and track your score alongside your training. You can also use the free macro calculator to make sure your calorie and protein targets are supporting the muscle you’re working to build.

For a more immersive approach, THOR’s women’s wellness & yoga retreats incorporate guided movement, mobility, and strength work into the retreat experience, giving you a supportive setting to practice the same functional skills the SRT is designed to assess.

If you want a plan built around your own results, 1:1 nutrition coaching can help translate your SRT score into a more targeted training strategy focused on the areas that need the most attention.

Important: This article is educational and does not replace individualized medical advice. Please consult a physician or physical therapist before attempting this test if you have a joint replacement, recent surgery, or a condition affecting balance.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

What’s the difference between the sitting-rising test and the sit-to-stand test?

They’re related but distinct. The sitting-rising test (SRT), covered in this article, involves lowering all the way to the floor and standing back up. The sit-to-stand test typically refers to a chair-based assessment, often counting how many times someone can stand up and sit back down in 30 seconds, used commonly in physical therapy and geriatric settings.

What’s considered a “good” SRT score?

Generally, a score at or above the 50th percentile for your age and sex is considered a reasonable target, which for most midlife women falls somewhere in the 7 to 9 range, though this varies by age.

Can I improve my score, or is it fixed by genetics and age?

It can be improved. Strength, mobility, and balance are all trainable at any age, and the specific deficiency behind a low score (strength, mobility, or balance) points directly to what to train.

Is a low score a diagnosis of something serious?

No. It’s a marker associated with mortality risk at a population level in research studies, not an individual diagnosis. A low score is a signal to pay attention to, not a medical verdict.

How often should I retest my score?

Every 4 to 8 weeks is reasonable while actively working on the systems behind a low score, since meaningful strength and mobility changes typically take several weeks to show up.

Is it normal to lose points even if I consider myself fit?

Yes. Cardiovascular fitness and general “fitness” don’t always translate to floor mobility, since the SRT specifically tests a combination of strength, hip and ankle mobility, and balance that many training programs don’t directly address.

Does the test work the same for someone with knee or hip arthritis?

The test can still be informative, but modifications and physician guidance are appropriate, since arthritis can affect the movement independent of overall functional capacity. Don’t force a full unsupported attempt if it causes pain.

Why does ankle mobility matter so much for this test?

Getting up from the floor without using your hands requires meaningful ankle dorsiflexion (the ability to bring your shin toward your foot), a range of motion that’s rarely trained directly and tends to decline with age and sedentary habits.

Can children or very fit young adults score below 10?

Rarely, but it can happen, particularly if flexibility or coordination is limited despite good strength. The test is most useful and most differentiating in adults roughly 46 and older.

Does practicing the test itself count as training?

Practicing the movement pattern helps with coordination and confidence, but true score improvement usually requires targeting the underlying strength, mobility, or balance deficit directly, not just repeating the test.

Is the sitting-rising test culturally biased toward people who squat regularly?

To some degree, yes. People with a lifelong habit of floor-sitting or squatting tend to score higher, which researchers have noted as a limitation. It doesn’t invalidate the test’s value as a personal baseline and tracking tool, but it’s a reasonable caveat when comparing scores across very different lifestyle backgrounds.

Should I do this test alone or with someone watching?

Either works for a general self-assessment, but having someone watch the first attempt, especially if balance is a concern, adds a safety margin and can help catch small support movements you might not notice yourself doing.

How does this relate to sarcopenia?

The SRT is one practical way to catch the functional consequences of sarcopenia, age-related muscle loss, before they show up as a fall or loss of independence. THOR’s Sarcopenia guide covers the full picture of why this muscle loss happens and how to address it.

What if I can’t get to the floor at all right now?

That’s valuable information on its own and a strong reason to start with the individual components (chair-based sit-to-stand practice, hip and ankle mobility work) before attempting the full floor version, ideally with guidance from a physical therapist.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.

References

  • de Brito, L. B. B., Ricardo, D. R., Araújo, D. S. M. S., Ramos, P. S., Myers, J., & Araújo, C. G. S. (2014). Ability to sit and rise from the floor as a predictor of all-cause mortality. European Journal of Preventive Cardiology, 21(7), 892-898.
  • Araújo, C. G., de Souza e Silva, C. G., Laukkanen, J. A., Fiatarone Singh, M., Kunutsor, S. K., Myers, J., et al. (2022). Successful 10-second one-legged stance performance predicts survival in middle-aged and older adults. British Journal of Sports Medicine, 56(17), 975-980.
  • Araújo, C. G., et al. Age- and sex-specific reference values for the sitting-rising test in a large non-athlete adult population. European Journal of Preventive Cardiology.
  • National Institute on Aging patient guidance on functional fitness assessments and fall risk.
  • American Physical Therapy Association clinical guidance on sit-to-stand testing in older adults.

Disclaimer: This article is educational and does not constitute medical advice. The sitting-rising test requires adequate strength, mobility, coordination, and balance, and may not be appropriate for everyone. If you have a joint replacement, recent surgery, significant knee or hip pain, dizziness, balance problems, or another condition affecting safe movement, consult a physician or physical therapist before attempting the test or following the exercises in this article.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Why You Lose Balance Younger Than You Think (And How to Get It Back)

Paula was forty-four when she stepped off a paddleboard and went straight down into three feet of water, no wave, no current, nothing to blame but her own body failing to make a correction it should have made automatically. She laughed it off with the friends she was with, the way you do, but she told me about it months later at a women’s yoga retreat because it had quietly bothered her ever since.

She’d always thought of herself as coordinated. Balance problems were an old-lady thing, something her mother dealt with, not something that happened to a woman still doing hot yoga three times a week. What Paula didn’t know, and what almost nobody tells women in their 40s, is that the systems responsible for balance don’t wait until your 70s to start declining.

Research on postural control and balance-related sensory systems shows measurable changes beginning decades earlier than most people assume, often well before anyone notices a problem in daily life. By the time a stumble off a paddleboard or a missed curb gets someone’s attention, the underlying decline has usually been building quietly for years.

Falls remain one of the leading causes of injury-related disability and death in older adults, but the systems that prevent falls don’t fail all at once in old age. They erode gradually, starting earlier than almost anyone expects, which means the window to catch and address that decline opens far sooner than most balance content acknowledges.

Important: This article is educational and does not replace individualized medical advice. Sudden, severe, or worsening balance problems, especially with dizziness, vertigo, or vision changes, warrant a medical evaluation rather than a self-directed exercise plan.

When Does Balance Decline Begin?

Balance isn’t a single skill. It’s the output of several sensory and physical systems working together continuously, and research measuring postural control across age groups has found that subtle changes in that coordination can begin as early as the 40s, well before most people notice any functional problem in daily life.

Balance changes can begin in your 40s

The decline is gradual and largely invisible at first, showing up in lab measures like postural sway and reaction time long before it shows up as an actual stumble.

This is part of why balance training so often gets postponed. Nothing feels wrong yet, so there’s no obvious reason to address it, and by the time something does feel wrong, a meaningful amount of underlying capacity has often already eroded.

“I’ve had more than one retreat guest in her mid-40s tell me some version of Paula’s story, a stumble that came out of nowhere, a moment on a hike or in the shower where their body just didn’t correct the way they expected. Almost every one of them had assumed balance wasn’t something they needed to think about yet. I tell them the same thing every time: the earlier you catch it, the easier it is to train.”

Terry Tateossian, Founder of The House of Rose

What Are the Three Systems That Create Balance?

Balance depends on three sensory systems sending information to the brain, plus the muscular system that acts on that information. When any one of the three is compromised, the others have to work harder to compensate, and compensation only goes so far.

  • The vestibular system: Located in the inner ear, detects head position and movement and is often the first system people think of when they hear the word “balance.” It’s responsible for that specific, disorienting feeling of vertigo or dizziness when it isn’t working correctly.
  • The visual system: Provides information about the body’s position relative to the surrounding environment. This is why balance often feels noticeably worse in dim lighting or with eyes closed, the visual system is doing more balance work than most people realize, even when it doesn’t feel like it.
  • The proprioceptive system: Sensors in the muscles, joints, and skin (especially the feet and ankles), reports the body’s position in space without needing to look at it. This is the system responsible for knowing where your foot is on uneven ground without staring at it.

Important: Weakness or decline in any one of these three systems can often be compensated for by the other two, up to a point. This is part of why balance problems can go unnoticed for years. The compensation works, until it doesn’t, often at the exact moment an unexpected demand (a curb, a wet floor, a sudden stop) exceeds what the remaining systems can handle.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Changes Specifically in Midlife?

Several midlife-specific factors compound the general age-related decline described above.

Midlife changes affecting balance through muscles, hormones, and vision.
  • Muscle mass and proprioceptive sensitivity decline together: Sarcopenia, the age-related loss of muscle mass that often begins in the 40s, doesn’t just reduce strength. It reduces the density and sensitivity of the proprioceptive sensors embedded in that muscle tissue, meaning less muscle often means less accurate positional feedback, not just less force production.
  • Hormonal shifts affect the vestibular system too: Estrogen receptors are present in the inner ear’s vestibular structures, and some research suggests the hormonal fluctuations of perimenopause and menopause may contribute to the dizziness and balance complaints many women report during this transition, independent of any inner ear disease.
  • Vision changes accelerate: Presbyopia (the age-related loss of near-focus ability) typically becomes noticeable in the 40s, and changes in depth perception and contrast sensitivity, both important for navigating uneven or dimly lit surfaces, often follow in the decade after.

The ankle is one of the most concentrated sources of proprioceptive feedback in the entire body, and ankle mobility tends to quietly decline with sedentary habits and unsupportive footwear well before it becomes noticeable.

This is part of why the sitting-rising test can reveal mobility limitations that often go unnoticed. A body can be strong through the hips and core while still carrying a meaningful, unaddressed ankle mobility gap.

What Overlooked Causes Affect Balance?

Beyond the three core systems, several common, frequently overlooked factors contribute to balance decline.

  • Medications: Several common medication categories, including blood pressure medications, certain antidepressants, and sedatives, can affect balance as a side effect, sometimes subtly enough that the connection isn’t obvious. A medication review with a physician or pharmacist is a reasonable step for anyone noticing new balance changes, particularly after starting a new prescription.
  • Low vitamin D: Vitamin D receptors are present in muscle tissue, and low vitamin D status has been associated with reduced muscle function and increased fall risk in multiple studies, making it a worthwhile lab value to check.
  • Alcohol: Even moderate alcohol intake temporarily impairs both the vestibular system and reaction time, and the effect can persist longer than the sensation of intoxication does.
  • Footwear: Unsupportive or overly cushioned footwear can dull the proprioceptive feedback from the feet, while high heels shift the body’s center of gravity forward in a way that changes the entire balance equation.
  • Sedentary time: Extended periods of sitting reduce the frequency of the small, constant balance corrections that daily movement normally provides, meaning the systems involved get less practice than they would in a more active day.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Why Do Falls Carry More Risk Than People Realize?

Falls are consistently reported as one of the leading causes of both fatal and non-fatal injury among older adults, and the risk profile isn’t limited to advanced age.

Fall risk, balance, and bone strength infographic

A fall that would have been a minor stumble in someone’s 20s can result in a fracture in someone’s 50s or 60s, partly because bone density has often already declined by that point and partly because the same systems responsible for the fall itself, reduced muscle mass, slower reaction time, are also involved in how the body absorbs impact.

Improving balance helps reduce the chance of falling, while stronger bones can reduce the severity of injury if a fall does happen. That is why bone density exercises pair so naturally with balance training, addressing both sides of the same midlife fall-prevention strategy.

Important: A fall isn’t only a physical event. Fear of falling after a first fall often leads people to reduce activity, which accelerates the exact muscle and balance decline that caused the fall in the first place. Addressing balance proactively, before a fall happens, avoids that entire downward cycle.

How Can You Test Your Own Balance Right Now?

Two free, one-minute tests give a useful baseline without any equipment.

  • The single-leg stance test: Measures how long you can balance on one leg without support, giving you a simple snapshot of stability and control. THOR’s single-leg stance guide includes scoring thresholds and a practical progression for improving your result.
  • The sitting-rising test: Uses one floor-based movement to assess strength, mobility, coordination, and balance together. The sitting-rising test can help reveal limitations that may not show up during more isolated strength or balance exercises.

Taking both tests gives a more complete picture than either alone, since a low score on one but not the other points toward a specific system (pure balance versus combined strength-and-mobility) being the priority to train first.

How Should You Train Balance by System, Not Just by Habit?

Generic balance exercises help, but targeting the specific system behind a low score produces faster results than a one-size-fits-all routine.

Balance training by vestibular, visual, proprioceptive, and strength systems
  • For vestibular-specific training: Slow head turns while maintaining focus on a fixed point, standing balance with eyes closed (near a wall or counter for safety), and gentle rotational movements that challenge the inner ear without triggering dizziness.
  • For visual-system training: Balance practice in varied lighting conditions, and exercises that involve tracking a moving object while maintaining a stable stance.
  • For proprioceptive training: Barefoot balance work on varied surfaces (grass, sand, a folded towel), single-leg stance progressions, and ankle mobility drills that restore the range of motion needed for accurate positional feedback.
  • For strength-based balance support: Squats, step-ups, and lateral lunges build the muscular capacity needed to turn sensory feedback into a quick, effective balance correction. Understanding the difference between power and strength also helps explain why both force production and the ability to use that force quickly matter for staying steady and recovering from a stumble.

This chart helps you match common balance problems with the system most involved and the exercises that can help strengthen it:

If You Notice… Likely System Start Here
Dizziness with quick head movement Vestibular Slow head turns, gentle rotational drills
Worse balance in dim light or unfamiliar spaces Visual Varied-lighting balance practice
Trouble on uneven ground even in good light Proprioceptive Barefoot balance work, ankle mobility
Balance feels fine but strength feels weak Muscular Squats, step-ups, lateral lunges

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Can You Build a Weekly Balance Practice?

Balance training responds well to frequency over intensity. Three to five short sessions per week, 5 to 10 minutes each, tend to produce better results than one long weekly session, since balance is a skill that benefits from frequent, low-fatigue practice rather than occasional maximal effort.

Weekly balance practice infographic

A reasonable starting structure: two sessions per week focused on whichever system the testing in Section 6 identified as the priority, one session incorporating all three sensory systems together, and general strength training (already likely part of an existing routine) providing the muscular foundation underneath all of it.

Your Next Steps

  1. Take both the single-leg stance test and the sitting-rising test this week to establish a baseline.
  2. Identify which of the three balance systems (vestibular, visual, proprioceptive) is most likely behind any deficit, using the checklist in Section 7.
  3. Add 3 to 5 short, targeted balance sessions to your weekly routine, prioritizing the system that needs the most work.
  4. Review medications, vitamin D status, and footwear for overlooked contributing factors.
  5. Support the muscular foundation underneath your balance training with THOR’s free macro calculator to make sure protein intake matches your training load.

For guided, in-person balance and mobility work, THOR’s women’s yoga, hiking and wellness retreats build this kind of functional training directly into the schedule.

For a personalized program built around your specific test results, THOR’s 1:1 strength coaching program can structure training around the exact system your assessment reveals.

Important: This article is educational and does not replace individualized medical advice. New, severe, or worsening balance problems, especially with dizziness or vision changes, should be evaluated by a physician.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

At what age does balance start to decline?

Measurable changes in postural control and balance-related sensory processing can begin as early as the 40s, well before most people notice any problem in daily activities.

Why did I suddenly stumble or lose my balance when nothing seemed different?

A sudden stumble often reflects gradual, invisible decline finally exceeding what compensation from the other balance systems could handle, rather than a sudden new problem. It’s worth using as a prompt to test and train, not just brush off.

Is dizziness the same thing as a balance problem?

Dizziness is often related to the vestibular system specifically, while balance problems can stem from the vestibular, visual, or proprioceptive systems, or a combination. Persistent or severe dizziness warrants a medical evaluation.

Can menopause really affect balance?

Estrogen receptors exist in the inner ear’s vestibular structures, and hormonal changes during perimenopause and menopause may contribute to balance and dizziness complaints in some women, independent of any underlying inner ear disease.

What medications commonly affect balance?

Certain blood pressure medications, some antidepressants, and sedatives are among the categories most commonly associated with balance side effects. A medication review with a physician or pharmacist is worthwhile if balance changes coincide with a new prescription.

How quickly can balance training show results?

Many people notice improvement within a few weeks of consistent practice, though the sensory systems involved (particularly vestibular adaptation) sometimes take longer than muscular strength to fully retrain.

Should I see a doctor before starting balance exercises?

If balance problems are new, severe, associated with dizziness or vision changes, or following a fall, a medical evaluation is a reasonable first step before starting a self-directed program.

Is it normal to have worse balance in one direction or on one side?

Asymmetry is common and often reflects a previous injury, dominant-side habits, or an underlying strength imbalance. Testing both the single-leg stance and sitting-rising test can help identify whether one side is meaningfully weaker.

Does vision correction (glasses or contacts) affect balance?

Yes. Uncorrected vision changes can reduce the visual system’s contribution to balance, and an outdated prescription is a common, overlooked contributor worth ruling out.

Can I improve balance without any equipment?

Yes. All of the exercises in this article require nothing beyond a wall or counter for safety support, making balance training one of the most accessible types of training to start immediately.

How does alcohol affect balance beyond the night it’s consumed?

Alcohol’s effect on the vestibular system and reaction time can persist for longer than the felt sensation of intoxication, and frequent alcohol intake is associated with broader declines in balance-related measures over time.

What’s the connection between balance and bone density?

They address two different sides of fall risk. Balance training reduces the likelihood of a fall happening. Bone density determines how serious the consequences are if one does. Both matter together.

Is barefoot training better for balance?

For proprioceptive training specifically, yes, since footwear can dull the sensory feedback from the feet that proprioception relies on. This should be done on safe, appropriate surfaces rather than as a blanket recommendation for all activity.

Can balance decline be reversed, or only slowed?

Both are possible depending on the underlying cause and how early training begins. Muscular and proprioceptive contributions in particular tend to respond well to consistent, targeted training at any age.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.

References

  • Araújo, C. G., et al. Age- and sex-specific reference values for balance and functional testing in adult populations. European Journal of Preventive Cardiology.
  • Centers for Disease Control and Prevention. Older Adult Fall Prevention: facts about falls and injury statistics.
  • National Institute on Deafness and Other Communication Disorders. Balance disorders: causes, vestibular system overview.
  • American Academy of Otolaryngology. Patient education materials on vestibular function and age-related balance change.
  • Menant, J. C., et al. Vitamin D and muscle function, falls risk in older adults, systematic review data.
  • North American Menopause Society clinical guidance on vestibular and balance symptoms during the menopause transition.
  • National Institute on Aging. Fall prevention and balance exercise guidance for older adults.

Disclaimer: This article is educational and does not constitute medical advice. Balance problems can have many causes, including vestibular, vision, neurological, medication-related, and musculoskeletal factors. If you experience new, severe, or worsening balance problems, dizziness, vertigo, vision changes, fainting, or symptoms following a fall, consult a healthcare provider before starting the tests or exercises in this article. Perform balance exercises near a stable support and progress only within your current abilities.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

Why Nutrition Advice Is So Controversial (What 4 Years of Hosting Retreats Taught Me)

Four years ago, before our first yoga retreat, I asked every guest to fill out a short dietary form. Gluten-free, dairy-free, vegan, keto, no restrictions, whatever applied. I took the forms seriously, briefed our chef, labeled every dish, planned an entire week of meals around what fourteen women told me they needed.

By day two, the gluten-free woman was asking, quietly, if there was any way to get a slice of the coffee cake we’d made for someone else’s dietary needs. The vegan was finishing her plate faster when there happened to be a little parmesan folded into the risotto.

The woman who told me she was strict keto ordered a second glass of wine and a s’more at the fire pit that night, and neither seemed to register to her as a contradiction. Nobody was lying to me. They were describing an intention, and then living a slightly different reality, the way almost all of us do around food.

I didn’t understand yet how useful that observation would become. Four years and dozens of retreats later, I’ve fed hundreds of women, collected hundreds of dietary forms, and watched hundreds of those forms diverge from what happened at the table. And somewhere in that pattern is the real answer to a question that professional nutrition science has spent decades and millions of dollars trying to solve: why can’t anyone agree on the best way to eat?

Why Does the Nutrition Debate Never End (And Why Does Everyone Sound So Sure)?

Ask a room of nutrition-minded people what the best diet for humans is and watch what happens. The keto crowd will say it’s keto. The vegans will say it’s plant-based. Someone will say Mediterranean, with the quiet confidence of a person who thinks they’re above the argument. And someone else will offer the increasingly popular non-answer: “the best diet is the one you’ll stick to,” which sounds wise until you remember that plenty of people could stick to fast food every day if given permission.

Nutrition debate and diet research infographic

Each camp has studies. Each camp has true believers. And the rest of us are left more confused than when we started. One recent survey found that eight in ten Americans say they don’t know what to believe about nutrition anymore, because the information seems to keep changing. That number was seven in ten just a few years earlier. We have more nutrition research available than at any point in history, and confidence in it keeps dropping, not rising.

That’s not a coincidence, and it’s not because nutrition scientists are incompetent or being paid off by industry, although that occasionally happens too. It’s because the thing nutrition science is trying to measure, how a specific way of eating affects a human body over years or decades, is one of the hardest things to study rigorously in all of science.

Why Is the Definitive Nutrition Study Impossible to Run?

Here’s what a truly definitive nutrition study would require. Take a large group of genetically similar people. Lock them in a controlled facility. Assign half to eat exactly one way and half to eat exactly another way, for decades, with zero deviation. Control every other variable, exercise, sleep, stress, sunlight, alcohol. Then measure health outcomes and mortality at the end.

No ethics board on earth would approve that study, and no human being would volunteer for it. So nutrition science has to work around that impossibility using imperfect substitutes, and every one of those substitutes introduces its own blind spot.

Important: This isn’t a reason to distrust nutrition science altogether. It’s a reason to understand why any single study, especially one making headlines, deserves more skepticism than the confident headline usually invites.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

What Are Four Ways We Study Food, and What Does Each One Get Wrong?

Four nutrition study methods and their limitations

Randomized Controlled Trials (RCTs)

Randomized controlled trials are the gold standard for testing a specific, narrow claim, such as whether a supplement changes a blood marker over 12 weeks. But RCTs testing entire dietary patterns over years are rarely done because they’re enormously expensive and nearly impossible to enforce for that long.

The few large diet RCTs that do exist, including trials on the Mediterranean diet, are extremely valuable. Still, they cannot run for the 30 or 40 years it may take conditions like heart disease or cancer to fully develop.

Observational or Cohort Studies

Observational or cohort studies follow large groups of real people over years, asking them periodically what they eat and then tracking health outcomes.

These studies have shaped decades of public health guidance. Their main weakness is their reliance on self-reported food intake, which can be notoriously unreliable.

Mechanistic and Animal Studies

Mechanistic and animal studies examine how nutrients behave at the cellular level or in animal models.

They are useful for generating hypotheses, but the findings do not always translate cleanly to how the same nutrient behaves in a free-living human eating a complex, varied diet.

Short-Term Feeding Trials

Short-term feeding trials place people in controlled settings for days or weeks and measure precise outcomes such as blood sugar or cholesterol response.

These studies are highly accurate for what they measure, but a few weeks tells us relatively little about what happens over a lifetime.

This table shows the strengths and limits of each nutrition study type:

Study Type What It’s Good At What It Gets Wrong
Randomized controlled trial Testing one specific, narrow claim precisely Rarely funded or feasible for whole diets over decades
Observational/cohort study Tracking real people over real years Relies on self-reported intake, which is often inaccurate
Mechanistic/animal study Explaining biological mechanism Doesn’t always translate to free-living humans
Short-term feeding trial Precise measurement over days or weeks Too short to capture long-term outcomes

No single method gives a complete picture. Each one sees a different slice of the truth, which is part of why headlines built on a single study so often contradict each other.

What Has the Say-Do Gap Taught Me About How Women Eat at Retreats?

This is where four years of hosting yoga retreats has taught me something the research methodology section above can only gesture at: the gap between what people report eating and what they eat isn’t a minor rounding error. It’s enormous, and it’s completely unconscious.

At nearly every women’s retreat, a pattern repeats. A guest tells me on her intake form that she’s gluten-free, and by the second or third night, she’s asking for a slice of whatever gluten-containing dessert is on the table, sometimes with a small, genuine laugh about it, sometimes without seeming to register the contradiction at all.

Guests who identify as vegan will finish a plate with a little cheese folded into it and not mention it, not because they’re being dishonest, but because in the moment, the identity (“I’m vegan”) and the behavior (eating the cheese anyway) aren’t occupying the same part of their attention.

Women who describe themselves as strict keto will order dessert at the fire pit and talk about their low-carb lifestyle in the same conversation, with no apparent friction between the two.

“After four years of collecting dietary intake forms and then watching what happens at the table, I’ve stopped being surprised by the gap. What surprised me at first was how unconscious it is. Almost nobody is lying on that form. They’re describing an intention, a version of themselves they believe in, and then living a slightly different reality a few days later. If that happens over one retreat week with me watching, imagine what it looks like over months of a self-reported food diary nobody is checking.”

Terry Tateossian, Founder of The House of Rose

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

Why Isn’t This About Willpower or Honesty?

It’s tempting to read the gluten-free-cake story as a case of weak willpower or dishonesty, but that misses what’s actually happening.

Food choices are shaped by hunger, social context, availability, and routine.

Identity-based food labels such as gluten-free, vegan, or keto often describe a goal or self-image more than consistent moment-to-moment behavior. The label can be sincere while daily eating still shifts based on:

  • Social context: What other people are eating or offering.
  • Hunger: Immediate appetite can override longer-term intentions.

  • Availability: What is actually on the table matters.
  • Routine and circumstance: Small daily decisions do not always match the broader label.

This is a normal human pattern, not a character flaw. And if it appears repeatedly in a controlled retreat setting, the same gap can easily show up in everyday life.

Why Does This Gap Skew the Research Itself?

Now connect this back to the four research methods above. Most large nutrition cohort studies rely on people accurately reporting what they eat, often through food frequency questionnaires filled out periodically over months or years.

If the gap I’ve watched play out over a single retreat week is real, and I’d argue four years of consistent, repeated observation makes a fairly strong case that it is, then imagine that same gap playing out across a self-reported diet study with tens of thousands of participants, none of whom are being watched at every meal the way retreat guests unknowingly are.

This is a big part of why nutrition epidemiology has such a difficult reputation. It’s not that the researchers are careless. It’s that the data they’re working with, self-reported human eating behavior, carries the same say-do gap I’ve watched unfold in person for four years, just at a scale no one can directly observe or correct for.

Here’s how the say-do gap can distort the data:

What a Participant Reports What Likely Happened Effect on Study Data
“I follow a low-sugar diet” Occasional dessert not recalled or reported Sugar intake underestimated
“I rarely drink alcohol” Social drinking underrecalled or minimized Alcohol-related health effects harder to isolate
“I eat mostly plant-based” Animal products consumed in social settings, not logged Plant-based benefit may be over- or underestimated

None of this means self-reported studies are worthless. It means their conclusions deserve to be read as directional evidence gathered under real-world limitations, not as precise measurements.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

What Is the Blind Men and the Elephant Problem With Diet Gurus?

There’s an old parable about several blind men each touching a different part of an elephant, the trunk, the ear, the leg, and each confidently describing a completely different animal based on the one part they could feel. Nutrition advice online often works the same way.

The keto researcher has spent years studying insulin and carbohydrate metabolism, so that’s the part of the elephant she’s touching, and she’s not wrong about what she’s found. The vegan researcher has spent years studying plant compounds and cardiovascular markers, and he’s not wrong about what he’s found either. Neither is lying. Neither has the whole animal.

This is why picking a single guru and following their advice as though it’s the complete picture tends to disappoint people over time. The research any one expert is fluent in is usually real, but it’s a slice, not the whole structure.

What Still Works Despite All of This?

Healthy nutrition patterns infographic

None of the above means nutrition science is useless or that nothing can be trusted. Large, long-running cohort studies, imperfect as they are, have consistently pointed toward the same handful of patterns across different populations and decades:

  • Whole foods: Diets built primarily around minimally processed foods consistently align with better long-term health outcomes.
  • Adequate protein: Sufficient protein supports muscle maintenance, metabolic health, and healthy aging.
  • Vegetables: Regular vegetable intake remains a recurring feature of dietary patterns associated with better health.
  • Minimal ultra-processed food: Lower consumption of ultra-processed foods consistently associates with better long-term outcomes.
  • Overall dietary pattern: These findings remain fairly consistent regardless of which specific nutrition “camp” frames the advice.

The Mediterranean dietary pattern, in particular, has more randomized controlled trial support than almost any other whole-diet approach. That is part of why it appears so often in serious nutrition guidance rather than fad-diet content.

A Mediterranean-style diet offers one of the better-studied whole-diet frameworks for midlife women, with stronger clinical trial evidence behind it than many competing dietary approaches.

Important: Imperfect research is not the same as no research. When the overall weight of evidence across different study types consistently points in the same direction, it is more trustworthy than any single headline-grabbing study viewed in isolation.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

What Do I Eat (And Tell Every Client)?

After four years of watching intention and behavior diverge at my own dinner tables, and after 25 years running businesses before that, here’s the principle I use, and the one I give every client and retreat guest: track what you actually eat, not what you intend to eat, for at least a week, before deciding what “diet” you’re even following.

This is the entire logic behind THOR’s approach to macros. Not because macro tracking is magic, but because it closes the say-do gap this article is built around. A food log with real weights and real numbers doesn’t care what identity a person holds about their eating. It shows the plate as it was.

“I don’t ask clients what kind of diet they follow anymore, at least not first. I ask them to track one honest week. Almost every time, the gap between what they believed about their own eating and what the log showed was the most useful information in the entire process. That gap is the real starting point, not the label.”

Terry Tateossian, Founder of The House of Rose

Understanding where your actual intake differs from what you expected is useful, but the next step is learning how to interpret those numbers correctly. THOR’s guide to macro fundamentals after 50 explains how tracking protein, carbohydrates, fats, and overall calories can help you spot patterns and make more informed adjustments.

Your Next Steps

Five-step nutrition plan for tracking food and setting macro goals.
  1. Before adopting or continuing a specific diet label, track one honest week of exactly what you eat, weighing and logging your portions as accurately as possible.
  2. Compare what the log shows with what you believed about your eating beforehand. That gap can reveal portion patterns, overlooked calories, or nutrient imbalances that are difficult to spot from memory alone.
  3. Make sure you understand the basics of tracking and balancing macros so the information you collect gives you a more accurate picture of your current intake.
  4. Instead of relying on a restrictive diet label, consider a Mediterranean-style approach built around whole foods, protein, fiber, healthy fats, and other foods that support midlife nutrition.
  5. Once you understand what you are eating, use the free macro calculator to establish personalized calorie and macro targets based on your body, activity level, and goals.

If you’d like to experience this philosophy in practice, THOR’s women’s wellness retreats bring together structured meals, real food, movement, and nutrition support without demanding perfection at every meal.

For a more individualized approach, 1:1 coaching can turn what your food log shows into a personalized nutrition and training strategy rather than forcing your habits into a predefined diet label.

Important: This article reflects general nutrition science literacy and Terry’s personal and professional observations. It is not individualized medical or dietary advice. Women with specific medical dietary restrictions, including celiac disease or diagnosed food allergies, should continue following the recommendations provided by their healthcare professionals.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

Frequently Asked Questions

Why do nutrition experts disagree so often?

Because they’re often studying different slices of a very complex system using different research methods, each with real but partial evidence. No single study or expert has the complete picture, which is part of why confident-sounding advice can still conflict.

Is nutrition science reliable, or should I ignore it?

It’s reliable in aggregate, when many imperfect studies using different methods all point the same direction, and less reliable when relying on any single study, especially one behind a dramatic headline.

What is the “say-do gap” in nutrition?

It’s the difference between what people report eating and what they eat, which tends to be larger and more common than most people realize, and which research increasingly recognizes as a major source of noise in self-reported dietary studies.

Why do people say they’re gluten-free, vegan, or keto and then not fully follow it?

Usually not out of dishonesty. The label often reflects a sincere intention or identity, while day-to-day eating is shaped by context, social settings, and hunger in ways the label doesn’t always predict.

Is the Mediterranean diet better supported than other diets?

It has more randomized controlled trial evidence behind it than most whole-diet approaches, which is a meaningfully stronger evidence base than diets supported mainly by observational data or theory.

Should I trust a nutrition influencer who cites a lot of studies?

Citing studies isn’t the same as representing the full body of evidence. It’s worth asking whether the studies cited are representative of the overall body of research or a selectively chosen subset that supports a predetermined conclusion.

How can I know what I eat if my own perception is unreliable?

Structured food tracking with a scale, for at least a week, is the most reliable way to see actual intake rather than intended or remembered intake.

Does this mean calorie and macro tracking apps are more trustworthy than self-report studies?

When used consistently and accurately, yes, because they capture intake at the point of eating rather than relying on memory or self-image days or weeks later. Accuracy still depends on avoiding common tracking mistakes.

Why do some foods get blamed for cancer one year and celebrated the next?

Large-scale reviews of nutrition research have found that a striking number of common ingredients have been linked to both increased and decreased disease risk across different studies, often because observational associations are sensitive to small differences in study design and population.

Is “eat the diet you can stick to” good advice?

It’s a useful starting filter, but not a complete answer, since plenty of unsustainable eating patterns are also easy to “stick to” without producing good health outcomes. Sustainability matters, but it isn’t the same as effectiveness.

What does THOR recommend instead of picking a diet camp?

A whole-food, protein-forward, Mediterranean-influenced framework, personalized through actual tracked intake rather than self-identified labels, is the approach THOR builds all of its nutrition content around.

How long should I track before I trust what I’m seeing?

At least one full week, including a weekend, since eating patterns often shift meaningfully between structured weekdays and less structured weekends.

Does the say-do gap apply to exercise self-reporting too?

Yes, the same pattern (reported intention diverging from actual behavior) shows up in self-reported exercise data, though this article focuses specifically on the food side of it.

Is it normal to be confused about nutrition advice after years of trying to “figure it out”?

Completely normal, and the confusion is a reasonable response to a truly difficult research problem, not a sign of personal failure to understand something simple.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.

References

  • International Food Information Council. Annual Food and Health Survey (public confidence in nutrition information trend data).
  • Ioannidis, J. P. A. (2013). Implausible results in human nutrition research. BMJ, 347, f6698.
  • Schoenfeld, J. D., & Ioannidis, J. P. A. (2013). Is everything we eat associated with cancer? A systematic cookbook review. American Journal of Clinical Nutrition, 97(1), 127-134.
  • Willett, W. C., et al. Nurses’ Health Study, ongoing prospective cohort methodology and findings summary. Harvard T.H. Chan School of Public Health.
  • Estruch, R., et al. (2018). Primary prevention of cardiovascular disease with a Mediterranean diet supplemented with extra-virgin olive oil or nuts (PREDIMED trial). New England Journal of Medicine, 378(25), e34.
  • Subar, A. F., et al. (2015). Addressing current criticism regarding the value of self-report dietary data. Journal of Nutrition, 145(12), 2639-2645.
  • Archer, E., Hand, G. A., & Blair, S. N. (2013). Validity of U.S. nutritional surveillance: National Health and Nutrition Examination Survey caloric energy intake data, 1971-2010. PLOS ONE, 8(10), e76632.
  • Academy of Nutrition and Dietetics position statements on dietary pattern research and evidence hierarchy.

Disclaimer: This article is educational and does not constitute medical or individualized nutrition advice. Dietary needs vary based on health conditions, medications, allergies, intolerances, activity levels, and other personal factors. If you have celiac disease, diagnosed food allergies, diabetes, kidney disease, gastrointestinal conditions, or other medical dietary restrictions, consult a qualified healthcare provider or registered dietitian before making significant changes to your diet, calorie intake, or macronutrient targets.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

Why Tracking Macros Isn’t Working: 6 Common Mistakes

Wendy is fifty-two, and by every measure on her phone, she was doing everything right. Four weeks of logging her food daily, macros hitting her targets more nights than not, protein numbers she’d worked hard to get comfortable with. The scale hadn’t moved. Not up, not down, just a flat line that made her wonder if her body had simply stopped responding to anything at all.

It hadn’t. What Wendy had was a tracking practice that looked accurate and wasn’t, in a handful of specific, fixable places. She was logging chicken breast at the raw weight printed on the package, then cooking and eating the smaller, denser, higher-calorie-per-gram cooked portion.

She was deciding what to eat about ten minutes before she ate it, which meant her days were a chain of reasonable-sounding choices that didn’t add up to the numbers she thought they did. Neither mistake would show up as an error in the app. Both were quietly moving her actual intake away from her logged intake, day after day, for a month.

This is the pattern behind most macro tracking that “isn’t working.” It’s rarely about willpower, and it’s almost never about the app being wrong. It’s about a small number of specific, common errors that make logged numbers diverge from real numbers, invisibly, until someone points them out. Here are the six that matter most.

Important: This article is educational and does not replace individualized nutrition guidance. Women with a history of disordered eating should approach macro tracking cautiously and ideally alongside a registered dietitian or therapist, since precise food logging can be a difficult format for some people in recovery.

Are You Tracking Cooked Weight as Raw Weight or Vice Versa?

Raw vs cooked food weight tracking infographic

The Mistake

Weighing chicken, rice, oats, or pasta at one state (raw) and logging it under a database entry meant for the other state (cooked), or the reverse. Because cooking changes water content, cooked and raw weights of the same food carry meaningfully different calorie and macro density per gram.

A 6-ounce raw chicken breast becomes roughly 4.5 ounces once cooked, since it loses water weight during cooking, meaning the cooked chicken is denser in protein and calories per ounce than the raw version.

Why It Happens

Most food database entries default to raw weight for meats and dry goods like rice and oats, but people naturally weigh their food after it’s cooked and ready to eat, since that’s the moment they’re actually holding a plate.

If the app entry says “cooked” but the number logged was actually the raw weight, or the reverse, the error compounds at every single meal that includes that food.

How to Fix It

Pick one method and use it consistently: either weigh every meat and grain raw before cooking and log the raw-weight database entry, or weigh everything cooked and make sure the specific database entry selected says “cooked.” Rice, oats, and pasta follow the same rule, since they absorb water and roughly double or triple in weight once cooked.

Food Raw Weight Cooked Weight Approx. Change
Chicken breast 6 oz 4.5 oz Loses ~25% weight (water)
White rice 1/2 cup dry 1.5 cups cooked Gains ~200% weight (water)
Oats 1/2 cup dry 1 cup cooked Gains ~100% weight (water)
Ground beef (85/15) 4 oz 3 oz Loses ~25% weight (water and fat)

Important: If a recipe or database entry doesn’t specify raw or cooked, assume raw unless labeled otherwise, since that’s the more common default, and confirm before logging a new food for the first time.

Are You Pre-Planning Meals Before the Day Starts?

The Mistake

Deciding what to eat meal by meal, in the moment, rather than roughly mapping out the day’s meals in advance. This seems like a minor logistics issue, but it’s one of the biggest drivers of “surprise” macro overages, since reactive eating decisions are made under time pressure, hunger, or convenience constraints that don’t leave room to check how a choice fits the day’s remaining targets.

Why It Happens

Pre-planning takes a few extra minutes that feel unnecessary when someone already knows their target numbers. But knowing the target and having a plan for hitting it are different skills, and without a plan, the day tends to drift toward whatever’s easiest in the moment, then gets logged after the fact as a surprise.

How to Fix It

Spend five minutes each morning, or the night before, roughly mapping meals against the day’s targets. This doesn’t require a rigid recipe-level plan. Even a loose outline (breakfast: eggs and toast, lunch: chicken and rice bowl, dinner: flexible based on remaining macros) prevents the common trap of eating a good breakfast and lunch, then discovering at 6 p.m. that dinner has to fit into 300 remaining calories.

“The clients who struggle most with macros aren’t the ones who lack discipline. They’re the ones treating tracking as an after-the-fact record instead of a same-day plan. I tell every client the same thing: log tomorrow’s rough plan tonight, even if it changes. A five-minute plan beats a perfect memory every time.”

Terry Tateossian, Founder of The House of Rose

Why Does Pre-Planning Matter More in Midlife Than It Did at 25?

Hunger and fullness signals shift during perimenopause and menopause, often becoming less reliable cues for portion size than they once were. A meal plan that leans on “eating until satisfied” without a rough target in mind is more likely to under- or overshoot macros in midlife than it would have a decade earlier, which makes the five-minute planning habit more valuable now, not less.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

Are You Eyeballing Portions Instead of Weighing Them?

Weighing food portions for accurate tracking.

The Mistake

Estimating a portion size by sight (“that looks like about a cup”) rather than using a food scale, especially for calorie-dense foods like nut butters, oils, cheese, and granola, where a small visual misjudgment translates into a large calorie error.

Why It Happens

Weighing food feels tedious, and after a while, most people feel confident they can eyeball portions accurately. Research on portion estimation consistently shows that confidence and accuracy are not well correlated, and even experienced trackers tend to underestimate calorie-dense foods specifically.

How to Fix It

Keep a food scale on the counter, not in a cabinet, since visibility drives use. Weigh nut butters, oils, cheese, granola, and dried fruit every time, since these are the foods where eyeballing causes the largest errors. Lower-density foods like leafy greens or berries can be measured more loosely without meaningfully affecting accuracy.

How Does a Small Eyeballing Error Compound?

Food Estimated Portion Actual Weight Calorie Difference
Peanut butter “A tablespoon” (eyeballed) 1.5 tbsp actual +50 calories
Olive oil for cooking “A drizzle” 2 tbsp actual +240 calories
Shredded cheese “A handful” 1.5 oz actual +60 calories
Daily total if repeated +350 calories/day

Three small eyeballing errors, repeated daily, can add up to a few hundred calories a day, enough to stall progress even when every logged number looks accurate on paper.

Are You Forgetting the Small Stuff Like Oils, Sauces, and Drinks?

The Mistake

Logging the main components of a meal (protein, starch, vegetable) accurately while forgetting the cooking oil, salad dressing, condiments, coffee creamer, or beverages consumed alongside it.

Why It Happens

These items feel like afterthoughts rather than “real food,” so they’re mentally filed as not worth logging, even though many of them are calorically dense. A tablespoon of olive oil used in a pan, two tablespoons of ranch dressing, and a flavored coffee creamer can together add several hundred unlogged calories to a day that otherwise looks perfectly tracked.

How to Fix It

Log cooking oil at the point of adding it to the pan, not after cooking (it’s easy to forget once it’s absorbed into the food). Measure sauces and dressings the same way as any other food. Treat beverages, including alcohol, cream in coffee, and sports drinks, as loggable items rather than exceptions.

Important: Alcohol in particular is frequently under-tracked and interacts with the body’s fat-burning priority, since the body processes alcohol before fat, effectively pausing fat oxidation until the alcohol is cleared. This doesn’t mean alcohol can’t fit into a tracked plan, but it should be logged accurately rather than treated as a free pass.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

Are You Recalculating as Weight and Activity Change?

Recalculating macros as weight and activity change.

The Mistake

Setting macro targets once, at the start of a tracking journey, and never adjusting them as body weight changes, activity level shifts, or the original goal (fat loss, maintenance, muscle gain) evolves.

Why It Happens

Recalculating feels like starting over, and once a routine feels comfortable, most people are reluctant to change the numbers they’ve gotten used to hitting. But calorie and macro needs are a function of current body weight and activity, not the numbers from three months ago.

As weight drops, so does the number of calories needed to maintain the new, lower weight, which means the same targets that drove initial progress can quietly become a maintenance-level intake over time.

How to Fix It

Recalculate targets every 10-15 pounds of change, or every 6-8 weeks of consistent tracking without a weight change despite accurate logging elsewhere. THOR’s free macro calculator makes this a five-minute reset rather than a guessing exercise.

As your body, activity level, and goals change over time, your nutrition targets may need to change with them. Understanding the fundamentals of macros after 50 provides the foundation for adjusting protein, carbohydrates, fats, and overall calorie intake.

After a period of restriction, reverse dieting offers a structured way to increase calories gradually, while a more detailed reverse diet after 50 can help guide those adjustments step by step.

“I see this constantly with clients who lost the first fifteen pounds fast, then stalled for months while still ‘eating the same as before.’ The same numbers that created a deficit at 180 pounds are often close to maintenance at 165. Nothing about their tracking got worse. Their body just changed, and the targets didn’t follow it.”

Terry Tateossian, Founder of The House of Rose

Are You Tracking Weekdays Only and Calling It a Full Week?

The Mistake

Logging food diligently Monday through Friday, then tracking loosely or not at all on weekends, while still evaluating weekly progress as though the whole week was tracked consistently.

Why It Happens

Weekday routines tend to be more structured, with regular meal timing and fewer social eating occasions, which makes tracking easier. Weekends bring restaurants, gatherings, and looser schedules, all of which make tracking feel harder to maintain, so it often quietly drops.

How to Fix It

Weekend tracking doesn’t need to be as precise as weekday tracking to still be useful. A reasonable estimate logged for a restaurant meal is far more valuable than no log at all, since even an estimate keeps the week’s overall pattern visible.

If full tracking on weekends isn’t realistic, at minimum log a rough calorie estimate for restaurant or social meals rather than skipping the log entirely.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

What Does a Sample Day Done Correctly Look Like?

Meal What’s Logged Common Error Avoided
Breakfast Oats (logged as cooked weight, consistent with database entry) + berries + coffee with creamer (measured) Mistake 1 (cooked vs. raw) and Mistake 4 (forgetting creamer)
Lunch Pre-planned chicken and rice bowl, chicken weighed cooked, rice weighed cooked, dressing measured Mistake 2 (pre-planning) and Mistake 3 (weighing, not eyeballing)
Snack Greek yogurt + measured tablespoon of nut butter Mistake 3 (weighing calorie-dense foods)
Dinner Flexible based on remaining macros, but planned that morning, oil logged when added to the pan Mistake 2 (pre-planning) and Mistake 4 (logging cooking oil)
Weekly review Targets checked against current weight every 2 weeks; weekend restaurant meal estimated and logged Mistake 5 (recalculating) and Mistake 6 (weekend consistency)

What Does the Research Say About Tracking Accuracy?

Research on self-reported dietary intake consistently finds a gap between what people log and what they actually consume, with under-reporting most common for calorie-dense, less “photogenic” foods like oils, sauces, and alcohol, and portion-size misjudgment more common for energy-dense foods generally.

Research on food tracking accuracy and portion errors.

This isn’t a character flaw. It reflects genuine perceptual and logistical limits in estimating food weight and composition without a scale, and it’s exactly why the six mistakes above are so common even among motivated, consistent trackers.

Important: None of this is meant to suggest tracking should become obsessive. The goal of fixing these six mistakes is better accuracy with the same time investment, not more time spent tracking. A five-minute pre-planning habit and a kitchen scale solve most of the gap without adding meaningful daily effort.

What Are Your Next Steps?

  1. Pick one meat or grain you eat regularly and confirm whether you’re weighing and logging it consistently as raw or cooked.
  2. Spend five minutes tonight roughly planning tomorrow’s meals against your targets.
  3. Move your food scale to the counter and commit to weighing calorie-dense foods for the next week.
  4. Check whether it’s been more than 6-8 weeks, or 10-15 pounds, since your macros were last recalculated. If so, revisit THOR’s free macro calculator.
  5. Review THOR’s fundamentals of a macro diet for women over 50 for the full nutritional framework behind these numbers.

Accurate tracking is easiest to sustain with a food plan built around it. THOR’s Macro Miracle Mediterranean Cookbook provides pre-calculated recipes that remove the guesswork this article covers, since every recipe already accounts for cooked weights and hidden extras like oil and dressing.

For women who want a coached, personalized approach to building and adjusting a tracking practice over time, THOR’s 1:1 coaching program includes ongoing macro recalculation and troubleshooting as part of the process.

Supplement gaps that support a tracked nutrition plan, including protein and fiber options, are covered on THOR’s vitamins and supplements page.

Important: This article is educational and does not replace individualized nutrition guidance. Please consult a registered dietitian if you have a history of disordered eating before beginning detailed food tracking.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

Frequently Asked Questions

Should I weigh food cooked or raw?

Either works, as long as it’s consistent and matched to the correct database entry. The error happens when the weighing method and the logged database entry don’t match (weighing cooked chicken but logging it under a raw-weight entry, for example).

How much does the cooked-vs-raw mistake actually matter?

For protein sources like chicken, it can shift logged calories and protein by 20-25% per serving, which compounds significantly across a week of regular meals containing that food.

Do I really need to weigh everything, or just some foods?

Calorie-dense foods (oils, nut butters, cheese, granola, dried fruit) benefit most from weighing, since small volume misjudgments translate into the largest calorie errors. Lower-density foods like vegetables can be measured more loosely.

Is it normal for the scale not to move even when I’m tracking accurately?

Short plateaus (1-2 weeks) are normal due to water retention and other factors. Longer plateaus (4+ weeks) despite consistent tracking are the signal to check for one of the six mistakes above, particularly Mistake 5 (needing a recalculation).

How often should I recalculate my macros?

Every 10-15 pounds of weight change, or every 6-8 weeks if weight hasn’t changed despite accurate tracking, whichever comes first.

Does alcohol really affect fat loss if it fits my macros?

Yes, independent of whether it “fits.” Alcohol is processed before fat, temporarily pausing fat oxidation, so frequent alcohol intake can slow progress even when calories and macros are logged accurately.

What’s the easiest mistake to fix immediately?

Moving the food scale to the counter (Mistake 3) and pre-planning the next day the night before (Mistake 2) are both immediate, low-effort fixes that most people can implement the same day.

Do restaurant meals ruin accurate tracking?

Not if estimated and logged rather than skipped. Most tracking apps have restaurant menu databases, and even a rough estimate keeps the week’s pattern visible.

Should beginners track every single day, including weekends?

Ideally yes, though weekend tracking can be less precise than weekday tracking. The key is logging something rather than nothing, even a rough restaurant estimate.

Can I trust my hunger cues instead of tracking at all?

Hunger and fullness cues can shift during perimenopause and menopause, making them a less reliable stand-alone guide than they may have been earlier in life. Tracking, even loosely, provides a more consistent reference point during this transition.

Is a food scale really necessary, or can measuring cups work?

Measuring cups work reasonably well for dry goods but are less accurate for irregularly shaped or dense foods. A scale is more precise and often faster once the habit is established.

What if my app’s database entry doesn’t specify raw or cooked?

Assume raw unless labeled otherwise, since that’s the more common default in most food databases, and verify by checking the calorie count against a known reference for that food.

How long does it take to build an accurate tracking habit?

Most people notice a meaningful accuracy improvement within 1-2 weeks of implementing the fixes for these six mistakes, though building the pre-planning habit specifically tends to take a bit longer to feel automatic.

Does tracking macros work differently for women in perimenopause versus younger women?

The mechanics of tracking are the same, but the context around it changes: shifting hunger cues, changing body composition, and evolving activity levels mean the recalculation habit (Mistake 5) matters more, and more often, in midlife than it typically did a decade earlier.

References

  • Academy of Nutrition and Dietetics patient education materials on accurate portion measurement and food logging.
  • Poslusna, K., et al. (2009). Misreporting of energy and micronutrient intake estimated by food records and 24-hour recalls, control and adjustment methods in practice. British Journal of Nutrition, 101(S2), S73-S85.
  • Champagne, C. M., et al. (2002). Energy intake and energy expenditure: a controlled study comparing dietitians and non-dietitians. Journal of the American Dietetic Association, 102(10), 1428-1432.
  • Livingstone, M. B. E., & Black, A. E. (2003). Markers of the validity of reported energy intake. Journal of Nutrition, 133(3), 895S-920S.
  • Burke, L. E., et al. (2011). Self-monitoring in weight loss: a systematic review of the literature. Journal of the American Dietetic Association, 111(1), 92-102.
  • Ravussin, E., & Bogardus, C. (1989). Relationship of genetics, age, and physical fitness to daily energy expenditure and fuel utilization. American Journal of Clinical Nutrition, 49(5), 968-975.
  • Suter, P. M. (2005). Is alcohol consumption a risk factor for weight gain and obesity? Critical Reviews in Clinical Laboratory Sciences, 42(3), 197-227.
  • North American Menopause Society clinical guidance on appetite regulation and body composition changes during the menopause transition.
  • Mayo Clinic patient education materials on food tracking accuracy and portion control.

Disclaimer: This article is educational and does not constitute medical or individualized nutrition advice. Macro tracking can be a useful tool, but calorie and nutrient needs vary based on body composition, activity level, health conditions, medications, and personal goals. If you have a history of disordered eating, are recovering from an eating disorder, or find detailed food tracking distressing or obsessive, consult a registered dietitian, therapist, or qualified healthcare provider before using the strategies in this article.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.