Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Acupuncture and Myofascial Release for Midlife Women: How the Two Practices Work Together (With a 5-Day Integration Program and Videos)

Acupuncture and myofascial release may seem like very different practices, but both work with fascia. Acupuncture uses needles to create mechanical and neurological input, while myofascial release uses sustained pressure and movement to help restricted tissue move more freely.

This matters in midlife because declining estrogen can affect collagen turnover, hydration, and fascial glide. The result can be more stiffness, restricted movement, and persistent tension through perimenopause and menopause.

Acupuncture can reach deeper restrictions and influence pain signaling, while myofascial release offers direct mechanical input that can also be practiced at home. Used together, they provide two complementary ways to support fascial health.

This guide covers how both practices work, what the research says, when to use each one, how to combine them safely, and a five-day program for integrating self-myofascial release alongside professional acupuncture.

Important: Acupuncture should be performed by a qualified practitioner. Avoid self-myofascial release over acute injuries, open wounds, bruising, infections, major blood vessels, or inflamed areas, and consult your healthcare provider if you have a bleeding disorder, take blood thinners, have deep vein thrombosis, advanced osteoporosis, or another condition that may affect safety.

Why Do Acupuncture and Myofascial Release Belong in the Same Conversation?

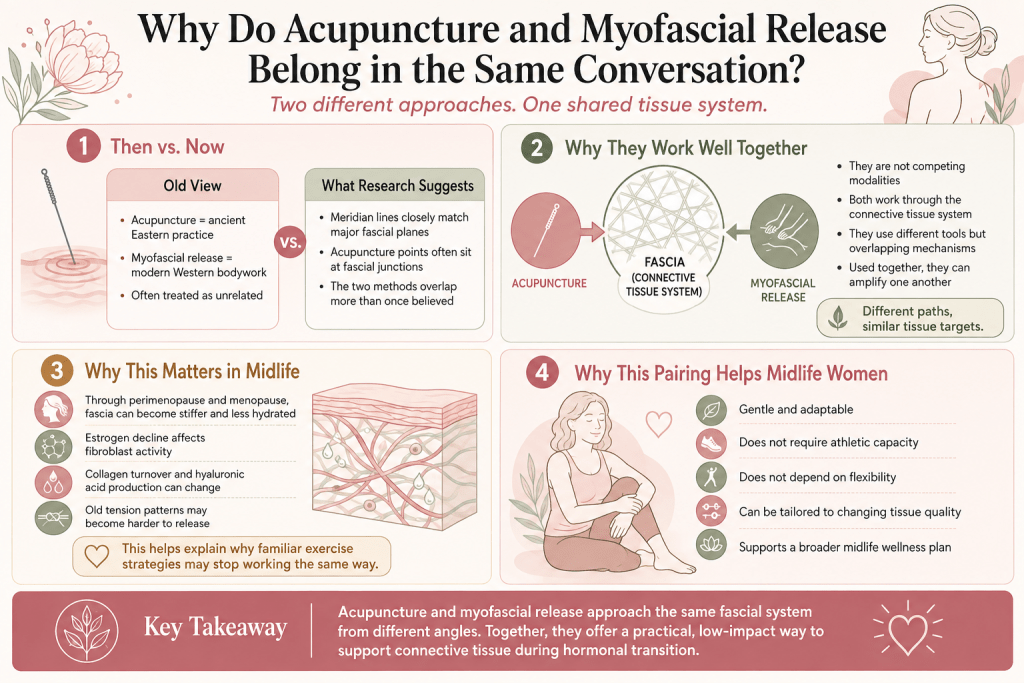
For most of the twentieth century, acupuncture and myofascial release were treated as if they came from entirely separate worlds. Acupuncture was seen as an ancient Eastern practice with mystical energy meridians, and myofascial release was seen as a modern Western bodywork technique with mechanical explanations. Recent anatomical research has shown that the two overlap far more than anyone previously realized. The meridian lines described in classical Chinese medicine correspond closely to major fascial planes described in modern connective tissue anatomy. Acupuncture points cluster along fascial junctions where multiple layers of connective tissue meet.
Acupuncture and myofascial release for midlife fascia.

This convergence matters because it means acupuncture and myofascial release are not competing modalities. They are two approaches to the same tissue system, arrived at from different directions, using different tools, working through overlapping mechanisms. When you use them together thoughtfully, they amplify one another.

For midlife women, this pairing is particularly powerful. Fascia changes measurably through perimenopause and menopause. The connective tissue matrix becomes stiffer, less hydrated, and more prone to holding restriction patterns. Estrogen decline directly affects fibroblast activity, collagen turnover, and hyaluronic acid production. Traditional exercise that used to work often stops working. Old tension patterns become harder to shake. Both acupuncture and myofascial release offer ways to work with fascia that do not require athletic capacity, do not depend on flexibility, and can be adapted to the specific tissue quality changes that come with hormonal transition.

This article walks through the science, the practice, and the safe combination of both. By the end, you will understand what each practice does, how they influence fascia through overlapping and complementary mechanisms, when to choose one over the other, how to combine them in a weekly practice, and how they fit into the broader midlife wellness framework we teach at The House of Rose.

What Is Fascia and Why Do Midlife Changes Matter?

Fascia is the continuous connective tissue web that runs through the entire body. It surrounds every muscle fiber, every muscle group, every organ, and every blood vessel. It is one uninterrupted structure from your feet to your face. Anatomists once dismissed it as packing material. Modern anatomy recognizes fascia as a sensory organ in its own right, with more nerve endings per square centimeter than skin in some regions, and with active roles in force transmission, proprioception, and immune signaling.

Healthy fascia is hydrated, glides smoothly along adjacent layers, and adapts to load. Fibroblasts, the primary cells that build and maintain fascia, produce collagen, elastin, and the hyaluronic acid that makes fascia glide. Fasciacytes, a specialized fibroblast subtype identified relatively recently, produce most of the hyaluronic acid in the loose connective tissue between fascial layers.

In midlife women, estrogen decline directly affects each of these processes. Estrogen receptors on fibroblasts influence collagen synthesis, so falling estrogen means slower collagen turnover. Hyaluronic acid production drops, so fascia becomes drier and stickier. The result is that fascia does not glide the way it used to. Areas that used to feel loose feel dense. Old injuries flare in new places. Ranges of motion that felt effortless start to feel effortful.

You feel this as chronic tightness that stretching does not resolve, restricted range of motion in the shoulders, hips, or thoracic spine, one-sided pain that migrates around the body, and areas that feel dense or ropey when you press on them. These are all signs of fascial restriction, and they respond well to targeted mechanical or neurological input. Myofascial release provides mechanical input. Acupuncture provides both mechanical input (via the needle) and neurological input (via the response the needle triggers).

Understanding how hormonal changes affect fascia helps explain why stiffness, reduced tissue glide, and slower recovery can become more noticeable in midlife. Adding fascia-focused exercises that encourage mobility and lymphatic flow provides another part of that foundation. From there, the focus shifts to how acupuncture and myofascial release specifically interact with fascia in midlife bodies.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Are the Ancient History and Modern Science Behind Both Practices?

Acupuncture is one of the oldest continuously practiced medical systems on the planet. The Yellow Emperor’s Classic of Internal Medicine, one of the foundational Chinese medical texts, describes acupuncture in detail and dates from roughly the third century BCE. The practice traveled from China to Korea and Japan over the following centuries, then to Vietnam, and eventually to Europe through Jesuit missionaries in the seventeenth century. Modern medical acupuncture, which integrates traditional acupuncture with contemporary anatomy and physiology, developed through the twentieth century as Western physicians and physical therapists began adapting techniques for musculoskeletal medicine.

Myofascial release as a distinct named practice is much younger. The osteopathic tradition, founded in the late nineteenth century by Andrew Taylor Still, incorporated soft tissue and fascial work. Modern myofascial release techniques were developed in the 1960s and 1970s, most prominently by John Barnes, who codified an approach that spread through physical therapy education. The John Barnes technique emphasizes sustained gentle pressure held for extended durations to allow fascia to release through a viscoelastic response. Other traditions of myofascial work developed in parallel, including Rolfing, structural integration, active release techniques, and instrument assisted soft tissue mobilization.

The convergence of the two practices happened through anatomy. In 2001, Peter Deadman and colleagues, and in 2004, Helene Langevin at the University of Vermont, began publishing research showing that acupuncture points sit at fascial planes and that inserting a needle at these locations produces a measurable mechanical response in surrounding connective tissue. Langevin’s imaging studies demonstrated that when an acupuncture needle is inserted and rotated, connective tissue winds around the needle like fabric on a spindle. This mechanical winding creates tension in the surrounding fascia that persists after the needle is removed and appears to be a significant part of how acupuncture works locally.

Subsequent research by Langevin and others has demonstrated that acupuncture affects fibroblast activity, connective tissue remodeling, and the sensory nerve endings in fascia. This is not mystical. It is mechanical, biological, and reproducible. The traditional descriptions of acupuncture in terms of energy and meridians can be translated meaningfully into modern fascial anatomy and physiology.

Meanwhile, research on myofascial release has demonstrated similar effects on fibroblast activity, extracellular matrix remodeling, and pain modulation through mechanical stimulation. The two practices converge on the same tissue, influence the same cells, and produce overlapping clinical effects. They differ in how they deliver the input.

How Does Acupuncture Work on Fascia?

Acupuncture involves inserting thin sterile needles into specific points on the body. Traditional acupuncture points map to locations that modern anatomy has since shown to be fascial junctions, where multiple layers of connective tissue meet, where nerve bundles run, and where blood vessels branch. The classical meridian lines correspond closely to fascial planes.

When a needle is inserted at an acupuncture point, several things happen. First, the mechanical insertion creates a small local disruption in the connective tissue. Fibroblasts in the area respond to this mechanical stimulus by changing their behavior. They begin producing signaling molecules that affect surrounding cells and tissues. This response can persist for hours after the needle is removed.

Second, if the practitioner rotates the needle, the fascia around the needle winds up mechanically, creating a small but measurable tension load in the surrounding tissue. Langevin’s imaging studies at the University of Vermont documented this winding effect in detail. The wound fascia does not immediately unwind when the needle is removed. Instead, it slowly releases over time, providing a sustained mechanical signal to the tissue.

Third, the needle activates local sensory nerve endings. These nerve endings communicate with the central nervous system through pathways that release endogenous opioids, modulate pain signaling, and influence the autonomic nervous system. This is one of the well-documented pain-relieving mechanisms of acupuncture and has been demonstrated through functional MRI studies of brain activity during and after treatment.

Fourth, the local circulation changes. Blood flow to the treated area increases substantially and remains elevated for hours after treatment. This increased perfusion delivers oxygen and nutrients and clears metabolic waste that may have accumulated in restricted tissue.

Fifth, acupuncture appears to influence systemic inflammation. Multiple studies have documented changes in inflammatory markers including reduced levels of pro-inflammatory cytokines after acupuncture treatment. This effect is particularly notable for chronic pain conditions where low-grade inflammation contributes to symptom persistence.

For midlife women specifically, acupuncture has additional documented effects on hormone-related symptoms. The strongest evidence base is for hot flashes, night sweats, and sleep disruption during perimenopause and menopause. Multiple randomized controlled trials have shown that acupuncture produces clinically meaningful reductions in vasomotor symptoms, often comparable in effect size to certain pharmaceutical interventions and without the side effects.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Does Myofascial Release Work on Fascia?

Myofascial release covers a range of techniques that use sustained mechanical pressure, movement, or shear to influence fascial tissue. The techniques vary in tool, pressure, duration, and philosophy. What they share is direct mechanical input to fascia through the skin.

Common myofascial release approaches include:

  • John Barnes myofascial release: Sustained gentle pressure held for 90 seconds to five minutes, working with the tissue’s viscoelastic response.
  • Trigger point therapy: Focused pressure on specific tender points to release referred pain patterns.
  • Foam rolling: Self-applied pressure using a foam cylinder to release large muscle groups and general fascia maintenance.
  • Ball release: Focal self-applied pressure using a lacrosse, tennis, or specialty ball for small or hard-to-reach areas.
  • Instrument assisted soft tissue mobilization: Using specialized metal or plastic tools to apply mechanical shear along the skin, similar to traditional gua sha.
  • Active release techniques: Applied by trained practitioners, combines pressure with active movement of the client.
  • Rolfing and structural integration: Deep systematic fascial work delivered over multiple sessions.

Each of these produces mechanical input to fascia. The specific effects vary by technique but consistently include:

  • Viscoelastic response: Fascia has both elastic and viscous properties. Sustained low-load pressure produces a slow yield response, where the tissue lengthens over time. This is why John Barnes technique holds pressure for extended durations. The tissue does not release immediately. It releases over time as the viscoelastic response develops.
  • Fibroblast mechanotransduction: Sustained mechanical input to fascia influences fibroblast activity. Fibroblasts sense mechanical load and respond by producing or degrading extracellular matrix components. Regular mechanical input keeps fibroblasts producing the collagen and hyaluronic acid needed for healthy fascia.
  • Interstitial fluid movement: Mechanical pressure moves fluid through the loose connective tissue between fascial layers. This flushes stagnant tissue and improves the glide between layers.
  • Sensory nerve activation: Mechanical pressure activates the mechanoreceptors, proprioceptors, and nociceptors embedded in fascia. This activation communicates with the central nervous system and influences pain processing, muscle tone, and autonomic function.
  • Muscle tone modulation: Through connections between fascia and the neuromuscular system, myofascial release affects the resting tone of muscles. Chronically overactive muscles often reduce their baseline tone after myofascial work.

Self-myofascial release using foam rollers, balls, and simple tools is the most accessible form of this work. It is safe, effective for maintenance and mild-to-moderate restriction, and integrates well into daily practice. Professional myofascial release adds skilled assessment, precise application, and access to techniques that self-treatment cannot easily reproduce.

How Do Acupuncture and Myofascial Release Compare to Other Bodywork Methods?

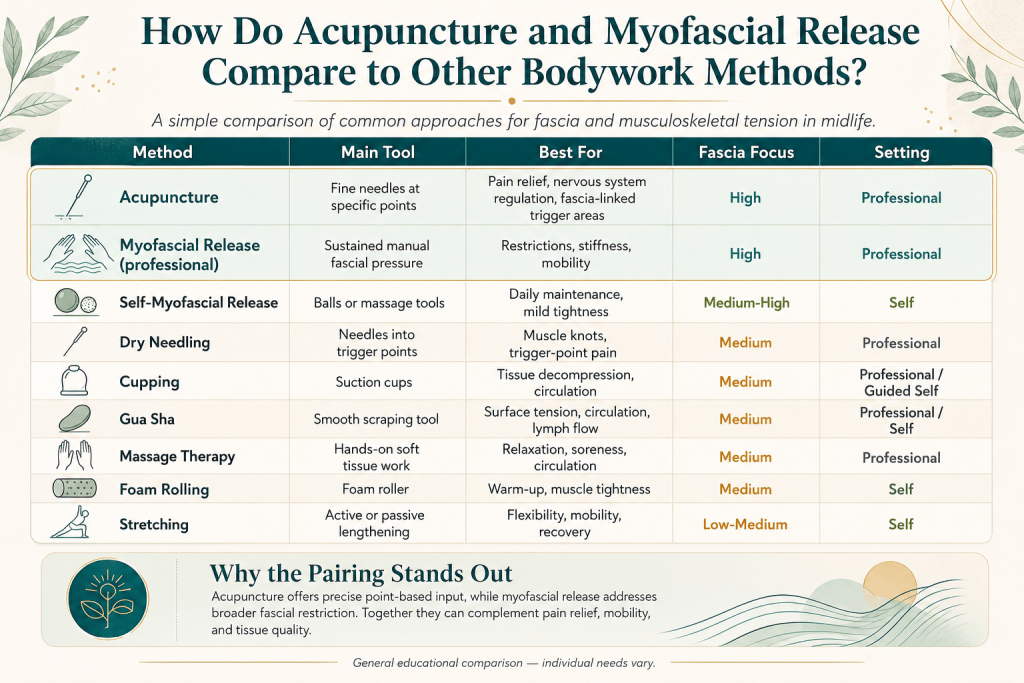
The table below compares acupuncture and myofascial release to the other common approaches for working with fascia and musculoskeletal tension in midlife.
Acupuncture and myofascial release bodywork comparison infographic

Method

Mechanism

Best for

Limitations

Home practice friendly

Acupuncture

Needle insertion at fascial junctions; mechanical winding, nerve activation, increased blood flow, systemic effects

Chronic pain, hormone-related symptoms, deep fascial restriction, systemic inflammation

Requires licensed practitioner; needle phobia; cost

No

Myofascial Release (professional)

Sustained mechanical pressure with skilled application

Complex restrictions, injury recovery, structural patterns needing skilled assessment

Requires appointments; cost; limited insurance coverage

No

Self-Myofascial Release

Sustained mechanical pressure via foam roller, ball, or tools

Maintenance, general fascia care, mild-to-moderate restriction

Cannot substitute for skilled assessment of complex patterns

Yes

Dry Needling

Needle insertion at trigger points, typically by physical therapist

Trigger points, muscle knots, sports injury

Not traditional acupuncture; requires trained practitioner

No

Cupping

Negative pressure decompresses fascia and increases blood flow

Chronically compressed tissue, deep restriction

Leaves marks; requires practice

Yes

Gua Sha

Mechanical shear along skin unsticks fascial layers

Adhered fascial layers, superficial fascia

Leaves temporary marks

Yes

Massage Therapy

Skilled hands work all tissue layers

Comprehensive fascial work

Requires appointments; cost

No

Foam Rolling

Sustained compression flattens and rehydrates fascia

Large muscle groups, warm-up

Cannot reach small or deep areas

Yes

Yin Yoga

Sustained low-load stretch for deep connective tissue

Chronic tension patterns, slow fascial hydration

Requires time and patience

Yes

Stretching

Passive lengthening of muscle-fascia unit

Range of motion improvements

Does not directly address stuck fascial layers

Yes

Acupuncture and myofascial release occupy complementary positions in this list. Acupuncture is unmatched for reaching deep fascial layers, addressing systemic effects, and modulating pain through central nervous system pathways. Self-myofascial release is unmatched for daily maintenance, accessibility, and cost-effectiveness. Combining professional acupuncture with a home self-myofascial release practice gives you both the depth of skilled needle work and the consistency of daily self-care.

Worked example. A woman in her late forties has chronic low back tension that started during her second pregnancy and has been managed with sporadic massage since. As perimenopause progresses, the pattern worsens. She books a series of six acupuncture sessions with a licensed acupuncturist, scheduled weekly. Between sessions, she performs a daily 10-minute self-myofascial release routine using a foam roller on her low back and glutes, and a ball on her piriformis and hip flexors.

Over the six-week series, the professional acupuncture addresses the deep pattern that has been resistant to prior treatment. The daily self-work maintains what each session opens up and prevents the tissue from returning to its baseline restriction between visits. This combination produces sustained results in a way that either practice alone would not.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Does the Research Say?

The research bases for acupuncture and myofascial release have both grown substantially. Both have limitations in study quality and blinding, but the volume of evidence for both is now considerable.

  • Acupuncture and chronic pain: A 2018 individual patient data meta-analysis by Vickers and colleagues, published in the Journal of Pain, pooled data from more than 20,000 patients across 39 trials. The analysis found that acupuncture produced clinically meaningful reductions in chronic pain (musculoskeletal, headache, and osteoarthritis) compared to both sham acupuncture and no acupuncture controls. Effect sizes persisted at one-year follow-up in a subset of studies, suggesting sustained benefit.
  • Acupuncture and menopausal symptoms: Multiple systematic reviews have examined acupuncture for vasomotor symptoms. A 2019 review in BMJ Open pooled data from 15 randomized controlled trials and found that acupuncture significantly reduced the frequency and severity of hot flashes compared to controls. Effects generally persisted for at least three months after treatment ended. A separate line of research has examined acupuncture for menopausal sleep disturbance, mood changes, and sexual function, with generally positive findings though smaller evidence bases.
  • Acupuncture and connective tissue: Langevin and colleagues at the University of Vermont have published extensively on the connective tissue effects of acupuncture. Their imaging studies documented mechanical winding of fascia around needles, effects on fibroblast morphology, and downstream changes in extracellular matrix components. This body of research provides a mechanistic foundation for what practitioners have observed clinically.
  • Myofascial release and chronic pain: A 2015 systematic review in the Journal of Bodywork and Movement Therapies examined myofascial release for various pain conditions. Results were positive overall, with the strongest evidence for chronic low back pain and neck pain. A 2020 meta-analysis focused specifically on plantar heel pain found that myofascial release reduced pain and improved function compared to control interventions.
  • Self-myofascial release with foam rollers: A large body of research has examined foam rolling. A 2019 systematic review and meta-analysis in Frontiers in Physiology found that foam rolling before exercise improved short-term flexibility without impairing performance. Foam rolling after exercise reduced perceived muscle soreness. Both effects are consistent with mechanical influence on fascia and neuromuscular function.
  • Combined bodywork approaches: Fewer studies have examined combined protocols directly, but the physiological rationale for combining approaches is strong. Both acupuncture and myofascial release influence overlapping tissue and physiological systems. The mechanisms are complementary rather than redundant.
  • Safety: Both practices have excellent safety profiles when performed appropriately. Serious adverse events from acupuncture are rare and typically involve non-sterile technique or contraindications that were missed. Adverse events from myofascial release are typically minor (bruising, temporary soreness) and preventable with reasonable technique.
  • Limitations: Both fields struggle with blinding, standardization of technique across studies, and control group selection. Sham acupuncture is difficult to design because inserting a needle at any location produces some physiological effect. Myofascial release studies vary widely in technique used, making comparison across studies difficult. Despite these limitations, the consistent direction of findings across multiple research groups and methodologies is meaningful.

When Should You Choose Acupuncture, Myofascial Release, or Both?

Both modalities have situations where they excel.

Choose acupuncture when you have:

  • Chronic pain that has not responded to other approaches
  • Perimenopause or menopause symptoms including hot flashes, night sweats, sleep disruption
  • Deep fascial restriction that surface work has not reached
  • Systemic patterns like widespread muscle tension or fibromyalgia
  • Interest in the systemic and central nervous system effects
  • Access to a licensed acupuncturist and the financial capacity for a series of sessions
  • Patience for a course of treatment (typically 6 to 12 sessions to assess benefit)

Choose myofascial release when you have:

  • Specific mechanical restrictions you can identify and target
  • Areas that respond to sustained pressure
  • Interest in a daily self-care practice
  • Budget constraints that make professional treatment difficult
  • The desire to build fascia care into your daily routine
  • Recovery needs after training or activity

Use both when you want to:

  • Address chronic patterns from multiple angles
  • Combine the depth of professional needle work with daily self-maintenance
  • Build a sustainable long-term fascia practice
  • Support recovery from significant injury
  • Manage complex conditions with multiple contributing factors
  • Get the most complete fascial care your resources allow

The typical protocol when combining is to schedule acupuncture sessions weekly or biweekly for a defined course (often six to twelve sessions), while maintaining a daily or near-daily self-myofascial release practice. The acupuncture addresses deep patterns. The self-work maintains progress and prevents regression between sessions.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Can Acupuncture Support Perimenopause and Menopause?

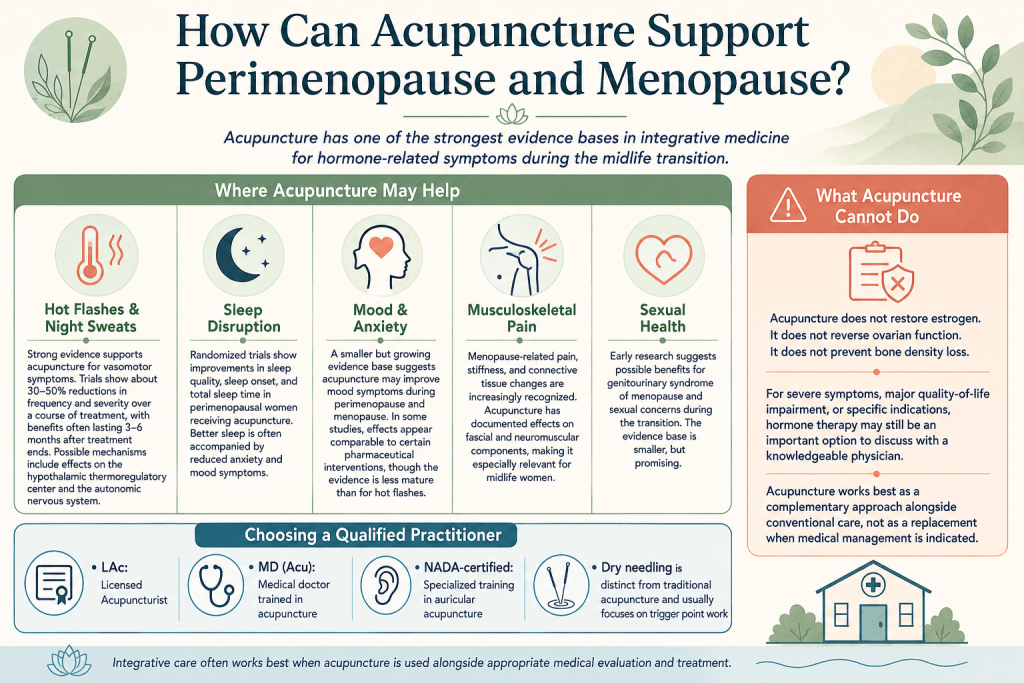
Acupuncture has one of the strongest evidence bases in integrative medicine for hormone-related symptoms during the midlife transition. This deserves specific attention.
Acupuncture support for menopause symptoms.
  • Hot flashes and night sweats: The evidence for acupuncture in vasomotor symptoms is now substantial. Multiple randomized controlled trials have documented reductions in the frequency and severity of hot flashes ranging from 30 to 50 percent over a course of treatment, with effects often persisting three to six months after the treatment series ends. The mechanism appears to involve modulation of the hypothalamic thermoregulatory center and downstream effects on the autonomic nervous system.
  • Sleep disruption: Randomized trials have shown improvements in sleep quality, sleep onset, and total sleep time in perimenopausal women receiving acupuncture. Effects are often accompanied by reductions in anxiety and mood symptoms that also affect sleep.
  • Mood and anxiety: A smaller but growing body of research documents effects on mood symptoms during perimenopause and menopause. Effects appear comparable in some studies to certain pharmaceutical interventions, though the evidence base is less mature than for vasomotor symptoms.
  • Musculoskeletal pain: The “musculoskeletal syndrome of menopause,” described in recent literature, includes widespread pain, stiffness, and connective tissue changes. Acupuncture has documented effects on the fascial and neuromuscular components of this syndrome. This is where the acupuncture-fascia connection becomes particularly relevant to midlife women.
  • Sexual health: Some research examines acupuncture for genitourinary syndrome of menopause and sexual concerns during the transition. The evidence base is smaller but promising.
  • What acupuncture cannot do: Acupuncture does not restore estrogen. It does not reverse ovarian function. It does not prevent bone density loss. For women with severe symptoms, significant menopausal effects on quality of life, or specific indications, hormone therapy remains an important option that should be discussed with a knowledgeable physician. Acupuncture is a complementary approach that works well alongside conventional care, not a substitute for medical management when medical management is indicated.

Look for practitioners with the LAc credential (Licensed Acupuncturist) or the equivalent depending on your state. Some medical doctors also practice medical acupuncture and hold the MD (Acu) credential. NADA-certified practitioners have specialized training in auricular acupuncture. In some states, chiropractors and physical therapists provide dry needling, which is technically distinct from traditional acupuncture and typically focused on trigger point work rather than the full scope of acupuncture practice.

What Tools and Setup Do You Need for Home Myofascial Release Practice?

Self-myofascial release requires minimal equipment. The following tools cover almost every need.

  • Foam roller: The primary tool for large muscle groups. Options include:
  • Standard density foam roller: 6-inch diameter, 36 inches long. Good starting point for most people. Under $30.
  • High density foam roller: More aggressive pressure. For those who have progressed past standard density. Under $40.
  • Textured foam roller: Ridges or knobs for more focal pressure. Useful once you have progressed past smooth rollers. Around $40.
  • Vibrating foam roller: Adds mechanical vibration to the pressure. Some evidence suggests it may enhance effects. $80 to $200.

Balls for Focal Release

  • Lacrosse ball: Firm rubber ball perfect for focal pressure on glutes, piriformis, feet. Around $5.
  • Tennis ball: Softer alternative for beginners. A few dollars.
  • Peanut-shaped double ball: For work along the spine without direct pressure on vertebrae. Around $15.
  • Softer therapy balls: Various brands offer graduated firmness. $10 to $30.

Additional Tools

  • Trigger point cane or hook: For hard-to-reach areas like upper back. $20 to $40.
  • Percussion massager: Handheld device delivering rapid mechanical percussion. Range from $80 to $600.
  • Yoga mat: For floor work. Around $30.

Environment

  • Warm room: Cold muscles do not respond as well.
  • Enough floor space to lie down and roll.
  • Time: Rushing myofascial release reduces its effectiveness.
  • No distractions: Attention to sensation matters.

Contraindications for Self-Myofascial Release

Do not apply myofascial release directly over:

  • Acute injuries, open wounds, or active infections
  • Areas of bruising or recent trauma
  • Directly over the spine or joints (work adjacent tissue)
  • Major blood vessels (front of neck, groin, inside of elbow)
  • Areas of active inflammation from other causes

Do not use self-myofascial release if you:

  • Have bleeding disorders or are on blood thinners without physician clearance
  • Have advanced osteoporosis (may need modifications for pressure)
  • Have deep vein thrombosis
  • Have any acute infection or fever
  • Are in a fragile state where excessive input could aggravate

Consult a physical therapist or licensed practitioner if you have complex conditions or are unsure whether these tools are appropriate for you.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Is the 5-Day Integration Program?

This program builds a self-myofascial release practice alongside professional acupuncture (either concurrent with a treatment series or in preparation for one). The self-work supports and extends what acupuncture achieves.

Day

Focus

Practice

Duration

Day 1

Foundation, back and hips

Foam roll upper back, mid back, glutes; ball release piriformis

12 minutes

Day 2

Add legs

Repeat Day 1, add foam roll IT band, quadriceps, calves

18 minutes

Day 3

Add feet and hands

Repeat Day 2, add ball release plantar fascia and forearms

22 minutes

Day 4

Full body integration

Full sequence from Day 3, work more slowly with attention to sensation

25 minutes

Day 5

Add breath and stillness

Full sequence with sustained holds and diaphragmatic breathing during focal releases

30 minutes

Day 1 Detail: Foundation, Back and Hips

Lie on the foam roller with it across your upper back at the level of your shoulder blades. Support your head with your hands. Slowly roll from shoulder blade level to just below the shoulder blades. Pause on any tender area for 20 to 30 seconds. Repeat for 3 minutes. Then position the roller under your glutes and roll each side, using slow deliberate movement, for 2 minutes each side. Finally, place a lacrosse ball under your piriformis (the deep hip external rotator) and use your body weight to apply pressure. Hold for 30 to 60 seconds per side. Breathe through any tenderness.

Day 2 Detail: Add Legs

Repeat the Day 1 back and hip work. Then add the following: foam roll the outside of each thigh (IT band region) for 90 seconds each side, working slowly. Foam roll the quadriceps for 90 seconds each side. Foam roll the calves for 90 seconds each side. The IT band region often produces significant sensation the first few times. Do not force it. Reduce pressure until it is intense but manageable.

Day 3 Detail: Add Feet and Hands

Repeat Day 2 sequence. Then add ball work for the feet: stand with a lacrosse or tennis ball under one foot, using body weight to roll the ball from heel to ball of foot. Two minutes each side. Then use the ball on your forearms while seated: place the ball between your forearm and a firm surface (table edge), and apply pressure while flexing and extending the wrist. One minute per forearm. Extend if desk work leaves you tight in the forearms.

Day 4 Detail: Full Body Integration

Complete the full sequence from Day 3. Work more slowly. Instead of moving continuously along an area, pause on specific spots for 60 to 90 seconds. Notice how the tissue responds. Notice areas that are asymmetric between sides. Track this over time as a diagnostic tool.

Day 5 Detail: Add Breath and Stillness

Complete the Day 4 sequence with two additions. First, on each focal release (piriformis, IT band trigger point, forearm), hold the pressure while performing five slow diaphragmatic breaths. Inhale through the nose for a count of 4, exhale through the nose for a count of 6. Feel the tissue soften with each exhale. Second, at the end of the full sequence, rest on your mat for 5 minutes in a comfortable position while continuing slow breathing. This integrates the mechanical work with parasympathetic nervous system activation.

After completing the 5-day introduction, most women benefit from 15 to 25 minutes of self-myofascial release three to four times per week. Rotate which areas you emphasize based on need. If you are also receiving acupuncture, coordinate the self-work with your sessions. Schedule intensive self-work on non-acupuncture days and lighter maintenance on acupuncture days.

How Can You Do Self-Myofascial Release Safely?

Technique matters more than time or intensity.

Self-myofascial release safety tips infographic.
  • Warm the tissue first: A warm shower, gentle movement, or a few minutes of walking prepares fascia to respond. Cold tissue resists mechanical input and can bruise more easily.
  • Move slowly: Slow is where the release happens. Fast rolling is aerobic exercise for your legs, not myofascial release. Aim for movement so slow that a bystander might wonder if you are actually moving.
  • Breathe: Hold your breath and the tissue guards. Breathe deeply and the tissue softens. Every session, remind yourself to breathe.
  • Pause on tender spots: When you find a spot that produces significant sensation, stop. Hold pressure for 30 to 90 seconds. The tissue often softens dramatically during this hold. If it does not soften after 90 seconds, move on and return in a future session.
  • Do not force it: If a spot produces sharp pain, cutting sensation, or radiating pain, reduce pressure or skip that area. Myofascial release should feel like productive intensity, not injury.
  • Work adjacent tissue when direct pressure is problematic: For sensitive areas, work the tissue around and beyond the sensitive area first. This often reduces the sensitivity of the target area indirectly.
  • Hydrate before and after: Fascia is largely water. Working on well-hydrated tissue produces better results than working on dehydrated tissue.
  • Avoid the spine directly: Do not roll or press directly on your spine. Work the muscles adjacent to the spine (paraspinals) instead.
  • Follow with movement: After myofascial release, do a few minutes of gentle range of motion or light activity. This helps integrate the changes.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How Should You Prepare for an Acupuncture Session?

Preparation improves the experience and the results.

Before the Session

  • Eat a light meal 1 to 2 hours before: Do not arrive on an empty stomach or immediately after a large meal.
  • Wear loose comfortable clothing that provides access to arms, legs, and back.
  • Avoid alcohol for at least 24 hours before.
  • Bring a list of medications and supplements.
  • Bring notes on your specific concerns, including how long you have had them and what has helped or not helped.
  • Arrive 10 to 15 minutes early: Rushing sets the wrong autonomic tone.

During the Session

  • Communicate openly: Tell the practitioner what you are feeling. If a needle placement is uncomfortable, say so.
  • Relax as much as you can: Deep breathing helps.
  • Some sensations are normal: dull ache, heaviness, warmth, tingling: Sharp pain is not normal. Report it.
  • Rest on the table for the duration the practitioner specifies: Do not remove needles yourself.

After the Session

  • Move slowly for the first 30 minutes: Some people feel briefly light-headed or emotionally open.
  • Hydrate
  • Rest if possible
  • Avoid alcohol and intense exercise for the rest of the day.
  • Notice how you feel over the next 24 to 72 hours: Effects often continue to unfold after the session.

Between Sessions

  • Track symptoms: Note improvements, regressions, or shifts in the pattern.
  • Maintain your self-myofascial release practice if you have one.
  • Follow any lifestyle guidance the practitioner provided.
  • Attend scheduled follow-up sessions: Acupuncture typically produces the best results with a series (often six to twelve sessions).

What Are Common Mistakes and How Can You Avoid Them?

  • Treating acupuncture as a one-and-done treatment: Acupuncture typically requires a series of sessions to produce meaningful benefit for chronic conditions. Judging acupuncture by a single session is like judging strength training by a single workout. Commit to a course of treatment before deciding whether it works for you.
  • Rolling fast on the foam roller: Fast rolling does not work. It reduces the technique to something between a warm-up and a cardio session. Slow, deliberate movement with attention to sensation is what produces fascial change.
  • Only working the sore spots: Restrictions often refer sensation elsewhere. The spot that hurts may not be the spot that needs work. Work broadly across major fascial regions rather than only on the specific place that feels tight.
  • Skipping self-work between acupuncture sessions: The tissue changes acupuncture produces can regress between sessions if the tissue returns to its baseline patterns. Daily or near-daily self-myofascial release maintains progress and often accelerates cumulative benefit.
  • Comparing acupuncture and dry needling as if they were the same: Dry needling and acupuncture use similar tools but come from different traditions and typically address different problems. Dry needling is focused on trigger point release for muscular pain, usually performed by physical therapists with specialized training. Acupuncture involves a broader diagnostic and treatment approach based on traditional Chinese medicine and modern acupuncture research. Both are valid. They are not interchangeable.
  • Assuming needle discomfort means it is not working: Sensation during acupuncture is often part of the response, not a sign of poor technique. The dull ache, heaviness, or warmth that some points produce is called “de qi” in traditional practice and is thought to indicate an effective response. Sharp pain is different and should be communicated. Learn to distinguish sensation from pain.
  • Working through injuries with self-myofascial release: Fresh injuries need different care than chronic patterns. Do not roll or press directly on recent sprains, strains, or bruising. Wait until the acute phase resolves, then work adjacent tissue before returning to the injury site.
  • Doing it all yourself when you would benefit from professional guidance: Self-myofascial release is powerful for maintenance. It is not a substitute for skilled assessment of complex patterns. If a restriction has not responded to consistent self-work over four to eight weeks, work with a professional.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Should You Expect From Sensations, Marks, and Timelines?

  • During acupuncture: Initial needle insertion is often barely felt. Once needles are in place, sensations include mild ache, heaviness, warmth, tingling, or a spreading feeling. These sensations are normal parts of the response. Sharp pain is not.
  • During self-myofascial release: You feel pressure. Some areas feel smooth. Others feel dense, ropey, or tender. Tender areas often become less tender as you hold pressure and breathe. This is the release.
  • Immediately after acupuncture: Deep relaxation is common. Some people feel briefly tired or emotionally open. Sensations from the treatment may continue for hours.
  • Immediately after myofascial release: Increased warmth and looseness in the treated area. Improved range of motion. Sometimes brief lightheadedness, particularly after long sessions.
  • First 24 to 72 hours: Effects of acupuncture often continue unfolding for two to three days. Effects of myofascial release typically peak in the first day and gradually return partially over subsequent days. Both are normal.
  • First few weeks: For chronic patterns, both practices produce cumulative benefit over multiple sessions or weeks of consistent practice. Individual sessions may feel modestly different, but the trend line over weeks is what matters.
  • Longer term: Structural changes take months of consistent practice. Chronic pain patterns often reduce substantially over a six-to-twelve week course of combined work. This is normal timing for tissue-level change.
  • When to be concerned: Increased pain that persists beyond 48 hours, new symptoms that appear after treatment, bruising that seems excessive for the pressure applied, or any signs of infection at needle sites. These are unusual and warrant contacting your practitioner.

When Should You See a Licensed Practitioner?

Self-care has limits. Professional guidance matters when the problem exceeds those limits.

See a Licensed Acupuncturist When You Have

  • Chronic pain that has not responded to self-care and conventional treatment
  • Significant perimenopause or menopause symptoms
  • Complex conditions requiring skilled assessment
  • Interest in a complete course of treatment
  • Access and financial capacity for regular sessions

See a Physical Therapist or Myofascial Release Specialist When You Have

  • Post-injury restrictions requiring skilled hands-on work
  • Complex scar tissue or adhesion patterns
  • Rehabilitation from surgery
  • Conditions where self-work has not produced adequate progress
  • A specific movement dysfunction requiring assessment

What To Look For in an Acupuncturist

Licensed Acupuncturist (LAc) credential or equivalent for your state. Formal training from an accredited school (typically 3 to 4 years of graduate education for LAcs). Clean office and appropriate sterile technique. Willingness to discuss your specific concerns. Communication with your other healthcare providers. Reasonable treatment plan and clear pricing.

What To Look For in a Myofascial Release Specialist

Licensed physical therapist (DPT), certified massage therapist (LMT), or equivalent professional credential. Specific training in myofascial release (John Barnes certification is a common credential). Experience with midlife women’s tissue quality if that is relevant to you. Willingness to teach you techniques you can use between sessions.

Cost Expectations

Acupuncture sessions typically range from $75 to $200 in the United States. Some insurance plans cover acupuncture for specific diagnoses (usually chronic pain). Physical therapy is generally covered by insurance with appropriate diagnosis. Standalone myofascial release from a licensed massage therapist typically costs $80 to $180 per session.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

Does acupuncture actually release fascia?

Yes, based on modern research. Helene Langevin’s imaging studies at the University of Vermont demonstrated that acupuncture needles mechanically wind fascia around themselves when rotated, producing sustained tension in the surrounding tissue. Subsequent research has shown effects on fibroblasts, extracellular matrix components, and connective tissue remodeling. This mechanical effect on fascia is one of the well-documented mechanisms of acupuncture, alongside its effects on nerves, blood flow, and systemic inflammation.

Is dry needling the same as acupuncture?

No. Dry needling uses similar tools (thin filiform needles) but comes from a different tradition and is typically focused on trigger point release for muscular pain. It is usually performed by physical therapists with specialized training. Acupuncture involves a broader diagnostic and treatment approach based on both traditional Chinese medicine and modern acupuncture research, performed by licensed acupuncturists. Both can be useful. They are distinct practices with different scopes.

How many acupuncture sessions do I need?

For chronic conditions, a typical initial course is six to twelve sessions, often scheduled weekly or biweekly. For acute conditions, fewer sessions may be needed. Maintenance schedules vary from monthly to quarterly depending on the condition and individual response. Discuss expectations with your practitioner.

Can I do acupuncture and myofascial release on the same day?

Yes, but sequence matters. Gentle myofascial release before acupuncture can prepare tissue to respond well. Aggressive myofascial release immediately after acupuncture may reduce some of the mechanical effects the needles produced. If you want to combine them same-day, do lighter self-work before the session and save any deeper self-work for the following day.

Does acupuncture help hot flashes?

The evidence base is now substantial. Multiple randomized controlled trials show reductions in hot flash frequency and severity, often persisting three to six months after a treatment series ends. Effects vary between individuals, but the overall pattern of evidence supports acupuncture as a legitimate option for perimenopausal and menopausal vasomotor symptoms.

Can I use a percussion massager instead of a foam roller?

Percussion massagers deliver rapid mechanical percussion that produces some effects similar to foam rolling. Research on percussion devices is less extensive than research on foam rolling, but early studies suggest they can be effective for warm-up, recovery, and some myofascial applications. They do not fully replace sustained pressure techniques for deeper fascial work.

Is acupuncture safe during perimenopause?

Yes, when performed by a licensed practitioner. Acupuncture is one of the more thoroughly studied complementary therapies for perimenopausal symptoms, and the safety profile is excellent. Discuss any medications you are taking with your practitioner, particularly anticoagulants.

How do I know if a self-myofascial release technique is right for me?

Start with the most conservative version of any technique. Use less pressure, less time, and gentler tools than you think you need. Notice how your body responds over the following 24 to 48 hours. Progress gradually as your tissue tolerates more input. If pain increases or persists, back off and consult a professional.

Can acupuncture help with sleep?

Multiple studies have documented improvements in sleep quality with acupuncture, particularly in perimenopausal women. Effects appear related to reduced vasomotor symptoms, reduced anxiety, and direct autonomic nervous system modulation. If sleep is a specific concern, mention it to your practitioner so they can adjust the treatment approach.

What about acupuncture for weight and metabolism?

Some research examines acupuncture for weight-related concerns, particularly in perimenopausal women where hormonal changes affect metabolism. The evidence is smaller and less consistent than for pain or vasomotor symptoms. Acupuncture is not a substitute for the fundamentals of protein intake, resistance training, and sleep. It may support these efforts in some individuals as one component of a broader plan.

How do I find a good acupuncturist?

Look for licensed practitioners with formal training from accredited schools. Check credentials with your state’s licensing board. Ask about experience with your specific concerns. Read reviews. Have an initial consultation before committing to a series. A good acupuncturist will discuss your history in depth, explain their approach, and set realistic expectations.

Does acupuncture hurt?

The needles used in acupuncture are much thinner than injection needles. Initial insertion is often barely felt. Once needles are in place, sensations include dull ache, heaviness, warmth, or tingling. These sensations are typically not painful, though they can be unusual. Sharp pain is not normal and should be reported to the practitioner immediately.

Can I do self-myofascial release every day?

Yes, most people benefit from daily self-myofascial release once they have adjusted to it. Session length should be modest (10 to 25 minutes) if you are working daily. Longer sessions (30 to 45 minutes) with rest days between them work well for those who prefer that pattern. Rotate which areas you emphasize.

Is myofascial release safe during pregnancy?

Gentle self-myofascial release is generally safe during pregnancy for areas away from the abdomen and low back. Consult your obstetric provider for individual guidance, particularly for the second and third trimesters. Professional myofascial release specifically trained in prenatal work is a safer option than self-work during pregnancy.

Can I do these instead of exercise?

No. Acupuncture and myofascial release support movement and recovery. They do not replace the mechanical loading, cardiovascular work, and neuromuscular training that regular exercise provides. Use them as complements to your movement practice, not as substitutes.

References

  • Vickers, A. J., Vertosick, E. A., Lewith, G., MacPherson, H., Foster, N. E., Sherman, K. J., Irnich, D., Witt, C. M., Linde, K., & Acupuncture Trialists’ Collaboration. (2018). Acupuncture for chronic pain: Update of an individual patient data meta-analysis. Journal of Pain, 19(5), 455-474.
  • Langevin, H. M., & Yandow, J. A. (2002). Relationship of acupuncture points and meridians to connective tissue planes. Anatomical Record, 269(6), 257-265.
  • Langevin, H. M., Churchill, D. L., Wu, J., Badger, G. J., Yandow, J. A., Fox, J. R., & Krag, M. H. (2002). Evidence of connective tissue involvement in acupuncture. FASEB Journal, 16(8), 872-874.
  • Langevin, H. M., Bouffard, N. A., Badger, G. J., Iatridis, J. C., & Howe, A. K. (2005). Dynamic fibroblast cytoskeletal response to subcutaneous tissue stretch ex vivo and in vivo. American Journal of Physiology: Cell Physiology, 288(3), C747-C756.
  • Ee, C., French, S. D., Xue, C. C., Pirotta, M., & Teede, H. (2017). Acupuncture for menopausal hot flashes: Clinical evidence update and its relevance to decision making. Menopause, 24(8), 980-987.
  • Lund, K. S., Siersma, V., Brodersen, J., & Waldorff, F. B. (2019). Efficacy of a standardised acupuncture approach for women with bothersome menopausal symptoms: A pragmatic randomised study in primary care. BMJ Open, 9(1), e023637.
  • Avis, N. E., Coeytaux, R. R., Isom, S., Prevette, K., & Morgan, T. (2016). Acupuncture in menopause (AIM) study: A pragmatic, randomized controlled trial. Menopause, 23(6), 626-637.
  • Ajimsha, M. S., Al-Mudahka, N. R., & Al-Madzhar, J. A. (2015). Effectiveness of myofascial release: Systematic review of randomized controlled trials. Journal of Bodywork and Movement Therapies, 19(1), 102-112.
  • Wilke, J., Müller, A. L., Giesche, F., Power, G., Ahmedi, H., & Behm, D. G. (2020). Acute effects of foam rolling on range of motion in healthy adults: A systematic review with multilevel meta-analysis. Sports Medicine, 50(2), 387-402.
  • Cheatham, S. W., Kolber, M. J., Cain, M., & Lee, M. (2015). The effects of self-myofascial release using a foam roll or roller massager on joint range of motion, muscle recovery, and performance: A systematic review. International Journal of Sports Physical Therapy, 10(6), 827-838.
  • Wiech, K., Ploner, M., & Tracey, I. (2008). Neurocognitive aspects of pain perception. Trends in Cognitive Sciences, 12(8), 306-313.
  • MacPherson, H., Vertosick, E. A., Foster, N. E., Lewith, G., Linde, K., Sherman, K. J., Witt, C. M., & Vickers, A. J. (2017). The persistence of the effects of acupuncture after a course of treatment: A meta-analysis of patients with chronic pain. Pain, 158(5), 784-793.
  • Stecco, C., Stern, R., Porzionato, A., Macchi, V., Masiero, S., Stecco, A., & De Caro, R. (2011). Hyaluronan within fascia in the etiology of myofascial pain. Surgical and Radiologic Anatomy, 33(10), 891-896.
  • Schleip, R., Gabbiani, G., Wilke, J., Naylor, I., Hinz, B., Zorn, A., Jäger, H., Breul, R., Schreiner, S., & Klingler, W. (2019). Fascia is able to actively contract and may thereby influence musculoskeletal dynamics. Frontiers in Physiology, 10, 336.
  • Wright, K. E., Skinner, S., & Zhu, S. (2023). The musculoskeletal syndrome of menopause. Climacteric, 26(4), 366-371.
  • Wilke, J., Schleip, R., Yucesoy, C. A., & Banzer, W. (2018). Not merely a protective packing organ? A review of fascia and its force transmission capacity. Journal of Applied Physiology, 124(1), 234-244.
  • Dong, H., & Zhang, X. (2017). The efficacy and safety of acupuncture for menopausal hot flashes: A systematic review and meta-analysis. BJOG, 124(1), 22-30.
  • Zhao, F. Y., Fu, Q. Q., Kennedy, G. A., Conduit, R., Zhang, W. J., & Zheng, Z. (2021). Acupuncture as an independent or adjuvant management to standard care for perimenopausal depression: A systematic review and meta-analysis. Frontiers in Psychiatry, 12, 666988.
  • Vas, J., Modesto, M., Aguilar, I., Gonçalo, C. S., & Rivas-Ruiz, F. (2013). Efficacy and safety of auriculopressure for primary care patients with chronic non-specific spinal pain: A multicentre randomised controlled trial. Acupuncture in Medicine, 32(3), 227-235.
  • Yeh, C. H., Kwai-Ping Suen, L., Chien, L. C., Margolis, L., Liang, Z., Glick, R. M., & Morone, N. E. (2015). Day-to-day changes of auricular point acupressure to manage chronic low back pain: A 29-day randomized controlled study. Pain Medicine, 16(10), 1857-1869.

Disclaimer: This article is for educational purposes only and does not constitute medical advice, diagnosis, or treatment. Acupuncture should be performed by a qualified or licensed practitioner, and self-myofascial release should be practiced with appropriate technique and pressure. Avoid myofascial release over acute injuries, open wounds, bruising, infections, inflamed areas, major blood vessels, or directly over the spine. Consult a healthcare provider before beginning these practices if you take blood thinners, have a bleeding disorder, deep vein thrombosis, advanced osteoporosis, an acute medical condition, or any health concern that may affect your safety.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

The Nordic Fascia Release Method: What Midlife Women Should Know Before Booking a Session or Buying the Tools

The Nordic Fascia Release Method has emerged from the broader Scandinavian wellness tradition that includes long-standing engagement with cold exposure, sauna, massage traditions, and various body-based practices. In its contemporary form, the method combines specific myofascial manual techniques with the use of specialized wooden or ceramic tools designed to apply sustained pressure to fascial tissues. Certified practitioners in various parts of the world (concentrated primarily in Scandinavia, with expanding presence in North America and other regions) offer sessions using the method, and the developers also sell tools and training programs.

Important: Fascia bodywork including the Nordic Fascia Release Method is generally safe for most healthy midlife women. Certain conditions warrant medical clearance before starting including recent surgery, active injuries, cardiovascular concerns, and various other specific situations. Discuss with your healthcare provider if you have any concerns. This article is educational and does not constitute medical advice.

What Is the Nordic Fascia Release Method?

The Nordic Fascia Release Method is a specific proprietary bodywork approach. The general publicly available description of what the method involves helps midlife women understand what they would encounter in a session or in training.

Nordic Fascia Release Method overview infographic.
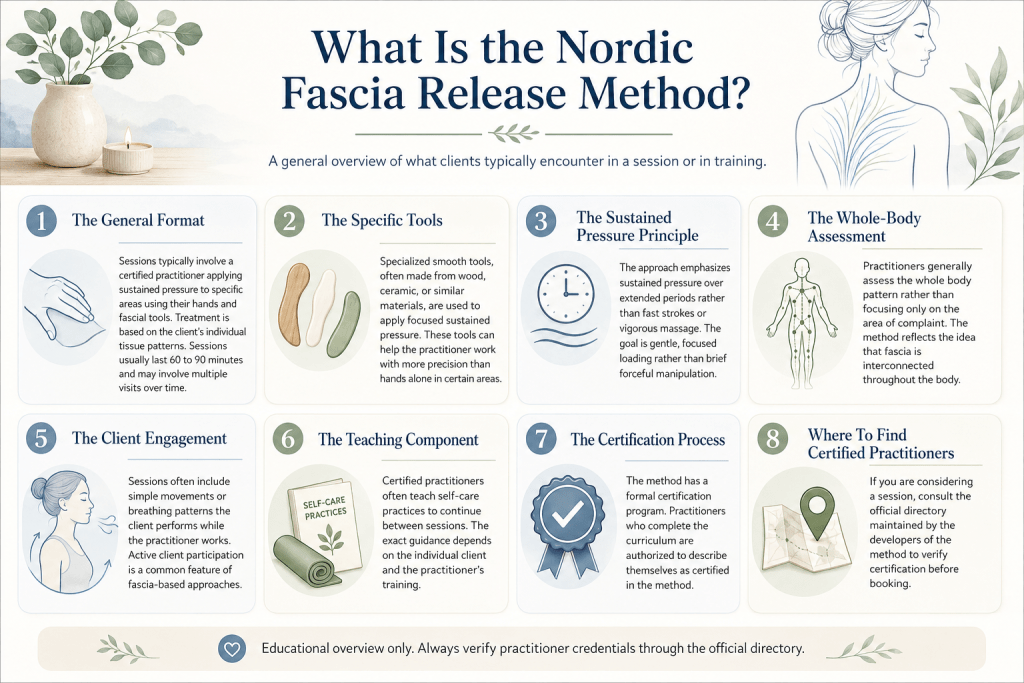
  • The general format: Sessions typically involve a certified practitioner applying sustained pressure to specific areas of the client’s body using their hands and specific tools designed for fascial work. The practitioner works through specific tissue patterns based on the assessment of the individual client. Sessions typically last 60 to 90 minutes and often involve multiple visits over time for cumulative benefit.
  • The specific tools: The method uses specialized smooth tools (often made from wood, ceramic, or similar materials) designed to apply focused sustained pressure to fascial tissues. The specific design and use of these tools is part of the proprietary teaching. In general terms, the tools allow the practitioner to work with more focused pressure than hands alone can provide in certain areas.
  • The sustained pressure principle: The general approach emphasizes sustained pressure over extended periods rather than fast strokes or vigorous massage. This sustained approach aligns with the broader fascia research showing that fascia responds to sustained gentle loading over minutes rather than to brief vigorous manipulation.
  • The whole-body assessment: Practitioners generally assess the client’s whole body pattern rather than focusing only on the specific area of complaint. Fascia is interconnected, and the general Nordic approach reflects this interconnection by treating the body as a whole.
  • The client engagement: Sessions often include specific movements or breathing patterns the client is asked to perform while the practitioner works. This active engagement is a general feature of many fascia approaches.
  • The teaching component: Certified practitioners in the method often teach clients specific self-care practices to continue between sessions. The specific practices taught depend on the individual and on the practitioner’s training.
  • The certification process: The Nordic Fascia Release Method has a specific certification program for practitioners. Trained practitioners have completed the specific curriculum and are authorized to represent themselves as certified in the method. Uncertified practitioners who describe their work using this specific method name are misrepresenting their qualifications.
  • Where to find certified practitioners: The developers of the method maintain a directory of certified practitioners. If you are considering booking a session using this specific method, consult the official directory to verify certification.

What Is the Scandinavian Wellness Tradition Context?

Understanding the broader tradition the Nordic Fascia Release Method emerges from helps contextualize the approach.

  • The general Scandinavian wellness lineage: Nordic countries have long-standing wellness traditions including sauna, cold water immersion, various massage traditions, outdoor movement, and specific approaches to body work. These traditions are integrated into daily life in ways that Western wellness cultures often are not.
  • The specific relationship to touch: Scandinavian bodywork traditions often emphasize deliberate touch as a specific therapeutic modality. Various forms of Swedish massage, Finnish massage traditions, and specific modern developments have contributed to this broader tradition.
  • The nature-based framework: Scandinavian wellness often includes explicit connection to nature (outdoor time, natural elements, seasonal awareness) as part of the general health framework. Fascia bodywork in this tradition often reflects this broader nature-connected framing.
  • The specific relationship to seasonality: Scandinavian traditions have strong seasonal awareness that shows up in wellness practices. Winter and summer practices differ. This seasonal awareness sometimes shows up in how bodywork is practiced or discussed.
  • The modern development: Various contemporary Scandinavian practitioners have developed specific modern approaches that combine traditional lineage with contemporary understanding of fascia and connective tissue. The Nordic Fascia Release Method is one specific example of this modern development.
  • The cultural context matters: For practitioners and clients coming from outside the Scandinavian cultural context, understanding the broader tradition helps interpret the specific practices. The method is not just a set of techniques but reflects a broader cultural approach to body work.
  • The specific caution about cultural adoption: As with any cultural tradition adopted by wellness industries outside the source culture, there are specific concerns about cultural adoption, oversimplification, and commercial repackaging. Approach any specific method with appropriate cultural humility.
  • The specific value of engaging with the source tradition: For those seriously interested in this specific method, engaging with practitioners trained in the source lineage produces different value than working with wellness-industry practitioners who have adopted vocabulary without the training.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Why Are Midlife Women Drawn to This Method Now?

The specific interest in the Nordic Fascia Release Method among midlife women reflects broader patterns worth understanding.

Growing Awareness and Menopause-Related Interest

  • The fascia awareness moment: Fascia has moved from obscure anatomical detail to mainstream wellness topic over the last several years. Midlife women who are experiencing the specific aches and stiffness of perimenopause and menopause are often actively searching for fascia-focused approaches.
  • The specific menopause fascia connection: The specific fascia changes of the perimenopause and menopause transition drive real symptoms that fascia-focused bodywork approaches can help address. Midlife women searching for solutions to these symptoms often find fascia methods.

Novelty, Tools, and Deeper Engagement

  • The high perceived novelty: The Nordic origin and specific tool-based approach differentiates the method from more familiar bodywork forms. This differentiation attracts women who have tried various other approaches without the results they hoped for.
  • The specific tool appeal: Purchasing specific tools appeals to the same impulses that drive other wellness product purchases. The tools become both functional equipment and identifying markers of engagement with the method.
  • The retreat and training appeal: Beyond individual sessions, the method offers immersive training experiences that appeal to women interested in deeper engagement or in becoming practitioners themselves.
  • The cultural travel appeal: Some midlife women travel to Scandinavia to experience the method in its source culture. This travel appeal adds to the general attraction.

Influencer Visibility and the Need for Caution

  • The influencer amplification: The Nordic Fascia Release Method has been promoted by various wellness influencers and podcasters, which has substantially increased visibility. This amplification is neither endorsement nor criticism of the method itself but explains its current visibility.
  • The specific caution about influencer content: Wellness-influencer content about the method varies widely in accuracy and depth. Some content is thoughtful engagement with the method’s actual principles. Other content is superficial marketing that may not reflect what the method involves. Evaluate influencer content with the same critical thinking you would apply to any other wellness marketing.

“The specific question I hear from coaching clients about the Nordic Fascia Release Method is whether it is worth the specific investment of time and money required for either sessions or training. My honest answer depends on the specific client’s situation. For a woman who has already installed the foundational fascia framework (regular movement, appropriate nutrition, quality sleep, nervous system regulation, and some form of consistent self-care fascia practice) and who wants to explore deeper professional support, working with a certified practitioner in this or any specific credentialed fascia method can add meaningful value. For a woman who has not yet installed the foundational framework and who is looking for a specific method to substitute for that foundation, no proprietary bodywork method will produce the outcomes she hopes for. The method works best as a specific addition to a solid foundation, not as a replacement for the foundation. That framing is the specific consideration I recommend to clients evaluating this or any other specific proprietary approach.”

Terry Tateossian, Founder of The House of Rose

Which General Principles Align With Fascia Research?

Several of the general principles that the Nordic Fascia Release Method emphasizes align well with the broader fascia research base.

  • Sustained pressure over time: The general principle of applying sustained pressure over minutes rather than brief vigorous manipulation aligns with the broader fascia research. Fascia responds to sustained loading over 90 seconds to several minutes more than to short strokes. This is a general principle that appears across many effective fascia approaches.
  • Whole-body pattern assessment: The general principle of assessing the whole body rather than treating only the site of symptoms aligns with the fascia research showing that fascial restrictions in one area often refer symptoms to distant sites. Treating fascia locally without considering the whole pattern often produces incomplete results.
  • The client engagement component: The general principle of involving the client actively during the session (through breathing, specific movements, or attention) aligns with the research on the neural component of fascial release. Fascia is densely innervated and responds partly through neurological rather than purely mechanical mechanisms.
  • The interconnection framework: The general acknowledgment that fascia is a connected system rather than a set of separate structures aligns with modern understanding of fascial anatomy. The specific fascial lines that connect distant body regions are well-documented anatomically.
  • The self-care teaching component: The general practice of teaching clients specific self-care to continue between sessions aligns with the research showing that consistent daily practice produces better outcomes than occasional intensive sessions.
  • The tool-based focused pressure: The general use of tools to apply focused sustained pressure to specific areas aligns with the broader self-myofascial release research showing that focused pressure produces measurable improvements in tissue mobility and range of motion.
  • The specific caveat about proprietary claims: While the general principles align with research, specific proprietary claims about how a particular method uniquely accomplishes these effects may exceed what the general research supports. The principles are broadly supported. Specific proprietary claims require separate evaluation.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Does the Broader Fascia Research Support?

The broader research on fascia release provides the context for evaluating any specific method including the Nordic approach.

  • Self-myofascial release research: Multiple systematic reviews and meta-analyses document that self-myofascial release techniques using foam rollers, balls, and similar tools produce measurable improvements in range of motion, reduce delayed onset muscle soreness, and support recovery. Effect sizes are modest but consistent.
  • Manual fascia therapy research: Research on manual myofascial release performed by trained practitioners documents improvements in pain, function, and range of motion across various conditions. The specific proprietary methods vary in their evidence bases.
  • Fascial mobility research: Studies of fascial mobility using various imaging techniques document that fascia can be affected by manual intervention in ways that produce measurable tissue changes. The specific mechanisms include hydration changes, hyaluronic acid effects, and mechanical remodeling over time.
  • The sustained pressure research: Studies of sustained pressure durations document that meaningful fascial response typically requires at least 90 seconds of sustained pressure on a specific area. Longer holds produce more response up to a point.
  • The whole-body versus local research: Studies comparing whole-body versus locally-focused fascial interventions generally support the whole-body approach for outcomes beyond immediate local pain reduction.
  • The self-care versus practitioner-only research: Research consistently supports the value of daily self-care practice alongside or instead of periodic practitioner sessions. Self-care practice produces meaningful cumulative benefits.
  • The consistency research: Consistent daily practice over weeks produces meaningfully better outcomes than occasional intensive sessions. This applies to both self-care practice and to combined self-care plus practitioner sessions.
  • What the research does not clearly show: The research generally does not clearly demonstrate that one specific proprietary method produces uniquely better outcomes than well-designed alternative approaches. Various methods produce broadly similar outcomes when practiced consistently. This does not mean specific methods have no value. It means that specific proprietary claims of unique superiority typically exceed what the comparative research supports.

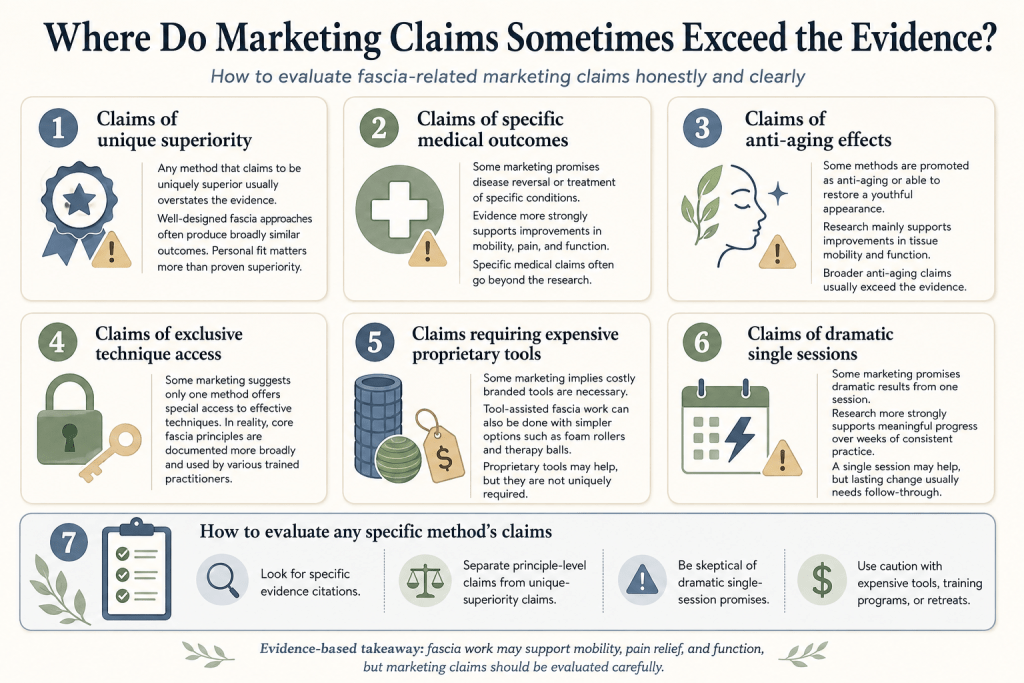
Where Do Marketing Claims Sometimes Exceed the Evidence?

Being honest about where marketing claims sometimes exceed what evidence supports helps midlife women evaluate any specific method including the Nordic approach.

Marketing claims versus fascia evidence infographic.
  • Claims of unique superiority: Any specific method that claims to be uniquely superior to alternatives typically overstates what comparative research demonstrates. Various well-designed fascia approaches produce broadly similar outcomes. The specific choice among them depends on personal fit rather than on demonstrated superiority.
  • Claims of specific medical outcomes: Some marketing suggests that specific fascia methods produce specific medical outcomes (reversing specific diseases, treating specific conditions). The general fascia research supports improvements in mobility, pain, and function. Claims of specific medical treatment outcomes usually exceed what evidence supports.
  • Claims of anti-aging effects: Some marketing suggests that specific fascia methods produce anti-aging effects, restore youthful appearance, or reverse age-related changes. The general research supports specific improvements in tissue mobility and function. Broader anti-aging claims typically exceed what evidence supports.
  • Claims of exclusive technique access: Some marketing frames specific methods as offering exclusive technique access that is not available elsewhere. The general principles of effective fascia work are well-documented in the broader research and are available through various trained practitioners.
  • Claims requiring expensive proprietary tools: Some marketing suggests that specific proprietary tools are required for effective fascia work. The general principles of tool-assisted fascia work can be applied with various tools including inexpensive foam rollers and therapy balls. Specific proprietary tools may have specific advantages but are typically not uniquely required.
  • Claims of dramatic single sessions: Some marketing suggests that single sessions produce dramatic outcomes. The general research supports meaningful improvements over weeks of consistent practice. Single sessions can produce immediate subjective changes but typically require follow-through for lasting effects.
  • How to evaluate any specific method’s claims: Look for specific evidence citations. Distinguish between principle-level claims (which are often supported) and unique-superiority claims (which are typically not). Be skeptical of dramatic single-session promises. Approach expensive training programs, tools, or retreats with appropriate caution.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Can You Expect From a Session?

For midlife women considering booking a session with a certified practitioner in the Nordic Fascia Release Method, understanding what to expect helps set appropriate expectations.

Before and During the Session

The first part of the process focuses on understanding your needs and identifying the areas that may require the most attention.

  • The intake: A first session typically begins with a thorough intake including your specific health history, current symptoms, previous injuries, current medications, and specific goals for the work. This intake is a normal part of any competent bodywork practice.
  • The assessment: The practitioner typically assesses your specific body patterns through observation and palpation. This assessment guides where and how the practitioner will work during the session.
  • The session itself: Sessions typically last 60 to 90 minutes. The practitioner works through various areas using their hands and specific tools. Sensation varies from mild pressure to occasionally intense sensation during focused work on specific restricted areas.

What You May Feel During and After the Work

Fascia-focused bodywork can involve physical and emotional sensations that may feel different from those experienced during familiar forms of massage.

  • The specific sensations: Fascia work often produces distinctive sensations that differ from familiar massage. These can include specific burning, tingling, deep pressure, occasional sharp releases, and various other sensations. Communicate with your practitioner about specific sensations that concern you.
  • The emotional component: Fascia work often produces emotional responses including spontaneous tears, feelings of grief or relief, and various other emotional experiences. This is a documented phenomenon in body-based practice and is generally considered a healthy sign of stored tension releasing. Practitioners trained in fascia work are typically prepared to support these responses appropriately.

Follow-Up, Frequency, and Investment

The work usually extends beyond the session itself through self-care, repeated sessions, and ongoing evaluation of your progress.

  • The homework: Practitioners typically provide specific self-care recommendations to continue between sessions. Follow-through with the self-care matters as much as the session itself for producing lasting results.
  • The frequency recommendation: Practitioners typically recommend specific frequency depending on your situation. Common patterns include weekly sessions for the first month or two followed by monthly maintenance sessions.
  • The specific investment: Sessions typically cost $150 to $300 depending on the practitioner and location, with initial packages of multiple sessions often recommended.

Setting Realistic Expectations

Results can vary from person to person, so it is important to evaluate how your body responds over time rather than expecting immediate transformation.

  • Realistic expectations: Meaningful improvement typically appears over multiple sessions combined with consistent self-care practice. Immediate transformation is rare. Sustained improvement over months of consistent engagement is common.
  • When to reconsider: If sessions produce persistent pain, if you feel the practitioner is not listening to your feedback, if the recommendations feel excessive or expensive, or if the specific approach does not fit your body, consider changing practitioners or approaches.

What Are the Tools and Their General Functions?

The specific tools used in the Nordic Fascia Release Method deserve some discussion because they are a distinctive feature of the approach.

  • The general purpose: Tools in fascia work generally allow the practitioner (or self-practitioner) to apply focused sustained pressure to specific areas in ways that hands alone cannot easily achieve. The specific shape, material, and design of tools varies by tradition.
  • The Nordic-style tools: Tools used in the Nordic Fascia Release Method are typically smooth wooden or ceramic pieces designed for fascial work. The specific designs are part of the proprietary offering of the method.
  • The specific tool categories: Various tools exist for different specific purposes including broad surface tools for large areas, smaller focused tools for specific spots, and tools designed for specific body regions.
  • The alternative tools available: The general principles of tool-assisted fascia work can be practiced with various alternatives including foam rollers, therapy balls (tennis balls, lacrosse balls), massage sticks, and various other options. These alternatives are often significantly less expensive than proprietary tools.
  • The specific value of specialized tools: Well-designed specialized tools may offer specific advantages in shape, texture, or ergonomics that generic tools do not. Whether these advantages justify significant additional cost depends on the individual and the specific tools.
  • The buying question: For midlife women considering purchasing tools associated with the Nordic Fascia Release Method or any specific proprietary method, consider whether you have first established consistent practice with basic tools. If daily practice is already well-installed, upgraded tools may be worthwhile. If practice is inconsistent, better tools will not create consistency.
  • The specific caution about tool marketing: As with any wellness product, tool marketing sometimes exceeds what the tools accomplish. Basic tools produce most of the fascial benefit for most people. Specific specialty tools may offer specific advantages but are typically not uniquely required.
  • The DIY alternative: Some effective fascia tools can be made or improvised at home from various materials. Tennis balls in socks. Rolling pins for larger surfaces. Various other alternatives exist. The specific principles matter more than the specific tools.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Does the Method Compare to Other Fascia Approaches?

Placing the Nordic Fascia Release Method in the context of other fascia approaches helps midlife women make informed comparisons.

  • The general principle: Various fascia approaches share common general principles (sustained pressure, whole-body awareness, breath integration, consistent practice) while differing in specific techniques, training lineages, and cultural contexts. The general principles matter more than the specific method for most outcomes.
  • The specific choice question: The specific choice among fascia approaches depends on individual factors including personal preference, availability of trained practitioners, budget, cultural resonance, and specific goals. No single method is universally superior for all midlife women.
  • The specific value of trying multiple approaches: Some midlife women find that different approaches suit them at different times or for different specific concerns. Being open to multiple approaches often produces better long-term outcomes than rigid commitment to a single method.
  • The specific value of consistency within any approach: Whatever specific approach you choose, consistency over months and years produces the specific benefits that fascia work can deliver. Occasional engagement with the most sophisticated method produces less than consistent engagement with a simpler approach.

What Should You Know About Foam Rolling and Self-Myofascial Release?

Foam rolling is the most widely accessible fascia approach and provides useful context for comparing with proprietary methods.

Foam rolling and self-myofascial release infographic.
  • The general approach: Foam rolling uses cylindrical foam rollers of various densities to apply body weight pressure to large muscle groups and their surrounding fascia. Self-practice at home is the standard format.
  • The evidence base: The research on foam rolling is one of the more developed research bases for any fascia intervention. Multiple systematic reviews document specific benefits for range of motion, recovery, and delayed onset muscle soreness.
  • The cost accessibility: Foam rollers typically cost $15 to $50 and last for years. This is dramatically less expensive than most proprietary fascia methods.
  • The specific limitations: Foam rolling addresses large muscle groups well but is less effective for specific small areas that benefit from more focused pressure. Combining foam rolling with therapy balls addresses this limitation.
  • The specific comparison: Foam rolling and proprietary methods like the Nordic Fascia Release Method share general principles. The specific choice depends on whether the individual benefits from professional guidance and specialized tools versus self-directed practice with basic equipment.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Does Traditional Deep Tissue Massage Compare?

Traditional deep tissue massage is another familiar bodywork approach that shares some overlap with fascia work.

Approach and Evidence

  • The general approach: Deep tissue massage typically involves a trained massage therapist applying deep sustained pressure to muscles and their fascial coverings through various stroke techniques.
  • The evidence base: Massage therapy has a broad evidence base supporting various outcomes including pain reduction, stress reduction, and improved recovery.

Cost and Key Differences

  • The cost consideration: Traditional deep tissue massage typically costs $100 to $200 per session. This is often less expensive than specialty proprietary methods but represents ongoing cost.
  • The specific comparison: Traditional deep tissue massage and specialty fascia methods share general principles. Specialty methods often offer more specific tool-based work, more explicit focus on fascial rather than muscular tissue, and specific training lineages. Traditional massage offers wider practitioner availability and typically lower cost.

Who May Find It a Better Fit?

Midlife women who benefit from general therapeutic touch and stress reduction alongside targeted body work may find traditional massage a good fit. Those specifically seeking fascia-focused technical work may prefer specialty methods.

How Does Fascial Stretch Therapy Compare?

Fascial Stretch Therapy is a specific proprietary approach that focuses on assisted stretching rather than tool-based release.

  • The general approach: Fascial Stretch Therapy involves a trained practitioner passively moving the client through specific stretch patterns designed to address fascial mobility. Sessions typically use a specialized table with straps.
  • The evidence base: The specific research on Fascial Stretch Therapy is more limited than for foam rolling or general massage but generally supports improvements in range of motion and function.
  • The specific comparison: Fascial Stretch Therapy focuses on assisted movement and stretching while the Nordic Fascia Release Method emphasizes tool-based sustained pressure. Both address fascial mobility through different specific mechanisms.
  • The specific fit: Midlife women who respond well to passive stretching and movement-based work may find Fascial Stretch Therapy a good fit. Those who respond well to focused pressure work may prefer tool-based methods.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Do Yin Yoga and Sustained Postures Support Fascia?

Yin yoga is a self-practice approach that shares many principles with proprietary fascia methods.

Yin yoga and fascia support infographic.
  • The general approach: Yin yoga involves sustained holds of specific postures for 3 to 5 minutes or longer, using body weight and gravity to apply the sustained loading that fascia responds to.
  • The evidence base: Yin yoga research is emerging but generally supports improvements in flexibility, stress reduction, and various other outcomes.
  • The cost accessibility: Yin yoga can be practiced at home for free using video instruction or with modest investment in classes.
  • The specific comparison: Yin yoga shares the general principles of sustained loading with proprietary fascia methods. It works through movement patterns rather than tool-based pressure and offers self-practice rather than practitioner-based sessions.
  • The specific integration: Many midlife women benefit from combining yin yoga self-practice with periodic sessions of a specific proprietary method. The two approaches work well together.

How Do Cupping and Gua Sha Traditions Compare?

Cupping and gua sha are traditional East Asian bodywork approaches that share some overlap with fascia methods.

  • The general approach: Cupping uses suction cups applied to the skin to lift and mobilize tissues. Gua sha uses smooth-edged tools to scrape the skin, producing what the tradition considers therapeutic effects on tissue and circulation.
  • The evidence base: Both approaches have growing research bases supporting specific effects on pain, mobility, and various other outcomes.
  • The specific comparison: Traditional East Asian approaches share the general principle of tool-based tissue work with the Nordic Fascia Release Method. The specific mechanisms and cultural contexts differ.
  • The specific consideration: For midlife women interested in traditional lineage-based bodywork, exploring the East Asian traditions alongside or instead of Scandinavian traditions offers different specific experiences.
  • The cultural respect consideration: As with any traditional practice, engaging with the source lineage rather than with commercial adaptation typically produces different value.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Should You Evaluate Practitioners?

For midlife women considering booking sessions in the Nordic Fascia Release Method or any specialty fascia approach, evaluating practitioners matters.

Check Training and Relevant Experience

  • Verify certification: For proprietary methods, verify that the practitioner is certified in the specific method they claim to practice. Consult the official directory maintained by the method developers.
  • Ask about training background: Beyond specific method certification, ask about the practitioner’s broader bodywork training and experience. Practitioners with strong general foundations often deliver better outcomes than those with only narrow specialty training.
  • Ask about experience with your specific concerns: Different practitioners have different specific areas of experience. A practitioner experienced with midlife women, menopause-related concerns, or your specific issues typically produces better outcomes than a general practitioner.

Ask About the Session and Expected Outcomes

  • Ask about session structure: A competent practitioner should be able to describe their typical session structure, intake process, and follow-up recommendations clearly. Vague answers may indicate less established practice.
  • Ask about specific outcomes and expectations: A competent practitioner should offer realistic expectations rather than dramatic promises. Be skeptical of practitioners who promise dramatic outcomes.
  • Ask about coordination with other care: A competent practitioner should support your continued relationship with your medical providers and should discourage substituting bodywork for appropriate medical care.

Consider Comfort, Trust, and Setting

  • Trust your response to the initial consultation: Beyond specific credentials, notice how you feel during the initial consultation. Do you feel heard? Do you feel comfortable with the practitioner? Do you trust their judgment? These felt responses matter.
  • Consider the setting: The physical setting should be professional, clean, and comfortable. Boundaries around the session should be clear and appropriate.

Keep Practitioner Fit in Perspective

Some practitioners in any specialty method are excellent. Others are less well-trained or less well-suited to your specific needs. Finding the right practitioner may take a few tries.

What Should You Know About Cost, Frequency, and Realistic Expectations?

Setting realistic expectations for cost, frequency, and outcomes helps midlife women evaluate whether specialty fascia methods fit their situation.

Cost and Frequency

  • The typical session cost: Certified practitioners in specialty fascia methods typically charge $150 to $300 per session. Cost varies by location, practitioner experience, and specific method.
  • The typical frequency recommendation: Weekly sessions for the first month or two followed by monthly maintenance is a common recommended pattern. Some practitioners recommend more frequent early work.

Timeline and Total Investment

  • The typical timeline for meaningful improvement: Subjective improvements often appear within the first few sessions. Meaningful cumulative improvement typically requires consistent engagement over 2 to 3 months. Sustained transformation requires ongoing practice over 6 to 12 months or more.
  • The specific total investment: For a full initial course of specialty fascia work plus monthly maintenance for a year, total investment often exceeds $3,000 to $5,000 including tools if purchased. This is a meaningful financial commitment.
  • The alternative investment: For the same total investment, a midlife woman could purchase basic self-care tools, take classes in yin yoga or tai chi, join a well-run coaching program, or attend an immersive retreat. Each of these alternatives has specific value.

Evaluating the Value

  • The specific value proposition: Specialty fascia methods deliver specific value including expert assessment, focused work you cannot easily do yourself, and structured programming. Whether this value justifies the cost depends on the individual.
  • The specific caution about escalating recommendations: Some practitioners recommend progressively more sessions, more tools, or more training. Evaluate these recommendations carefully. Not every escalation is warranted.

Compare Specialty Work With Accessible Alternatives

Before committing to expensive specialty methods, consider whether you have exhausted the value available from more accessible alternatives. Consistent daily self-care produces meaningful outcomes. Adding specialty work on top of an established foundation produces different value than substituting specialty work for foundational practice.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Who Should Consider This Method (and Who Should Not)?

Being honest about who is likely to benefit from this specific method and who may benefit more from alternatives helps midlife women make informed decisions.

Good Candidates for Exploring the Method

Good candidates for exploring the Nordic Fascia Release Method or similar specialty approaches include:

  • Midlife women who have already installed a solid foundation of daily movement, nutrition, sleep, and nervous system regulation, and who want to add specific specialty bodywork to complement the foundation.
  • Women who have tried general foam rolling and self-care fascia work and want more specialized professional support for specific persistent issues.
  • Women who have the financial resources and time for ongoing specialty sessions plus consistent self-care.
  • Women who resonate with the Scandinavian wellness tradition or with tool-based work.
  • Women who have access to a well-trained certified practitioner in their geographic area.
  • Women who want a specific structured program with an experienced practitioner.

Better Candidates for Alternative Approaches

Some women may benefit more from alternative approaches, depending on their current needs, resources, and priorities.

  • Women who have not yet installed the foundational lifestyle medicine framework. Foundation first, specialty work after.
  • Women with limited financial resources for ongoing specialty sessions. Excellent self-care outcomes are available with more accessible approaches.
  • Women who prefer self-directed practice over practitioner-based work.
  • Women whose primary need is general stress relief and touch rather than specific fascia-focused technical work. Traditional massage may fit better.
  • Women whose primary need is movement improvement rather than tissue-focused release. Yoga, tai chi, or Pilates may fit better.
  • Women who do not have access to a well-trained certified practitioner. Traveling long distances for occasional sessions typically does not produce good outcomes.
  • Women dealing with significant medical conditions that require primary medical care. Bodywork can complement but cannot substitute for appropriate medical treatment.

The Honest Self-Assessment

The specific value of this or any specialty method for you depends on your specific situation. Honest assessment of where you currently are and what would produce the biggest improvement in your specific situation helps guide the decision.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

When Should You See a Healthcare Professional?

Specialty fascia methods and any bodywork are not substitutes for appropriate medical care. Certain situations warrant professional evaluation.

  • Persistent unexplained pain: Pain that persists despite consistent bodywork warrants medical evaluation to identify underlying causes.
  • Progressive symptoms: Any progressive worsening of symptoms warrants evaluation regardless of any bodywork engagement.
  • Neurological symptoms: Numbness, weakness, radiating pain, or other neurological symptoms warrant medical evaluation.
  • Recent injuries or surgeries: Wait for medical clearance before beginning specialty bodywork after any significant injury or surgery.
  • Cardiovascular concerns: Any known cardiovascular disease warrants physician clearance before starting intensive bodywork.
  • Any concerning symptoms during sessions: Chest pain, severe dizziness, or other alarming symptoms during a bodywork session warrant immediate medical evaluation.
  • Mental health concerns: Some bodywork produces emotional responses that can be intense. If you have specific mental health concerns or trauma history, working with practitioners trained in trauma-informed approaches produces better outcomes than working with practitioners without this specific training.
  • Pregnancy: Some bodywork approaches need modification during pregnancy. Work with practitioners with prenatal training.

What Are Your Next Steps?

If you are considering the Nordic Fascia Release Method or any specialty fascia approach, here are the four next steps in order of friction.

  1. Assess your foundation. Before investing in specialty methods, honestly assess whether you have installed the foundational lifestyle medicine framework. If not, the foundation produces bigger benefits than any specialty method.
  2. Try accessible self-care first. Basic foam rolling, therapy ball work, and yin yoga home practice using free video instruction lets you experience fascia work at minimal cost.
  3. If you decide to explore specialty methods, verify practitioner credentials. For any proprietary method, verify certification through the official directory. Ask about training background and experience with midlife women.
  4. Consider an immersive women’s yoga and wellness retreat or 1:1 online coaching 

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

What is the Nordic Fascia Release Method?

The Nordic Fascia Release Method is a specific proprietary bodywork approach developed within the Scandinavian wellness tradition. Sessions typically involve a certified practitioner applying sustained pressure to specific areas of the body using their hands and specialized wooden or ceramic tools designed for fascial work. Certified practitioners work with clients through specific tissue patterns based on individual assessment.

Is the Nordic Fascia Release Method evidence-based?

The general principles the method emphasizes (sustained pressure, whole-body assessment, breath integration, client engagement) align with the broader fascia release research base. The specific proprietary techniques and specific claims of unique superiority have less specific evidence and should be evaluated with appropriate skepticism. Various well-designed fascia approaches produce broadly similar outcomes.

How much does a Nordic Fascia Release session cost?

Certified practitioners typically charge $150 to $300 per session depending on location, practitioner experience, and session length. Initial course of multiple sessions often recommended. Total investment for an initial course plus monthly maintenance can exceed $3,000 to $5,000 per year including tools if purchased.

Where can I find certified practitioners?

The developers of the method maintain an official directory of certified practitioners. If you are considering booking a session using this specific method, consult the official directory to verify certification. Uncertified practitioners representing themselves as certified in the method are misrepresenting their qualifications.

Can I learn to do this method myself?

The specific method has a certification program for practitioners. Learning to practice the specific method professionally requires completing the specific training. However, the general principles of self-care fascia work are accessible through various self-directed practices including foam rolling, therapy ball work, and yin yoga.

How does this method compare to foam rolling?

Both share the general principle of tool-assisted sustained pressure to fascia. The Nordic method offers professional guidance, specialized tools, and structured programming. Foam rolling offers self-directed practice at dramatically lower cost. Both produce meaningful outcomes with consistent practice. The specific choice depends on individual preferences and resources.

Does the Nordic method help with menopause aches and stiffness?

Fascia bodywork including the Nordic method addresses the specific fascial changes that contribute to menopause aches and stiffness. Any well-designed fascia approach can help; the specific method matters less than consistent engagement with an approach that fits you.

How often should I do fascia release?

For self-care practice, daily 10 to 15 minute sessions produce meaningful cumulative benefit. For specialty practitioner sessions, weekly for the first month or two followed by monthly maintenance is a common pattern. Consistency matters more than frequency.

Is the Nordic method safe?

For most healthy midlife women, appropriate fascia bodywork is safe. Certain conditions warrant medical clearance including recent surgery, active injuries, cardiovascular concerns, and various other specific situations. Discuss with your healthcare provider if you have concerns. Trained certified practitioners typically conduct appropriate intake to identify contraindications.

Do I need the specific tools?

The specific proprietary tools used in the method offer specific advantages in shape and design. Similar general benefits can be achieved with more accessible tools including foam rollers, therapy balls, and various other options. Whether the specialty tools justify their cost depends on individual circumstances and how established your practice is.

What are the alternatives to the Nordic method?

Alternatives with similar general principles include foam rolling, self-myofascial release with balls, traditional deep tissue massage, Fascial Stretch Therapy, yin yoga, cupping, gua sha, and various other approaches. Each has specific strengths. The best fit depends on individual preferences and specific goals.

How long before I see results?

Subjective improvements often appear within the first few sessions or first few weeks of consistent self-care. Meaningful cumulative improvement typically requires 2 to 3 months of consistent engagement. Sustained transformation requires ongoing practice over 6 to 12 months or more.

Can this method help with lymphatic drainage?

Fascia and the lymphatic system are functionally interconnected. Fascia work often produces effects on lymphatic circulation as one component of the broader effects.

Is the Nordic method better than yoga for fascia?

Neither is universally better. Yoga (particularly yin yoga) uses sustained postures and gravity to produce fascial effects through movement patterns. The Nordic method uses tool-based sustained pressure by a practitioner. Both address fascia through different mechanisms. Many midlife women benefit from combining both.

Should I take the training to become a practitioner?

The training decision depends on your specific goals. If you want to practice the method professionally, the specific certification is required. If you want deeper self-care knowledge, other more accessible training options may fit better. Evaluate the specific investment against your specific goals.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.


References

  • Schleip, R., & Müller, D. G. (2013). Training principles for fascial connective tissues: scientific foundation and suggested practical applications. Journal of Bodywork and Movement Therapies, 17(1), 103–115.
  • Stecco, C., Fede, C., Macchi, V., et al. (2018). The fasciacytes: a new cell devoted to fascial gliding regulation. Clinical Anatomy, 31(5), 667–676.
  • Stecco, C., Stern, R., Porzionato, A., et al. (2011). Hyaluronan within fascia in the etiology of myofascial pain. Surgical and Radiologic Anatomy, 33(10), 891–896.
  • Ajimsha, M. S., Al-Mudahka, N. R., & Al-Madzhar, J. A. (2015). Effectiveness of myofascial release: systematic review of randomized controlled trials. Journal of Bodywork and Movement Therapies, 19(1), 102–112.
  • Beardsley, C., & Škarabot, J. (2015). Effects of self-myofascial release: a systematic review. Journal of Bodywork and Movement Therapies, 19(4), 747–758.
  • Behm, D. G., & Wilke, J. (2019). Do self-myofascial release devices release myofascia? Rolling mechanisms: a narrative review. Sports Medicine, 49(8), 1173–1181.
  • Cheatham, S. W., Kolber, M. J., Cain, M., & Lee, M. (2015). The effects of self-myofascial release using a foam roll or roller massager on joint range of motion, muscle recovery, and performance: a systematic review. International Journal of Sports Physical Therapy, 10(6), 827–838.
  • Wiewelhove, T., Döweling, A., Schneider, C., et al. (2019). A meta-analysis of the effects of foam rolling on performance and recovery. Frontiers in Physiology, 10, 376.
  • Klingler, W., Velders, M., Hoppe, K., et al. (2014). Clinical relevance of fascial tissue and dysfunctions. Current Pain and Headache Reports, 18(8), 439.
  • Chaitow, L. (2020). Fascia as a sensory organ: implications for practice. Journal of Bodywork and Movement Therapies, 24(4), 3–4.
  • Bordoni, B., & Zanier, E. (2013). Anatomic connections of the diaphragm: influence of respiration on the body system. Journal of Multidisciplinary Healthcare, 6, 281–291.
  • Field, T. (2016). Massage therapy research review. Complementary Therapies in Clinical Practice, 24, 19–31.
  • Ernst, E. (2009). Massage therapy for cancer palliation and supportive care: a systematic review of randomised clinical trials. Supportive Care in Cancer, 17(4), 333–337.
  • Brincat, M. P., Baron, Y. M., & Galea, R. (2005). Estrogens and the skin. Climacteric, 8(2), 110–123.
  • Thornton, M. J. (2013). Estrogens and aging skin. Dermato-endocrinology, 5(2), 264–270.
  • Wright, V. J. (2023). Musculoskeletal syndrome of menopause: an emerging concept. Journal of Women’s Health Physical Therapy, 47(3), 152–159.
  • Woodyard, C. (2011). Exploring the therapeutic effects of yoga and its ability to increase quality of life. International Journal of Yoga, 4(2), 49–54.
  • Chang, D. G., Holt, J. A., Sklar, M., & Groessl, E. J. (2016). Yoga as a treatment for chronic low back pain: a systematic review of the literature. Journal of Orthopedics and Rheumatology, 3(1), 1–8.
  • Anderson, T., & Wideman, L. (2017). Exercise and the cortisol awakening response: a systematic review. Sports Medicine Open, 3(1), 37.
  • Chikly, B. J. (2005). Manual techniques addressing the lymphatic system: origins and development. Journal of the American Osteopathic Association, 105(10), 457–464.

Disclaimer: This article is educational and does not constitute medical advice. THOR is not certified in the Nordic Fascia Release Method or affiliated with the method’s developers. For specific training or professional sessions in the method, consult certified practitioners through the official directory maintained by the method’s developers. Persistent, severe, or unexplained musculoskeletal symptoms warrant medical evaluation regardless of any bodywork engagement.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Is Fascia? A Midlife Woman’s Guide to the Tissue Running Your Whole Body

You wake up, swing your legs out of bed, and the first few steps feel like you’re walking on someone else’s feet. Your hips don’t open the way they used to. Your shoulders live somewhere up near your ears. You stretch, you roll, you foam-roll, you drink water — and some days it helps, and some days nothing does. If you’re a woman in your 40s, 50s, or 60s, this is one of the most common complaints I hear from clients, and nine times out of ten the conversation ends up in the same place: we have to talk about fascia.

Most of us were never taught about fascia in school biology. We learned about muscles and bones and organs, and we were told they sat in our body like parts in a kit. Nobody mentioned that there is a living, webbing sheet of connective tissue wrapping every single one of those parts — holding them in place, transmitting force through them, and, crucially, stiffening up in predictable ways as we age and move through menopause. Once you understand what fascia is, a lot of the aches, the posture changes, and the “my body just feels different now” feelings start to make real sense. Better still, you can actually do something about them.

What Is Fascia in the Body? 

Fascia is the body’s connective-tissue network. If you’ve ever cooked a chicken breast and peeled off that thin, papery white film — that’s fascia. In a human body, that film is everywhere. It wraps each muscle fiber, groups those fibers into bundles, groups the bundles into whole muscles, then links muscles together across entire chains of the body. It also wraps your organs, your nerves, and your blood vessels. Researchers sometimes call it the “great communicator” of the body because it connects everything to everything else.

The tissue itself is made mostly of collagen and elastin fibers suspended in a jelly-like substance called the ground substance, which is rich in hyaluronic acid. When fascia is healthy, it is wet, springy, and slides smoothly against the structures it’s wrapping. When fascia is dehydrated, inflamed, or stuck, it gets grabby. It starts to tether things together that used to glide past each other. That’s when you get that “stiff, stuck, can’t loosen up” sensation that no amount of regular stretching seems to touch.

For decades, fascia was treated as packing material — something to cut through to get to the interesting stuff underneath. That changed in the early 2000s when researchers like Dr. Helene Langevin at the National Institutes of Health started documenting that fascia is densely packed with nerve endings and plays an active role in how we sense, move, and experience pain. In 2007 the first International Fascia Research Congress was held at Harvard Medical School, and fascia science has exploded since. It’s now recognized as its own organ system — the largest sensory organ in the body after the skin.

A quick way to picture it: imagine wearing a full-body catsuit made of wet silk under your skin. Every time you move your arm, that catsuit shifts from your shoulder down into your hip on the opposite side. Every time you slouch at your desk for three hours, the catsuit starts to memorize that shape. Every time you dehydrate, skip sleep, or swing through a stress week, the catsuit gets a little tighter. That’s fascia. That’s what we’re working with.

The Three Types of Fascia and Where You’ll Feel Them

Not all fascia is the same. Anatomists usually break it into three main categories, and knowing which one is giving you trouble helps you pick the right intervention.

Superficial fascia sits just below your skin. It holds your fat, houses a lot of your sensory nerves, and is the layer that feels “thick” or “cottage-cheesy” when cellulite shows up. It’s also where you tend to feel that tender-to-the-touch sensation on the outer thighs, hips, and lower abdomen that many midlife women describe.

Deep fascia wraps your muscles individually and in groups. This is the layer that gets tight in your IT band, your plantar fascia under the foot, your upper traps, and the thoracolumbar fascia across your low back. When you say “my low back is stiff,” the culprit is often deep fascia, not the muscle underneath it. Deep fascia is where most myofascial release work targets.

Visceral fascia wraps your organs — your gut, your uterus, your lungs, your heart. It’s the layer that matters after abdominal surgery, after C-sections, after endometriosis, and after chronic gut inflammation. Visceral fascial restrictions can pull on your posture and your breathing from the inside out, which is why specialized visceral manipulation therapists exist.

The three layers are supposed to glide past each other. When they don’t, you get referred pain, odd posture, and that “something’s not right but I can’t describe it” feeling. Good fascia work addresses the layer that’s actually stuck — which is why a foam roller on your outer thigh doesn’t fix a problem that’s rooted in your inner pelvis.

Why Fascia Matters More for Women Over 40

Here’s where it gets personal for midlife women. Estrogen matters for fascia — a lot. Estrogen helps regulate collagen production, hyaluronic acid content in the ground substance, and tissue hydration. As estrogen drops through perimenopause and into menopause, fascia loses some of its slip and spring. The tissue gets drier, stiffer, and slower to recover from daily mechanical stress. This is the same reason your skin gets thinner and your joints feel creakier — it’s all connective tissue, and it all responds to estrogen.

Research published in peer-reviewed journals like Climacteric and the British Journal of Sports Medicine has documented that women in perimenopause and menopause experience measurable changes in tendon stiffness, ligament laxity, and collagen turnover. One study found postmenopausal women can lose up to 30% of their skin collagen in the first five years after menopause. That collagen loss is not limited to skin — it’s body-wide. Your fascia loses density the same way your skin does, and the result is a tissue that doesn’t transmit force the way it used to. You feel weaker in your workouts even though your muscle mass hasn’t changed much. You feel more “thuddy” when you run or jump. You wake up stiff. You bruise more easily. All of it traces partly to changes in connective tissue.

On top of the hormonal changes, midlife women also tend to be in the life phase with the most seated time — desks, cars, phones, the endless evening scroll. Fascia is use-it-or-lose-it tissue. When you hold the same shape for hours at a time, fascia remodels to reinforce that shape. If you sit 10 hours a day and sleep 8, that’s 18 hours of hip-flexor-short, thoracic-rounded fascia reinforcement every day. No wonder it’s stuck.

The good news is that fascia also remodels toward health — and it does so relatively quickly. A study in the Journal of Bodywork and Movement Therapies showed measurable tissue changes after just two weeks of consistent self-myofascial release. Your fascia listens. If you’re curious about the broader hormonal shifts making all of this worse, we’ve written a whole piece on 20 signs of perimenopause and what to do about them, and it pairs really well with what we’re covering here.

What Healthy Fascia Feels Like vs. Fascia Dysfunction

Healthy fascia feels slippery, springy, and springy again. When you push into a healthy muscle, your fingers sink in and the tissue responds like a slightly firm marshmallow — it gives, it springs back, it doesn’t shout at you. You can twist and bend without hearing a bone concerto. You wake up feeling like the same body you went to bed with.

Dysfunctional fascia feels like a rope that’s been left out in the rain and then dried in the sun. It’s hard, it’s knotty, and it tethers things together that shouldn’t be tethered. Common signs: pain that moves around (“my shoulder hurt yesterday, today it’s my hip”), morning stiffness that takes more than 10 minutes to work out of, a feeling that you “can’t get a full breath,” pulls and pinches when you rotate, tender spots that hurt when you press even lightly, and that feeling of walking in a body you don’t quite recognize. If that’s you — this article is for you.

Fascia dysfunction isn’t the same thing as an injury. You can have stuck fascia without a torn anything, and the X-ray will come back clean. That’s a huge piece of why so many midlife women get brushed off at the doctor’s office when they describe stiffness, aches, and mobility issues. The structures being measured look fine. The soft tissue web connecting those structures is where the problem actually lives.

Free 28-Day Fascia Reset Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Causes Fascia to Get Stuck, Tight or Inflamed in Midlife

Seven things drive most fascial dysfunction, and most midlife women have at least four of them at any given time.

Dehydration. Fascia is 70% water. When you’re chronically under-hydrated (and most people are, because coffee and wine and “I’ll drink water later” are powerful), the ground substance thickens, hyaluronic acid loses its lubricating effect, and tissue layers start gluing to each other.

Sustained posture. Sitting, driving, typing, scrolling. Fascia remodels toward whatever shape you hold the longest.

Chronic inflammation. Fascia responds to systemic inflammation the same way skin does — it thickens, it stiffens, it gets tender. Diet plays a huge role here. This is also why an anti-inflammatory eating style matters for fascia health. We go deep on exactly how to build that in the fundamentals of a macro diet for women over 50.

Stress and shallow breathing. Your diaphragm is fascial tissue, and when you breathe into the top third of your lungs for weeks on end because your nervous system is in fight-or-flight, the entire diaphragmatic and pelvic fascial network tightens.

Poor sleep. Fascia remodels during deep sleep. Menopausal sleep disruption means less fascia repair.

Low estrogen. Covered above — the hormonal layer underneath all of it.

Low-grade collagen and protein intake. You cannot build connective tissue without the raw materials. Most women over 40 are under-eating protein, which limits the amino acid building blocks their fascia needs.

The protein piece is huge. Before you go buy a tool, make sure you’re eating enough. You can get a free, personalized macro target in about three minutes with our free macro calculator — it’ll give you your protein floor and a sensible carb/fat split for midlife metabolism. Fascia cannot rebuild without fuel.

The Science of Self-Myofascial Release (What Rolling Actually Does)

For years, foam rolling was explained with a handwavy “it breaks up adhesions.” That’s not really what happens, and the better explanation is more interesting.

Research, including work summarized in the British Journal of Sports Medicine by Zügel and colleagues in 2018, suggests that self-myofascial release works through several mechanisms at once. First, it mechanically squeezes the tissue, which pushes water and inflammatory metabolites out and allows fresh interstitial fluid to flow back in — basically a sponge effect. Second, it stimulates the dense network of mechanoreceptors embedded in fascia, which sends a “calm down” signal up to the central nervous system, reducing protective muscle tension. Third, sustained pressure on a restricted spot appears to trigger piezoelectric changes in collagen fibers that help tissue reorganize. Fourth, it improves local blood flow for several minutes after you stop, which supports tissue repair.

What rolling does NOT do: physically “break” adhesions. Your fascia is strong enough to survive being run over by a car. You are not going to tear it with a foam roller. What you’re doing is communicating with your nervous system and rehydrating the tissue.

This is why “release” works better when it’s slow, sustained, and breath-paced. Ten seconds of rolling at warp speed does almost nothing. Sixty to ninety seconds of sustained pressure on a tender spot, with long slow exhales, does a lot. That’s the dosage most of the research supports.

7 Ways to Keep Your Fascia Healthy in Midlife

This is the part most women are looking for, so here’s the honest, science-informed list.

1. Drink water like it’s a non-negotiable.

Half your body weight in ounces is a useful starting point (so a 150-lb woman targets 75 oz). Caffeine and alcohol don’t count. If you want a measurable fascial-hydration boost, add a pinch of salt and a squeeze of lemon to your morning water.

2. Move in multiple directions every day.

Fascia doesn’t just want you to walk in a straight line. It wants rotation, side bends, reaches, squats, and hinges. A five-minute “spine spa” in the morning — cat-cow, thread-the-needle, side bends, hip circles — does more for your fascia than a single 60-minute workout three days later.

3. Lift heavy things.

This is non-negotiable for midlife women. Strength training builds the tensioned load that healthy fascia needs to stay organized. If you haven’t started lifting yet, it’s the single best thing you can do in your 40s, 50s, and 60s.

4. Eat enough protein and support collagen synthesis.

Aim for roughly 0.7 to 1 gram of protein per pound of goal body weight, spread across 3 to 4 meals. Vitamin C, zinc, and copper support collagen assembly. If you want to go further, collagen peptides are something we’ve written about in depth — they show up consistently in midlife women’s routines for a reason.

5. Breathe into your belly for five minutes a day.

Diaphragmatic breathing releases fascial tension through the core, pelvis, and neck simultaneously. Five minutes, box breathing (4-4-4-4), hand on belly, eyes closed. Unglamorous. Powerful.

6. Use self-myofascial release 3 to 5 times a week.

Foam roller, massage ball, or a fascia tool like the FasciaBlaster. 10 to 15 minutes on whatever feels stuck. Go slow. Breathe out on tender spots. We’ll get into tools in the next section.

7. Sleep 7 to 9 hours.

Fascia repairs during deep sleep, which menopause tends to disrupt. Prioritize sleep hygiene: cool, dark, off screens, magnesium if helpful. If your sleep is a mess because of hot flashes and waking at 3 a.m., that’s its own conversation and it’s one we’ve had in our post on reversing aging in midlife women.

Fascia Tools: What Works and What’s Worth Skipping

Walk into any Target and you’ll see a wall of fascia tools. Here’s the short version of what actually works for most midlife women.

Foam roller.

The gateway tool. Dense, high-quality foam rollers (not the soft white gym ones) are excellent for large muscle groups — quads, glutes, lats, upper back. Cheap, durable, and enough for most people starting out.

Massage balls.

Lacrosse balls, peanut-shaped double balls, and soft therapy balls reach places a foam roller can’t — deep into the glutes, between the shoulder blades, along the plantar fascia of the foot. Higher precision, higher intensity.

Percussion guns.

Great for warm-ups and for specific muscle spots. Not ideal for fascia work specifically because the duration on any one spot tends to be too short to get the full nervous-system “release” effect. Useful, but not the whole answer.

Fascia tools with a hard shaft and knobs or blades.

This is the category that includes the FasciaBlaster. These tools let you reach around curves, apply targeted pressure to specific fibers, and work the layers between muscle groups in a way that a round foam roller can’t. The learning curve is steeper, and you want to start gently, but women who commit to using one for 10 minutes a day report changes in how their bodies feel within a few weeks. The FasciaBlaster we carry is the same tool I personally use on my outer thighs, glute-hamstring junction, and the stubborn IT band area — the spots that a foam roller just can’t get into. If you’re going to invest in one fascia tool beyond a basic roller, this is the one I’d pick.

A word of caution: fascia work should feel like productive discomfort, not like punishment. Bruising, trembling, or pain that lingers for days after is a sign you went too hard. Easy does it. Consistency beats intensity every single time.

Free 28-Day Fascia Reset Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

The Fascia-Hormone Connection You Never Hear About

Here’s something rarely covered in a mainstream health article. Your fascia and your hormones talk to each other in both directions.

Estrogen regulates collagen synthesis and hyaluronic acid density in fascia. Low estrogen makes fascia drier and stiffer. But fascia also influences hormones through the nervous system. Chronic fascial tension activates sympathetic (fight-or-flight) signaling, which raises cortisol, which impairs estrogen and progesterone balance, which further dries the fascia. It’s a loop. One that works against you when nothing is addressed.

This is part of why women who start regular myofascial release work in perimenopause often report a surprising side effect: better sleep, fewer hot flashes, and calmer periods. They didn’t change their hormone therapy. They changed their nervous system input by changing the information their fascia was sending upstream. It’s one of the most underappreciated tools in the midlife toolkit, and it costs nothing more than 10 minutes and a foam roller.

If the weight-and-shape changes that come with perimenopause are part of what’s driving you to read an article like this, I’d also point you to our deep dive on perimenopause weight gain — there’s a lot of crossover.

When to See a Professional for Myofascial Work

Self-care is powerful but not unlimited. There are times to hand the work to a trained set of hands. Book a professional if you have pain that’s been present for more than six weeks without changing, if you’re dealing with scar tissue from surgery (C-section, abdominal, pelvic), if you have a specific injury like plantar fasciitis that isn’t responding to self-care, or if you suspect visceral fascia is involved (chronic gut issues, post-childbirth pelvic pain, endometriosis).

Good providers to look for: a licensed physical therapist trained in myofascial release (John F. Barnes method is one of the most well-known), a certified manual therapist, a structural integration practitioner (Rolfing-style work), or a skilled sports massage therapist who specializes in connective tissue. A single session can sometimes unlock something you’ve been self-rolling for months. Often, the right pattern is a handful of professional sessions to reset, then self-care to maintain.

If you want a more personalized plan that ties fascia, strength, nutrition, and hormones together, that’s the exact thing we build inside our 1:1 fitness and nutrition coaching program. Some women prefer to learn it hands-on in a group setting, and our women’s wellness retreats fold mobility, fascia work, strength training, and anti-inflammatory eating into a single reset week. Either way, you don’t have to figure it out alone.

Frequently Asked Questions About Fascia for Women Over 40

Is fascia the same as connective tissue?

Fascia is a type of connective tissue. Connective tissue is the broader category. It includes bones, cartilage, blood, tendons, ligaments, and fascia. Fascia is specifically the fibrous, collagen-rich sheeting that wraps and connects the other structures. When someone says “connective tissue” casually, they often mean fascia.

Can you feel fascia pain separately from muscle pain?

Yes, once you know what to listen for. Fascial pain tends to be diffuse (“my whole leg feels tight”), migrating (“it was my hip yesterday and my shoulder today”), tender to light pressure across a broad area rather than in one pinpoint spot, and often worse after periods of stillness than after movement. Muscle pain is more localized, tends to have a clearer cause (a specific workout or activity), and often improves with rest. Many midlife pains are a blend of the two.

Does hormone replacement therapy (HRT) help fascia?

It can. Because estrogen supports collagen synthesis and fascial hydration, women on HRT often report less morning stiffness, fewer aches, and better skin quality. HRT is a personal medical decision that should be made with a qualified menopause provider. What we can say is that the estrogen-collagen-fascia link is well-documented in the research literature, and many women feel it in their bodies when their hormones stabilize.

How long does it take to feel a difference after starting fascia work?

Most women notice some change within two weeks of daily 10-minute sessions. Lss morning stiffness, better range of motion, a subtle feeling of “more slip” in the body. Bigger changes in chronic patterns (tight IT bands, stuck shoulders, restricted hips) typically take 6 to 12 weeks of consistent work. Fascia remodels, but it remodels on its own timeline, not yours.

Is cellulite a fascia problem?

Partly. Cellulite involves superficial fascia, fat cells, and circulation in the layer just beneath the skin. No topical cream is going to fix it because the structure lives too deep. Fascia work, strength training, adequate protein, and hydration all influence the tissue structure that creates the cellulite appearance. Expect subtle improvements, not miracles.

Can I do too much fascia work?

Yes. Over-rolling can leave you sore, bruised, and inflamed, which is the opposite of what you want. The sweet spot is 10 to 20 minutes a day, slow and breath-paced, on tissue that feels productive-uncomfortable rather than painful. If you’re bruising, back off.

What should I eat to support my fascia?

Enough protein (0.7 to 1 g per pound of goal body weight), plenty of vitamin C (bell peppers, citrus, strawberries), foods rich in collagen-building amino acids (bone broth, eggs, fish skin), anti-inflammatory fats (olive oil, fatty fish, walnuts), and 2 to 3 liters of water a day. A Mediterranean-style pattern is basically a fascia-friendly eating pattern. If you want a whole book of recipes that hit exactly this nutritional profile, The Macro Miracle Mediterranean Cookbook was built for this.

Does stretching work the same way as myofascial release?

Not quite. Traditional static stretching lengthens muscle and some fascia, but it doesn’t hydrate the tissue or address the sticky spots between layers. Myofascial release addresses the layers themselves and the nervous-system input. The combination of both — stretch plus release — is what most mobility research supports as the gold standard.

Can supplements help fascia health?

Some can. Collagen peptides (10 to 20 g per day) paired with vitamin C have research support for supporting connective-tissue synthesis. Hyaluronic acid supplementation has more mixed evidence but shows promise for joint and skin hydration. Magnesium helps with muscle-fascia interaction and sleep quality. You can browse our curated selection of vitamins and supplements for midlife women if you want somewhere to start — everything there was chosen specifically with women over 40 in mind.

Free 28-Day Fascia Reset Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

The Takeaway

Fascia is the body-wide communicator most of us were never taught to listen to. In your 40s, 50s, and 60s, it becomes impossible to ignore. Your hormones, your activity level, and your collagen supply all conspire to stiffen it up. The fix isn’t complicated. Hydrate, move in multiple directions, lift heavy, eat enough protein, roll daily, breathe deeply, sleep well, and consider a targeted fascia tool for the spots your foam roller can’t reach. Do those things for 90 days and the body you wake up in will be different in ways you can feel.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.

Sources and References

  1. Langevin HM. Connective tissue: a body-wide signaling network? Medical Hypotheses. 2006;66(6):1074-1077. PubMed
  2. Schleip R, Jäger H, Klingler W. What is ‘fascia’? A review of different nomenclatures. Journal of Bodywork and Movement Therapies. 2012;16(4):496-502. DOI
  3. Zügel M, Maganaris CN, Wilke J, et al. Fascial tissue research in sports medicine: from molecules to tissue adaptation, injury and diagnostics. British Journal of Sports Medicine. 2018;52:1497-1506. BJSM
  4. Stecco C, Sfriso MM, Porzionato A, et al. Microscopic anatomy of the visceral fasciae. Journal of Anatomy. 2017;231(1):121-128. PubMed
  5. Brincat M, Kabalan S, Studd JW, et al. A study of the decrease of skin collagen content, skin thickness, and bone mass in the postmenopausal woman. Obstetrics & Gynecology. 1987;70(6):840-845. PubMed
  6. Wilke J, Krause F, Vogt L, Banzer W. What is evidence-based about myofascial chains? A systematic review. Archives of Physical Medicine and Rehabilitation. 2016;97(3):454-461. PubMed
  7. Ahmed W, Kulikowska M, Ahlmann T, et al. A comparative multi-site and whole-body assessment of fascia in the horse. Journal of Anatomy. 2019;235(6):1064-1077.
  8. Behm DG, Wilke J. Do self-myofascial release devices release myofascia? Rolling mechanisms: a narrative review. Sports Medicine. 2019;49(8):1173-1181. PubMed
  9. Hotta K, Behnke BJ, Arjmandi B, et al. Daily muscle stretching enhances blood flow, endothelial function, capillarity, vascular volume and connectivity in aged skeletal muscle. Journal of Physiology. 2018;596(10):1903-1917.
  10. North American Menopause Society. The 2022 hormone therapy position statement. Menopause. 2022;29(7):767-794.
  11. Proksch E, Segger D, Degwert J, et al. Oral supplementation of specific collagen peptides has beneficial effects on human skin physiology. Skin Pharmacology and Physiology. 2014;27(1):47-55.
  12. Bordoni B, Zanier E. Clinical and symptomatological reflections: the fascial system. Journal of Multidisciplinary Healthcare. 2014;7:401-411.