Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

The Nordic Fascia Release Method: What Midlife Women Should Know Before Booking a Session or Buying the Tools

The Nordic Fascia Release Method has emerged from the broader Scandinavian wellness tradition that includes long-standing engagement with cold exposure, sauna, massage traditions, and various body-based practices. In its contemporary form, the method combines specific myofascial manual techniques with the use of specialized wooden or ceramic tools designed to apply sustained pressure to fascial tissues. Certified practitioners in various parts of the world (concentrated primarily in Scandinavia, with expanding presence in North America and other regions) offer sessions using the method, and the developers also sell tools and training programs.

Important: Fascia bodywork including the Nordic Fascia Release Method is generally safe for most healthy midlife women. Certain conditions warrant medical clearance before starting including recent surgery, active injuries, cardiovascular concerns, and various other specific situations. Discuss with your healthcare provider if you have any concerns. This article is educational and does not constitute medical advice.

What Is the Nordic Fascia Release Method?

The Nordic Fascia Release Method is a specific proprietary bodywork approach. The general publicly available description of what the method involves helps midlife women understand what they would encounter in a session or in training.
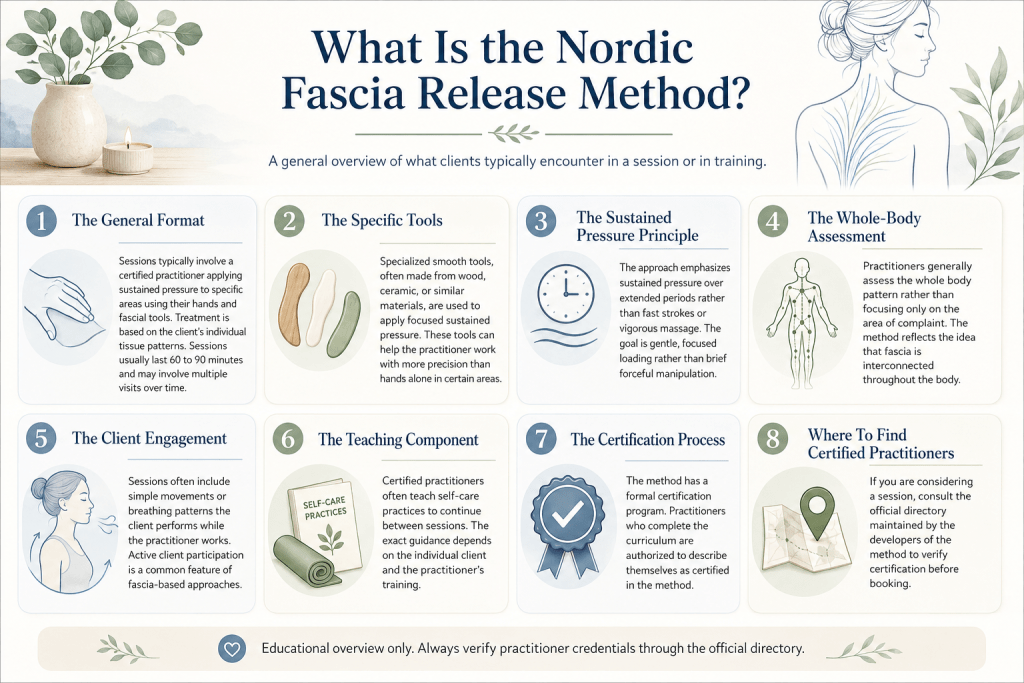
Nordic Fascia Release Method overview infographic.
  • The general format: Sessions typically involve a certified practitioner applying sustained pressure to specific areas of the client’s body using their hands and specific tools designed for fascial work. The practitioner works through specific tissue patterns based on the assessment of the individual client. Sessions typically last 60 to 90 minutes and often involve multiple visits over time for cumulative benefit.
  • The specific tools: The method uses specialized smooth tools (often made from wood, ceramic, or similar materials) designed to apply focused sustained pressure to fascial tissues. The specific design and use of these tools is part of the proprietary teaching. In general terms, the tools allow the practitioner to work with more focused pressure than hands alone can provide in certain areas.
  • The sustained pressure principle: The general approach emphasizes sustained pressure over extended periods rather than fast strokes or vigorous massage. This sustained approach aligns with the broader fascia research showing that fascia responds to sustained gentle loading over minutes rather than to brief vigorous manipulation.
  • The whole-body assessment: Practitioners generally assess the client’s whole body pattern rather than focusing only on the specific area of complaint. Fascia is interconnected, and the general Nordic approach reflects this interconnection by treating the body as a whole.
  • The client engagement: Sessions often include specific movements or breathing patterns the client is asked to perform while the practitioner works. This active engagement is a general feature of many fascia approaches.
  • The teaching component: Certified practitioners in the method often teach clients specific self-care practices to continue between sessions. The specific practices taught depend on the individual and on the practitioner’s training.
  • The certification process: The Nordic Fascia Release Method has a specific certification program for practitioners. Trained practitioners have completed the specific curriculum and are authorized to represent themselves as certified in the method. Uncertified practitioners who describe their work using this specific method name are misrepresenting their qualifications.
  • Where to find certified practitioners: The developers of the method maintain a directory of certified practitioners. If you are considering booking a session using this specific method, consult the official directory to verify certification.

What Is the Scandinavian Wellness Tradition Context?

Understanding the broader tradition the Nordic Fascia Release Method emerges from helps contextualize the approach.

  • The general Scandinavian wellness lineage: Nordic countries have long-standing wellness traditions including sauna, cold water immersion, various massage traditions, outdoor movement, and specific approaches to body work. These traditions are integrated into daily life in ways that Western wellness cultures often are not.
  • The specific relationship to touch: Scandinavian bodywork traditions often emphasize deliberate touch as a specific therapeutic modality. Various forms of Swedish massage, Finnish massage traditions, and specific modern developments have contributed to this broader tradition.
  • The nature-based framework: Scandinavian wellness often includes explicit connection to nature (outdoor time, natural elements, seasonal awareness) as part of the general health framework. Fascia bodywork in this tradition often reflects this broader nature-connected framing.
  • The specific relationship to seasonality: Scandinavian traditions have strong seasonal awareness that shows up in wellness practices. Winter and summer practices differ. This seasonal awareness sometimes shows up in how bodywork is practiced or discussed.
  • The modern development: Various contemporary Scandinavian practitioners have developed specific modern approaches that combine traditional lineage with contemporary understanding of fascia and connective tissue. The Nordic Fascia Release Method is one specific example of this modern development.
  • The cultural context matters: For practitioners and clients coming from outside the Scandinavian cultural context, understanding the broader tradition helps interpret the specific practices. The method is not just a set of techniques but reflects a broader cultural approach to body work.
  • The specific caution about cultural adoption: As with any cultural tradition adopted by wellness industries outside the source culture, there are specific concerns about cultural adoption, oversimplification, and commercial repackaging. Approach any specific method with appropriate cultural humility.
  • The specific value of engaging with the source tradition: For those seriously interested in this specific method, engaging with practitioners trained in the source lineage produces different value than working with wellness-industry practitioners who have adopted vocabulary without the training.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Why Are Midlife Women Drawn to This Method Now?

The specific interest in the Nordic Fascia Release Method among midlife women reflects broader patterns worth understanding.

Growing Awareness and Menopause-Related Interest

  • The fascia awareness moment: Fascia has moved from obscure anatomical detail to mainstream wellness topic over the last several years. Midlife women who are experiencing the specific aches and stiffness of perimenopause and menopause are often actively searching for fascia-focused approaches.
  • The specific menopause fascia connection: The specific fascia changes of the perimenopause and menopause transition drive real symptoms that fascia-focused bodywork approaches can help address. Midlife women searching for solutions to these symptoms often find fascia methods.

Novelty, Tools, and Deeper Engagement

  • The high perceived novelty: The Nordic origin and specific tool-based approach differentiates the method from more familiar bodywork forms. This differentiation attracts women who have tried various other approaches without the results they hoped for.
  • The specific tool appeal: Purchasing specific tools appeals to the same impulses that drive other wellness product purchases. The tools become both functional equipment and identifying markers of engagement with the method.
  • The retreat and training appeal: Beyond individual sessions, the method offers immersive training experiences that appeal to women interested in deeper engagement or in becoming practitioners themselves.
  • The cultural travel appeal: Some midlife women travel to Scandinavia to experience the method in its source culture. This travel appeal adds to the general attraction.

Influencer Visibility and the Need for Caution

  • The influencer amplification: The Nordic Fascia Release Method has been promoted by various wellness influencers and podcasters, which has substantially increased visibility. This amplification is neither endorsement nor criticism of the method itself but explains its current visibility.
  • The specific caution about influencer content: Wellness-influencer content about the method varies widely in accuracy and depth. Some content is thoughtful engagement with the method’s actual principles. Other content is superficial marketing that may not reflect what the method involves. Evaluate influencer content with the same critical thinking you would apply to any other wellness marketing.

“The specific question I hear from coaching clients about the Nordic Fascia Release Method is whether it is worth the specific investment of time and money required for either sessions or training. My honest answer depends on the specific client’s situation. For a woman who has already installed the foundational fascia framework (regular movement, appropriate nutrition, quality sleep, nervous system regulation, and some form of consistent self-care fascia practice) and who wants to explore deeper professional support, working with a certified practitioner in this or any specific credentialed fascia method can add meaningful value. For a woman who has not yet installed the foundational framework and who is looking for a specific method to substitute for that foundation, no proprietary bodywork method will produce the outcomes she hopes for. The method works best as a specific addition to a solid foundation, not as a replacement for the foundation. That framing is the specific consideration I recommend to clients evaluating this or any other specific proprietary approach.”

Terry Tateossian, Founder of The House of Rose

Which General Principles Align With Fascia Research?

Several of the general principles that the Nordic Fascia Release Method emphasizes align well with the broader fascia research base.

  • Sustained pressure over time: The general principle of applying sustained pressure over minutes rather than brief vigorous manipulation aligns with the broader fascia research. Fascia responds to sustained loading over 90 seconds to several minutes more than to short strokes. This is a general principle that appears across many effective fascia approaches.
  • Whole-body pattern assessment: The general principle of assessing the whole body rather than treating only the site of symptoms aligns with the fascia research showing that fascial restrictions in one area often refer symptoms to distant sites. Treating fascia locally without considering the whole pattern often produces incomplete results.
  • The client engagement component: The general principle of involving the client actively during the session (through breathing, specific movements, or attention) aligns with the research on the neural component of fascial release. Fascia is densely innervated and responds partly through neurological rather than purely mechanical mechanisms.
  • The interconnection framework: The general acknowledgment that fascia is a connected system rather than a set of separate structures aligns with modern understanding of fascial anatomy. The specific fascial lines that connect distant body regions are well-documented anatomically.
  • The self-care teaching component: The general practice of teaching clients specific self-care to continue between sessions aligns with the research showing that consistent daily practice produces better outcomes than occasional intensive sessions.
  • The tool-based focused pressure: The general use of tools to apply focused sustained pressure to specific areas aligns with the broader self-myofascial release research showing that focused pressure produces measurable improvements in tissue mobility and range of motion.
  • The specific caveat about proprietary claims: While the general principles align with research, specific proprietary claims about how a particular method uniquely accomplishes these effects may exceed what the general research supports. The principles are broadly supported. Specific proprietary claims require separate evaluation.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Does the Broader Fascia Research Support?

The broader research on fascia release provides the context for evaluating any specific method including the Nordic approach.

  • Self-myofascial release research: Multiple systematic reviews and meta-analyses document that self-myofascial release techniques using foam rollers, balls, and similar tools produce measurable improvements in range of motion, reduce delayed onset muscle soreness, and support recovery. Effect sizes are modest but consistent.
  • Manual fascia therapy research: Research on manual myofascial release performed by trained practitioners documents improvements in pain, function, and range of motion across various conditions. The specific proprietary methods vary in their evidence bases.
  • Fascial mobility research: Studies of fascial mobility using various imaging techniques document that fascia can be affected by manual intervention in ways that produce measurable tissue changes. The specific mechanisms include hydration changes, hyaluronic acid effects, and mechanical remodeling over time.
  • The sustained pressure research: Studies of sustained pressure durations document that meaningful fascial response typically requires at least 90 seconds of sustained pressure on a specific area. Longer holds produce more response up to a point.
  • The whole-body versus local research: Studies comparing whole-body versus locally-focused fascial interventions generally support the whole-body approach for outcomes beyond immediate local pain reduction.
  • The self-care versus practitioner-only research: Research consistently supports the value of daily self-care practice alongside or instead of periodic practitioner sessions. Self-care practice produces meaningful cumulative benefits.
  • The consistency research: Consistent daily practice over weeks produces meaningfully better outcomes than occasional intensive sessions. This applies to both self-care practice and to combined self-care plus practitioner sessions.
  • What the research does not clearly show: The research generally does not clearly demonstrate that one specific proprietary method produces uniquely better outcomes than well-designed alternative approaches. Various methods produce broadly similar outcomes when practiced consistently. This does not mean specific methods have no value. It means that specific proprietary claims of unique superiority typically exceed what the comparative research supports.

Where Do Marketing Claims Sometimes Exceed the Evidence?

Being honest about where marketing claims sometimes exceed what evidence supports helps midlife women evaluate any specific method including the Nordic approach.
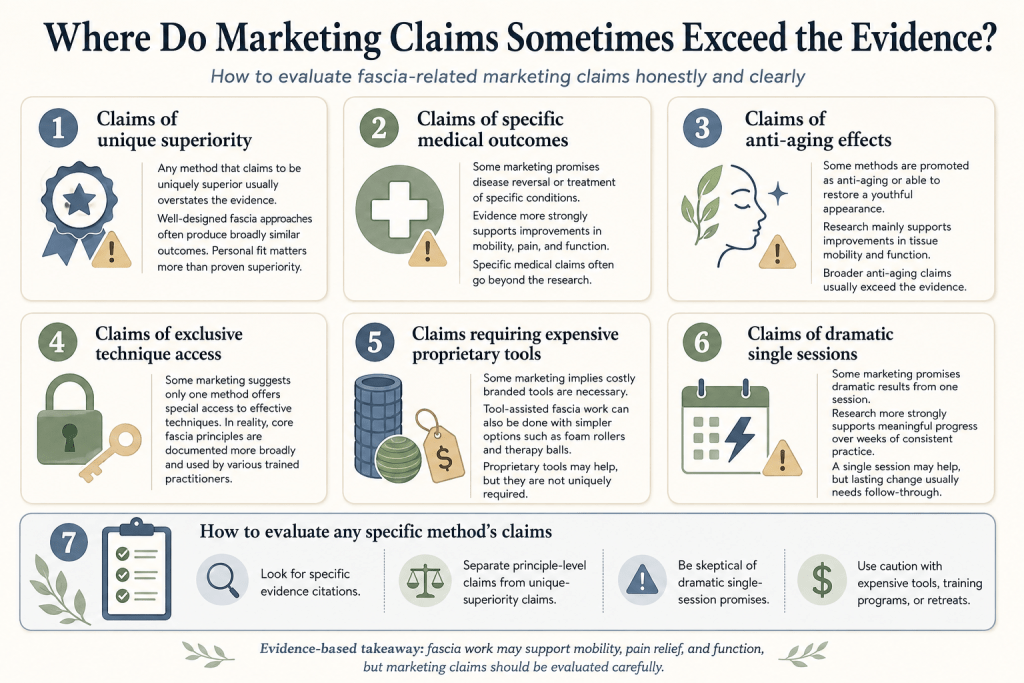
Marketing claims versus fascia evidence infographic.
  • Claims of unique superiority: Any specific method that claims to be uniquely superior to alternatives typically overstates what comparative research demonstrates. Various well-designed fascia approaches produce broadly similar outcomes. The specific choice among them depends on personal fit rather than on demonstrated superiority.
  • Claims of specific medical outcomes: Some marketing suggests that specific fascia methods produce specific medical outcomes (reversing specific diseases, treating specific conditions). The general fascia research supports improvements in mobility, pain, and function. Claims of specific medical treatment outcomes usually exceed what evidence supports.
  • Claims of anti-aging effects: Some marketing suggests that specific fascia methods produce anti-aging effects, restore youthful appearance, or reverse age-related changes. The general research supports specific improvements in tissue mobility and function. Broader anti-aging claims typically exceed what evidence supports.
  • Claims of exclusive technique access: Some marketing frames specific methods as offering exclusive technique access that is not available elsewhere. The general principles of effective fascia work are well-documented in the broader research and are available through various trained practitioners.
  • Claims requiring expensive proprietary tools: Some marketing suggests that specific proprietary tools are required for effective fascia work. The general principles of tool-assisted fascia work can be applied with various tools including inexpensive foam rollers and therapy balls. Specific proprietary tools may have specific advantages but are typically not uniquely required.
  • Claims of dramatic single sessions: Some marketing suggests that single sessions produce dramatic outcomes. The general research supports meaningful improvements over weeks of consistent practice. Single sessions can produce immediate subjective changes but typically require follow-through for lasting effects.
  • How to evaluate any specific method’s claims: Look for specific evidence citations. Distinguish between principle-level claims (which are often supported) and unique-superiority claims (which are typically not). Be skeptical of dramatic single-session promises. Approach expensive training programs, tools, or retreats with appropriate caution.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Can You Expect From a Session?

For midlife women considering booking a session with a certified practitioner in the Nordic Fascia Release Method, understanding what to expect helps set appropriate expectations.

Before and During the Session

The first part of the process focuses on understanding your needs and identifying the areas that may require the most attention.

  • The intake: A first session typically begins with a thorough intake including your specific health history, current symptoms, previous injuries, current medications, and specific goals for the work. This intake is a normal part of any competent bodywork practice.
  • The assessment: The practitioner typically assesses your specific body patterns through observation and palpation. This assessment guides where and how the practitioner will work during the session.
  • The session itself: Sessions typically last 60 to 90 minutes. The practitioner works through various areas using their hands and specific tools. Sensation varies from mild pressure to occasionally intense sensation during focused work on specific restricted areas.

What You May Feel During and After the Work

Fascia-focused bodywork can involve physical and emotional sensations that may feel different from those experienced during familiar forms of massage.

  • The specific sensations: Fascia work often produces distinctive sensations that differ from familiar massage. These can include specific burning, tingling, deep pressure, occasional sharp releases, and various other sensations. Communicate with your practitioner about specific sensations that concern you.
  • The emotional component: Fascia work often produces emotional responses including spontaneous tears, feelings of grief or relief, and various other emotional experiences. This is a documented phenomenon in body-based practice and is generally considered a healthy sign of stored tension releasing. Practitioners trained in fascia work are typically prepared to support these responses appropriately.

Follow-Up, Frequency, and Investment

The work usually extends beyond the session itself through self-care, repeated sessions, and ongoing evaluation of your progress.

  • The homework: Practitioners typically provide specific self-care recommendations to continue between sessions. Follow-through with the self-care matters as much as the session itself for producing lasting results.
  • The frequency recommendation: Practitioners typically recommend specific frequency depending on your situation. Common patterns include weekly sessions for the first month or two followed by monthly maintenance sessions.
  • The specific investment: Sessions typically cost $150 to $300 depending on the practitioner and location, with initial packages of multiple sessions often recommended.

Setting Realistic Expectations

Results can vary from person to person, so it is important to evaluate how your body responds over time rather than expecting immediate transformation.

  • Realistic expectations: Meaningful improvement typically appears over multiple sessions combined with consistent self-care practice. Immediate transformation is rare. Sustained improvement over months of consistent engagement is common.
  • When to reconsider: If sessions produce persistent pain, if you feel the practitioner is not listening to your feedback, if the recommendations feel excessive or expensive, or if the specific approach does not fit your body, consider changing practitioners or approaches.

What Are the Tools and Their General Functions?

The specific tools used in the Nordic Fascia Release Method deserve some discussion because they are a distinctive feature of the approach.

  • The general purpose: Tools in fascia work generally allow the practitioner (or self-practitioner) to apply focused sustained pressure to specific areas in ways that hands alone cannot easily achieve. The specific shape, material, and design of tools varies by tradition.
  • The Nordic-style tools: Tools used in the Nordic Fascia Release Method are typically smooth wooden or ceramic pieces designed for fascial work. The specific designs are part of the proprietary offering of the method.
  • The specific tool categories: Various tools exist for different specific purposes including broad surface tools for large areas, smaller focused tools for specific spots, and tools designed for specific body regions.
  • The alternative tools available: The general principles of tool-assisted fascia work can be practiced with various alternatives including foam rollers, therapy balls (tennis balls, lacrosse balls), massage sticks, and various other options. These alternatives are often significantly less expensive than proprietary tools.
  • The specific value of specialized tools: Well-designed specialized tools may offer specific advantages in shape, texture, or ergonomics that generic tools do not. Whether these advantages justify significant additional cost depends on the individual and the specific tools.
  • The buying question: For midlife women considering purchasing tools associated with the Nordic Fascia Release Method or any specific proprietary method, consider whether you have first established consistent practice with basic tools. If daily practice is already well-installed, upgraded tools may be worthwhile. If practice is inconsistent, better tools will not create consistency.
  • The specific caution about tool marketing: As with any wellness product, tool marketing sometimes exceeds what the tools accomplish. Basic tools produce most of the fascial benefit for most people. Specific specialty tools may offer specific advantages but are typically not uniquely required.
  • The DIY alternative: Some effective fascia tools can be made or improvised at home from various materials. Tennis balls in socks. Rolling pins for larger surfaces. Various other alternatives exist. The specific principles matter more than the specific tools.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Does the Method Compare to Other Fascia Approaches?

Placing the Nordic Fascia Release Method in the context of other fascia approaches helps midlife women make informed comparisons.

  • The general principle: Various fascia approaches share common general principles (sustained pressure, whole-body awareness, breath integration, consistent practice) while differing in specific techniques, training lineages, and cultural contexts. The general principles matter more than the specific method for most outcomes.
  • The specific choice question: The specific choice among fascia approaches depends on individual factors including personal preference, availability of trained practitioners, budget, cultural resonance, and specific goals. No single method is universally superior for all midlife women.
  • The specific value of trying multiple approaches: Some midlife women find that different approaches suit them at different times or for different specific concerns. Being open to multiple approaches often produces better long-term outcomes than rigid commitment to a single method.
  • The specific value of consistency within any approach: Whatever specific approach you choose, consistency over months and years produces the specific benefits that fascia work can deliver. Occasional engagement with the most sophisticated method produces less than consistent engagement with a simpler approach.

What Should You Know About Foam Rolling and Self-Myofascial Release?

Foam rolling is the most widely accessible fascia approach and provides useful context for comparing with proprietary methods.

Foam rolling and self-myofascial release infographic.
  • The general approach: Foam rolling uses cylindrical foam rollers of various densities to apply body weight pressure to large muscle groups and their surrounding fascia. Self-practice at home is the standard format.
  • The evidence base: The research on foam rolling is one of the more developed research bases for any fascia intervention. Multiple systematic reviews document specific benefits for range of motion, recovery, and delayed onset muscle soreness.
  • The cost accessibility: Foam rollers typically cost $15 to $50 and last for years. This is dramatically less expensive than most proprietary fascia methods.
  • The specific limitations: Foam rolling addresses large muscle groups well but is less effective for specific small areas that benefit from more focused pressure. Combining foam rolling with therapy balls addresses this limitation.
  • The specific comparison: Foam rolling and proprietary methods like the Nordic Fascia Release Method share general principles. The specific choice depends on whether the individual benefits from professional guidance and specialized tools versus self-directed practice with basic equipment.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Does Traditional Deep Tissue Massage Compare?

Traditional deep tissue massage is another familiar bodywork approach that shares some overlap with fascia work.

Approach and Evidence

  • The general approach: Deep tissue massage typically involves a trained massage therapist applying deep sustained pressure to muscles and their fascial coverings through various stroke techniques.
  • The evidence base: Massage therapy has a broad evidence base supporting various outcomes including pain reduction, stress reduction, and improved recovery.

Cost and Key Differences

  • The cost consideration: Traditional deep tissue massage typically costs $100 to $200 per session. This is often less expensive than specialty proprietary methods but represents ongoing cost.
  • The specific comparison: Traditional deep tissue massage and specialty fascia methods share general principles. Specialty methods often offer more specific tool-based work, more explicit focus on fascial rather than muscular tissue, and specific training lineages. Traditional massage offers wider practitioner availability and typically lower cost.

Who May Find It a Better Fit?

Midlife women who benefit from general therapeutic touch and stress reduction alongside targeted body work may find traditional massage a good fit. Those specifically seeking fascia-focused technical work may prefer specialty methods.

How Does Fascial Stretch Therapy Compare?

Fascial Stretch Therapy is a specific proprietary approach that focuses on assisted stretching rather than tool-based release.

  • The general approach: Fascial Stretch Therapy involves a trained practitioner passively moving the client through specific stretch patterns designed to address fascial mobility. Sessions typically use a specialized table with straps.
  • The evidence base: The specific research on Fascial Stretch Therapy is more limited than for foam rolling or general massage but generally supports improvements in range of motion and function.
  • The specific comparison: Fascial Stretch Therapy focuses on assisted movement and stretching while the Nordic Fascia Release Method emphasizes tool-based sustained pressure. Both address fascial mobility through different specific mechanisms.
  • The specific fit: Midlife women who respond well to passive stretching and movement-based work may find Fascial Stretch Therapy a good fit. Those who respond well to focused pressure work may prefer tool-based methods.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Do Yin Yoga and Sustained Postures Support Fascia?

Yin yoga is a self-practice approach that shares many principles with proprietary fascia methods.

Yin yoga and fascia support infographic.
  • The general approach: Yin yoga involves sustained holds of specific postures for 3 to 5 minutes or longer, using body weight and gravity to apply the sustained loading that fascia responds to.
  • The evidence base: Yin yoga research is emerging but generally supports improvements in flexibility, stress reduction, and various other outcomes.
  • The cost accessibility: Yin yoga can be practiced at home for free using video instruction or with modest investment in classes.
  • The specific comparison: Yin yoga shares the general principles of sustained loading with proprietary fascia methods. It works through movement patterns rather than tool-based pressure and offers self-practice rather than practitioner-based sessions.
  • The specific integration: Many midlife women benefit from combining yin yoga self-practice with periodic sessions of a specific proprietary method. The two approaches work well together.

How Do Cupping and Gua Sha Traditions Compare?

Cupping and gua sha are traditional East Asian bodywork approaches that share some overlap with fascia methods.

  • The general approach: Cupping uses suction cups applied to the skin to lift and mobilize tissues. Gua sha uses smooth-edged tools to scrape the skin, producing what the tradition considers therapeutic effects on tissue and circulation.
  • The evidence base: Both approaches have growing research bases supporting specific effects on pain, mobility, and various other outcomes.
  • The specific comparison: Traditional East Asian approaches share the general principle of tool-based tissue work with the Nordic Fascia Release Method. The specific mechanisms and cultural contexts differ.
  • The specific consideration: For midlife women interested in traditional lineage-based bodywork, exploring the East Asian traditions alongside or instead of Scandinavian traditions offers different specific experiences.
  • The cultural respect consideration: As with any traditional practice, engaging with the source lineage rather than with commercial adaptation typically produces different value.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How Should You Evaluate Practitioners?

For midlife women considering booking sessions in the Nordic Fascia Release Method or any specialty fascia approach, evaluating practitioners matters.

Check Training and Relevant Experience

  • Verify certification: For proprietary methods, verify that the practitioner is certified in the specific method they claim to practice. Consult the official directory maintained by the method developers.
  • Ask about training background: Beyond specific method certification, ask about the practitioner’s broader bodywork training and experience. Practitioners with strong general foundations often deliver better outcomes than those with only narrow specialty training.
  • Ask about experience with your specific concerns: Different practitioners have different specific areas of experience. A practitioner experienced with midlife women, menopause-related concerns, or your specific issues typically produces better outcomes than a general practitioner.

Ask About the Session and Expected Outcomes

  • Ask about session structure: A competent practitioner should be able to describe their typical session structure, intake process, and follow-up recommendations clearly. Vague answers may indicate less established practice.
  • Ask about specific outcomes and expectations: A competent practitioner should offer realistic expectations rather than dramatic promises. Be skeptical of practitioners who promise dramatic outcomes.
  • Ask about coordination with other care: A competent practitioner should support your continued relationship with your medical providers and should discourage substituting bodywork for appropriate medical care.

Consider Comfort, Trust, and Setting

  • Trust your response to the initial consultation: Beyond specific credentials, notice how you feel during the initial consultation. Do you feel heard? Do you feel comfortable with the practitioner? Do you trust their judgment? These felt responses matter.
  • Consider the setting: The physical setting should be professional, clean, and comfortable. Boundaries around the session should be clear and appropriate.

Keep Practitioner Fit in Perspective

Some practitioners in any specialty method are excellent. Others are less well-trained or less well-suited to your specific needs. Finding the right practitioner may take a few tries.

What Should You Know About Cost, Frequency, and Realistic Expectations?

Setting realistic expectations for cost, frequency, and outcomes helps midlife women evaluate whether specialty fascia methods fit their situation.

Cost and Frequency

  • The typical session cost: Certified practitioners in specialty fascia methods typically charge $150 to $300 per session. Cost varies by location, practitioner experience, and specific method.
  • The typical frequency recommendation: Weekly sessions for the first month or two followed by monthly maintenance is a common recommended pattern. Some practitioners recommend more frequent early work.

Timeline and Total Investment

  • The typical timeline for meaningful improvement: Subjective improvements often appear within the first few sessions. Meaningful cumulative improvement typically requires consistent engagement over 2 to 3 months. Sustained transformation requires ongoing practice over 6 to 12 months or more.
  • The specific total investment: For a full initial course of specialty fascia work plus monthly maintenance for a year, total investment often exceeds $3,000 to $5,000 including tools if purchased. This is a meaningful financial commitment.
  • The alternative investment: For the same total investment, a midlife woman could purchase basic self-care tools, take classes in yin yoga or tai chi, join a well-run coaching program, or attend an immersive retreat. Each of these alternatives has specific value.

Evaluating the Value

  • The specific value proposition: Specialty fascia methods deliver specific value including expert assessment, focused work you cannot easily do yourself, and structured programming. Whether this value justifies the cost depends on the individual.
  • The specific caution about escalating recommendations: Some practitioners recommend progressively more sessions, more tools, or more training. Evaluate these recommendations carefully. Not every escalation is warranted.

Compare Specialty Work With Accessible Alternatives

Before committing to expensive specialty methods, consider whether you have exhausted the value available from more accessible alternatives. Consistent daily self-care produces meaningful outcomes. Adding specialty work on top of an established foundation produces different value than substituting specialty work for foundational practice.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Who Should Consider This Method (and Who Should Not)?

Being honest about who is likely to benefit from this specific method and who may benefit more from alternatives helps midlife women make informed decisions.

Good Candidates for Exploring the Method

Good candidates for exploring the Nordic Fascia Release Method or similar specialty approaches include:

  • Midlife women who have already installed a solid foundation of daily movement, nutrition, sleep, and nervous system regulation, and who want to add specific specialty bodywork to complement the foundation.
  • Women who have tried general foam rolling and self-care fascia work and want more specialized professional support for specific persistent issues.
  • Women who have the financial resources and time for ongoing specialty sessions plus consistent self-care.
  • Women who resonate with the Scandinavian wellness tradition or with tool-based work.
  • Women who have access to a well-trained certified practitioner in their geographic area.
  • Women who want a specific structured program with an experienced practitioner.

Better Candidates for Alternative Approaches

Some women may benefit more from alternative approaches, depending on their current needs, resources, and priorities.

  • Women who have not yet installed the foundational lifestyle medicine framework. Foundation first, specialty work after.
  • Women with limited financial resources for ongoing specialty sessions. Excellent self-care outcomes are available with more accessible approaches.
  • Women who prefer self-directed practice over practitioner-based work.
  • Women whose primary need is general stress relief and touch rather than specific fascia-focused technical work. Traditional massage may fit better.
  • Women whose primary need is movement improvement rather than tissue-focused release. Yoga, tai chi, or Pilates may fit better.
  • Women who do not have access to a well-trained certified practitioner. Traveling long distances for occasional sessions typically does not produce good outcomes.
  • Women dealing with significant medical conditions that require primary medical care. Bodywork can complement but cannot substitute for appropriate medical treatment.

The Honest Self-Assessment

The specific value of this or any specialty method for you depends on your specific situation. Honest assessment of where you currently are and what would produce the biggest improvement in your specific situation helps guide the decision.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
When Should You See a Healthcare Professional?

Specialty fascia methods and any bodywork are not substitutes for appropriate medical care. Certain situations warrant professional evaluation.

  • Persistent unexplained pain: Pain that persists despite consistent bodywork warrants medical evaluation to identify underlying causes.
  • Progressive symptoms: Any progressive worsening of symptoms warrants evaluation regardless of any bodywork engagement.
  • Neurological symptoms: Numbness, weakness, radiating pain, or other neurological symptoms warrant medical evaluation.
  • Recent injuries or surgeries: Wait for medical clearance before beginning specialty bodywork after any significant injury or surgery.
  • Cardiovascular concerns: Any known cardiovascular disease warrants physician clearance before starting intensive bodywork.
  • Any concerning symptoms during sessions: Chest pain, severe dizziness, or other alarming symptoms during a bodywork session warrant immediate medical evaluation.
  • Mental health concerns: Some bodywork produces emotional responses that can be intense. If you have specific mental health concerns or trauma history, working with practitioners trained in trauma-informed approaches produces better outcomes than working with practitioners without this specific training.
  • Pregnancy: Some bodywork approaches need modification during pregnancy. Work with practitioners with prenatal training.

What Are Your Next Steps?

If you are considering the Nordic Fascia Release Method or any specialty fascia approach, here are the four next steps in order of friction.

  1. Assess your foundation. Before investing in specialty methods, honestly assess whether you have installed the foundational lifestyle medicine framework. If not, the foundation produces bigger benefits than any specialty method.
  2. Try accessible self-care first. Basic foam rolling, therapy ball work, and yin yoga home practice using free video instruction lets you experience fascia work at minimal cost.
  3. If you decide to explore specialty methods, verify practitioner credentials. For any proprietary method, verify certification through the official directory. Ask about training background and experience with midlife women.
  4. Consider an immersive women’s yoga and wellness retreat or 1:1 online coaching 

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

What is the Nordic Fascia Release Method?

The Nordic Fascia Release Method is a specific proprietary bodywork approach developed within the Scandinavian wellness tradition. Sessions typically involve a certified practitioner applying sustained pressure to specific areas of the body using their hands and specialized wooden or ceramic tools designed for fascial work. Certified practitioners work with clients through specific tissue patterns based on individual assessment.

Is the Nordic Fascia Release Method evidence-based?

The general principles the method emphasizes (sustained pressure, whole-body assessment, breath integration, client engagement) align with the broader fascia release research base. The specific proprietary techniques and specific claims of unique superiority have less specific evidence and should be evaluated with appropriate skepticism. Various well-designed fascia approaches produce broadly similar outcomes.

How much does a Nordic Fascia Release session cost?

Certified practitioners typically charge $150 to $300 per session depending on location, practitioner experience, and session length. Initial course of multiple sessions often recommended. Total investment for an initial course plus monthly maintenance can exceed $3,000 to $5,000 per year including tools if purchased.

Where can I find certified practitioners?

The developers of the method maintain an official directory of certified practitioners. If you are considering booking a session using this specific method, consult the official directory to verify certification. Uncertified practitioners representing themselves as certified in the method are misrepresenting their qualifications.

Can I learn to do this method myself?

The specific method has a certification program for practitioners. Learning to practice the specific method professionally requires completing the specific training. However, the general principles of self-care fascia work are accessible through various self-directed practices including foam rolling, therapy ball work, and yin yoga.

How does this method compare to foam rolling?

Both share the general principle of tool-assisted sustained pressure to fascia. The Nordic method offers professional guidance, specialized tools, and structured programming. Foam rolling offers self-directed practice at dramatically lower cost. Both produce meaningful outcomes with consistent practice. The specific choice depends on individual preferences and resources.

Does the Nordic method help with menopause aches and stiffness?

Fascia bodywork including the Nordic method addresses the specific fascial changes that contribute to menopause aches and stiffness. Any well-designed fascia approach can help; the specific method matters less than consistent engagement with an approach that fits you.

How often should I do fascia release?

For self-care practice, daily 10 to 15 minute sessions produce meaningful cumulative benefit. For specialty practitioner sessions, weekly for the first month or two followed by monthly maintenance is a common pattern. Consistency matters more than frequency.

Is the Nordic method safe?

For most healthy midlife women, appropriate fascia bodywork is safe. Certain conditions warrant medical clearance including recent surgery, active injuries, cardiovascular concerns, and various other specific situations. Discuss with your healthcare provider if you have concerns. Trained certified practitioners typically conduct appropriate intake to identify contraindications.

Do I need the specific tools?

The specific proprietary tools used in the method offer specific advantages in shape and design. Similar general benefits can be achieved with more accessible tools including foam rollers, therapy balls, and various other options. Whether the specialty tools justify their cost depends on individual circumstances and how established your practice is.

What are the alternatives to the Nordic method?

Alternatives with similar general principles include foam rolling, self-myofascial release with balls, traditional deep tissue massage, Fascial Stretch Therapy, yin yoga, cupping, gua sha, and various other approaches. Each has specific strengths. The best fit depends on individual preferences and specific goals.

How long before I see results?

Subjective improvements often appear within the first few sessions or first few weeks of consistent self-care. Meaningful cumulative improvement typically requires 2 to 3 months of consistent engagement. Sustained transformation requires ongoing practice over 6 to 12 months or more.

Can this method help with lymphatic drainage?

Fascia and the lymphatic system are functionally interconnected. Fascia work often produces effects on lymphatic circulation as one component of the broader effects.

Is the Nordic method better than yoga for fascia?

Neither is universally better. Yoga (particularly yin yoga) uses sustained postures and gravity to produce fascial effects through movement patterns. The Nordic method uses tool-based sustained pressure by a practitioner. Both address fascia through different mechanisms. Many midlife women benefit from combining both.

Should I take the training to become a practitioner?

The training decision depends on your specific goals. If you want to practice the method professionally, the specific certification is required. If you want deeper self-care knowledge, other more accessible training options may fit better. Evaluate the specific investment against your specific goals.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.


References

  • Schleip, R., & Müller, D. G. (2013). Training principles for fascial connective tissues: scientific foundation and suggested practical applications. Journal of Bodywork and Movement Therapies, 17(1), 103–115.
  • Stecco, C., Fede, C., Macchi, V., et al. (2018). The fasciacytes: a new cell devoted to fascial gliding regulation. Clinical Anatomy, 31(5), 667–676.
  • Stecco, C., Stern, R., Porzionato, A., et al. (2011). Hyaluronan within fascia in the etiology of myofascial pain. Surgical and Radiologic Anatomy, 33(10), 891–896.
  • Ajimsha, M. S., Al-Mudahka, N. R., & Al-Madzhar, J. A. (2015). Effectiveness of myofascial release: systematic review of randomized controlled trials. Journal of Bodywork and Movement Therapies, 19(1), 102–112.
  • Beardsley, C., & Škarabot, J. (2015). Effects of self-myofascial release: a systematic review. Journal of Bodywork and Movement Therapies, 19(4), 747–758.
  • Behm, D. G., & Wilke, J. (2019). Do self-myofascial release devices release myofascia? Rolling mechanisms: a narrative review. Sports Medicine, 49(8), 1173–1181.
  • Cheatham, S. W., Kolber, M. J., Cain, M., & Lee, M. (2015). The effects of self-myofascial release using a foam roll or roller massager on joint range of motion, muscle recovery, and performance: a systematic review. International Journal of Sports Physical Therapy, 10(6), 827–838.
  • Wiewelhove, T., Döweling, A., Schneider, C., et al. (2019). A meta-analysis of the effects of foam rolling on performance and recovery. Frontiers in Physiology, 10, 376.
  • Klingler, W., Velders, M., Hoppe, K., et al. (2014). Clinical relevance of fascial tissue and dysfunctions. Current Pain and Headache Reports, 18(8), 439.
  • Chaitow, L. (2020). Fascia as a sensory organ: implications for practice. Journal of Bodywork and Movement Therapies, 24(4), 3–4.
  • Bordoni, B., & Zanier, E. (2013). Anatomic connections of the diaphragm: influence of respiration on the body system. Journal of Multidisciplinary Healthcare, 6, 281–291.
  • Field, T. (2016). Massage therapy research review. Complementary Therapies in Clinical Practice, 24, 19–31.
  • Ernst, E. (2009). Massage therapy for cancer palliation and supportive care: a systematic review of randomised clinical trials. Supportive Care in Cancer, 17(4), 333–337.
  • Brincat, M. P., Baron, Y. M., & Galea, R. (2005). Estrogens and the skin. Climacteric, 8(2), 110–123.
  • Thornton, M. J. (2013). Estrogens and aging skin. Dermato-endocrinology, 5(2), 264–270.
  • Wright, V. J. (2023). Musculoskeletal syndrome of menopause: an emerging concept. Journal of Women’s Health Physical Therapy, 47(3), 152–159.
  • Woodyard, C. (2011). Exploring the therapeutic effects of yoga and its ability to increase quality of life. International Journal of Yoga, 4(2), 49–54.
  • Chang, D. G., Holt, J. A., Sklar, M., & Groessl, E. J. (2016). Yoga as a treatment for chronic low back pain: a systematic review of the literature. Journal of Orthopedics and Rheumatology, 3(1), 1–8.
  • Anderson, T., & Wideman, L. (2017). Exercise and the cortisol awakening response: a systematic review. Sports Medicine Open, 3(1), 37.
  • Chikly, B. J. (2005). Manual techniques addressing the lymphatic system: origins and development. Journal of the American Osteopathic Association, 105(10), 457–464.

Disclaimer: This article is educational and does not constitute medical advice. THOR is not certified in the Nordic Fascia Release Method or affiliated with the method’s developers. For specific training or professional sessions in the method, consult certified practitioners through the official directory maintained by the method’s developers. Persistent, severe, or unexplained musculoskeletal symptoms warrant medical evaluation regardless of any bodywork engagement.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Your Fascia and Your Hormones: How Estrogen Shapes the Connective Tissue That Explains Menopause Aches, Stiffness, and Joint Pain

Joint pain, stiffness, and unexplained body aches are common during perimenopause and menopause, yet they are often dismissed as normal aging. Many women experience stiff mornings, discomfort that moves between joints, reduced mobility, and the feeling that their body no longer moves as freely as it once did.

These changes may be connected to declining estrogen and its effects on fascia. Fascia is the connective tissue network that surrounds muscles, supports organs, and runs continuously throughout the body. Understanding this connection can make many midlife symptoms easier to explain and more effectively address.

Fascia is metabolically active, densely innervated, and connected to the immune and lymphatic systems. It also responds to hormonal signaling. Estrogen helps support fascial hydration, collagen organization, elasticity, and the smooth gliding of tissues.

As estrogen declines during the menopause transition, fascia may become less hydrated and pliable. This can contribute to stiffness, reduced range of motion, persistent aches, and joint discomfort that seems to appear without a clear cause.

I am Terry Tateossian, founder of The House of Rose and a certified lifestyle medicine coach who leads nutrition-focused yoga retreats for women in perimenopause, menopause, and post-menopause at our Smoky Mountains property in East Tennessee. I founded THOR after experiencing early-onset menopause at 41 and recognizing these same changes in my own body.

This guide explores how estrogen affects fascial tissue, why women’s fascia responds differently than men’s, what changes during menopause, and why pain and stiffness often appear in specific areas. It also covers six evidence-informed practices that can support fascia as part of a broader lifestyle medicine approach.

Important: Not all joint pain and body aches are caused by hormonal or fascial changes. Autoimmune conditions, thyroid dysfunction, medication effects, vitamin deficiencies, and other health issues can produce similar symptoms. Persistent, severe, or worsening symptoms should be evaluated by a medical professional.

What Is The Connective Tissue Called Fascia?

A brief refresh on what fascia is provides the foundation for understanding the hormonal connection.

Fascia anatomy and functions infographic.
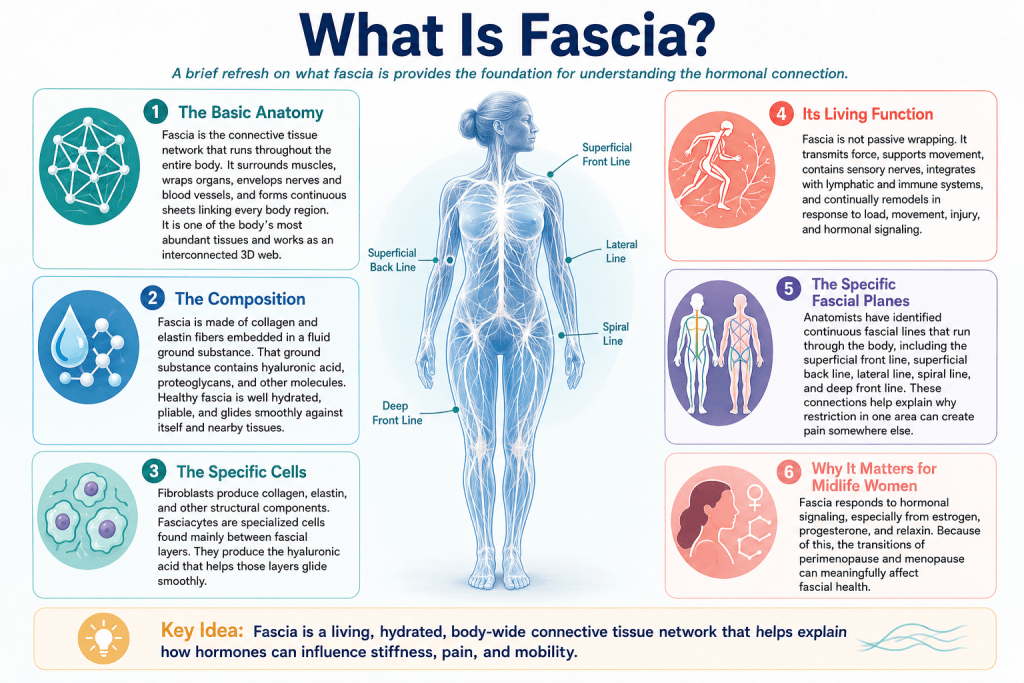
  • The basic anatomy: Fascia is the connective tissue network that runs throughout the entire body. It surrounds every muscle, wraps every organ, envelops every nerve and blood vessel, and forms continuous sheets that link every body region to every other body region. It is one of the most abundant tissues in the body and forms an interconnected three-dimensional web rather than a set of discrete structures.
  • The composition: Fascia is a web of collagen and elastin fibers embedded in a fluid ground substance. The ground substance includes hyaluronic acid (which holds enormous amounts of water), proteoglycans, and various other molecules. Healthy fascia is well hydrated, pliable, and glides smoothly against itself and against adjacent tissues.
  • The specific cells: Two cell types matter most for the hormonal conversation. Fibroblasts produce collagen, elastin, and other structural components. Fasciacytes are a specialized cell type identified more recently that live primarily at interfaces between fascial layers and produce the hyaluronic acid that keeps fascial layers gliding.
  • Its living function: Fascia is not passive wrapping. It transmits force, participates in movement, contains extensive sensory nerve innervation (which is why fascial restriction hurts), integrates with the lymphatic and immune systems, and continuously remodels in response to load, movement, injury, and hormonal signaling.
  • The specific fascial planes: Anatomists have mapped several continuous fascial lines that run through the body from region to region. The superficial front line, superficial back line, lateral line, spiral line, deep front line, and others each connect distant body regions in ways that explain how restriction in one area can produce pain in another.
  • Why it matters for midlife women: Fascia is responsive to hormonal signaling in ways that most other tissues are not, and the specific hormones women produce (estrogen, progesterone, relaxin) affect fascia meaningfully. This makes the hormonal transitions of perimenopause and menopause consequential for fascial health.

The Difference Between Women’s Fascia vs Men’s Fascia?

The specific ways in which women’s fascia differs from men’s are worth understanding because they explain the specific menopause-fascia connection.

  • Baseline compositional differences: Research has documented that women’s fascia tends to have somewhat different collagen composition, higher water content, and greater baseline elasticity compared to men’s fascia at the same age. These differences appear to be largely driven by the higher circulating estrogen levels women maintain through their reproductive years.
  • Baseline elasticity and springiness: Women’s fascia is generally more pliable and springy than men’s. This has practical implications for movement, flexibility, and injury patterns throughout adult life. It also has implications for what happens when estrogen levels shift.
  • The specific joint effects: Women have generally greater joint range of motion than men throughout the reproductive years, again attributed largely to hormonal effects on connective tissue. The specific range of motion at hips, spine, and other joints tends to be greater in premenopausal women than in age-matched men.
  • The pregnancy-specific adaptations: Women’s connective tissue is adapted to pregnancy, which requires substantial fascial and ligamentous laxity to accommodate a growing fetus and eventual birth. The hormone relaxin produces this laxity during pregnancy. The general responsiveness of female connective tissue to hormonal signaling is part of this broader adaptation.
  • The specific vulnerabilities: The higher fascial elasticity that supports pregnancy also produces specific vulnerabilities. Women have higher rates of certain ligament injuries (particularly ACL injuries in athletes) and certain joint conditions that reflect the hormonal responsiveness of female connective tissue.
  • What changes at menopause: As estrogen declines through perimenopause and menopause, the hormonal support for female fascial characteristics weakens. Fascia becomes stiffer, less hydrated, and less elastic. The specific baseline that women had through their reproductive years shifts toward a less-pliable state.
  • Not the same as becoming men’s fascia: Postmenopausal women’s fascia does not become identical to men’s fascia. It becomes women’s fascia with reduced hormonal support. The specific pattern of change reflects the loss of estrogen-supported qualities rather than a shift to a fundamentally different tissue type.
  • The practical implication: Because female fascia is responsive to hormonal signaling, the specific interventions that support fascia through menopause need to account for this hormonal responsiveness rather than treating fascia as a hormone-neutral tissue.

“The specific reason the fascia-hormone connection matters for coaching clients is that it names something that has often been dismissed or misdiagnosed. A coaching client in her late forties or early fifties who has been told repeatedly that her aches and stiffness are just aging often experiences meaningful relief simply from understanding that what she is experiencing is a specific hormonal shift affecting a specific tissue system in a specific way. The naming produces both intellectual clarity and practical direction. Once she understands why her body is different than it was five years ago, she can begin working with the specific practices that support fascia through this transition. Within two to three months of consistent daily fascial work combined with the broader lifestyle medicine framework, most coaching clients report meaningful reduction in the aches and stiffness that had been present. This is not a miracle. It is the specific application of a specific framework to a specific problem. The framing is what makes it possible.”

Terry Tateossian, Founder of The House of Rose

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Is the Specific Role of Estrogen in Fascial Tissue?

Understanding the specific mechanisms by which estrogen affects fascia clarifies why the menopause transition produces such visible effects in this tissue system.

  • Estrogen receptors on fascial cells: Fibroblasts and other fascial cells carry estrogen receptors. This means these cells respond directly to estrogen signaling. When estrogen levels are stable in the reproductive years, fascial cells receive consistent signaling that supports their function. When estrogen fluctuates through perimenopause and then declines through menopause, this signaling shifts substantially.
  • Estrogen and hyaluronic acid production: Estrogen supports hyaluronic acid production by fascial cells and by other tissues. Hyaluronic acid is the specific molecule that holds enormous amounts of water in connective tissue and that provides the specific gliding function at fascial layer interfaces. Reduced estrogen typically reduces hyaluronic acid production, producing the specific pattern of reduced fascial hydration and reduced glide.
  • Estrogen and collagen composition: Estrogen influences the specific ratio and organization of collagen types in fascial tissue. Postmenopausal shifts in collagen composition produce fascia that behaves differently mechanically than premenopausal fascia. The specific changes include altered ratio of Type I to Type III collagen and altered organization of the fibers.
  • Estrogen and skin: The skin is a specific fascial tissue that many women can observe directly. Research documents that women lose approximately 30 percent of skin collagen in the first five years post-menopause, followed by continued loss of approximately 2 percent per year. Skin becomes thinner, drier, and less elastic. Analogous changes are occurring in fascia throughout the body, even though they are less visible than the skin changes.
  • Estrogen and joint tissue: Estrogen affects cartilage, synovial fluid, and periarticular connective tissue. The specific changes in these tissues through the menopause transition contribute to the joint pain and stiffness that many women experience.
  • Estrogen and lymphatic function: Fascia and the lymphatic system are functionally interconnected. Estrogen effects on both systems contribute to the specific patterns of fluid retention, puffiness, and lymphatic sluggishness some midlife women experience.
  • The estrogen fluctuation of perimenopause: In the perimenopause window before final estrogen decline, hormone levels fluctuate irregularly. This produces the specific pattern of good weeks alternating with bad weeks in terms of fascial symptoms that many perimenopausal women describe. The fluctuation itself, not just the final decline, contributes to the felt experience.
  • The post-menopause stabilization: Once estrogen has declined and stabilized at postmenopausal levels, the fascial changes stabilize as well. The specific practice of supporting fascia in this stabilized state can produce meaningful improvement even in the absence of restored estrogen.

What Happens to Fascia Through Perimenopause and Menopause?

The specific timeline and pattern of fascial changes through the menopause transition helps midlife women understand what they are experiencing and when to expect improvement with intervention: These changes can begin during perimenopause and continue gradually throughout post-menopause.

How Do Fascial Changes Progress Through the Menopause Transition?

  • Perimenopause: the fluctuation phase: Perimenopause typically begins in the early to mid-forties and lasts from a few years to a decade. Estrogen levels fluctuate irregularly during this period. Fascial symptoms often begin in this window as intermittent stiffness, occasional joint aches, morning stiffness that comes and goes, and periods of feeling less flexible than usual. The specific fluctuation pattern often confuses women because good weeks are followed by bad weeks without obvious explanation.
  • The final menstrual period and immediate post-menopause: After the final menstrual period, estrogen typically declines to postmenopausal levels over a period of months to a few years. This is often the window of most rapid fascial change. Women who had ignored earlier symptoms often become unable to ignore them during this window. Morning stiffness may become daily. Joint aches may become persistent. Skin changes become visible. General flexibility often reduces noticeably.
  • The first five years post-menopause: Research has documented that women lose approximately 30 percent of skin collagen in the first five years after the final menstrual period. Analogous changes are occurring in fascia throughout the body. This is the specific window where fascial support interventions produce the most visible dividends because the loss is accelerating most rapidly.
  • Continued gradual change afterward: After the first several years post-menopause, the rate of fascial change slows to approximately 2 percent per year loss in connective tissue support. This gradual decline continues throughout later life without appropriate intervention.

What Symptoms Can Fascial Changes Produce?

The specific symptom pattern associated with fascial changes can affect movement, flexibility, comfort, and the general felt-sense of the body: These symptoms may occur across several areas rather than remaining limited to one joint or muscle.

  • Morning stiffness that improves with movement
  • Joint aches that migrate around the body without clear injury
  • Reduced range of motion at multiple joints
  • Tightness that does not resolve with standard stretching
  • A felt-sense of being stuck in the body
  • Skin changes that many women notice concurrently

Why Do Fascial Changes Vary Between Women?

The rate and severity of fascial change varies significantly across individuals based on baseline fascial health, activity level, nutrition, sleep quality, stress load, and various other factors: Two women at the same age with the same estrogen levels can have meaningfully different fascial states based on these other factors.

Can Menopause-Related Fascial Changes Be Improved?

The good news is that fascia is one of the most responsive tissues to targeted intervention: Consistent daily practice combined with the broader lifestyle medicine framework can meaningfully improve fascial mobility, hydration, and glide even in postmenopausal women. The changes are not immediately reversible, but the trajectory can be shifted meaningfully.

The perimenopause and early post-menopause window is the specific time when intervention produces the largest returns because the loss is happening most rapidly and the tissue is most responsive to support: Starting fascial practice in this window produces better long-term outcomes than starting a decade later.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Why Does This Produce the Specific Symptoms Midlife Women Experience?

The specific symptoms that midlife women experience are worth naming because they help identify when the fascia-hormone framework is the right explanation for what is happening.

Midlife fascia symptoms in women.
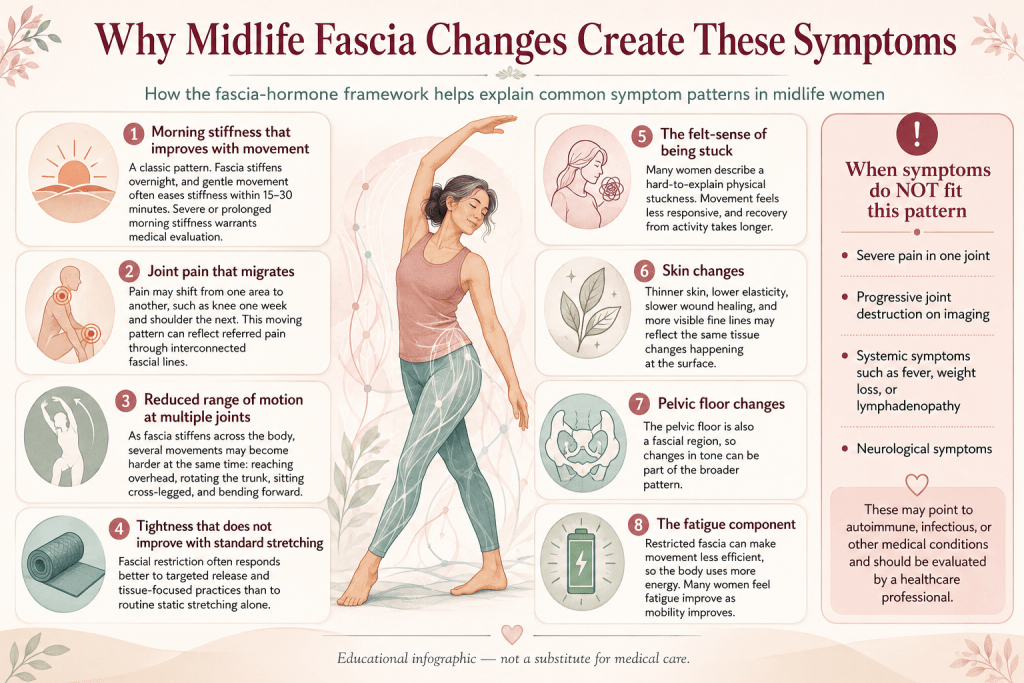
  • Morning stiffness and joint pain that improves with movement: This is one of the most characteristic patterns. Fascia is more hydrated during rest and stiffens overnight in the absence of movement. Morning stiffness that resolves within 15 to 30 minutes of movement often reflects fascial rather than joint pathology. Morning stiffness that persists for hours or that is severe warrants medical evaluation for other causes.
  • Joint pain that migrates around the body: Fascial restriction can refer pain to distant sites through the interconnected fascial lines. A woman may experience knee pain one week and shoulder pain the next, with no obvious injury explanation for either. This migratory pattern is characteristic of fascial referred pain.
  • Reduced range of motion at multiple joints: As fascia stiffens across the body, range of motion at multiple joints reduces simultaneously. Reaching overhead. Rotating the trunk. Sitting cross-legged. Bending forward. These simple movements become progressively harder. The generalized nature of the restriction points toward system-wide fascial changes rather than specific joint pathology.
  • Tightness that does not resolve with standard stretching: Fascial restriction responds differently to targeted release than to standard static stretching. Women who have been doing regular stretching without meaningful improvement may benefit from adding specific fascial practices that address the tissue quality directly.
  • The felt-sense of being stuck: Beyond specific symptoms, many midlife women describe a general sense of physical stuckness that is hard to articulate. Movement feels harder than it should. The body feels less responsive. Recovery from any physical demand takes longer. This felt-sense often reflects the combined fascial and mitochondrial changes of the transition.
  • Skin changes: The skin changes that many midlife women observe reflect fascial changes at the surface. Thinner skin. Reduced elasticity. Slower wound healing. More visible fine lines. These reflect the same underlying tissue changes happening deeper in the body.
  • Pelvic floor changes: The pelvic floor is a specific fascial region. The changes in pelvic floor tone that many midlife women experience reflect the broader fascial pattern.
  • The specific fatigue component: Chronically restricted fascia contributes to fatigue because moving a restricted body requires more energy than moving a fluid one. Many midlife women describe fatigue that improves as fascial mobility improves.
  • When symptoms do not fit this pattern: Some symptoms do not fit the fascia-hormone framework and warrant medical evaluation. Severe joint pain in a single joint. Progressive joint destruction visible on imaging. Systemic symptoms including fever, weight loss, or lymphadenopathy. Neurological symptoms. These may indicate autoimmune conditions, infections, or other conditions requiring specific medical care.

What Does the Research Say About Estrogen, Connective Tissue, and Menopause?

The specific research supporting the fascia-hormone connection is worth understanding because it separates evidence-based framework from wellness speculation.

  • Estrogen receptor research: Estrogen receptors have been documented on fibroblasts and other cells throughout connective tissue. This provides the specific mechanism by which estrogen affects fascia and confirms that fascia is a hormonally responsive tissue.
  • Skin collagen research: Multiple studies have documented specific collagen changes in skin through the menopause transition. Women lose approximately 30 percent of skin collagen in the first five years after final menstrual period and continue losing approximately 2 percent per year afterward. This is one of the largest single hormonally-driven biological changes of the menopause transition.
  • Joint and cartilage research: Estrogen effects on cartilage, chondrocytes, and joint tissues have been documented in multiple studies. Postmenopausal women have measurably different joint tissue characteristics than premenopausal women of similar age.
  • Musculoskeletal syndrome of menopause: Some clinicians now use the specific term “musculoskeletal syndrome of menopause” to describe the specific pattern of joint pain, stiffness, and reduced function that many midlife women experience. This framing acknowledges the specific hormonal contribution rather than dismissing the symptoms as generic aging.
  • Hyaluronic acid research: Research on hyaluronic acid production in connective tissue has documented estrogen effects on the specific molecule that most directly supports fascial hydration and glide.
  • Tendon and ligament research: Studies of specific tendons and ligaments in postmenopausal women have documented mechanical changes consistent with the fascia-hormone framework. Tendon stiffness. Reduced tissue elasticity. Altered response to loading.
  • Hormone therapy research: Studies of hormone therapy in postmenopausal women have documented specific effects on connective tissue including skin, joint function, and various other outcomes. This provides indirect confirmation that estrogen affects these tissues because restoring estrogen partially restores the tissue characteristics.
  • The specific limitations of current research: Much of the research on female-specific fascial physiology is more limited than the equivalent research on male athletes. This is partly a consequence of historical bias in exercise science research toward male subjects. The specific mechanisms of fascia-hormone interaction in the specific pattern of menopause are still being actively investigated.
  • What the current picture supports: The current evidence supports the general framework that estrogen meaningfully affects fascial tissue, that the menopause transition produces specific fascial changes contributing to the symptom pattern many midlife women experience, and that specific interventions can support fascia through this transition. The specific details are still being refined by ongoing research.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

When Is Fascia Not the Explanation?

Being honest about where the fascia-hormone framework does not explain midlife symptoms matters because it prevents misapplication of the framework. Several medical conditions can produce pain, stiffness, or other symptoms that resemble fascial changes but require different evaluation and treatment.

Medical Conditions That Can Resemble Fascial Symptoms

  • Autoimmune conditions: Rheumatoid arthritis, lupus, and other autoimmune conditions can present with joint pain and stiffness that superficially resembles the fascia-hormone pattern. These conditions typically involve specific patterns, including symmetric joint involvement, prolonged morning stiffness lasting over an hour, systemic symptoms, and specific laboratory findings. They require specific medical treatment.
  • Thyroid dysfunction: Both hypothyroidism and hyperthyroidism can produce muscle and joint symptoms that resemble the fascia-hormone pattern. Thyroid function warrants evaluation in any midlife woman with persistent musculoskeletal symptoms.
  • Vitamin D deficiency: Vitamin D deficiency is common and can produce diffuse musculoskeletal aches. Testing and appropriate supplementation can resolve this contribution to symptoms.
  • Fibromyalgia: Fibromyalgia is a specific chronic pain condition with defined diagnostic criteria that differs from the fascia-hormone pattern. Some overlap exists, but the conditions require different management.

Medication and Nerve-Related Causes

Certain symptoms may result from medication effects or nerve-related conditions rather than changes in the fascia.

  • Statin-related muscle symptoms: Some women taking cholesterol-lowering statins experience muscle aches that can be attributed to fascia when the actual cause is a medication effect. Discuss new muscle symptoms with your prescribing physician if they develop after starting a statin.
  • Peripheral neuropathy: Nerve pain from various causes, including diabetes, alcohol use, chemotherapy, and nutrient deficiencies, can be misattributed to fascia. Nerve pain has specific qualities, such as burning, shooting, tingling, or numbness, that distinguish it from typical fascial pain.

Structural Joint and Tissue Problems

Osteoarthritis, meniscal tears, rotator cuff injuries, and other specific structural conditions can produce joint symptoms that require specific management beyond general fascial support.

These conditions may involve localized pain, weakness, swelling, instability, or loss of function that does not improve through general movement and fascial support strategies.

Symptoms That Require Prompt Medical Evaluation

Some patterns of pain should not be assumed to come from fascia because they may indicate a more serious medical issue.

  • Cardiac symptoms: Certain patterns of pain, particularly left arm, chest, or jaw pain associated with exertion, can indicate cardiac issues rather than musculoskeletal problems. Any concerning cardiac symptoms warrant immediate medical evaluation.
  • Malignancy: Persistent unexplained pain, particularly if it is progressive or associated with weight loss, night sweats, or other systemic symptoms, warrants evaluation to rule out serious conditions.

The Practical Implication

The fascia-hormone framework explains a significant portion of midlife musculoskeletal symptoms. It does not explain all of them.

Persistent, severe, or atypical symptoms warrant medical evaluation before assuming the fascia-hormone framework is the right explanation.

These Six Evidence-Informed Practices Support Fascia Through Menopause:

The specific interventions that support fascia through the menopause transition are worth articulating clearly because most midlife women want a specific framework they can install rather than general advice.

Six practices supporting fascia through menopause.
  • Practice 1: Circadian rhythm alignment. Fascia repair happens preferentially during sleep. Consistent sleep and wake times, adequate sleep duration, and appropriate light exposure support the nightly fascial repair that keeps the tissue functioning well. This is not obviously a fascial practice, but it is one of the most impactful.
  • Practice 2: Daily gentle movement. Fascia responds to movement. Sedentary behavior directly worsens fascial restriction. Regular gentle movement throughout the day is more supportive than intense sporadic exercise combined with prolonged sitting.
  • Practice 3: Adequate hydration. Fascial hydration depends on adequate fluid intake. Chronic underhydration common in midlife directly affects fascial water content and glide.
  • Practice 4: Nutritional support. Adequate protein for collagen synthesis. Vitamin C for collagen crosslinking. Omega-3s for anti-inflammatory support. Colorful vegetables for antioxidants and polyphenols. These nutritional foundations support fascial tissue quality.
  • Practice 5: Nervous system regulation. Chronic sympathetic activation keeps fascia braced. Parasympathetic recovery time supports the tissue relaxation that allows fascial remodeling.
  • Practice 6: Targeted fascial practices. Specific fascial release techniques including foam rolling, myofascial ball work, and specific stretching practices produce local improvements in fascial mobility.

Each of these six practices is covered in detail in the following sections. The specific value of the framework is that these six practices work together. Any single practice produces modest results. The combination produces the specific improvements that midlife women describe as feeling like they got their body back.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Does Your Circadian Rhythm Affect Your Fascia?

Circadian rhythm may not seem like an obvious fascial practice, but it is one of the specific foundations that supports fascial repair. Sleep quality, hormonal timing, and consistent daily rhythms all influence the processes that maintain healthy connective tissue.

The Nightly Repair Window

Most tissue repair, including fascial repair, happens preferentially during sleep. Compromised sleep directly reduces the specific repair processes that maintain fascial health.

The Hormone-Sleep Connection

Cortisol, growth hormone, and various other hormones that affect connective tissue function follow specific circadian patterns. Disrupted sleep disrupts these hormonal rhythms, producing downstream effects on fascia.

The Menopause Sleep Pattern

The sleep disruption of perimenopause and menopause is one of the largest quality-of-life issues in this life stage. It also has direct fascial consequences beyond the general effects on daytime function.

A Practical Circadian Framework

The specific practices that support the circadian foundation for fascial repair include:

  • Consistent bed and wake times
  • Adequate sleep duration, typically seven to nine hours
  • A cool, dark bedroom
  • Screen limits in the evening
  • Morning light exposure
  • Appropriate stress management

The Specific Value for Fascial Health

Addressing sleep as a fascial intervention often produces meaningful improvement in fascial symptoms that would otherwise remain persistent. Sleep is not optional for fascial health.

How Does Movement Affect Fascia?

The specific role of movement in fascial health is worth understanding because both too little and too much of certain kinds of movement can be problematic.

  • Fascia requires movement: Sedentary behavior directly worsens fascial restriction because fascia adapts to the positions the body spends the most time in. Prolonged sitting produces the specific pattern of shortened hip flexors, tight lower back, restricted thoracic spine, and various other fascial restrictions.
  • The specific supportive movement pattern: Daily walking, regular resistance training targeting the four major muscle groups, and periodic specific fascial practices produce the movement variety that supports fascial health. Even short micro walks throughout the day can add another practical layer of consistent movement without requiring long workout sessions.
  • The rotation component: Fascia responds particularly well to gentle rotational movement. Yoga, tai chi, dance, and various other movement traditions that include rotation support fascial health in ways that pure linear movement does not.
  • The sustained-hold component: Fascia responds to sustained gentle loading over minutes rather than brief bouts of stretching. Yin yoga works with this principle by holding postures for 3 to 5 minutes or longer.
  • The dynamic warm-up importance: Fascia is stiffer when cold and more pliable when warm. Warming up before demanding movement supports fascial function. Cold static stretching is generally less supportive than dynamic warm-up.
  • The specific caution against excessive intense exercise: Some midlife women respond to menopause aches by dramatically increasing intense exercise. This can worsen fascial symptoms because intense loading of an already stiffened tissue system produces more restriction. The specific pattern that works better is gentle daily movement combined with appropriate resistance training, not more intense endurance training.
  • The frequency principle: Fascia benefits from consistent daily movement more than from occasional intense sessions. Five to fifteen minutes of daily fascial-focused practice produces better results than an hour once a week.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Does Hydration Affect Fascia?

Fascial hydration depends directly on adequate fluid intake, and chronic underhydration is one of the specific contributors to midlife fascial restriction.

How hydration supports healthy fascia.
  • The specific water requirement: Fascia’s ground substance is largely water held by hyaluronic acid. Reduced systemic hydration directly reduces fascial water content and produces the specific pattern of stiffness and reduced glide.
  • The midlife hydration problem: Many midlife women underhydrate for various reasons, including reduced thirst signaling that comes with age, busy schedules, coffee replacing water throughout the day, and other common hydration mistakes that can make it harder to maintain consistent fluid intake.
  • The electrolyte component: Water without appropriate electrolytes (sodium, potassium, magnesium) does not hydrate tissues as effectively as water with electrolytes. Some midlife women benefit from specific attention to electrolyte balance particularly during and after exercise.
  • The specific practical target: Approximately half your body weight in pounds converted to ounces of water is a reasonable general target (a 140-pound woman would target approximately 70 ounces per day). Individual needs vary based on activity, climate, and other factors.
  • The pre-fascia-work hydration: Being well-hydrated before doing targeted fascial practices produces better results than doing them dehydrated. Water intake in the hours before practice supports tissue response.
  • The specific note about excess water: Excessive water intake without electrolyte support can dilute sodium levels and produce its own problems. The goal is adequate hydration, not maximum water intake.

How Does Nutrition Support Fascia?

The specific nutrients that support fascial tissue quality are worth naming because targeted nutrition supports fascial health in ways that hydration alone cannot.

  • Adequate protein: Fascia is built from collagen and other proteins. Adequate daily protein intake provides the amino acid substrates. Approximately 1.6 to 2.2 grams per kilogram of body weight for midlife women is the general target, distributed across meals with 25 to 40 grams per meal.
  • Vitamin C: Vitamin C is a required cofactor for collagen synthesis. Adequate intake (approximately 500 mg daily as a working target) supports the specific enzymatic processes that build fascial collagen.
  • Omega-3 fatty acids: Omega-3s support anti-inflammatory function that reduces the chronic low-grade inflammation contributing to fascial restriction.
  • Colorful vegetables and polyphenols: Antioxidants and polyphenols protect fascial tissue from oxidative damage and support cellular repair.
  • Zinc and copper: These trace minerals support the enzymes involved in collagen synthesis and crosslinking.
  • Vitamin D: Vitamin D supports bone and connective tissue health broadly. Deficiency is common in midlife women and warrants specific attention.
  • The collagen supplementation question: Collagen peptide supplements have modest evidence for skin and joint outcomes. They are optional additions on top of the nutritional foundation, not substitutes for it.
  • The bone broth alternative: Traditional slow-cooked bone broth provides collagen, gelatin, and specific amino acids in food form. Adding bone broth to the diet is one specific way to support fascial nutrition through food rather than supplements.
  • The Mediterranean pattern: The general Mediterranean eating pattern with adequate protein, colorful vegetables, olive oil, and traditional food preparations aligns well with fascial nutritional support.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Does Nervous System Regulation Affect Fascia?

The specific role of nervous system regulation in fascial health is worth understanding because chronic sympathetic activation keeps fascia braced in ways that undermine every other intervention.

  • The bracing effect: Chronic stress produces continuous low-grade muscle and fascial tension throughout the body. This bracing pattern is one of the specific contributors to midlife fascial restriction that even good movement and nutrition cannot fully address if the underlying sympathetic activation remains.
  • The specific menopause-cortisol pattern: The cortisol dysregulation common in perimenopause and menopause contributes to the chronic bracing. Addressing cortisol through sleep, stress management, and nervous system practices supports fascial health.
  • The parasympathetic recovery importance: Fascia can only fully repair during parasympathetic dominance. Chronic sympathetic activation reduces the time the body spends in the repair state.
  • The specific vagal practices: Extended exhalation breathing, humming, gargling, cold face immersion, and other vagus nerve reset exercises can help encourage parasympathetic activation and support a calmer nervous system response.
  • The daily rhythm: A few minutes of specific parasympathetic practice built into the daily rhythm supports fascial repair. Morning practice sets the day’s tone. Evening practice supports sleep.
  • The specific menopause emotional layer: The mood changes and emotional intensity of perimenopause and menopause can add to the overall nervous system load, sometimes influencing everyday behaviors such as emotional eating and stress-related food habits.

Which Targeted Fascial Practices Support Mobility?

The specific fascial practices that address restriction directly are worth naming because they produce the most immediately visible effects on fascial mobility.

Foam Rolling and Targeted Ball Release

Slow, Sustained Movement Practices

  • Yin yoga: Yin yoga uses sustained postures held for 3 to 5 minutes or longer to produce specific fascial responses. This is one of the most effective movement traditions for fascial support.
  • Tai chi and slow rotational movement: The specific slow rotational movement of tai chi supports fascial planes in ways that linear movement does not.
  • Static stretching with breath: Traditional static stretching held for 45 seconds or longer with slow breath produces fascial as well as muscular effects. This is different from brief pre-workout stretching.

Professional Massage Support

Professional massage supports fascial mobility. Regular sessions, either monthly or bi-monthly, can support the home practice.

A Practical Menopause Fascial Routine

For midlife women specifically, a combination of the following practices produces meaningful support for fascia through the transition:

  • Daily 10-minute foam rolling
  • Targeted ball work for restricted areas
  • Twice-weekly yin yoga sessions
  • Periodic professional massage

When to Stop and Reassess

Sharp pain, nerve-like symptoms such as numbness or tingling, or radiating pain are signs to stop and reassess. Discomfort at a stretch is normal. Pain that seems wrong is a signal.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Can You Expect With Consistent Practice?

Setting realistic expectations for what improves and when helps midlife women stay consistent with the practices long enough to see results.

What Changes During the First Six Weeks?

  • Weeks 1 to 2: Some immediate subjective improvement in specific areas that receive targeted practice. Morning stiffness may reduce modestly. The felt-sense of tightness may soften. Improvements are typically modest at this stage.
  • Weeks 3 to 6: More noticeable improvements in specific areas. Some general reduction in aches and stiffness. Range of motion may improve modestly at specific joints. The practice starts to feel automatic rather than deliberate.

What Changes Between Seven Weeks and Six Months?

  • Weeks 7 to 12: Meaningful cumulative improvement. Many women describe feeling meaningfully better than at baseline. Chronic aches that had been persistent for years begin resolving. Movement feels easier. Sleep may improve. Skin may look better.
  • Months 3 to 6: Deeper structural improvements. Body composition changes may become visible as improved fascial mobility supports better movement and improved training response. Emotional relationship with the body often shifts noticeably.
  • Months 6 to 12: Substantial transformation for women who maintain consistent practice. The pattern of midlife aches and stiffness that had seemed permanent often resolves substantially. Some women describe feeling meaningfully more like their pre-menopause selves in terms of physical ease.

Why Does the Timeline Vary?

The individual variation. Timeline varies significantly across women. Baseline fascial health, consistency of practice, quality of the broader framework, and various other factors affect how quickly and how much improvement appears.

What May Not Return to the Pre-Menopause Baseline?

What does not return to pre-menopause baseline. Some fascial characteristics do not fully return to pre-menopause baseline without hormone therapy:

  • Skin thickness
  • Certain aspects of joint tissue
  • The specific bounce and springiness of premenopausal fascia

What can improve substantially is the felt-sense of the body, the aches and stiffness, the mobility, and the general trajectory.

Why Does Consistency Matter?

The specific caution. Sporadic practice produces limited results. Consistent daily practice over months produces the improvements. Women who abandon the framework after a few weeks and then blame the framework rather than the inconsistency miss the specific value the framework provides.

“The specific pattern I see with coaching clients who successfully install the fascia-hormone framework is that the first six weeks feel like ordinary self-care. Some improvement. Modest changes. Nothing dramatic. Then somewhere between weeks 8 and 12, something shifts. They wake up one morning and realize they are not stiff. They finish a workout and realize they recovered easily. They reach for something on a high shelf and realize it did not feel like work. The specific transformation that many midlife women had stopped expecting starts becoming visible. That is when the framework earns its place in their daily routine indefinitely. The specific work that produced the shift becomes ordinary and non-negotiable because they can feel what it is doing. This is why I encourage coaching clients to commit to three months of consistent practice before evaluating whether the framework works for them. Anything less usually misses the specific window where the shift becomes visible.”

Terry Tateossian, Founder of The House of Rose

Can Hormone Therapy Support Fascial Health?

The specific question of hormone therapy and fascia deserves honest attention because it is one of the specific interventions with direct effects on the underlying mechanism.

How Does Hormone Therapy Affect Fascia?

Restoring estrogen through hormone therapy provides the specific hormonal signaling that fascial cells respond to. Research documents that hormone therapy modestly supports:

  • Skin collagen
  • Joint tissue characteristics
  • Various other connective tissue outcomes

The specific concerns raised by the initial Women’s Health Initiative results have been substantially revised by subsequent analysis. For most women in the appropriate time window, hormone therapy is safer than the earlier interpretation suggested. Current North American Menopause Society position statements provide the specific evidence-based framework.

What Should You Consider Before Choosing Hormone Therapy?

Hormone therapy is a specific medical decision made in partnership with a menopause specialist. The specific considerations include:

  • Your specific symptoms
  • Medical history
  • Family history
  • Age at menopause
  • Time since menopause
  • Various other individual factors

This is not a decision to make based on general internet content.

For women considering the hormone therapy question, working with a menopause specialist rather than a general practitioner often produces better decision support. The North American Menopause Society directory can help identify specialists.

For some fascial concerns, particularly those involving the pelvic floor and skin, topical estrogen preparations produce specific local effects with fewer systemic implications than oral or transdermal hormone therapy. Discuss this option with your menopause specialist.

How Does Hormone Therapy Fit Into the Fascial Support Framework?

Hormone therapy does not eliminate the need for the fascial support framework. It complements the framework by addressing one specific mechanism.

  • Women on hormone therapy still benefit from the six practices in this article.
  • Women not on hormone therapy still benefit meaningfully from the framework alone.

Whether or not hormone therapy is part of your specific plan, the fascial support framework in this article addresses the specific tissue changes through appropriate practices. The framework is compatible with hormone therapy and produces meaningful results without it.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Are the Common Misinterpretations and Wellness Marketing Distortions?

Several specific misinterpretations and distortions of the fascia-hormone framework are worth naming directly.

  • Distortion 1: The miracle supplement. Some marketing content promises specific supplements or protocols will reverse menopause fascial changes dramatically. The specific reality is that meaningful improvement requires sustained consistent practice over months. No supplement produces the specific transformation that the framework produces.
  • Distortion 2: The one-secret protocol. Some content claims to know a specific hidden protocol that mainstream medicine does not share. The framework in this article is not secret. It is the specific application of well-known principles.
  • Distortion 3: The expensive fascial devices. Various expensive fascial devices (specific rollers, guns, machines) are marketed for menopause fascia. Most of the fascial benefit comes from the practice itself, not from expensive equipment. A basic foam roller and therapy ball provide most of the tool value.
  • Distortion 4: The bypass of hormone therapy consideration. Some content encourages women to reject hormone therapy consideration in favor of natural approaches. The honest framework treats hormone therapy as a specific medical decision worth evaluating with a qualified specialist, not as something to reject on principle.
  • Distortion 5: The pain-is-inevitable framing. The opposite distortion suggests that midlife pain and stiffness are inevitable consequences of aging that cannot be meaningfully improved. The specific research and clinical experience both indicate that meaningful improvement is possible with the right framework.
  • Distortion 6: The commercial packaging of standard practices. Some content packages basic movement, hydration, and nutrition practices with expensive branded programs. The specific practices are freely available. The value of a program is in the specific support for consistent execution, not in access to secret information.

Approach content with the same critical thinking you would apply to any other health topic. Look for specific evidence. Be skeptical of urgency, scarcity, and miracle claims. Distinguish between the specific practices that produce results and the marketing around them.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

When Should You See a Healthcare Professional?

Fascia-hormone framework is one component of midlife health but does not substitute for appropriate medical care.

  • Any severe or progressive symptoms: Persistent severe pain, progressive joint destruction, or systemic symptoms warrant medical evaluation.
  • Symptoms not fitting the fascial pattern: Numbness, weakness, systemic symptoms (fever, weight loss, night sweats), or symptoms suggesting cardiac issues warrant medical evaluation before assuming fascia is the explanation.
  • Persistent morning stiffness over an hour: Prolonged morning stiffness is a specific sign of inflammatory arthritis and warrants rheumatology evaluation.
  • Symmetric joint involvement: Symptoms affecting the same joints on both sides of the body simultaneously warrant evaluation for autoimmune conditions.
  • Failure to improve: If eight to twelve weeks of consistent framework practice produces no meaningful improvement, medical evaluation for other conditions is appropriate.
  • Consideration of hormone therapy: The hormone therapy decision requires professional guidance from a menopause specialist.
  • Vitamin D and thyroid: These specific conditions can produce fascia-like symptoms and warrant testing.
  • Medication review: New musculoskeletal symptoms after starting new medications warrant review with the prescribing physician.
  • Falls or acute injuries: Any fall or acute injury warrants medical evaluation regardless of the general fascial framework.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Are Your Next Steps?

If the framework in this article resonates and you want to install the fascia-hormone practice, here are the four next steps in order of friction.

  1. Install the sleep foundation this week. Consistent bed and wake times, adequate sleep duration, and a cool, dark bedroom can provide more fascial benefit than most people realize, making a well-rounded midlife sleep-support routine an important part of the foundation.
  2. Add ten minutes of daily fascial practice. Foam roller, therapy ball, or yin yoga postures. Same time each day for four weeks.
  3. Address the protein and hydration foundation. Our free Macro Calculator provides your protein target. Aim for adequate daily water intake with appropriate electrolyte balance.

Frequently Asked Questions

Does menopause cause joint pain and stiffness?

Yes, in a specific sense. The hormonal changes of perimenopause and menopause affect connective tissue including fascia, joint capsules, cartilage, and related structures. This produces the specific pattern of joint pain and stiffness that many midlife women experience. The specific mechanism involves reduced estrogen support for connective tissue hydration, elasticity, and glide. Other conditions can also produce similar symptoms, so persistent or severe symptoms warrant medical evaluation.

How does estrogen affect fascia?

Estrogen supports fascia through multiple mechanisms including direct effects on fibroblasts via estrogen receptors, support for hyaluronic acid production that maintains fascial hydration, effects on collagen composition and organization, and support for the overall pliability that keeps fascia gliding smoothly. As estrogen declines through menopause, all of these fascial qualities shift measurably.

Can I improve my fascia after menopause?

Yes. Fascia is one of the most responsive tissues to targeted intervention. Consistent daily practice combined with the broader lifestyle medicine framework can meaningfully improve fascial mobility, hydration, and glide even in postmenopausal women. Improvements typically appear within 4 to 12 weeks of consistent practice and continue developing over months.

Why does my body ache more in menopause?

The specific hormonal changes affect multiple systems including fascia, joints, cartilage, and related structures. Reduced estrogen support produces reduced fascial hydration and elasticity, contributing to widespread aches and stiffness. Combined with chronic sympathetic activation, sleep disruption, and other menopause changes, the result is the specific pattern of aches many midlife women experience.

What is the best way to reduce menopause stiffness?

The evidence-informed framework includes six practices: consistent sleep and circadian rhythm, daily gentle movement, adequate hydration, appropriate nutrition including adequate protein, nervous system regulation practices, and targeted fascial practices. The combination produces meaningful improvement within 8 to 12 weeks of consistent practice.

Does hormone therapy help with menopause joint pain?

Hormone therapy provides the specific estrogen signaling that fascial and joint tissue respond to. Research documents that hormone therapy modestly supports connective tissue outcomes. Whether hormone therapy is right for your specific situation is a medical decision made in partnership with a menopause specialist. Hormone therapy complements rather than replaces the fascial support framework.

Can fascia be restored after menopause?

Fascia can be substantially improved through targeted practice, though it does not fully return to pre-menopause baseline without hormone therapy. What can improve substantially with consistent practice includes fascial hydration, mobility, glide, subjective aches and stiffness, and general range of motion. Full pre-menopause fascial characteristics typically require some level of hormonal support.

How long before I see improvement in menopause aches?

Timeline varies. Modest subjective improvement often appears within 2 to 4 weeks. Meaningful reduction in aches and stiffness typically appears at 8 to 12 weeks. Substantial improvement in overall body ease continues to develop over 3 to 6 months of consistent practice. Sporadic practice produces limited results.

Is fascia release safe during menopause?

Yes, generally. Standard fascia release practices (foam rolling, myofascial ball work, yin yoga, static stretching) are safe for most midlife women without acute injury or specific medical conditions. Avoid nerve-like symptoms (numbness, tingling, radiating pain). If you have specific conditions or acute pain, consult a healthcare provider before starting.

What foods support fascia during menopause?

Adequate protein (25 to 40 grams per meal). Vitamin C-rich foods (bell peppers, citrus, berries). Omega-3-rich foods (fatty fish, flaxseed, walnuts). Colorful vegetables and polyphenols. Bone broth as a specific collagen and gelatin source. Adequate hydration. The general Mediterranean pattern aligns well with fascial nutritional support.

Can supplements help with menopause fascia?

The evidence-supported foundational supplements (vitamin D, magnesium, omega-3s, adequate protein) support the general fascial framework. Collagen peptide supplements have modest evidence for skin and joint outcomes. Supplements complement rather than substitute for the broader framework.

Why does yoga help with menopause stiffness?

Yoga provides the specific combination of sustained holds (particularly in yin styles), breath work, and gentle movement that fascia responds to. Regular yoga practice supports fascial mobility, nervous system regulation, and general functional capacity.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Are there specific stretches for menopause fascia?

Beyond general stretching, specific fascial practices including yin yoga postures held 3 to 5 minutes, myofascial ball work on restricted areas, and foam rolling major muscle groups produce specific fascial effects.

How is fascia different from muscle?

Muscle is contractile tissue that produces force. Fascia is connective tissue that surrounds, supports, and connects muscles and other structures throughout the body. The two are functionally connected but have different tissue characteristics and respond to different specific interventions. Both matter for midlife function.

Should I get professional massage for menopause fascia?

Regular professional massage supports fascial mobility and complements home practice. Monthly or bi-monthly massage is a reasonable frequency for most midlife women. The specific technique (Swedish, deep tissue, myofascial release, therapeutic) can be discussed with your massage therapist based on your specific needs.

References

  • Stecco, C., Fede, C., Macchi, V., et al. (2018). The fasciacytes: a new cell devoted to fascial gliding regulation. Clinical Anatomy, 31(5), 667–676.
  • Stecco, C., Stern, R., Porzionato, A., et al. (2011). Hyaluronan within fascia in the etiology of myofascial pain. Surgical and Radiologic Anatomy, 33(10), 891–896.
  • Schleip, R., & Müller, D. G. (2013). Training principles for fascial connective tissues: scientific foundation and suggested practical applications. Journal of Bodywork and Movement Therapies, 17(1), 103–115.
  • Brincat, M. P., Baron, Y. M., & Galea, R. (2005). Estrogens and the skin. Climacteric, 8(2), 110–123.
  • Thornton, M. J. (2013). Estrogens and aging skin. Dermato-endocrinology, 5(2), 264–270.
  • Sowers, M. F., Zheng, H., Jannausch, M. L., et al. (2010). Amount of bone loss in relation to time around the final menstrual period and follicle-stimulating hormone staging of the transmenopause. Journal of Clinical Endocrinology and Metabolism, 95(5), 2155–2162.
  • Roman-Blas, J. A., Castañeda, S., Largo, R., & Herrero-Beaumont, G. (2009). Osteoarthritis associated with estrogen deficiency. Arthritis Research and Therapy, 11(5), 241.
  • Vitale, J. A., Lombardi, G., Weydahl, A., & Banfi, G. (2018). Biological rhythms, chronodisruption and chrono-enhancement: the role of physical activity as synchronizer in correcting steroid circadian rhythm impairments. Chronobiology International, 35(9), 1185–1197.
  • Wright, V. J. (2023). Musculoskeletal syndrome of menopause: an emerging concept. Journal of Women’s Health Physical Therapy, 47(3), 152–159.
  • Ajimsha, M. S., Al-Mudahka, N. R., & Al-Madzhar, J. A. (2015). Effectiveness of myofascial release: systematic review of randomized controlled trials. Journal of Bodywork and Movement Therapies, 19(1), 102–112.
  • Beardsley, C., & Škarabot, J. (2015). Effects of self-myofascial release: a systematic review. Journal of Bodywork and Movement Therapies, 19(4), 747–758.
  • Klingler, W., Velders, M., Hoppe, K., et al. (2014). Clinical relevance of fascial tissue and dysfunctions. Current Pain and Headache Reports, 18(8), 439.
  • Bordoni, B., & Zanier, E. (2013). Anatomic connections of the diaphragm: influence of respiration on the body system. Journal of Multidisciplinary Healthcare, 6, 281–291.
  • Bauer, J., Biolo, G., Cederholm, T., et al. (2013). Evidence-based recommendations for optimal dietary protein intake in older people: a position paper from the PROT-AGE Study Group. Journal of the American Medical Directors Association, 14(8), 542–559.
  • North American Menopause Society. (2022). The 2022 hormone therapy position statement of The North American Menopause Society. Menopause, 29(7), 767–794.
  • Manson, J. E., Chlebowski, R. T., Stefanick, M. L., et al. (2013). Menopausal hormone therapy and health outcomes during the intervention and extended poststopping phases of the Women’s Health Initiative randomized trials. JAMA, 310(13), 1353–1368.
  • Karvinen, S., Jergenson, M. J., Hyvärinen, M., et al. (2019). Menopausal status and physical activity are independently associated with cardiovascular risk factors of healthy middle-aged women. Frontiers in Endocrinology, 10, 589.
  • Sipilä, S., Törmäkangas, T., Sillanpää, E., et al. (2020). Muscle and bone mass in middle-aged women: role of menopausal status and physical activity. Journal of Cachexia, Sarcopenia and Muscle, 11(3), 698–709.
  • Wildman, R. P., Colvin, A. B., Powell, L. H., et al. (2013). Associations of endogenous sex hormones with the vasculature in menopausal women: the Study of Women’s Health Across the Nation (SWAN). Menopause, 20(1), 27–35.
  • Chaitow, L. (2020). Fascia as a sensory organ: implications for practice. Journal of Bodywork and Movement Therapies, 24(4), 3–4.

Disclaimer: This article is educational and does not constitute medical advice. Persistent, severe, or atypical musculoskeletal symptoms warrant medical evaluation. Consider consultation with a menopause specialist for the specific hormone therapy question. Do not stop or change any medication based on general internet content.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.