Get 11 Sample Recipes from Our Bestselling Mediterranean Cookbook. 

Get our 11 Sample Recipes from our Best Selling Mediterranean Protein Friendly Cookbook. These are the most delicious recipes our retreat guests love the most. Easy, simple with few ingredients per meal.  Make delicious heart-friendly and healthy meals you enjoy every day. 

5 Science-Backed Ways to Lose Weight That Don’t End in a Binge, a Plateau, or a Rebound

Almost every weight loss plan runs into the same three walls, in roughly the same order, regardless of which diet a person started with. First, hunger climbs, quietly and then not so quietly, until it starts driving decisions the plan never accounted for.

Then progress stalls, the same eating pattern that produced steady loss for weeks suddenly produces nothing at all, for reasons that feel arbitrary but are not. And eventually, for a large share of people, some or all of the lost weight finds its way back, often with a side of guilt that has nothing to do with what actually happened in the body.

Most weight loss content treats each of these three moments as a personal failure: not enough discipline, not enough willpower, the wrong mindset. That framing gets the story backward.

Hunger climbing, progress stalling, and weight returning are not signs that a plan failed because a person lacked resolve. They are the predictable, well-documented output of specific physiological mechanisms, and each one has a specific, evidence-based countermeasure.

This article walks through five approaches built directly around those three collision points, so that hitting one of them can be treated as expected terrain to work through, not a verdict on your character.

Why Do Weight Loss Plans Collide With the Same Three Walls?
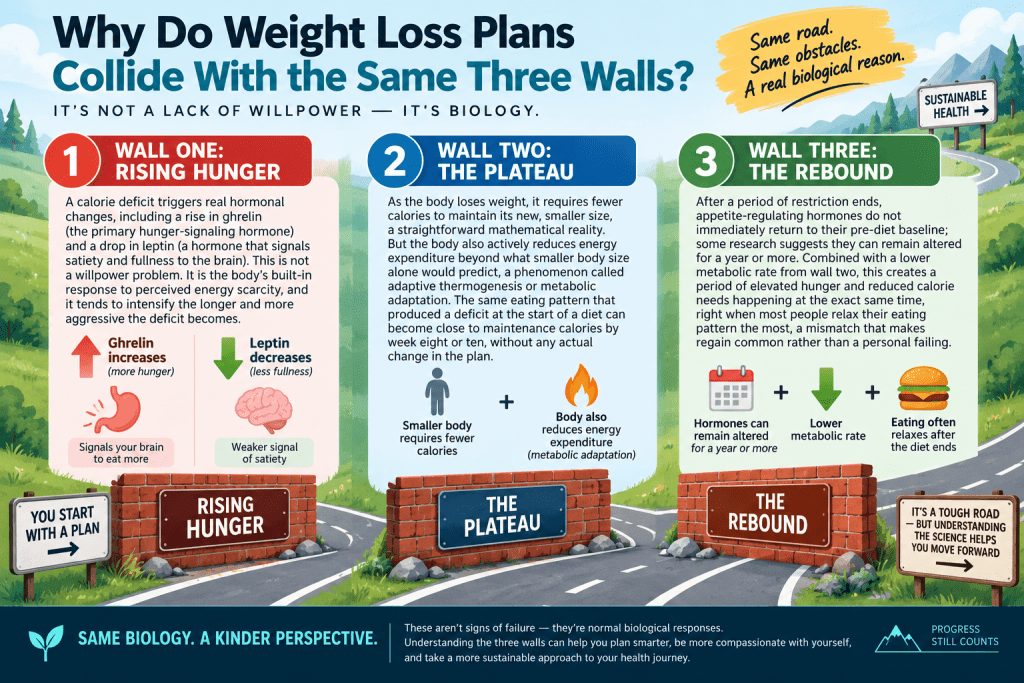
Three common weight loss barriers: hunger, plateau, and rebound.
  • Wall One: Rising Hunger. A calorie deficit triggers real hormonal changes, including a rise in ghrelin (the primary hunger-signaling hormone) and a drop in leptin (a hormone that signals satiety and fullness to the brain). This is not a willpower problem. It is the body’s built-in response to perceived energy scarcity, and it tends to intensify the longer and more aggressive the deficit becomes.
  • Wall Two: The Plateau. As the body loses weight, it requires fewer calories to maintain its new, smaller size, a straightforward mathematical reality. But the body also actively reduces energy expenditure beyond what smaller body size alone would predict, a phenomenon called adaptive thermogenesis or metabolic adaptation. The same eating pattern that produced a deficit at the start of a diet can become close to maintenance calories by week eight or ten, without any actual change in the plan.
  • Wall Three: The Rebound. After a period of restriction ends, appetite-regulating hormones do not immediately return to their pre-diet baseline; some research suggests they can remain altered for a year or more. Combined with a lower metabolic rate from wall two, this creates a period of elevated hunger and reduced calorie needs happening at the exact same time, right when most people relax their eating pattern the most, a mismatch that makes regain common rather than a personal failing.

Each of the five ways below targets one or more of these three walls directly, rather than offering another version of “eat less, move more” that ignores why the first attempt at exactly that advice already stopped working.

Why Use Diet Breaks, Not Diet Endings?

  • The Mechanism: Continuous, uninterrupted caloric restriction appears to produce more pronounced metabolic adaptation than restriction broken up by planned periods of eating at maintenance calories. A structured diet break, typically one to two weeks at maintenance intake every six to ten weeks of active dieting, gives appetite hormones and metabolic rate a chance to partially normalize before the next restriction phase begins.
  • The Research Behind It: A notable Australian study (sometimes referred to as the “MATADOR” study) compared continuous dieting to a matched intermittent approach with two-week maintenance breaks built in. The intermittent group lost significantly more fat over the same total dieting time, with less of the metabolic slowdown seen in the continuous group, supporting diet breaks as a legitimate performance strategy rather than a compromise.
  • How to Use It: Plan a maintenance-calorie break of 7 to 14 days after every 6 to 10 weeks of active caloric restriction, using this time to eat at your estimated maintenance calories (not to binge or abandon structure entirely) before resuming your deficit. This turns what many people experience as an uncontrolled binge, driven by accumulated restriction, into a planned, structured part of the process instead.

Get 11 Sample Recipes from Our Bestselling Mediterranean Cookbook. 

Get our 11 Sample Recipes from our Best Selling Mediterranean Protein Friendly Cookbook. These are the most delicious recipes our retreat guests love the most. Easy, simple with few ingredients per meal.  Make delicious heart-friendly and healthy meals you enjoy every day. 

How Can Protein and Fiber Blunt the Hunger Climb?

  • The Mechanism: Protein is the most satiating macronutrient per calorie, both through direct effects on satiety hormones and through a well-documented pattern where inadequate protein intake can drive continued eating, of any food, until a target protein intake is met, even after calorie needs are otherwise satisfied. Fiber adds to this effect by slowing digestion, increasing stomach distension, and supporting the release of additional satiety signals.
  • The Research Behind It: Multiple controlled studies comparing higher-protein to lower-protein diets at matched calorie levels show measurably lower hunger ratings and reduced spontaneous calorie intake in the higher-protein groups, supporting protein intake as a direct lever against wall one rather than simply a muscle-preservation strategy.
  • How to Use It: Prioritize 25 to 40 grams of protein per meal across three to four meals daily, and pair it with fibrous vegetables at most meals. This can help manage hunger during a calorie deficit more effectively than simply cutting calories further, which tends to make wall one worse rather than better. Your personalized macro targets can give you a clearer daily protein goal based on your body, activity level, and objectives.

How Can Preserving Muscle Protect Your Metabolic Rate?
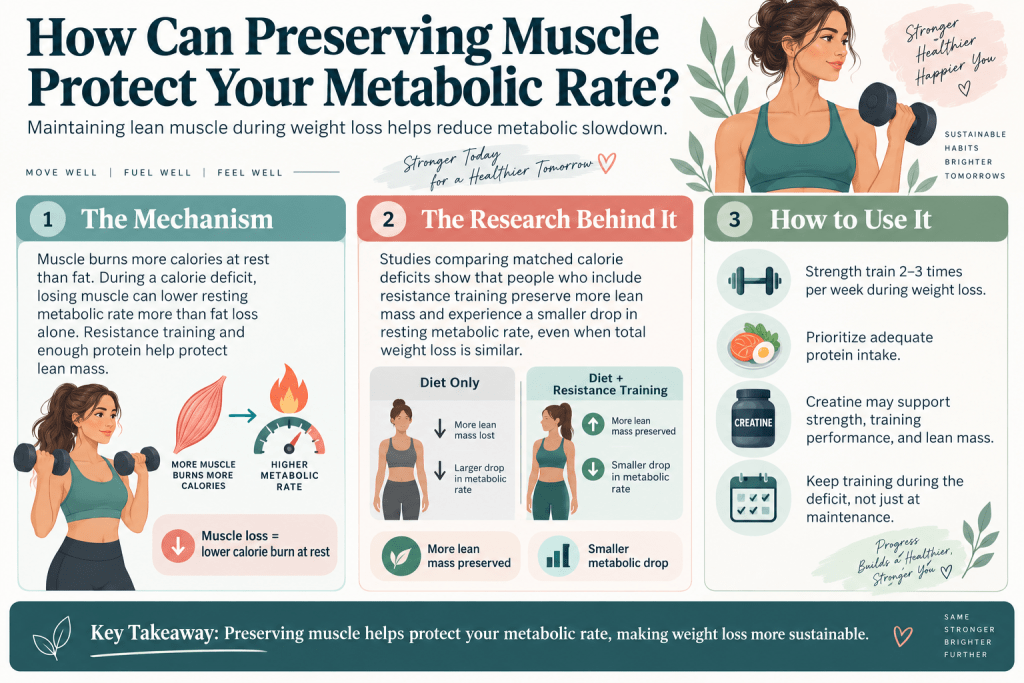
Preserving muscle helps protect metabolic rate during weight loss.
  • The Mechanism: Muscle tissue is metabolically active, meaning it burns more calories at rest than fat tissue does. A calorie deficit without adequate resistance training and protein intake tends to draw a meaningful share of the total weight lost from muscle rather than fat, which directly lowers resting metabolic rate beyond what fat loss alone would produce, accelerating wall two.
  • The Research Behind It: Studies comparing weight loss with and without resistance training, at matched calorie deficits, consistently show that the resistance training groups preserve significantly more lean mass and experience a smaller drop in resting metabolic rate, even when total weight lost is similar between groups.
  • How to Use It: Keep resistance training in your routine two to three times per week throughout a weight loss phase, not just once you reach maintenance. Consistent strength training after 40 helps preserve lean muscle while you lose weight, which is especially important when addressing the metabolic slowdown described in wall two. Pairing that training with creatine can provide additional support for strength, training performance, and lean mass during a calorie deficit.

“For years I thought a plateau meant I needed to eat even less. It took understanding the actual mechanism, that the body slows down partly in response to lost muscle, not just lost weight, to realize I had it backward. Protecting muscle during a deficit through resistance training and enough protein is not a nice-to-have on top of weight loss. It is one of the most direct ways to keep your metabolism from working against you.”

Terry Tateossian, Founder of The House of Rose

Get 11 Sample Recipes from Our Bestselling Mediterranean Cookbook. 

Get our 11 Sample Recipes from our Best Selling Mediterranean Protein Friendly Cookbook. These are the most delicious recipes our retreat guests love the most. Easy, simple with few ingredients per meal.  Make delicious heart-friendly and healthy meals you enjoy every day. 

Why Should You Plan the Maintenance Phase Before You Need It?

  • The Mechanism: Wall three, the rebound, is made significantly worse when a period of restriction ends abruptly, with an immediate jump back to prior eating habits, right at the moment when hunger hormones are still elevated and metabolic rate is still suppressed from the diet just completed. A gradual, planned increase in calories back toward true maintenance, rather than an abrupt stop, allows the body’s systems to recalibrate in step with the returning food intake instead of being overwhelmed by a sudden shift.
  • The Research Behind It: This is the foundational logic behind reverse dieting, a structured, gradual increase in calorie intake following a diet phase, and it is supported by the broader body of research on metabolic adaptation and post-diet weight regain, which consistently points to abrupt, unplanned transitions out of a deficit as a major contributor to rapid regain.
  • How to Use It: Rather than treating the end of a diet as a finish line, transition back toward maintenance gradually by increasing calories in small, measured steps and monitoring how your weight, energy, hunger, and training respond. Understanding the basics of reverse dieting can help you structure that transition, while a more detailed reverse diet after 50 provides a practical week-by-week framework for midlife women.

Why Should You Build the Habit Layer Before You Cut Calories?

  • The Mechanism: Adherence to any eating plan depends heavily on factors most diet plans never address directly: sleep quality, chronic stress and cortisol, environmental food cues, and the underlying emotional relationship with food. A calorie target layered on top of poor sleep, high unmanaged stress, and an environment full of easy defaults toward less helpful choices is fighting an uphill battle regardless of how well-designed the macros are.
  • The Research Behind It: Research on sleep deprivation shows direct effects on next-day hunger hormones and food choices, independent of any calorie target. Similarly, chronic stress and elevated cortisol are associated with increased preference for calorie-dense, highly palatable foods, meaning the “willpower” framing common in diet culture often obscures a genuine physiological headwind rather than a character issue.
  • How to Use It: Before or alongside starting a calorie deficit, strengthen the foundational habits that make the plan easier to sustain. Prioritize consistent, adequate sleep by building a practical midlife sleep routine, and weave a few tiny stress-management habits into your day rather than relying on occasional recovery efforts. It also helps to understand how cortisol affects midlife weight, especially when stress, disrupted sleep, hunger, and changing hormones are working against your weight-loss efforts. This groundwork gives the first four strategies in this article a more stable foundation to work from.

Get 11 Sample Recipes from Our Bestselling Mediterranean Cookbook. 

Get our 11 Sample Recipes from our Best Selling Mediterranean Protein Friendly Cookbook. These are the most delicious recipes our retreat guests love the most. Easy, simple with few ingredients per meal.  Make delicious heart-friendly and healthy meals you enjoy every day. 

How Can You Put the Five Ways Together in a Sample Framework?

Phase

Duration

Focus

Foundation

Weeks 1-2

Establish sleep, stress, and protein habits (Way 5) before adding a significant deficit

Active Phase 1

Weeks 3-8

Moderate calorie deficit, protein and fiber prioritized (Way 2), resistance training 2-3x/week (Way 3)

Diet Break

Weeks 9-10

Return to maintenance calories, continue resistance training (Way 1)

Active Phase 2

Weeks 11-16

Resume deficit, same structure as phase 1

Reverse Diet / Maintenance Transition

Weeks 17-20+

Gradual calorie increase back to maintenance over several weeks (Way 4)

This is a framework to adapt to your own timeline and goals, not a fixed prescription, but it illustrates how the five ways function as a connected system rather than five separate, unrelated tips.

What Does a Normal Plateau Look Like vs. a Sign to Adjust?
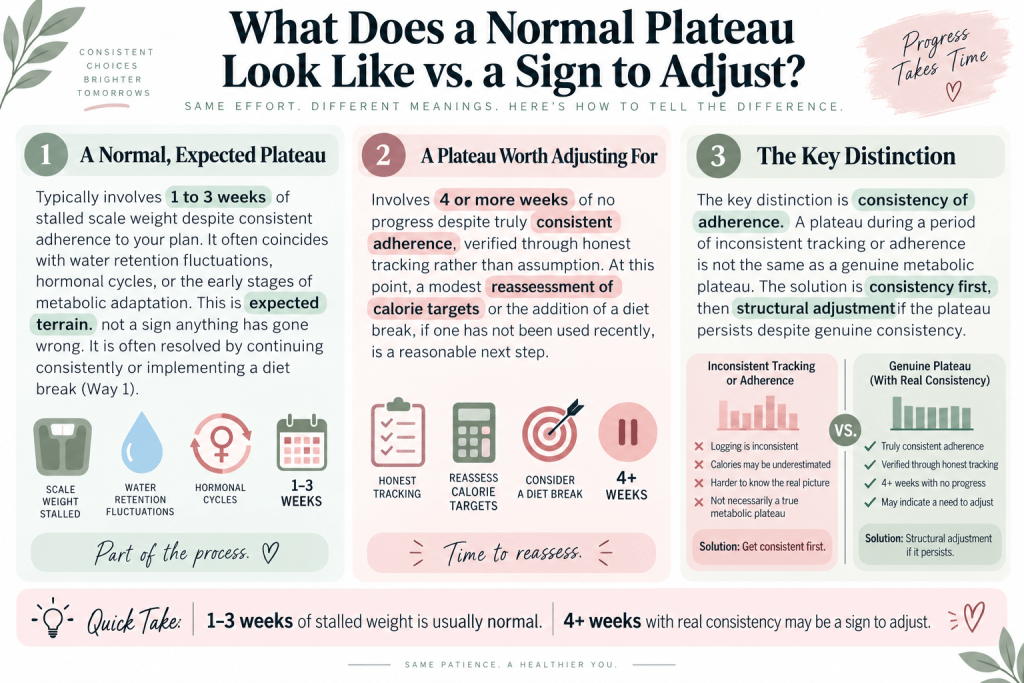
Normal weight loss plateau vs. when to adjust.
  • A normal, expected plateau: Typically involves 1 to 3 weeks of stalled scale weight despite consistent adherence to your plan, often coinciding with water retention fluctuations, hormonal cycles, or the early stages of metabolic adaptation described in Section 1. This is expected terrain, not a sign anything has gone wrong, and is often resolved by continuing consistently or implementing a diet break (Way 1).
  • A plateau worth adjusting for: Involves 4 or more weeks of no progress despite truly consistent adherence, verified through honest tracking rather than assumption. At this point, a modest reassessment of calorie targets (accounting for a lower body weight and any metabolic adaptation) or the addition of a diet break, if one has not been used recently, is a reasonable next step.
  • The key distinction: Is consistency of adherence. A plateau during a period of inconsistent tracking or adherence is not the same phenomenon as a genuine metabolic plateau, and addressing the two requires different responses: consistency first, then structural adjustment if the plateau persists despite genuine consistency.

Get 11 Sample Recipes from Our Bestselling Mediterranean Cookbook. 

Get our 11 Sample Recipes from our Best Selling Mediterranean Protein Friendly Cookbook. These are the most delicious recipes our retreat guests love the most. Easy, simple with few ingredients per meal.  Make delicious heart-friendly and healthy meals you enjoy every day. 

Why Does This Matter More in Perimenopause and Menopause?

The three walls described in Section 1 do not appear only in midlife, but several factors make them more pronounced during the menopause transition specifically.

  • Declining estrogen affects fat distribution and insulin sensitivity: As estrogen changes through perimenopause and menopause, body fat tends to shift toward the abdomen while glucose regulation and insulin sensitivity can also change. These metabolic shifts help explain why weight loss can feel different in midlife, making the broader pattern of perimenopause weight gain important to understand when adjusting nutrition, movement, and recovery strategies.
  • Sleep disruption from night sweats and hormonal shifts compounds Way 5 directly: Since disrupted sleep independently worsens hunger hormone regulation on top of whatever a calorie deficit is already doing.
  • Muscle loss becomes increasingly important through the menopause transition: Declining estrogen and age-related changes in muscle function can make preserving lean mass more challenging in midlife, which makes Way 3—resistance training to protect muscle and metabolic health—especially important during this stage of life.
  • Cortisol and stress patterns often shift during this period: Adding another layer to Way 5 that a midlife dieter is more likely to be navigating than a dieter in their twenties.

None of this means weight loss is not achievable in midlife. It means the five ways in this article, particularly Ways 3 and 5, deserve more emphasis, not less, during this specific life stage.

What Common Mistakes Undo These Strategies?

Common mistakes that can stall weight loss progress.
  • Treating a diet break as a free-for-all: A diet break means eating at maintenance calories with the same food quality standards, not abandoning structure entirely for one to two weeks.
  • Cutting protein first when trying to reduce calories further: Protein is the macronutrient most protective against wall one; reducing it to create a larger deficit tends to backfire by increasing hunger faster than it reduces calories.
  • Skipping resistance training “to save energy” during a deficit: This is precisely backward; resistance training during a deficit is what protects the metabolic rate that makes continued progress possible.
  • Ending a diet abruptly instead of reverse dieting: As covered in Way 4, this is one of the most common and most preventable contributors to rapid regain.
  • Ignoring sleep and stress as “separate issues” from the diet itself: As covered in Way 5, these are not separate from weight loss; they are foundational inputs that determine whether the other four ways can work as intended.

This article is educational and is not a substitute for personalized medical or nutritional advice. Consult a physician or registered dietitian before making significant changes to your eating pattern, particularly if you have an existing health condition.

Get 11 Sample Recipes from Our Bestselling Mediterranean Cookbook. 

Get our 11 Sample Recipes from our Best Selling Mediterranean Protein Friendly Cookbook. These are the most delicious recipes our retreat guests love the most. Easy, simple with few ingredients per meal.  Make delicious heart-friendly and healthy meals you enjoy every day. 

Frequently Asked Questions

Why does weight loss always seem to hit a plateau?

Plateaus result from a combination of a smaller body needing fewer calories to maintain itself and adaptive thermogenesis, where the body actively reduces energy expenditure beyond what smaller size alone predicts. This is a normal, well-documented physiological response, not a sign that your plan or effort has failed.

How long should a diet break last?

Most research-supported protocols use 7 to 14 days at maintenance calories, taken after every 6 to 10 weeks of active caloric restriction.

Why do I get hungrier the longer I diet?

Caloric restriction triggers a rise in ghrelin (hunger hormone) and a drop in leptin (satiety hormone), an evolved response to perceived energy scarcity. This tends to intensify with the length and aggressiveness of the deficit, which is part of why moderate, sustainable deficits combined with adequate protein tend to outperform very aggressive ones over time.

Is weight regain after dieting inevitable?

No, but it is common, particularly when a diet ends abruptly rather than transitioning gradually into a planned maintenance phase (reverse dieting). Regain is best understood as a predictable risk to plan around, not an inevitability.

Why is resistance training important for weight loss, not just muscle building?

Muscle tissue is metabolically active, and preserving it during a calorie deficit protects your resting metabolic rate. Weight loss without resistance training tends to come from a mix of fat and muscle, which lowers metabolic rate more than fat loss alone would.

What is reverse dieting?

Reverse dieting provides a structured way to transition out of a prolonged calorie deficit by gradually increasing food intake toward maintenance. Following a reverse dieting approach can help you make those increases in small, measured steps while monitoring hunger, energy, weight trends, and training performance along the way.

How much protein do I need to reduce hunger during a diet?

Research generally supports 25 to 40 grams of high-quality protein per meal, across three to four meals daily, as an effective target for supporting satiety during a caloric deficit.

Does stress really affect weight loss?

Yes. Chronic stress and elevated cortisol are associated with increased preference for calorie-dense, highly palatable foods and can influence fat storage patterns, making stress management a genuine, evidence-based part of a sustainable weight loss approach rather than a secondary concern.

Is it harder to lose weight during perimenopause and menopause?

Several factors, including declining estrogen’s effects on fat distribution and insulin sensitivity, accelerated muscle loss, and sleep disruption from hormonal changes, can make weight loss more challenging during this transition, which is part of why muscle preservation and sleep management (Ways 3 and 5) deserve extra emphasis during this life stage.

What should I do if I’ve been consistent but still haven’t seen progress in a month?

After verifying genuine consistency (through honest tracking, not assumption), a reasonable next step is reassessing your calorie target to account for your current, lower body weight and any accumulated metabolic adaptation, or implementing a diet break if you have not used one recently.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.

References

  • Byrne, N. M., Sainsbury, A., King, N. A., Hills, A. P., & Wood, R. E. (2018). Intermittent energy restriction improves weight loss efficiency in obese men: The MATADOR study. International Journal of Obesity, 42(2), 129-138.
  • Sumithran, P., Prendergast, L. A., Delbridge, E., Purcell, K., Shulkes, A., Kriketos, A., & Proietto, J. (2011). Long-term persistence of hormonal adaptations to weight loss. New England Journal of Medicine, 365(17), 1597-1604.
  • Weigle, D. S., Breen, P. A., Matthys, C. C., Callahan, H. S., Meeuws, K. E., Burden, V. R., & Cummings, D. E. (2005). A high-protein diet induces sustained reductions in appetite, ad libitum caloric intake, and body weight despite compensatory changes in diurnal plasma leptin and ghrelin concentrations. American Journal of Clinical Nutrition, 82(1), 41-48.
  • Trexler, E. T., Smith-Ryan, A. E., & Norton, L. E. (2014). Metabolic adaptation to weight loss: Implications for the athlete. Journal of the International Society of Sports Nutrition, 11, 7.
  • Josse, A. R., Atkinson, S. A., Tarnopolsky, M. A., & Phillips, S. M. (2011). Increased consumption of dairy foods and protein during diet- and exercise-induced weight loss promotes fat mass loss and lean mass gain in overweight and obese premenopausal women. Journal of Nutrition, 141(9), 1626-1634.
  • Wing, R. R., & Phelan, S. (2005). Long-term weight loss maintenance. American Journal of Clinical Nutrition, 82(1 Suppl), 222S-225S.
  • Spiegel, K., Tasali, E., Penev, P., & Van Cauter, E. (2004). Brief communication: Sleep curtailment in healthy young men is associated with decreased leptin levels, elevated ghrelin levels, and increased hunger and appetite. Annals of Internal Medicine, 141(11), 846-850.
  • Tomiyama, A. J. (2019). Stress and obesity. Annual Review of Psychology, 70, 703-718.
  • Wright, K. E., Skinner, S., & Zhu, S. (2023). The musculoskeletal syndrome of menopause. Climacteric, 26(4), 366-371.

Disclaimer: This article is educational and does not constitute medical or nutritional advice. Weight loss strategies involving calorie restriction, diet breaks, protein targets, resistance training, or changes in eating patterns should be individualized based on your health, medications, activity level, and nutritional needs. If you have a medical condition, a history of disordered eating, are pregnant or breastfeeding, or experience persistent fatigue, dizziness, weakness, or other concerning symptoms while attempting weight loss, consult a physician or registered dietitian before following the strategies in this article.

Get 11 Sample Recipes from Our Bestselling Mediterranean Cookbook. 

Get our 11 Sample Recipes from our Best Selling Mediterranean Protein Friendly Cookbook. These are the most delicious recipes our retreat guests love the most. Easy, simple with few ingredients per meal.  Make delicious heart-friendly and healthy meals you enjoy every day. 

Reverse Dieting After Menopause: The Science-Backed Plan to Eat More and Lose Weight

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

If you’re eating less than your 20-year-old niece, walking more than your husband, and still watching the scale creep up — this article is for you. I hear this story every single week in our coaching calls and at every Midlife Method workshop: “I’m barely eating, Terry, and I’m still gaining weight. What is wrong with me?”

Nothing. Nothing is wrong with you. Your metabolism is doing exactly what it’s designed to do when it’s been underfed for years. It’s downshifted. It’s defensive. And it’s waiting for you to tell it that food is safe again.

Reverse dieting after menopause is the process of doing that. Slowly, deliberately, and with math — not vibes — you add food back into your life until your metabolism wakes up, your hormones calm down, and your body stops clinging to every calorie like it’s preparing for a famine. It is one of the most counterintuitive, most powerful tools we teach at THOR, and almost nobody is talking about it in the mainstream menopause conversation. Let’s fix that.

This is a long article. Get comfortable. By the end, you’ll know what reverse dieting actually is, why it matters more after 50 than at any other point in your life, the exact macro framework to use, and a week-by-week plan you can start on Monday.

What Is Reverse Dieting (And Why It’s Not a Diet at All)

Let’s get the definition straight first, because the name is confusing. Reverse dieting isn’t a diet in the cut-calories, shrink-your-body sense. It’s a structured protocol for slowly increasing your calorie intake after a long period of under-eating, so that your metabolism can adapt upward instead of staying parked in survival mode.

Here’s the analogy I use at our retreats. Imagine your metabolism is a thermostat. When you cut calories for months or years, the thermostat quietly drops its setting. Your body burns less energy at rest. Your thyroid slows. Your cortisol rises. Your hunger hormones get noisy, then go silent. The whole system recalibrates for less food — and that’s not a bug, that’s a feature. It’s how humans survived famines.

The problem is, you’re not in a famine. You’re just on diet number 17 since you turned 30, and your thermostat has been dropping a little further each time. Reverse dieting is the opposite process. You add a small amount of food each week, and you let your thermostat nudge itself back up.

The concept isn’t new. Physique athletes and bodybuilders have been using reverse dieting for decades to recover from competition prep. What’s new is applying it to women 40+ who’ve spent their whole adult lives under-eating, especially after menopause when the hormonal context makes the whole problem worse. A 2014 review published in Nutrition & Metabolism by Trexler and colleagues — “Metabolic adaptation to weight loss: implications for the athlete” — laid out the mechanism. When you restrict calories for extended periods, your resting metabolic rate drops by more than can be explained by weight loss alone. That gap between predicted and actual metabolic rate is called adaptive thermogenesis, and it can persist for years after the diet ends.

If you’ve already read our piece on the fundamentals of macro diet for women over 50, you have the macro framework. Reverse dieting is the part that comes before or after cutting. It’s the bridge from a suppressed metabolism to a functional one.

Why Reverse Dieting Matters More for Women Over 50

The reason this matters so much for midlife women — and not as much for a 25-year-old — is the hormonal context of menopause. When your estrogen drops, several things shift at once. Your insulin sensitivity falls. Your body becomes more efficient at storing fat, especially visceral fat around your middle. Your muscle protein synthesis slows. And your cortisol rhythm gets disrupted, which raises your baseline blood sugar and makes your body cling to calories even harder.

Now add decades of under-eating on top of that. Most women I coach have been running on 1,200 to 1,400 calories a day since their twenties. They’ve done Weight Watchers, Noom, keto, intermittent fasting, 75 Hard, juice cleanses, and maybe two bouts of full-on caloric restriction. Each round trained their metabolism to do more with less.

By the time menopause arrives, their body is running at maybe 1,300 resting calories when it should be closer to 1,500–1,600. Their thyroid panel looks “normal” but sluggish. Their sleep is trash. Their cravings are constant. And when they cut more calories — because that’s what they’ve always done — they gain weight. Because now they’re under-fueled in the context of already-low estrogen, and their body pulls every protective lever it has.

The Rosenbaum and Leibel research out of Columbia University published in the International Journal of Obesity in 2010 — “Adaptive thermogenesis in humans” — showed that people who had lost weight and kept it off burned 300 to 400 fewer calories per day than people of the same body weight who had never dieted. Three to four hundred calories. For years. That’s the metabolic debt your body carries.

Reverse dieting is the checkout line for that debt. You pay it back with food.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

The Real Science of Metabolic Adaptation in Menopause

Let’s get into the weeds for a minute, because understanding what’s actually happening in your body is the difference between trusting the process and quitting in week two when the scale goes up.

When you chronically under-eat, five measurable things happen:

Resting metabolic rate drops. Your body uses less energy at rest. This is partly because you’re smaller, but partly — and this is the adaptive thermogenesis piece — for reasons above and beyond body size. A classic 2009 study on the Biggest Loser contestants, published in the American Journal of Clinical Nutrition by Johannsen and colleagues, found that six years after the show, contestants’ resting metabolic rates were on average 500 calories per day lower than predicted. Six years.

Thyroid hormones shift. Specifically, active T3 drops and reverse T3 rises. Your TSH might still look fine on a lab, but the actual thyroid activity is muted. This is a survival mechanism. Your body is conserving energy. In menopause, when your thyroid is already under hormonal pressure from dropping estrogen, this adaptation hits harder.

Leptin falls, ghrelin rises. Leptin is your “I’m full” hormone. Ghrelin is your “I’m hungry” hormone. When you restrict, leptin tanks and ghrelin climbs. The result is constant low-grade hunger that doesn’t match your energy needs. This is why dieting feels like a psychological war.

Non-exercise activity thermogenesis (NEAT) drops. Under-fed bodies fidget less, stand less, walk less, gesture less. You don’t notice it, but your step count falls, your posture slouches, and the tiny background movements that burn hundreds of calories a day quietly disappear. Research by Levine et al. at Mayo Clinic demonstrated this effect — NEAT can account for up to 2,000 calories per day of variance between people, and it is highly responsive to energy availability.

Sex hormones suppress further. In premenopausal women, chronic low calorie intake can push menstrual cycles into hypothalamic dysfunction. In perimenopausal and menopausal women, it amplifies every symptom — worse hot flashes, worse sleep, worse mood, worse libido. The body reads low food as threat, and threat is not the context in which it wants to run reproductive and vitality systems at full capacity.

The Seattle Midlife Women’s Health Study, a landmark longitudinal project published in PMC (PMC2749064) and running for nearly two decades, documented the way these metabolic and hormonal shifts compound across the menopause transition. Women who entered the transition with a history of chronic dieting had worse symptom trajectories than women who hadn’t.

The takeaway: you cannot restrict your way out of a restricted metabolism. You have to feed it back up.

How to Know If You Need to Reverse Diet

Before we get into the how, let’s talk about who. Not every woman needs to reverse diet. Some are genuinely over-fed and need to recalibrate downward. Others are in the maintenance zone and just need better protein and more sleep. But if any of these sound familiar, reverse dieting is probably the missing piece:

You’re eating under 1,500 calories a day and not losing weight. You’ve been “dieting” for more than six months continuously. Your energy is low and you’re cold all the time. Your hair is shedding more than it used to. Your periods have become irregular (if you’re still cycling) or your hot flashes have gotten worse (if you’re not). Your workouts feel harder than they should. Your cravings for sugar or salt are relentless. Your digestion has slowed. Your sleep is broken. You’ve tried to “eat clean and move more” for years, and the body composition won’t budge.

All of those are signals that your metabolism is hunkered down. A reverse diet won’t fix them overnight, but over 8 to 16 weeks, it can fundamentally change what your baseline looks like.

If you’re not sure whether you fit this profile, the free macro calculator at THOR is the fastest way to find out. Plug in your age, weight, activity level, and goal. If the calculator’s maintenance number is significantly higher than what you’ve been eating, you’re probably a candidate. (It also gives you a starting macro breakdown, so it’s the first step in the reverse diet plan I’m about to walk you through.)

The Step-by-Step Reverse Dieting Plan for Women Over 40

Here’s the protocol we use with our coaching clients. It’s conservative on purpose. Women over 40 respond better to slow, patient progression than to aggressive calorie additions, because the hormonal context means any “pressure” feels like threat, and threat keeps the body defensive.

Week 0: Baseline. Before you change anything, track what you’re actually eating for three to five days. Not what you think you eat. What you actually eat. Use a food tracker — Cronometer, MacroFactor, or whatever you already have. Weigh or measure. This sounds tedious, and it is, but you can only reverse from a baseline you actually know. Also record: morning weight (same conditions each day), menstrual cycle phase if relevant, sleep hours, hot flash frequency, and a 1–10 energy score.

Weeks 1–2: Add protein first. Before you add any other food, get your protein to 0.8 to 1 gram per pound of goal body weight. For most women over 40, that’s between 100 and 140 grams per day. This alone often triggers 2 to 3 pounds of water weight gain in the first two weeks — that’s glycogen replenishing in your muscles. It is not fat gain. Breathe.

Weeks 3–6: Add carbs slowly. Increase your total daily calories by about 50 to 75 calories per week, and put almost all of those new calories into carbohydrates. Yes, carbs. Your thyroid, your ovaries, and your brain all need glucose to run well, and they’ve been running on fumes. Add a palm-sized portion of rice, sweet potato, fruit, or oats to one meal. Track weight. Track how you feel.

Weeks 7–10: Dial in fats. Once carbs are in a reasonable range — say, 150 to 200 grams per day depending on your body — add 5 to 10 grams of fat per week. Healthy fats. Avocado, olive oil, nuts, fatty fish, eggs. Fat matters for hormone production, especially the sex hormones that are already struggling in menopause.

Weeks 11–16: Stabilize and assess. By this point you should be eating hundreds more calories than you started with. You should be sleeping better. Your energy should be steadier. Your mood should be calmer. If the scale has moved up a few pounds, that’s normal. If it’s moved up 10, you added too fast and we back off. If it’s stayed the same or gone down, your metabolism was even more suppressed than we thought, and we continue the reverse for another cycle.

The key is patience. A real reverse diet takes three to four months. Anyone promising you a two-week version is selling you something.

The Best Macros for Menopause Weight Loss During a Reverse Diet

Let’s talk numbers. There’s no single macro split that works for every woman, but there’s a defensible range that matches the physiology of menopause. Here’s the framework we use:

Protein: 30–35% of calories, or 0.8–1 gram per pound goal body weight. Menopausal women are more anabolically resistant — meaning you need more protein to trigger the same muscle protein synthesis a younger woman gets from less. This is consistent with research by Moore and colleagues published in the Journals of Gerontology, which found that older adults need roughly 40% more leucine per meal than younger adults to maximally stimulate muscle protein synthesis. Spread protein across four meals at roughly 30 grams each.

Carbohydrates: 40–45% of calories. Yes, really. Contrary to internet keto mythology, carbohydrates are not the enemy in menopause. They support thyroid conversion (T4 to active T3), cortisol regulation, serotonin production, and muscle glycogen. The menopausal liver is more insulin-resistant, so quality matters — slow carbs from whole foods over fast carbs from packaged food — but the total amount should be substantial.

Fats: 25–30% of calories. Enough to support hormone production, fat-soluble vitamin absorption, and satiety — but not so much that carbs get crowded out. The research on low-carb high-fat diets in menopausal women is mixed; the research on adequate carbs plus adequate protein is consistent.

If you want the exact numbers for your body, run them through the THOR macro calculator. It’s built specifically for women 40+, and it defaults to the menopause-friendly ratios above instead of the generic bodybuilder splits most online calculators use.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

What to Expect Week by Week During a Reverse Diet

Let me walk you through what actually happens in a body during a reverse, because the psychological piece is as important as the physical.

Week 1. You feel fine. Protein is up, nothing else changed much. You might notice slightly better energy by the end of the week.

Week 2. The scale goes up 1 to 3 pounds. This is glycogen and water. You panic. You tell your coach you knew this wouldn’t work. Your coach tells you to drink more water and keep going.

Weeks 3–4. Carbs are climbing. Your workouts start to feel stronger. You’re recovering faster. Your hair is still shedding because hair takes months to respond, but you’ll notice the regrowth in month 4.

Weeks 5–6. You start sleeping better. Most women notice deeper sleep in this window. Hot flashes may not disappear, but they often decrease in intensity.

Weeks 7–8. Your body starts to shift. Weight may stabilize or even drop a little. Body composition shifts — you look leaner even at the same weight. Your clothes fit differently. Your husband asks if you’ve been working out more. You haven’t.

Weeks 9–12. Mood and cognitive stability improve. Brain fog lifts. Your cravings calm down because you’re eating enough. Your libido may start to wake up.

Weeks 13–16. You’re eating 400 to 700 more calories a day than when you started, and you weigh roughly what you weighed at the beginning — or less. Your resting metabolic rate is higher. Your thyroid panel looks better if you retest. Your life is easier because eating is easier.

This is not a marketing story. This is what the research on refeeding after chronic caloric restriction consistently shows, and it is what we watch play out in our clients week after week.

Common Mistakes to Avoid When Reverse Dieting After Menopause

Three mistakes I see over and over, and how to avoid each.

Mistake 1: Going too fast. The temptation to add 200 calories in week two is real. Don’t. The whole point of a reverse is to nudge your metabolism up without triggering your fat storage machinery. Adding too fast puts the fat storage machinery right back in business, and you’ll gain weight you didn’t need to.

Mistake 2: Not tracking. You cannot reverse from a vibe. You have to know your baseline and your weekly numbers. You don’t have to track forever — most of our coaching clients stop tracking around month 4 — but you absolutely have to track during the reverse.

Mistake 3: Adding crap food. A reverse diet is not permission to eat cookies. The extra calories should come from nutrient-dense, whole-food sources that support hormone health. Protein first, then quality carbs, then good fats. This is where cookbooks become your best friend — our THOR cookbook series has macro-specific recipes that hit the right ratios without turning you into a meal-prep monk.

If any of this feels overwhelming, that’s what 1:1 coaching is for. A good coach makes the difference between a reverse that works and one that spirals. We’ve walked hundreds of women through this exact protocol at THOR.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

How Reverse Dieting Fits with Strength Training in Midlife

One thing I want to make explicit: reverse dieting without strength training is a missed opportunity. The reason your metabolism dropped is partly adaptive thermogenesis, but it’s also partly muscle loss. You’ve lost muscle every year since your mid-thirties, and more of it through perimenopause. Reverse dieting restores the energy environment your body needs to rebuild that muscle — but only if you give it a reason to.

The reason is resistance training. Three to four sessions a week. Heavy enough that the last two reps are hard. Compound movements. Progressive overload. This is what signals the body to actually use the new calories for something productive instead of storing them.

If you’re not sure how to start, our benefits of jumping piece covers the plyometric and rebounding side of training that supports bone density, and our diet break post covers the shorter cousin of reverse dieting. The combination of feeding up, lifting heavy, and recovering well is what rebuilds a midlife body.

How Long Does Reverse Dieting After Menopause Take?

The honest answer is 12 to 16 weeks for most women, and 6 to 9 months for some. It depends on how long you were under-eating, how suppressed your metabolism became, and how patient you are with the process. Women who came from a few years of moderate dieting might wrap up in 10 weeks. Women who’ve been cycling through 1,200-calorie diets since their twenties may need longer.

One more piece. Reverse dieting is a protocol, not a permanent state. Once your metabolism is restored and you’re eating at a real maintenance level, you can choose what comes next. Maybe you stay there for a while to enjoy actually eating food. Maybe you do a short cut to lose the five pounds you want off. Maybe you start training for a retreat and want to feel your strongest.

The point is, you get your options back. A suppressed metabolism takes options away. A restored one hands them back.

Frequently Asked Questions About Reverse Dieting After Menopause

Will I gain weight during a reverse diet?

Probably 1 to 4 pounds, mostly water and glycogen. Some women gain a little more if they add calories too fast. A well-executed reverse produces minimal fat gain and often improves body composition over the 12 to 16 weeks, even at a slightly higher scale weight.

How much should I eat to start a reverse diet?

Start exactly where you are. The first move is not a calorie change — it’s a protein prioritization. Get protein to 0.8 to 1 gram per pound of goal body weight first, hold total calories constant, then start adding in week three.

Can I reverse diet if I’m on HRT?

Yes. Hormone replacement therapy doesn’t change the mechanics of metabolic adaptation, though it can make the reverse feel easier because sleep and cortisol regulation are often better on HRT. Talk to your prescriber about any concerns, but there’s no contraindication to reverse dieting alongside HRT.

How do I know when the reverse diet is done?

When you’ve been eating at the new, higher calorie level for 3 to 4 weeks with stable weight, good energy, good sleep, and no new body composition concerns. That’s your new maintenance. Some women then hold there. Some then do a brief, controlled cut. Some add more food because their metabolism keeps responding. There’s no single endpoint — there’s a new baseline.

Is reverse dieting safe for women over 60?

Yes, with the same protocol. Older women may need to go even slower on the additions and focus more on protein quality. If you have any diagnosed metabolic condition, work with a coach or registered dietitian rather than doing it solo.

How does reverse dieting differ from a diet break?

A diet break is a short pause — usually one to two weeks — at maintenance calories in the middle of a cut. It helps manage the psychological and hormonal strain of extended restriction, but it doesn’t fundamentally reset a suppressed metabolism. A reverse diet is the longer, structured process of actually raising that baseline.

Can I reverse diet if I’m still trying to lose weight?

Counterintuitively, yes. Women who reverse diet first and then enter a mild cut from a higher baseline lose weight faster, keep muscle better, and rebound less than women who cut from an already-suppressed state. The reverse is an investment, not a detour.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

What should I eat on a reverse diet?

Whole-food protein sources (lean meat, fish, eggs, Greek yogurt, cottage cheese), quality carbs (rice, oats, potatoes, fruit, legumes), and healthy fats (avocado, olive oil, nuts, fatty fish). Keep ultra-processed foods in the 10% range they’ve always belonged in. Our cookbook has macro-mapped recipes if you need a starting point.

How much water should I drink during a reverse diet?

Half your body weight in ounces, as a floor. The extra glycogen your muscles are storing binds water, and your kidneys appreciate the help. Most women over 40 are under-hydrated to begin with.

Why does reverse dieting work for menopause weight loss when regular dieting doesn’t?

Because regular dieting, in the context of an already-suppressed metabolism, deepens the suppression. Reverse dieting restores the metabolic capacity you need to eventually diet effectively. It’s a “sharpen the saw” step most people skip.

Do I need to count macros to reverse diet?

For the first 12 to 16 weeks, yes. You don’t have to count forever, but you need precision during the reverse because the whole point is controlled, measured additions. Eyeballing doesn’t work here. The THOR macro calculator gives you the starting targets, and any tracking app can keep you honest.

Can I do intermittent fasting while reverse dieting?

It’s possible, but not ideal. Tight eating windows make it harder to hit the protein targets a reversing metabolism needs, and the meal spacing benefits of intermittent fasting tend to be less relevant when the bigger goal is restoration. Once your metabolism is back online, you can experiment with windows again if you like them.

What role does strength training play during a reverse diet?

Central. Without resistance training, the extra calories you’re adding risk being partitioned toward fat. With it, they get partitioned toward muscle, which then raises your resting metabolic rate, which then lets you eat even more. Three to four heavy sessions a week is the minimum.

How do I keep from panicking when the scale goes up?

Track more than the scale. Photos. Measurements. Strength numbers in the gym. Sleep quality. Energy scores. Hot flash frequency. If the majority of those metrics are moving in the right direction, the scale is noise. A reverse diet is one of the rare cases where weight is genuinely the least informative number you can track.

Will reverse dieting fix my hot flashes?

Not directly. But it often reduces their frequency or intensity by stabilizing cortisol, blood sugar, and sleep. Those three things are the usual suspects behind hot flash spikes, and all three improve with adequate fueling.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

Your Next Step After Menopause Reverse Dieting

Here’s the bottom line. If you’ve been eating less and less and less for years, and your body has stopped responding, the answer is not to eat even less. The answer is to slowly, patiently, scientifically teach your body that food is safe again.

Start with the free THOR macro calculator. Get your numbers. Plan your protein. Start tracking your baseline. That’s week zero.

If you want someone walking you through it week by week, our 1:1 coaching program is built for exactly this situation, and our Midlife Method workshop series (next round at our Clinton, NJ studio) covers the full framework in six weeks. We’ve coached hundreds of women through the reverse. The ones who stuck it out for 12 to 16 weeks tell us the same thing on the other side: “I eat more than I ever have, and I feel like I did at 35.”

That’s the whole point. You don’t have to shrink your life to fit a smaller metabolism. You can rebuild the metabolism to fit the life you want.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.


Sources and Further Reading

  1. Trexler, E. T., Smith-Ryan, A. E., & Norton, L. E. (2014). Metabolic adaptation to weight loss: implications for the athlete. Journal of the International Society of Sports Nutrition, 11, 7. https://pubmed.ncbi.nlm.nih.gov/24571926/
  2. Rosenbaum, M., & Leibel, R. L. (2010). Adaptive thermogenesis in humans. International Journal of Obesity, 34(Suppl 1), S47–S55. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3673773/
  3. Fothergill, E., Guo, J., Howard, L., et al. (2016). Persistent metabolic adaptation 6 years after “The Biggest Loser” competition. Obesity, 24(8), 1612–1619. https://pubmed.ncbi.nlm.nih.gov/27136388/
  4. Johannsen, D. L., Knuth, N. D., Huizenga, R., et al. (2012). Metabolic slowing with massive weight loss despite preservation of fat-free mass. Journal of Clinical Endocrinology & Metabolism, 97(7), 2489–2496. https://pubmed.ncbi.nlm.nih.gov/22535969/
  5. Woods, N. F., & Mitchell, E. S. (2005). Symptoms during the perimenopause: prevalence, severity, trajectory, and significance in women’s lives (Seattle Midlife Women’s Health Study). American Journal of Medicine, 118(12B), 14S–24S. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2749064/
  6. Moore, D. R., Churchward-Venne, T. A., Witard, O., et al. (2015). Protein ingestion to stimulate myofibrillar protein synthesis requires greater relative protein intakes in healthy older versus younger men. Journals of Gerontology: Series A, 70(1), 57–62. https://pubmed.ncbi.nlm.nih.gov/25056502/
  7. Levine, J. A. (2002). Non-exercise activity thermogenesis (NEAT). Best Practice & Research Clinical Endocrinology & Metabolism, 16(4), 679–702. https://pubmed.ncbi.nlm.nih.gov/12468415/
  8. MacLean, P. S., Bergouignan, A., Cornier, M. A., & Jackman, M. R. (2011). Biology’s response to dieting: the impetus for weight regain. American Journal of Physiology: Regulatory, Integrative and Comparative Physiology, 301(3), R581–R600. https://pubmed.ncbi.nlm.nih.gov/21677272/
  9. Stiegler, P., & Cunliffe, A. (2006). The role of diet and exercise for the maintenance of fat-free mass and resting metabolic rate during weight loss. Sports Medicine, 36(3), 239–262. https://pubmed.ncbi.nlm.nih.gov/16526835/
  10. Mauvais-Jarvis, F., Clegg, D. J., & Hevener, A. L. (2013). The role of estrogens in control of energy balance and glucose homeostasis. Endocrine Reviews, 34(3), 309–338. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3660717/
  11. North American Menopause Society. (2022). The 2022 Hormone Therapy Position Statement of The North American Menopause Society. Menopause, 29(7), 767–794. https://pubmed.ncbi.nlm.nih.gov/35797481/