Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

The Mitochondria and Fascia Connection: What Midlife Women Need to Know About Cellular Energy, Fascial Restriction, and the Six Practices That Serve Both

Mitochondria and fascia are two closely connected systems in midlife women’s health, yet they are rarely discussed together. Most advice treats low energy as a mitochondrial issue and stiffness as a fascial issue. This guide explains how the two systems influence each other and why supporting both can improve energy, mobility, and recovery.

During perimenopause and menopause, declining estrogen can reduce mitochondrial energy production while also affecting fascial hydration, elasticity, and connective tissue health. These changes are not simply happening at the same time. Fascial cells need mitochondrial energy to maintain healthy tissue and produce the hyaluronic acid that supports smooth movement, while mitochondria benefit from the circulation, movement, and mechanical environment provided by healthy fascia.

I am Terry Tateossian, founder of The House of Rose and a certified lifestyle medicine coach. After experiencing early-onset menopause at 41, an 80-pound midlife body composition shift, and decades of balancing business and family life, mitochondrial support and fascia work became central to my recovery. They now form an important part of what I teach through coaching and at our women’s yoga & wellness retreats in the Smoky Mountains. This guide explains how mitochondria and fascia work, why their connection matters during midlife, and the six daily practices that support both systems.

Important: Consult your healthcare provider before beginning a new movement, nutrition, or supplement program, especially if you have a chronic condition, take multiple medications, or experience persistent unexplained fatigue or muscsuloskeletal restriction.

What Are Mitochondria?

Mitochondria are the specialized structures inside almost every cell of the human body that produce the energy each cell uses to do its work. Understanding what mitochondria do, and why their function matters at the whole-body level, is the foundation for understanding the fascial connection that follows.
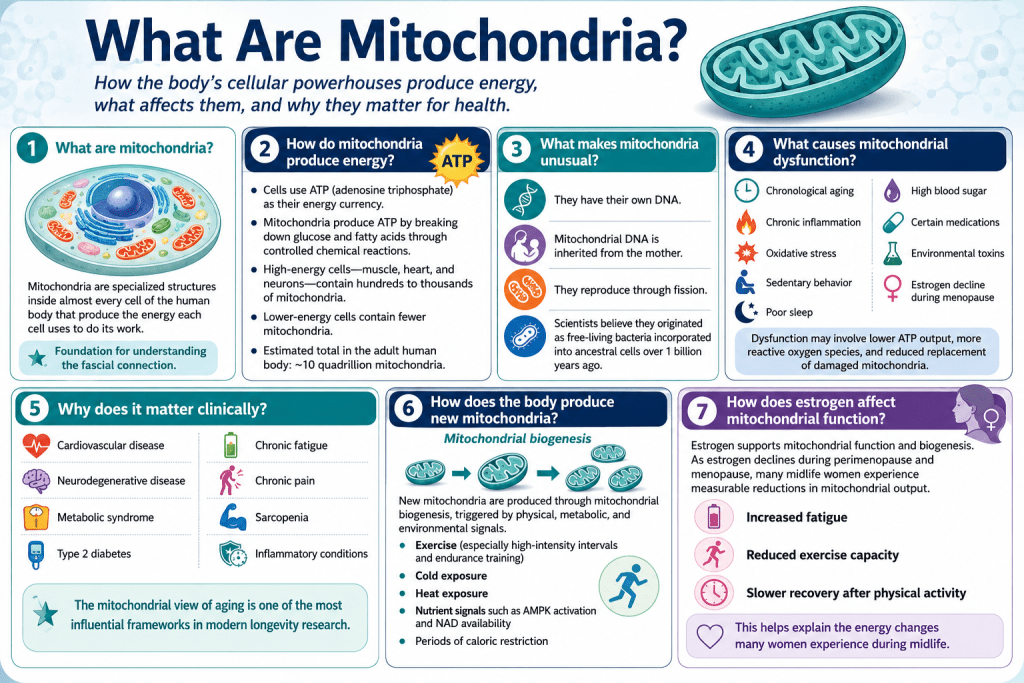
Mitochondria energy and health infographic.

How Do Mitochondria Produce Energy?

Every cell needs energy to function. Muscle cells need energy to contract, neurons need energy to fire, and fascial cells need energy to synthesize collagen and hyaluronic acid.

The specific energy currency cells use is a molecule called ATP, or adenosine triphosphate. Mitochondria are the primary organelles that produce ATP by breaking down glucose and fatty acids through a controlled series of chemical reactions.

The number of mitochondria in each cell varies dramatically by cell type:

  • High-energy cells, including muscle cells, heart cells, and neurons, contain hundreds to thousands of mitochondria.
  • Cells with lower energy demands contain fewer mitochondria.
  • The total number of mitochondria in an adult human body is estimated at approximately ten quadrillion.

What Makes Mitochondria Biologically Unusual?

Mitochondria have their own DNA, which is inherited from the mother. They also reproduce through a process called fission.

Scientists believe mitochondria originated as free-living bacteria that were incorporated into ancestral cells more than a billion years ago. This unusual biology has significant implications for how mitochondria respond to injury, aging, and environmental stress.

What Causes Mitochondrial Dysfunction?

Several factors can reduce mitochondrial number or impair mitochondrial function, including:

  • Chronological aging
  • Chronic inflammation
  • Oxidative stress
  • Sedentary behavior
  • Poor sleep
  • High blood sugar
  • Certain medications
  • Environmental toxins
  • Estrogen decline during menopause

Mitochondrial dysfunction can appear as reduced ATP output per cell, increased leakage of reactive oxygen species, and a reduced ability to replace damaged mitochondria. These changes can create downstream effects across nearly every tissue in the body.

Why Does Mitochondrial Dysfunction Matter Clinically?

Mitochondrial dysfunction has been implicated in many major chronic diseases and conditions associated with aging, including:

  • Cardiovascular disease
  • Neurodegenerative disease
  • Metabolic syndrome
  • Type 2 diabetes
  • Chronic fatigue
  • Chronic pain
  • Sarcopenia
  • Inflammatory conditions

The mitochondrial view of aging has therefore become one of the most influential frameworks in modern longevity research.

How Does the Body Produce New Mitochondria?

New mitochondria are produced through a process called mitochondrial biogenesis. This process is triggered by specific physical, metabolic, and environmental signals, including:

  • Exercise, particularly high-intensity intervals and endurance training
  • Cold exposure
  • Heat exposure
  • Nutrient signals such as AMPK activation and NAD availability
  • Periods of caloric restriction

Understanding what drives mitochondrial biogenesis is central to the practical intervention framework discussed later in this article.

How Does Estrogen Affect Mitochondrial Function?

Estrogen supports mitochondrial function and biogenesis through multiple mechanisms. As estrogen declines during perimenopause and menopause, many midlife women experience measurable reductions in mitochondrial output.

These changes can appear as:

  • Increased fatigue
  • Reduced exercise capacity
  • Slower recovery after physical activity

This relationship between estrogen and mitochondrial function is one of the specific mechanisms behind the energy changes many women experience during midlife.

What Is Fascia?

Fascia is the connective tissue network that surrounds every muscle, wraps every organ, and forms continuous sheets that link every body region to every other body region. A brief refresh of what fascia is provides the foundation for the mitochondrial connection that follows.

  • The physical structure: Fascia is a web of collagen and elastin fibers embedded in a fluid ground substance. Healthy fascia is pliable, well-hydrated, and glides smoothly against itself and against adjacent tissues. Restricted fascia becomes stiffer, less hydrated, and stuck to itself and to nearby structures.
  • The whole-body network: Fascia is not just a passive wrapping. It transmits force through the body, contributes to posture, participates in movement, and communicates mechanical information from one region to another. When you feel tension in a shoulder that is driven by restriction in the opposite hip, fascia is often the transmission line.
  • The specific cells within fascia: Two cell types matter most for this article. Fibroblasts are the primary cells that produce collagen and other structural components of fascia. Fasciacytes are a specialized cell type identified more recently, located primarily at the interfaces between fascial layers, that produce hyaluronic acid and contribute significantly to the glide function of healthy fascia.
  • The living function: Fascia is not inert. It is metabolically active, densely innervated by sensory nerves, integrated with the lymphatic system, involved in immune signaling, and continuously remodeling in response to load, movement, injury, and inflammation.
  • What restriction looks like: Restricted or fibrotic fascia is common in midlife women. It shows up as chronic tightness that does not resolve with stretching, reduced range of motion, felt-sense of being physically stuck, altered posture, restricted breath, and reduced tolerance for movement.
  • The specific midlife pattern: Perimenopause and menopause accelerate fascial restriction through multiple mechanisms including estrogen decline (which affects connective tissue composition), reduced hydration (which affects the ground substance), reduced movement (which affects tissue remodeling), and increased inflammation (which drives fibrotic changes).

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Do Mitochondria and Fascia Influence Each Other?

The connection between mitochondrial function and fascial health is bidirectional, meaning each system influences the other in ways that produce a self-reinforcing loop when one starts to fail.

How Do Mitochondria Affect Fascia?

The cells of fascia, particularly fibroblasts and fasciacytes, depend on mitochondrial ATP to do their work. Several essential fascial processes require energy:

  • Synthesizing collagen
  • Producing hyaluronic acid
  • Maintaining fascia in a pliable, hydrated, and functional state

When mitochondrial output declines in fascial cells, these processes slow down. Over months and years, the result is fascia that becomes less mobile, less hydrated, and more prone to fibrotic changes.

How Does Fascia Affect Mitochondria?

The mechanical, thermal, and circulatory environment of the tissues significantly affects mitochondrial function. Healthy fascia supports:

  • Adequate blood flow and lymphatic circulation
  • The delivery of oxygen and nutrients to mitochondria
  • The removal of metabolic waste
  • Mechanotransduction signaling through healthy movement and appropriate fascial loading

Restricted fascia impairs blood flow and lymphatic circulation, which can reduce mitochondrial function. Healthy movement and appropriately loaded fascia also support mitochondrial biogenesis. In contrast, sedentary bodies with restricted fascia signal for fewer new mitochondria over time.

How Does the Reinforcing Loop Develop?

These two directions form a self-reinforcing loop:

  1. Mitochondrial decline reduces fascial cell function.
  2. Reduced fascial cell function decreases fascial mobility.
  3. Lower fascial mobility reduces circulation and mechanotransduction.
  4. Reduced circulation and mechanotransduction further impair mitochondrial function.

This loop is one of the specific mechanisms behind the pattern of accelerating stiffness, fatigue, and physical decline that many midlife women recognize.

Where Can the Loop Be Interrupted?

The loop is not one-way. Interventions that improve mitochondrial function often improve fascial mobility over time. Interventions that improve fascial mobility can also improve local mitochondrial function.

This is the practical reason the two systems should be addressed together rather than separately. It is also where the six-practice framework in Section 9 gets its power.

What Does the Research Show?

The specific bidirectional connection is still an active area of research. Some elements are well-established:

Other elements are still being mapped in detail. The overall framework is supported by the current literature, although specific quantitative predictions have not yet been fully worked out.

“The moment this connection clicked for me in coaching was watching a client who had been working diligently on strength training and nutrition for six months without seeing the energy return she was hoping for. Her body composition was improving. Her sleep was better. But she still felt exhausted and stiff in a way that did not match her behavioral changes. When we added daily body-based work that targeted her fascia (a combination of foam roller, targeted release, and slow flowing movement), her energy started shifting within four weeks. It was not more calories, more supplements, or more sleep. It was addressing the fascial restriction that was throttling the mitochondrial supply chain in the tissues her strength work depended on. That experience is what convinced me that the two systems have to be worked together. Working on one without the other leaves progress on the table.”

Terry Tateossian, Founder of The House of Rose

How Does Menopause Accelerate Dysfunction in Both Systems?

Perimenopause and menopause accelerate dysfunction in both the mitochondrial and fascial systems, and the acceleration happens through overlapping mechanisms.
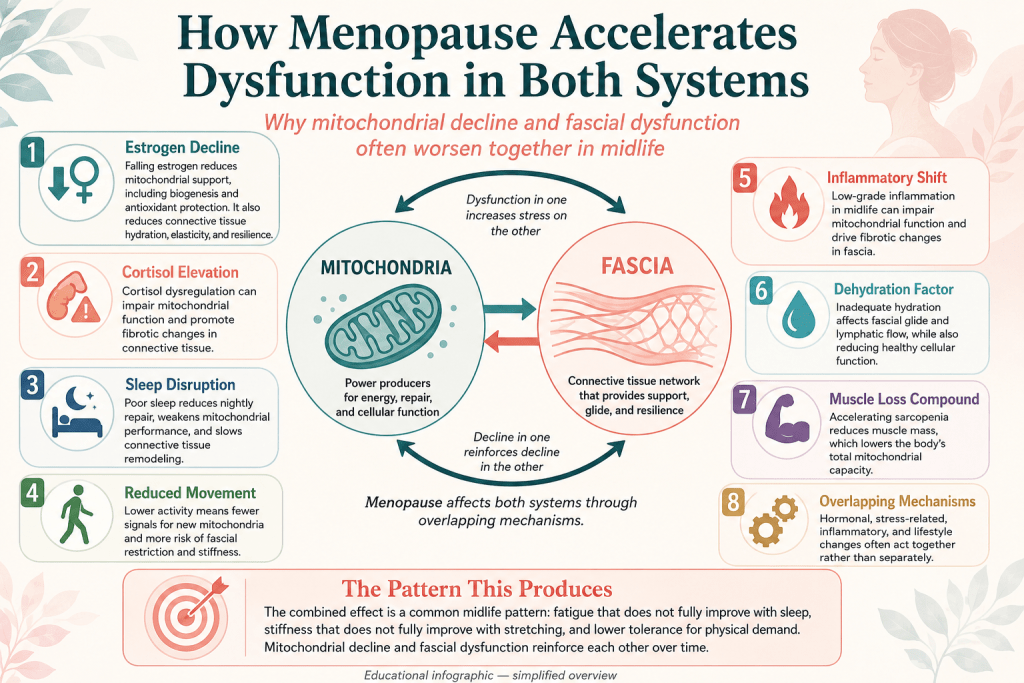
Menopause effects on mitochondria and fascia.
  • The estrogen decline: Estrogen has direct effects on both mitochondrial function and fascial tissue. Estrogen supports mitochondrial biogenesis, mitochondrial membrane function, and the antioxidant defenses that protect mitochondria from oxidative damage. Estrogen also supports connective tissue composition, hydration, and elasticity. As estrogen falls through the menopause transition, both systems lose one of their major supportive signals.
  • The cortisol elevation: Perimenopause and menopause are frequently accompanied by cortisol dysregulation. Elevated cortisol directly impairs mitochondrial function through several mechanisms and also drives fibrotic changes in connective tissue. See our cortisol and menopause weight gain article for the broader cortisol picture.
  • The sleep disruption: The sleep disruption of perimenopause and menopause reduces the nightly repair that both systems depend on. Poor sleep reduces mitochondrial function and impairs the connective tissue remodeling that maintains fascial health.
  • The reduced movement: Many midlife women reduce activity levels through the perimenopause and menopause window, sometimes due to fatigue, sometimes due to joint pain, sometimes due to life circumstances. Reduced movement signals for both fewer new mitochondria and more fascial restriction.
  • The inflammatory shift: Midlife often produces a low-grade inflammatory state driven by visceral fat accumulation, sleep debt, dietary factors, and hormonal changes. Chronic inflammation impairs mitochondrial function and drives fibrotic changes in fascia.
  • The dehydration factor: Many midlife women are chronically underhydrated, which affects both systems. Fascial hydration depends directly on adequate fluid intake and lymphatic function. Mitochondrial function also depends on adequate cellular hydration. See our hydration mistakes article for the broader hydration picture.
  • The muscle loss compound: The sarcopenia that begins accelerating in midlife reduces the tissue population that carries most of the body’s mitochondria. Less muscle means fewer total mitochondria. The four muscle groups for aging well article covers the strength training foundation that addresses this piece.
  • The specific pattern this produces: The combination of these factors produces the specific midlife pattern of fatigue that does not resolve with sleep, stiffness that does not resolve with stretching, and reduced tolerance for physical demand. Both systems are declining together, each reinforcing the other, and the specific complaints reflect the combined dysfunction rather than either system alone.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Do Fibroblasts and Fasciacytes Depend on Mitochondrial Energy?

Zooming in to the cellular level makes the mitochondrial-fascial connection concrete. Two specific cell types matter most for understanding this connection.

  • Fibroblasts: Fibroblasts are the primary connective tissue cells throughout the body. They produce collagen, elastin, and other structural proteins that make up the extracellular matrix. Fibroblasts are metabolically active. Producing new collagen requires substantial ATP input. Maintaining the resident population of fibroblasts and their activity depends on adequate mitochondrial function.
  • When fibroblast mitochondria fail: When mitochondrial output in fibroblasts declines, several changes occur. Collagen production shifts toward less organized forms. The balance between collagen production and collagen breakdown tilts toward accumulation. The resulting tissue becomes more fibrotic, less pliable, and less functional. This is one of the specific cellular mechanisms behind the fibrotic fascia pattern that many midlife women develop.
  • Fasciacytes: Fasciacytes are a specialized cell type identified more recently in fascial research. They are located primarily at the interfaces between fascial layers and are the primary producers of hyaluronic acid in these interfaces. Hyaluronic acid is the specific molecule that allows fascial layers to glide against each other rather than sticking. Healthy fasciacyte function is essential for healthy fascial glide.
  • The fasciacyte-mitochondrial connection: Producing hyaluronic acid requires energy. Fasciacytes depend on adequate mitochondrial ATP to maintain hyaluronic acid production. When mitochondrial function declines in fasciacytes, hyaluronic acid production drops, fascial glide reduces, and adjacent tissues start sticking. Many of the felt-sense stiffness patterns that midlife women describe map directly onto this specific cellular change.
  • The oxidative stress problem: Fibroblasts and fasciacytes are particularly vulnerable to oxidative stress. Damaged mitochondria leak reactive oxygen species that damage these cells further. In midlife women whose antioxidant defenses have been challenged by hormonal changes and life-load stress, this vulnerability is amplified.
  • The exercise stimulus: Fibroblast and fasciacyte function respond positively to appropriate mechanical loading. Movement stimulates these cells to produce healthier tissue over time. This is one of the specific mechanisms behind why regular gentle movement supports fascial health, and why sedentary behavior compounds fascial restriction.
  • The nutritional support: These cells depend on adequate protein intake for the amino acids needed to synthesize new collagen. They also depend on adequate vitamin C for collagen synthesis, adequate zinc and copper for connective tissue enzyme function, and adequate polyphenols and antioxidants for protection from oxidative stress. The nutritional framework in the Macro Calculator and our Macro Friendly Recipe Book covers these foundations.

How Does the Fibrosis Loop Develop Between Mitochondrial Dysfunction and Fascial Restriction?

The specific pathological loop that develops when mitochondrial dysfunction meets fascial restriction is worth understanding in detail because it explains many of the specific patterns midlife women experience.
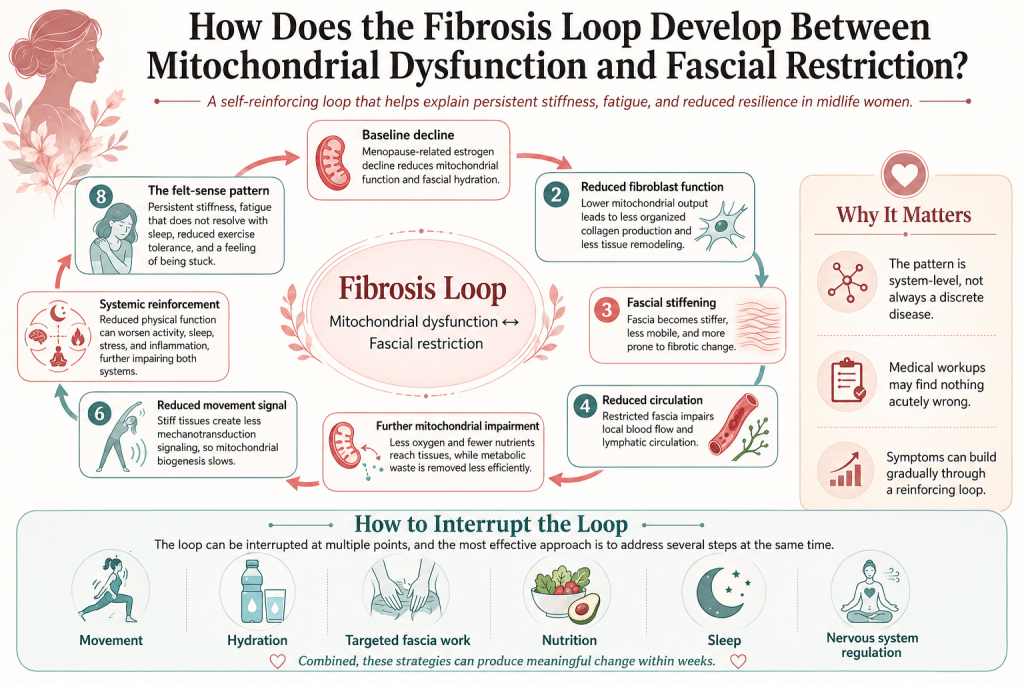
Fibrosis loop between mitochondria and fascia.
  • Step 1: Baseline decline. Menopause-related estrogen decline reduces mitochondrial function and fascial hydration simultaneously. This is the initial condition.
  • Step 2: Reduced fibroblast function. Reduced mitochondrial output in fibroblasts leads to less organized collagen production and reduced tissue remodeling.
  • Step 3: Fascial stiffening. The tissue becomes progressively stiffer, less mobile, and more prone to fibrotic changes.
  • Step 4: Reduced circulation. Restricted fascia impairs local blood flow and lymphatic circulation.
  • Step 5: Further mitochondrial impairment. Reduced circulation delivers less oxygen and fewer nutrients to the mitochondria in the affected tissues, and removes metabolic waste less efficiently. Local mitochondrial function declines further.
  • Step 6: Reduced movement signal. Restricted, stiff tissues produce less mechanotransduction signaling for mitochondrial biogenesis. New mitochondria are made more slowly.
  • Step 7: Systemic reinforcement. The reduced physical function often leads to reduced overall activity, reduced sleep quality, increased stress, and increased inflammation, all of which further impair both systems.
  • Step 8: The felt-sense pattern. By this point, the woman experiences persistent stiffness, chronic fatigue that does not resolve with sleep, reduced exercise tolerance, and a felt-sense of being stuck. Medical workup often finds nothing acutely wrong because the pattern is a combined system-level dysfunction rather than a discrete disease.

The loop can be interrupted at any of the eight steps. The interventions that work most reliably in practice are those that address multiple steps simultaneously, which is the specific value of the six-practice framework in Section 9. Movement, hydration, targeted fascia work, nutrition, sleep, and nervous system regulation each interrupt the loop at multiple points, and combined they produce meaningful change within weeks.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Do Mitochondria Support Hyaluronic Acid Production and Fascial Glide?

Hyaluronic acid deserves specific attention because it is one of the most direct points where the mitochondrial-fascial connection shows up in a form that midlife women can influence.

What Does Hyaluronic Acid Do?

Hyaluronic acid is a large sugar molecule that provides the ground substance for fascia, cartilage, skin, joint fluid, and other connective tissues. It has extraordinary water-holding capacity, which gives healthy fascia and skin their hydrated, gliding, and elastic quality.

Hyaluronic acid is produced in several areas throughout the body:

  • Fibroblasts and fasciacytes produce it throughout the fascial system.
  • Chondrocytes produce it in cartilage.
  • Synovial cells produce it in joint fluid.
  • Fasciacytes located at the interfaces between fascial layers are major producers within the fascial system.

Why Does Mitochondrial Function Matter?

Producing hyaluronic acid requires substantial ATP input from the cell’s mitochondria. This energy requirement is one reason mitochondrial dysfunction can directly impair fascial glide.

When fascial cells do not receive enough cellular energy, their ability to produce the hyaluronic acid needed to keep fascial layers hydrated and moving smoothly may decline.

How Does Estrogen Affect Hyaluronic Acid Production?

Estrogen supports hyaluronic acid production. As estrogen declines through menopause, hyaluronic acid production often declines as well.

This reduction may contribute to several changes commonly experienced by midlife women:

  • Skin dryness
  • Joint stiffness
  • Reduced tissue hydration
  • Fascial restriction

Can Oral Hyaluronic Acid Supplements Help?

Supplemental oral hyaluronic acid has become popular in recent years, but the evidence base remains mixed. Some studies support modest benefits for skin hydration and joint comfort.

The mechanism does not involve the swallowed molecule being directly incorporated into the tissues, as this is not how absorption works. Instead, oral hyaluronic acid may produce downstream signaling effects that support the body’s own hyaluronic acid production. If you are considering a supplement, discuss it with your healthcare provider.

What Is the Most Reliable Whole-Body Approach?

The more reliable way to support hyaluronic acid production is to support the cellular systems that make it. This means supporting fibroblast and fasciacyte mitochondrial function through the same six practices that support fascia and mitochondria generally. There is no shortcut around the underlying cell biology.

How Does the Nervous System Affect Fascia and Mitochondrial Signaling?

The nervous system deserves specific attention because it modulates both mitochondrial function and fascial health in ways that are directly addressable through daily practice.

  • The autonomic nervous system: The autonomic nervous system has two branches. The sympathetic branch drives activation, alertness, and stress response. The parasympathetic branch drives rest, recovery, and repair. In perimenopause and menopause, many women experience chronic sympathetic dominance, which impairs both mitochondrial recovery and fascial repair.
  • Cortisol and both systems: Chronic cortisol elevation impairs mitochondrial function and drives fibrotic changes in connective tissue. Both systems suffer from the same cortisol dysregulation that midlife hormonal shifts often produce.
  • Vagal tone and both systems: Higher vagal tone supports parasympathetic recovery, which supports both mitochondrial repair and fascial remodeling. Practices that raise vagal tone (extended exhalation breathing, humming, gargling, cold face immersion, and the other practices in our vagus nerve reset exercises article) support both systems.
  • Mechanotransduction: Every time the body moves, mechanical signals travel through fascial tissues to fibroblasts, fasciacytes, and their mitochondria. These signals trigger biogenesis, remodeling, and repair. Sedentary behavior removes these signals. Regular movement provides them. This is one of the reasons daily movement matters so much for both systems.
  • The pain-restriction feedback loop: Restricted fascia often becomes painful, which drives further reduction in movement, which further impairs mitochondrial signaling. Breaking this loop with gentle appropriate movement is one of the earliest and most powerful interventions.
  • Sleep as neural repair time: Sleep is when the nervous system consolidates learning, when the brain clears metabolic waste, when the parasympathetic branch has its extended dominance window, and when both mitochondrial repair and fascial remodeling can happen at their peak. Sleep is not optional for either system.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Which Six Practices Support Both Mitochondria and Fascia?

The specific value of understanding the mitochondrial-fascial connection is that a small number of practices address both systems simultaneously. Six practices consistently support both, and installing them in daily rhythm produces meaningful change within weeks rather than months.
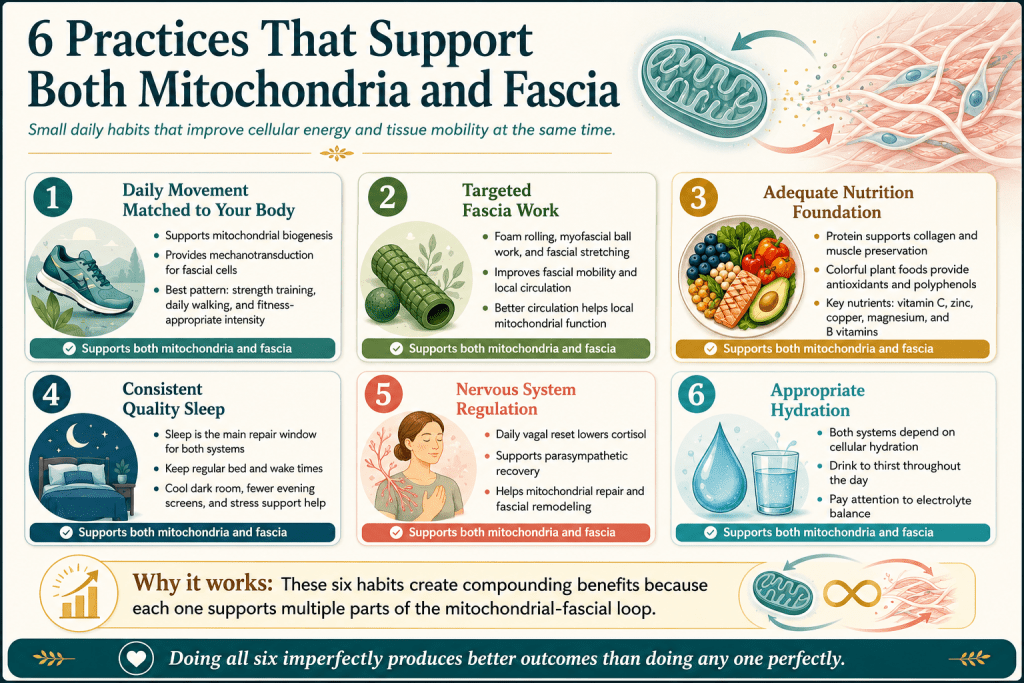
Six practices that support mitochondria and fascia.

Practice 1: Daily Movement Matched to Your Body

Regular movement supports mitochondrial biogenesis and provides the mechanotransduction signaling that fascial cells depend on. The most impactful pattern combines resistance training (two to three sessions per week covering the four major muscle groups), daily walking or gentle activity, and periodic higher-intensity efforts appropriate to your fitness. See our articles on micro walks and tai chi walking for seniors.

Practice 2: Targeted Fascia Work

Direct fascia interventions including foam rolling, myofascial ball work, and specific fascial stretches produce local improvements in fascial mobility that then support local mitochondrial function through improved circulation. The fascia release exercises for weight loss article, the tight psoas article, and the five yin yoga poses article cover specific home practices.

Practice 3: Adequate Nutrition Foundation

Both systems require adequate protein for collagen synthesis and muscle preservation, adequate colorful plant foods for antioxidants and polyphenols, appropriate calorie balance, and specific micronutrients including vitamin C, zinc, copper, magnesium, and B vitamins.

Practice 4: Consistent Quality Sleep

Sleep is where both systems do most of their repair. Consistent bed and wake times, cool dark bedroom, screen limits in the evening, and appropriate stress management all support the sleep quality that both systems depend on. See our menopause sleep remedies article and midlife sleep stack article.

Practice 5: Nervous System Regulation

Daily vagal reset practice reduces cortisol, activates parasympathetic recovery, and supports the internal environment that both mitochondrial repair and fascial remodeling require.

Practice 6: Appropriate Hydration

Both fascia and mitochondrial function depend on adequate cellular hydration. Drinking to thirst throughout the day with attention to appropriate electrolyte balance supports both systems.

These six practices produce individually meaningful benefits, but combined they produce compounding effects because each one addresses multiple aspects of the mitochondrial-fascial loop. The specific value of the framework is that no single practice needs to be perfect for the combination to move the needle. Doing all six imperfectly produces better outcomes than doing any one perfectly.

“The women who see the biggest change from this framework are the ones who stop trying to isolate a single intervention and instead install the whole six-practice pattern. Every single one of those practices supports both systems. Doing three of them well and skipping the other three produces meaningful results. Doing all six imperfectly for a year produces substantial results across every dimension of energy and mobility. The compounding is not linear. When mitochondrial function improves, movement feels better, which improves fascial mobility, which improves circulation, which further improves mitochondrial function, and the whole loop starts running in the healthy direction rather than the depleting direction. That reversal of the loop is what the practical framework is for.”

Terry Tateossian, Founder of The House of Rose

What Does This Connection Mean for Common Midlife Complaints?

The mitochondrial-fascial framework provides a specific way of understanding several of the most common midlife women’s complaints that often confuse both patients and providers.

How Does the Connection Affect Energy and Exercise?

  • Fatigue that does not resolve with sleep: Reduced mitochondrial output produces fatigue that sleeping more does not fully address because the underlying constraint is cellular energy production. Combined with reduced circulation from fascial restriction, the fatigue pattern becomes entrenched. Addressing both systems together often resolves fatigue patterns that sleep interventions alone do not.
  • Sluggish recovery from exercise: Recovery depends on mitochondrial repair of exercise-induced damage and fascial remodeling of the loaded tissues. When both systems are impaired, recovery slows dramatically. Older women often blame this on age, but it is more accurately attributed to the combined mitochondrial-fascial dysfunction that age has amplified.
  • Reduced exercise tolerance: Reduced mitochondrial output limits how much work the tissues can do before fatigue sets in. Combined with fascial restriction that makes movement itself harder, the felt sense is of being unable to do what you used to do at the same effort level. Both systems must recover to restore tolerance.

How Does the Connection Contribute to Stiffness, Pain, and Limited Movement?

  • Stiffness that does not resolve with stretching: Fibrotic fascial changes do not respond well to conventional stretching because the underlying tissue quality is the constraint. Combined with reduced mitochondrial function in fascial cells, which slows the tissue remodeling that stretching would normally stimulate, the stiffness becomes chronic. Addressing both systems together often produces improvements that stretching alone did not.
  • Unexplained aches and pains: Fascial restriction can refer pain to distant sites through the interconnected network. Combined with the reduced cellular resilience associated with impaired mitochondrial function, ordinary loads produce more pain than they should. The workup often finds nothing structural because the problem is a system-level dysfunction rather than a discrete injury.
  • Reduced range of motion: Chronic fascial restriction reduces the range of motion available in every joint. Combined with sarcopenia-related loss of strength, functional range gradually shrinks over the years. Both systems must be addressed to reverse the pattern.

How Does the Connection Affect Healing and Skin Health?

  • Slower wound and injury healing: Fibroblast and fasciacyte function are directly involved in healing. Reduced mitochondrial output in these cells slows healing at the cellular level. Combined with the general age-related decline in healing capacity, the effect can be substantial.
  • Skin changes: The skin is a fascial tissue. Reduced hyaluronic acid production and collagen turnover contribute to the dryness, thinning, and reduced elasticity associated with midlife skin. Supporting both mitochondrial and fascial health addresses the underlying cell biology.

What Is the Broader Reframe?

When a midlife woman recognizes several of these patterns in herself, the mitochondrial-fascial framework often provides the specific explanation that has been missing.

Individual workups may have found nothing wrong. General wellness advice may have produced only modest results. The specific combined framework is often the missing piece.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Where Is the Research Still Developing?

Being honest about where the research is still developing matters for maintaining appropriate calibration on this framework.

Which Parts of the Mitochondrial-Fascial Connection Are Still Being Mapped?

The specific bidirectional connection is real but still being mapped.

  • Mitochondria to fascia: The direction that mitochondrial function supports fascial cell function is well-established.
  • Fascia to mitochondria: The direction that fascial mobility supports mitochondrial function through mechanotransduction and circulation is supported but less definitively established at the quantitative level.

Both directions have research support, and the overall framework is defensible, but specific numerical predictions are not yet available.

The estrogen-mitochondria-fascia axis is also under active investigation. How exactly menopausal estrogen decline drives combined dysfunction in these two systems remains a topic of ongoing research. The general pattern is well-supported, but the specific mechanisms and quantitative contributions of each pathway are still being worked out.

What Do We Still Need to Learn About Exercise and Nutrition?

The exercise dose-response is not fully mapped. The general observation that movement supports both systems is strong, but controlled research has not yet identified the optimal:

  • Amount of movement
  • Type of exercise
  • Intensity level
  • Frequency for midlife women

The recommendations in this article are based on general principles combined with clinical experience, not on specific dose-response trials focused on both mitochondrial and fascial health.

The nutritional support pattern is generally established, but specific interventions are less clearly mapped. A Mediterranean-style diet with adequate protein and colorful plant foods supports both systems. However, individual nutrients and their optimal doses within this combined framework are less well-established.

Following the general nutrition foundation is currently more supported than relying on any single-nutrient intervention.

What Does the Research Say About Supplements?

The supplement question remains open. Various supplements are marketed for mitochondrial support, fascial support, or both, including:

  • CoQ10
  • NAD precursors
  • Hyaluronic acid
  • Collagen
  • Other targeted formulas

The evidence base for any specific supplement within the combined midlife women’s framework is limited. Some products may be helpful, while others are supported largely by marketing rather than strong evidence.

Any supplement decision should be made in consultation with a healthcare provider.

Is the Framework Still Worth Acting On?

The overall framework is worth acting on despite the remaining research gaps. The general principles are supported, the specific practices are safe, and the potential benefits are meaningful.

Waiting for perfect research before acting is not the right response to the current state of evidence. Acting on the general framework while remaining open to refinement as the research develops is the more appropriate approach.

Which Common Mistakes Undermine the Mitochondria-Fascia Framework?

Six common mistakes reduce the effectiveness of the mitochondrial-fascial framework for midlife women.

  • Treating the two systems separately: Working on mitochondrial support alone (through supplements or exercise) while ignoring fascia often produces limited results. Working on fascia alone (through massage or stretching) while ignoring mitochondrial support often produces limited results. The specific value of the framework is treating them together.
  • Expecting rapid results: Meaningful changes in both systems require weeks to months of consistent daily practice. Judging the framework on the basis of two weeks of practice produces false negatives.
  • Skipping the boring practices: Sleep and hydration look unimpressive on paper compared to trendy supplements or fancy movement modalities. They are the foundational practices with the largest cumulative effects. Do not skip them.
  • Focusing only on the practices that feel good: The full six-practice framework addresses different aspects of the loop. Skipping practices that feel less enjoyable (often the resistance training or the nutritional discipline) reduces the overall effect.
  • Overcomplicating the movement piece: Complex specialized movement programs are not necessary. Regular resistance training, daily walking, and periodic fascia work covers the essentials. Consistency matters more than complexity.
  • Not tracking anything: Subjective improvements in energy and mobility can be difficult to notice week-to-week. Tracking a simple metric or two (sleep quality, energy on a 1-10 scale, resting heart rate on a wearable) over months makes the progress visible when the daily changes feel invisible.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
When Should You See a Healthcare Professional?

Most midlife women can safely apply the framework in this article on their own. Some situations require professional evaluation first or alongside.

  • Persistent unexplained fatigue: Fatigue that does not respond to any intervention over a period of months warrants medical workup for thyroid dysfunction, anemia, sleep disorders, chronic infections, autoimmune conditions, or other underlying causes.
  • Progressive muscle weakness: Weakness that is progressing or interfering with daily function warrants evaluation for neurological or muscular conditions.
  • Unexplained joint or muscle pain: New severe or progressing pain warrants evaluation before assuming it is fascial or mitochondrial.
  • Cardiovascular symptoms: Chest pain, shortness of breath, palpitations, or reduced exercise tolerance that appears suddenly warrants medical evaluation.
  • Post-viral or post-infectious fatigue: Long-COVID and other post-viral syndromes have specific evaluation and management considerations that require medical care.
  • Chronic autoimmune or inflammatory conditions: These often affect both mitochondrial function and connective tissue and warrant specialist care alongside any lifestyle framework.
  • Any decision about supplements: Discuss any supplement decision with your healthcare provider, particularly if you are on multiple medications or have complex medical conditions.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Frequently Asked Questions

What is the connection between mitochondria and fascia?

The connection is bidirectional. Fascial cells (fibroblasts and fasciacytes) depend on mitochondrial ATP to produce collagen, hyaluronic acid, and other components that keep fascia healthy. Fascial mobility supports mitochondrial function through improved circulation and mechanotransduction signaling. When one system declines, the other tends to decline as well, producing a self-reinforcing loop that many midlife women recognize as combined stiffness and fatigue.

Why do both mitochondria and fascia decline in menopause?

Estrogen supports both mitochondrial biogenesis and fascial hydration. As estrogen falls through perimenopause and menopause, both systems lose one of their major supportive signals. The decline is compounded by sleep disruption, cortisol dysregulation, reduced movement, and increased inflammation that also often accompany the menopause transition.

Can I improve mitochondrial function through exercise?

Yes, and exercise is one of the strongest known triggers for mitochondrial biogenesis (the production of new mitochondria). Both resistance training and endurance training produce this effect. For midlife women, a combination of two to three resistance training sessions per week plus daily walking and periodic higher-intensity efforts is a strong general framework.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
What is a fasciacyte?

A fasciacyte is a specialized cell type located primarily at the interfaces between fascial layers. Fasciacytes produce hyaluronic acid, the specific molecule that allows fascial layers to glide against each other rather than sticking. Healthy fasciacyte function is essential for healthy fascial glide, and it depends on adequate mitochondrial ATP.

Do I need supplements for mitochondrial and fascial health?

Supplements can play a supporting role but are not necessary for most midlife women who install the six-practice framework consistently. The foundational supplement stack for midlife women (vitamin D, magnesium, omega-3s, adequate protein) covers most of what both systems need. Specific mitochondrial supplements and specific fascial supplements have variable evidence bases. Discuss any supplement decision with your healthcare provider.

How long before I feel results from the framework?

Subjective improvements in energy and mobility often appear within two to three weeks of consistent daily practice. Deeper changes in mitochondrial function and fascial mobility develop over three to six months. Full effects compound over one to two years of consistent practice.

Can hyaluronic acid supplements improve fascia?

The evidence base is mixed. Some studies support modest benefits of oral hyaluronic acid for skin hydration and joint comfort. The mechanism is not direct incorporation of the swallowed molecule but downstream signaling effects. The more reliable approach is to support the cellular systems that produce hyaluronic acid endogenously through the six-practice framework.

Does yoga help both mitochondria and fascia?

Yes, yoga combines movement, breath, mindfulness, and fascial stretching in ways that support both systems. Gentle to moderate yoga practice is well-tolerated by most midlife women. See our five yin yoga poses article for a specific home practice.

Is mitochondrial dysfunction the same as chronic fatigue?

They overlap but are not identical. Mitochondrial dysfunction can contribute to chronic fatigue but is not the only cause. Chronic fatigue syndrome is a specific clinical diagnosis with defined criteria. If you have persistent unexplained severe fatigue, work with a healthcare provider for evaluation.

Can this framework help with menopause weight gain?

Improved mitochondrial function supports better metabolism, and improved fascial mobility supports easier movement, both of which support the broader midlife body composition framework. Weight management is more directly driven by nutrition, protein intake, strength training, and sleep. The mitochondrial-fascial framework supports these interventions but does not replace them.

Does cold exposure help mitochondria?

Cold exposure is one of the documented triggers for mitochondrial biogenesis. Cold water face immersion, cold showers, and cold water immersion are all forms. Discuss with your healthcare provider before starting cold exposure practice if you have cardiovascular concerns.

Is fibrosis the same as fascial restriction?

Fibrosis and fascial restriction are related but not identical. Fibrosis refers to excessive accumulation of collagen and connective tissue in an organized but pathological pattern. Fascial restriction is a broader term that includes fibrosis but also includes reduced hydration, reduced glide, and other functional limitations that are not always driven by frank fibrotic changes.

Can massage help both systems?

Yes, and regular massage supports fascial mobility directly while also supporting the parasympathetic recovery that benefits mitochondrial function. Self-massage with a foam roller or therapy ball provides much of the benefit at lower cost than professional massage.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Does sleep really matter that much for both systems?

Yes, and sleep is when both systems do most of their repair. Mitochondrial repair, connective tissue remodeling, hormonal regulation, and nervous system recovery all happen preferentially during sleep. Skimping on sleep undermines every other intervention in the framework. Consistent quality sleep is not optional for either system.

How does this framework fit with hormone therapy?

Hormone therapy for menopause is a separate decision made with a menopause specialist. Some women benefit from hormone therapy for the specific menopause symptoms it addresses. The mitochondrial-fascial framework in this article is compatible with hormone therapy and does not replace it. Both approaches address the same general life-stage challenges through different mechanisms and are complementary rather than competing.

References

  • Schleip, R., & Müller, D. G. (2013). Training principles for fascial connective tissues: scientific foundation and suggested practical applications. Journal of Bodywork and Movement Therapies, 17(1), 103–115.
  • Stecco, C., Fede, C., Macchi, V., et al. (2018). The fasciacytes: a new cell devoted to fascial gliding regulation. Clinical Anatomy, 31(5), 667–676.
  • Stecco, C., Stern, R., Porzionato, A., et al. (2011). Hyaluronan within fascia in the etiology of myofascial pain. Surgical and Radiologic Anatomy, 33(10), 891–896.
  • Bordoni, B., & Zanier, E. (2013). Anatomic connections of the diaphragm: influence of respiration on the body system. Journal of Multidisciplinary Healthcare, 6, 281–291.
  • Zorov, D. B., Juhaszova, M., & Sollott, S. J. (2014). Mitochondrial reactive oxygen species (ROS) and ROS-induced ROS release. Physiological Reviews, 94(3), 909–950.
  • López-Otín, C., Blasco, M. A., Partridge, L., et al. (2013). The hallmarks of aging. Cell, 153(6), 1194–1217.
  • López-Otín, C., Blasco, M. A., Partridge, L., et al. (2023). Hallmarks of aging: an expanding universe. Cell, 186(2), 243–278.
  • Klinge, C. M. (2020). Estrogenic control of mitochondrial function. Redox Biology, 31, 101435.
  • Mattingly, K. A., Ivanova, M. M., Riggs, K. A., et al. (2008). Estradiol stimulates transcription of nuclear respiratory factor-1 and increases mitochondrial biogenesis. Molecular Endocrinology, 22(3), 609–622.
  • Torres, M. J., Kew, K. A., Ryan, T. E., et al. (2018). 17β-estradiol directly lowers mitochondrial membrane microviscosity and improves bioenergetic function in skeletal muscle. Cell Metabolism, 27(1), 167–179.
  • Zimmerman, B., Kundu, P., Rooney, W. D., & Raber, J. (2019). The effect of ovariectomy and estradiol replacement on mitochondrial function in the aging rat brain. Neuroscience, 421, 100–113.
  • Wallace, D. C. (2005). A mitochondrial paradigm of metabolic and degenerative diseases, aging, and cancer: a dawn for evolutionary medicine. Annual Review of Genetics, 39, 359–407.
  • Kelley, D. E., He, J., Menshikova, E. V., & Ritov, V. B. (2002). Dysfunction of mitochondria in human skeletal muscle in type 2 diabetes. Diabetes, 51(10), 2944–2950.
  • Sun, N., Youle, R. J., & Finkel, T. (2016). The mitochondrial basis of aging. Molecular Cell, 61(5), 654–666.
  • Findley, T. W., Chaudhry, H., & Dhar, S. (2015). Transmission of muscle force to fascia during exercise. Journal of Bodywork and Movement Therapies, 19(1), 119–123.
  • Ajimsha, M. S., Al-Mudahka, N. R., & Al-Madzhar, J. A. (2015). Effectiveness of myofascial release: systematic review of randomized controlled trials. Journal of Bodywork and Movement Therapies, 19(1), 102–112.
  • Beardsley, C., & Škarabot, J. (2015). Effects of self-myofascial release: a systematic review. Journal of Bodywork and Movement Therapies, 19(4), 747–758.
  • Klingler, W., Velders, M., Hoppe, K., et al. (2014). Clinical relevance of fascial tissue and dysfunctions. Current Pain and Headache Reports, 18(8), 439.
  • Chaitow, L. (2020). Fascia as a sensory organ: implications for practice. Journal of Bodywork and Movement Therapies, 24(4), 3–4.
  • Chaudhry, H., Schleip, R., Ji, Z., et al. (2008). Three-dimensional mathematical model for deformation of human fasciae in manual therapy. Journal of the American Osteopathic Association, 108(8), 379–390.
  • Bordoni, B., Marelli, F., Morabito, B., & Sacconi, B. (2019). The connective tissue and its properties as a peripheral communication system. Cureus, 11(3), e4187.
  • Bishop, D. J., Botella, J., Genders, A. J., et al. (2019). High-intensity exercise and mitochondrial biogenesis: current controversies and future research directions. Physiology, 34(1), 56–70.
  • Menshikova, E. V., Ritov, V. B., Fairfull, L., et al. (2006). Effects of exercise on mitochondrial content and function in aging human skeletal muscle. Journals of Gerontology Series A, 61(6), 534–540.
  • Distefano, G., Standley, R. A., Zhang, X., et al. (2018). Physical activity unveils the relationship between mitochondrial energetics, muscle quality, and physical function in older adults. Journal of Cachexia, Sarcopenia and Muscle, 9(2), 279–294.
  • Meex, R. C., Hoy, A. J., Morris, A., et al. (2015). Fetuin B is a secreted hepatocyte factor linking steatosis to impaired glucose metabolism. Cell Metabolism, 22(6), 1078–1089.

Disclaimer: Always consult with a qualified healthcare professional before starting any new movement, nutrition, or supplement program, particularly if you have chronic medical conditions, take multiple medications, or have unexplained persistent symptoms that have not been evaluated. This article is educational and does not constitute medical advice.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

Flavanols: The Compound Most Midlife Women Are Not Getting Enough Of (And Why It Matters for Heart, Brain, and Skin)

Flavanols for women over 40 have become an important topic in midlife nutrition, yet most women I coach have never heard of them. A 2026 biomarker study involving more than 30,000 adults found that roughly four out of five people were not getting enough of these plant compounds, even when they followed standard dietary recommendations.

Flavanols are a subgroup of polyphenols that includes epicatechin, catechin, and related compounds. Research has linked higher intake with cardiovascular health, cognitive function, blood sugar regulation, exercise capacity, and healthier skin aging. The problem is that many foods commonly considered healthy do not provide enough flavanols to close the gap.

I am Terry Tateossian, founder of The House of Rose and a certified lifestyle medicine coach who leads nutrition-focused wellness retreats for women in perimenopause, menopause, and post-menopause at our Smoky Mountains property in East Tennessee. I built THOR after experiencing early-onset menopause at 41, an 80-pound midlife body composition shift, and 25 years of running businesses while raising two children.

This guide explains what flavanols are, why they matter for women over 40, what studies such as the COSMOS trial found, and why standard dietary advice may not provide enough.

Important: Always consult your healthcare provider before making significant dietary changes or starting a supplement, especially if you have cardiovascular disease, take blood-thinning medication, or manage a health condition that requires dietary supervision.

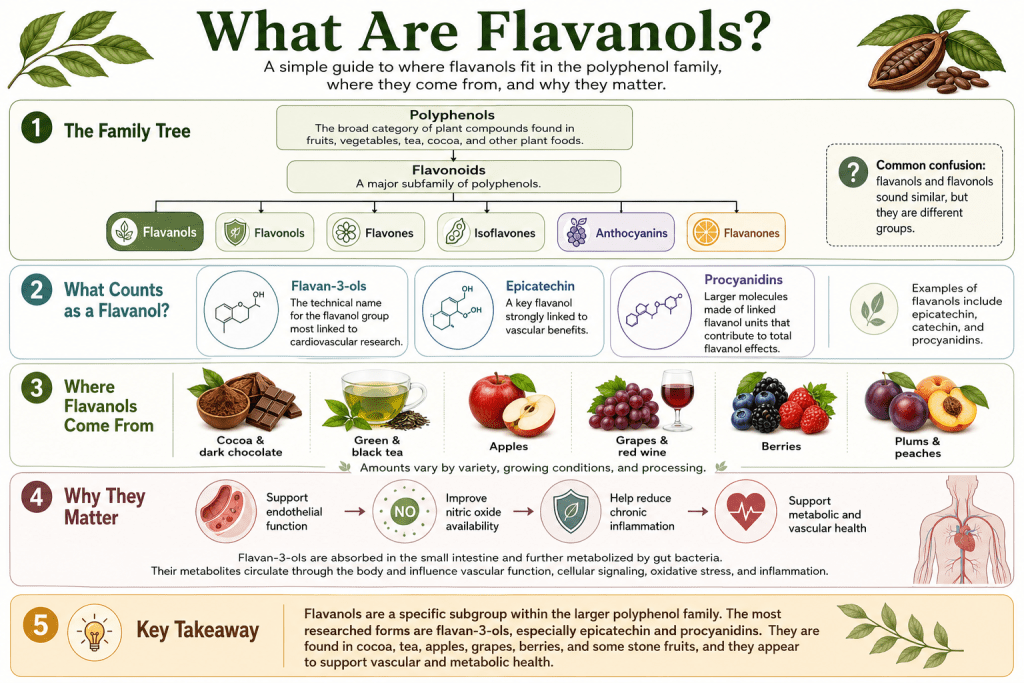
What Are Flavanols?

Flavanols are a subfamily of plant compounds within the broader category of polyphenols. Understanding this structure matters because the specific molecules that produce the health effects sit within a larger and often confusing family tree.

Flavanol types, food sources, and health benefits.

How Do Flavanols Fit Within the Polyphenol Family?

  • Polyphenols: The overarching category. Polyphenols are plant compounds produced by fruits, vegetables, and other plant foods largely as protective molecules against sun, insects, and stress. Thousands of individual polyphenols exist across the plant kingdom.
  • Flavonoids: A major subfamily of polyphenols. Flavonoids include several groups: flavanols, flavonols, flavones, isoflavones, anthocyanins, and flavanones. The naming similarity between flavanols and flavonols is a common source of confusion. Flavanols, the group covered in this article, include epicatechin, catechin, and their oligomers called procyanidins. Flavonols include quercetin and kaempferol. Both are important, but they are different molecules with different effects.
  • Flavan-3-ols: The technical name for the specific flavanol group most relevant to recent cardiovascular research. When the Academy of Nutrition and Dietetics issued its 2022 dietary bioactive guideline for cardiometabolic health, the specific recommendation was for flavan-3-ols. This is broadly the same group of compounds this article addresses.
  • Epicatechin: The specific flavanol molecule most strongly linked to vascular benefits in the research literature. It is one of the primary flavanols found in cocoa, tea, apples, and grapes.
  • Procyanidins: Larger molecules made of linked flavanol units. Procyanidins are abundant in cocoa, apples, and certain berries, and they contribute to the total flavanol effect.

Where Do Flavanols Come From?

The primary dietary sources of flavan-3-ols include:

  • Cocoa and dark chocolate, specifically non-alkalized products
  • Green and black tea
  • Apples
  • Grapes and red wine
  • Certain berries, particularly strawberries and blackberries
  • Stone fruits such as plums and peaches

The specific amount of flavanols in these foods can vary substantially depending on the variety, growing conditions, and processing methods.

Why Do Flavanols Matter Physiologically?

Flavan-3-ols are absorbed in the small intestine and further metabolized by gut bacteria. The resulting metabolites circulate through the body and appear to affect several biological processes, including:

  • Vascular function
  • Cellular signaling
  • Oxidative stress
  • Inflammation

The specific mechanisms are still being mapped, but the overall pattern suggests that flavan-3-ols support vascular endothelial function, improve nitric oxide availability, reduce chronic inflammation, and contribute to several downstream metabolic outcomes.

Why Do Flavanols Matter for Women Over 40?

The general population case for adequate flavanol intake is strong. The case for women over 40 is stronger, and it is worth understanding why the intersection matters.

  • Cardiovascular disease is the leading cause of death in women over 50: More than one in three women in the United States dies of cardiovascular disease. The risk rises meaningfully after menopause because the cardiovascular protection that estrogen provided declines. Any intervention with meaningful cardiovascular benefit is worth serious attention in this population.
  • The menopause vascular transition: The specific vascular changes of perimenopause and menopause include reduced endothelial function, increased arterial stiffness, altered lipid profiles, and changes in blood pressure regulation. Flavan-3-ols support endothelial function and nitric oxide availability, which addresses one of the primary vascular changes in this window.
  • Cognitive changes in midlife: Many women in perimenopause and menopause experience measurable changes in memory, processing speed, and mental stamina. The flavanol research on cognitive function (particularly hippocampal memory) is directly relevant to this concern.
  • Metabolic changes: Perimenopause and menopause produce measurable declines in insulin sensitivity and changes in body composition that increase cardiometabolic risk. The flavanol research on insulin function and glucose regulation is directly relevant.
  • Skin aging: The skin aging that accelerates in midlife women is driven partly by the same oxidative and inflammatory processes that flavanols address. The specific research on flavanols and skin aging in women is one of the few studies conducted in a female-specific population.
  • Longevity signal: The Danish cohort research linking total flavonoid intake to reduced all-cause, cardiovascular, and cancer mortality is not specific to midlife women, but the mortality signal is directly relevant to a population thinking about the next thirty or forty years of life.
  • Exercise capacity for aging well: The flavanol research on cardiorespiratory fitness and exercise capacity is directly relevant to the muscle preservation and functional aging framework that midlife women need. See our four muscle groups for aging well article for the strength side of this picture.
  • The gap in most midlife diets: Even women who eat what most people would consider a healthy diet often fall short of the flavanol threshold associated with the strongest research findings. This means the gap is closable through specific dietary choices rather than through massive dietary overhaul.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

“One of the most under-addressed pieces of the menopause transition is the specific cardiovascular risk shift. Most women I coach have been so focused on weight, sleep, and mood that the fact that their cardiovascular disease risk climbs dramatically after menopause has not really registered. The flavanol conversation is important precisely because it gives midlife women a specific, evidence-informed, food-based, low-cost intervention that addresses one of the actual biggest health risks they face over the next three decades. It is not a supplement pitch. It is a specific reframe of what to prioritize in the produce section, in the tea aisle, and in the chocolate purchase, that changes the flavanol load enough to matter over years. Small daily choices, compounded over decades, in one of the specific categories where the compounding has been documented.”

Terry Tateossian, Founder of The House of Rose

What Did the COSMOS Trial Show?

The COSMOS trial, or Cocoa Supplement and Multivitamin Outcomes Study, is the largest randomized controlled trial conducted on cocoa flavanols and cardiovascular outcomes.

Understanding both what the trial found and what it did not find is essential for interpreting the evidence accurately.

How Was the COSMOS Trial Designed?

COSMOS enrolled more than 21,000 older adults, primarily women over 65 and men over 60. Participants were randomly assigned to receive either a cocoa flavanol supplement or a placebo for a median follow-up period of approximately 3.6 years.

The main features of the trial included:

  • Daily Dose: The supplement provided 500 mg of total cocoa flavanols and 80 mg of epicatechin.
  • Participant Group: The study primarily included older adults, with women representing a large portion of the sample.
  • Comparison Group: Participants received either the cocoa flavanol supplement or an inactive placebo.
  • Follow-Up Period: Researchers tracked cardiovascular outcomes for approximately 3.6 years.

The dose used in COSMOS later became an important reference point for flavanol recommendations. The Academy of Nutrition and Dietetics’ 2022 guideline recommends 400 to 600 mg of flavan-3-ols per day for cardiometabolic health, a range centered closely on the COSMOS dose.

What Did the Primary and Secondary Outcomes Show?

The primary outcome was a combination of major cardiovascular events, including heart attack, stroke, cardiovascular death, coronary revascularization, and other cardiovascular endpoints.

The main findings were:

  • Primary Endpoint: The cocoa flavanol group experienced a 10% reduction in the combined cardiovascular endpoint. However, this result did not reach conventional statistical significance.
  • Cardiovascular Death: Cardiovascular deaths were reduced by 27% in a pre-specified secondary analysis.
  • Total Cardiovascular Events: A separate pre-specified cardiovascular composite also showed a meaningful reduction.
  • Consistent Supplement Use: Participants who took their supplements consistently showed larger benefits across several outcomes.

The distinction between primary and secondary findings matters. The 27% reduction in cardiovascular death was not discovered through an unplanned analysis after the trial ended. It was a pre-specified secondary outcome that researchers had decided to examine before the trial began.

However, because it was a secondary endpoint, it carries somewhat less evidentiary weight than it would have if the primary endpoint had reached statistical significance.

How Should the Results Be Interpreted?

The most accurate interpretation is that COSMOS found a promising cardiovascular signal for cocoa flavanols at a daily dose of 500 mg. The strongest individual finding was the reduction in cardiovascular death.

The evidence is meaningful, but it is not definitive. The primary cardiovascular endpoint did not reach statistical significance, so the trial does not prove that cocoa flavanols prevent cardiovascular disease. However, its findings align with broader observational research connecting higher flavonoid intake with lower cardiovascular and mortality risk.

The results should also be understood within the population studied:

  • Most Directly Applicable Group: Older adults similar to the COSMOS participants.
  • Midlife Women: The same benefits in younger women were not directly tested, although the biological mechanisms and observational research suggest the findings may still be relevant.
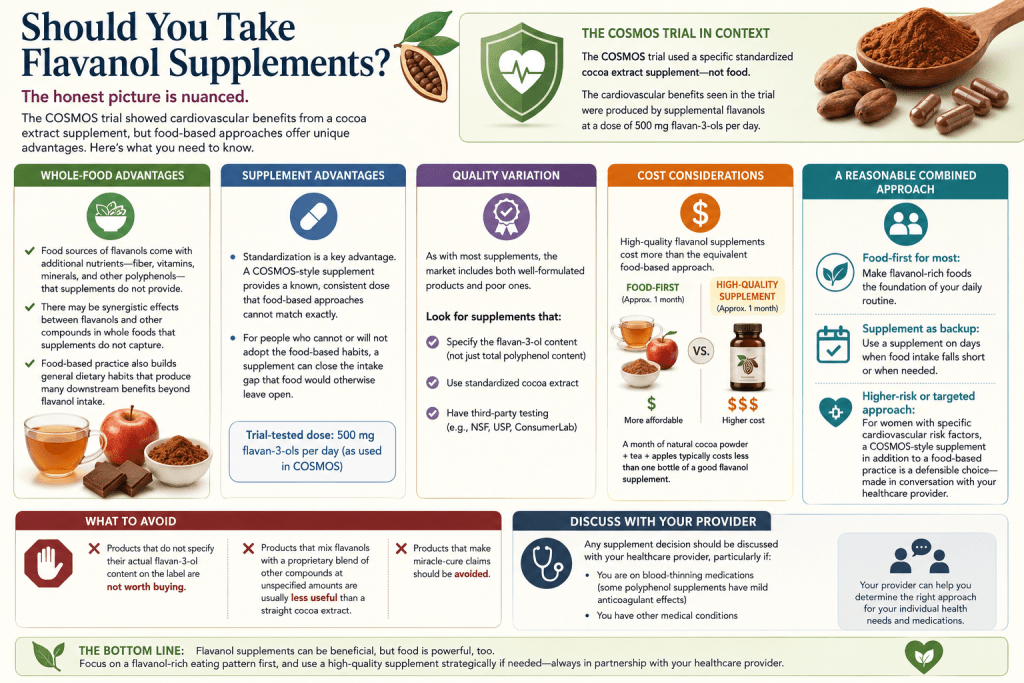
  • Specific Product Tested: The trial used a standardized cocoa flavanol supplement, not ordinary dark chocolate or general cocoa products.

In 2023, the FDA authorized a qualified health claim stating that high-flavanol cocoa powder may reduce the risk of cardiovascular disease. The word qualified reflects that the evidence is promising but not yet conclusive.

The claim applies specifically to high-flavanol cocoa powder. It does not apply broadly to dark chocolate or every product containing cocoa.

Why Do Most Midlife Women Fall Short on Flavanols?

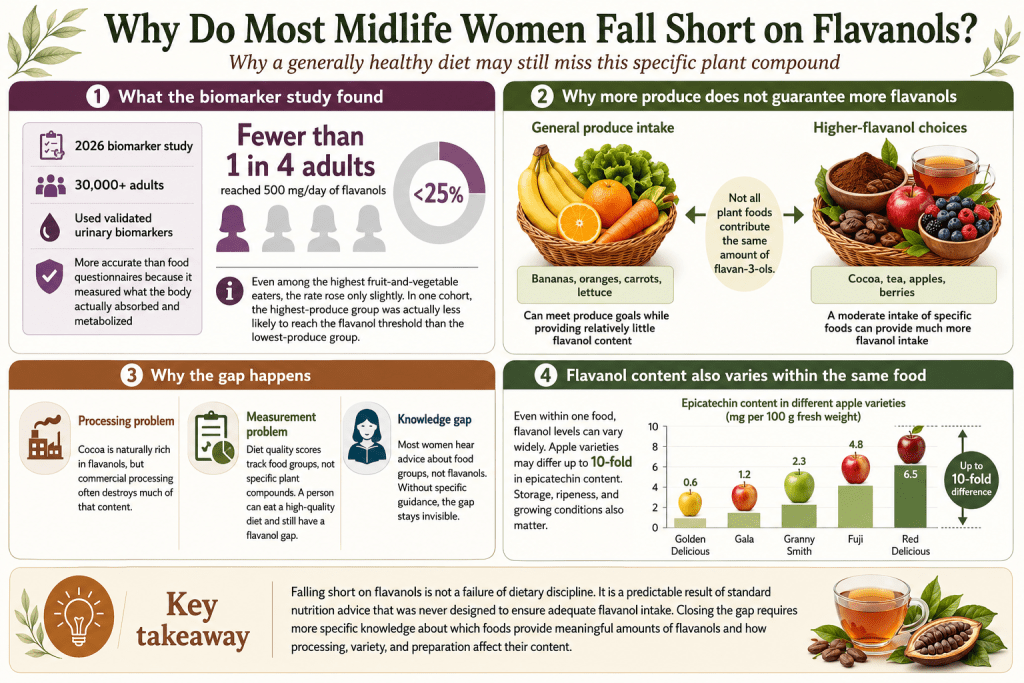
The 2026 biomarker study cited at the top of this article measured actual flavanol intake in more than 30,000 adults through validated urinary biomarkers. This method is significantly more accurate than food frequency questionnaires because it measures what the body absorbed and metabolized rather than what people reported eating.

Why midlife women fall short on flavanols.

What Did the Biomarker Study Find?

Fewer than one in four adults reached the 500 mg per day flavanol intake associated with the strongest research findings.

Among people in the top quartile of fruit and vegetable consumption—the ones eating the most produce—the rate only rose slightly. In one cohort, the highest-produce quartile was less likely to reach the flavanol threshold than the lowest-produce quartile.

Why Does Eating More Produce Not Guarantee More Flavanols?

The fruits and vegetables that deliver meaningful amounts of flavanols are only a subset of the broader produce category. A banana and a piece of dark chocolate both count as plant foods in a general sense, but they contribute very different amounts of flavan-3-ols.

Someone who eats large amounts of bananas, oranges, carrots, and lettuce may be meeting general produce recommendations while receiving relatively little flavanol content. Someone who eats moderate amounts of specific high-flavanol foods may receive a much higher intake in less overall food volume.

Some of the most significant sources include:

  • Cocoa
  • Tea
  • Apples
  • Berries

Even within the same food, flavanol content can vary substantially. Different apple varieties can differ tenfold in epicatechin content, while storage conditions, ripeness, and growing conditions can all change the specific flavanol load. The upper and lower ends of the same food category may therefore provide very different amounts.

What Other Factors Contribute to the Flavanol Gap?

Several additional issues make it difficult for midlife women to consistently reach the recommended flavanol intake:

  • The processing problem: Cocoa is one of the richest natural sources of flavanols, but most commercial cocoa is processed in ways that destroy much of its flavanol content. This is covered in detail in Section 7.
  • The measurement problem: Standard dietary quality indices score whether a diet includes an appropriate variety of food groups. They do not typically measure specific plant compounds. It is entirely possible to score in the highest bracket of dietary quality while still having a substantial flavanol deficit because the scoring system was not designed to detect this specific gap.
  • The knowledge gap: Most midlife women have never heard specific advice about flavanols. Standard nutrition education emphasizes food groups—such as fruits, vegetables, and whole grains—rather than individual plant compounds. Without specific knowledge, the flavanol gap remains invisible.

Falling short of the flavanol threshold is not a failure of dietary discipline. It is a predictable consequence of following standard advice that was never designed to ensure adequate flavanol intake.

Closing the gap requires more specific knowledge about which foods provide meaningful amounts of flavanols and how processing, variety, and preparation affect their content. That is what the rest of this article provides.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

What Are the Six Health Effects That Make Flavanols Worth Attention?

The reason the flavanol conversation matters more than most single-compound conversations in nutrition is that the effects span several body systems in ways that are particularly relevant to midlife women. Six specific effect areas are worth understanding in detail.

Effect 1: Cardiovascular Health

The COSMOS trial found a 27% reduction in cardiovascular death and meaningful reductions in cardiovascular events at 500 mg daily. The mechanism involves improved endothelial function, better nitric oxide availability, reduced arterial stiffness, and improvements in blood pressure and lipid profiles. For midlife women whose cardiovascular risk rises significantly through the menopause transition, this is the single most important effect.

Effect 2: Cognitive Function and Hippocampal Memory

A sub-study of COSMOS looked specifically at cognition. The overall primary cognitive outcome was not significant across the whole sample, but among participants with lower baseline diet quality and lower baseline flavanol intake, the intervention appeared to restore hippocampal memory function. The pattern suggests a depletion-repletion effect where the flavanols help brains that were most depleted. Midlife women often have some cognitive shifts around perimenopause that map onto this pattern.

Effect 3: Blood Sugar and Insulin Regulation

A meta-analysis of nineteen randomized trials of cocoa flavanols found significant improvements in fasting insulin, HOMA-IR (a marker of insulin resistance), and fasting glucose. A separate large observational cohort found that higher flavonoid-rich diets were associated with 26% lower risk of developing type 2 diabetes. For midlife women whose insulin sensitivity declines through the menopause window, this metabolic effect is directly relevant.

Effect 4: Exercise Capacity

A trial in older adults (age 55 to 79) using a higher dose (1000 mg per day of cocoa flavanols split into two doses) over 30 days found significant improvements in peak oxygen uptake, maximum exercise capacity, blood pressure, and vascular function. For midlife women trying to maintain the fitness and function that support aging well, this effect is meaningful.

Effect 5: Skin Aging

A 24-week randomized trial in women with moderate photo-aging used 320 mg per day of cocoa flavanols and found reductions in facial wrinkles and improvements in skin elasticity. This is one of the few flavanol trials conducted specifically in a female population and specifically for a skin outcome that midlife women often care about.

Effect 6: Longevity

A Danish cohort study followed more than 56,000 adults over 23 years and found that total flavonoid intake was associated with lower all-cause mortality, cardiovascular mortality, and cancer mortality. The benefit appeared to plateau at approximately 500 mg per day of total flavonoids. This finding tracks a broader compound family than just flavan-3-ols, but the convergence around the same intake threshold is notable.

The pattern across effects. When a single dietary compound demonstrates meaningful effects across cardiovascular, cognitive, metabolic, physical fitness, dermatological, and mortality outcomes at roughly the same intake level, that pattern is unusual in the nutrition literature. Most single-compound interventions show benefit in one or two areas but not across multiple systems. The flavan-3-ol pattern suggests a fundamental biological role rather than a narrow niche effect.

What Are the Best Food Sources of Flavanols?

Reaching the 500 mg daily threshold through food requires knowing which specific foods deliver meaningful amounts. The list is not long, and it is not what most people would guess.

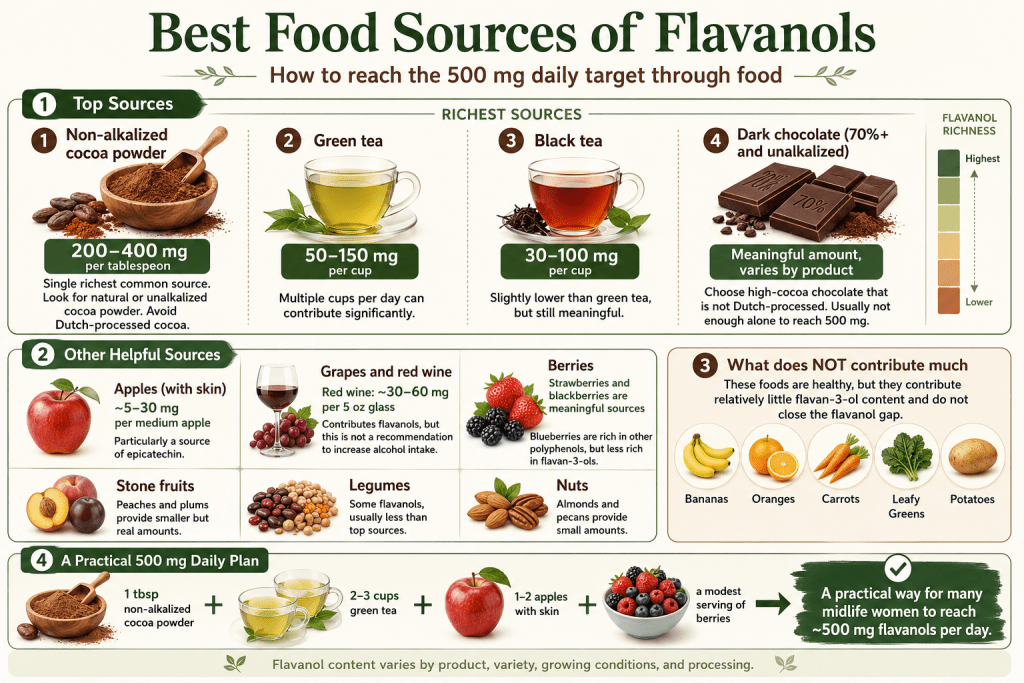
Flavanol-rich foods and a practical 500 mg daily plan.
  • Non-alkalized cocoa powder: The single richest common source. A tablespoon of unalkalized (natural) cocoa powder can contain 200 to 400 mg of flavanols depending on the specific product. This is the single most efficient food-based way to close the flavanol gap. Look for “natural cocoa powder” or “unalkalized cocoa powder” on the label. Avoid Dutch-processed cocoa (see Section 7).
  • Dark chocolate (specifically high-cocoa, unalkalized): Dark chocolate can contribute meaningful flavanols but the amount varies substantially by product. Chocolate with a high cocoa percentage (70% or higher) that has not been Dutch-processed is preferable. Even good dark chocolate typically requires eating more than most people would want to reach 500 mg from chocolate alone.
  • Green tea: A cup of well-brewed green tea can contain 50 to 150 mg of flavanols. Multiple cups per day can contribute significantly. The specific flavanol content depends on brewing time, water temperature, and tea quality.
  • Black tea: Slightly lower in flavanols than green tea, but still meaningful. A cup of well-brewed black tea can contain 30 to 100 mg of flavanols.
  • Apples: Apples contribute meaningful flavanols, particularly epicatechin. The amount varies enormously by variety and growing conditions (up to tenfold differences between apples of the same variety grown in different conditions). Estimates range from 5 to 30 mg per medium apple. Eating apples with the skin captures the most flavanols.
  • Grapes and red wine: Grapes and red wine contribute flavanols. A five-ounce glass of red wine can contribute approximately 30 to 60 mg of flavanols, though the alcohol content complicates the health equation for midlife women and this is not a recommendation to increase alcohol intake.
  • Berries: Strawberries and blackberries contain meaningful amounts of flavanols. Blueberries contain other beneficial polyphenols (anthocyanins) that are health-supportive but less rich in the specific flavan-3-ol group.
  • Stone fruits: Peaches and plums contribute smaller but real amounts of flavanols.
  • Legumes: Certain legumes contain some flavanols, though generally in smaller amounts than the top sources.
  • Nuts: Almonds and pecans contribute small amounts of flavanols along with their broader nutritional value.
  • What does not contribute much: Bananas, oranges, carrots, most leafy greens, potatoes, and most other common produce items contribute relatively little flavan-3-ol content. This is not a reason to eat less of them (they have other benefits), but they do not close the flavanol gap.
  • A practical daily target: For most midlife women, reaching 500 mg per day is achievable through a combination of one tablespoon of non-alkalized cocoa powder in a morning drink or oatmeal, two to three cups of green tea, one to two apples with skin, and modest berry intake. This total is not difficult once the specific foods are identified.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

Why Does Most Cocoa Powder Contain So Few Flavanols?

The processing problem for cocoa is one of the most important pieces of the flavanol conversation because cocoa is the single richest natural source, and most commercially available cocoa products have been processed in ways that destroy the flavanol content.

  • What Dutching (alkalization) does: Dutching is a manufacturing process that treats cocoa with alkaline solutions to reduce bitterness, darken the color, and improve mixing properties. The process was developed in the Netherlands in the 1820s and has become the dominant processing method for commercial cocoa. Most cocoa powder found in grocery stores has been Dutch-processed.
  • The impact on flavanols: A 2008 analysis of commercial cocoa powders found that non-alkalized (natural) cocoa averaged approximately 34.6 mg of flavanols per gram. Light alkalization dropped this to approximately 13.8 mg per gram. Medium alkalization dropped it to approximately 7.8 mg per gram. Heavy alkalization dropped it to approximately 3.9 mg per gram. The difference between the least processed and the most processed cocoa is roughly ninefold.
  • Reading labels: The distinction is important enough to check labels carefully. Look for “natural cocoa powder” or “unalkalized cocoa powder.” Products labeled “Dutch-processed,” “processed with alkali,” “cocoa processed with alkali,” or “European style” have been alkalized and contain much less flavanol content. Some products are silent on the processing method, which usually indicates alkalization.
  • The taste and color difference: Natural cocoa is lighter in color and has a more acidic, sharper taste. Dutch-processed cocoa is darker in color and has a smoother, milder taste. Most familiar dark cocoa aesthetics come from Dutching, which is why some people find natural cocoa unfamiliar initially. Combining natural cocoa with sweetness (a small amount of maple syrup, honey, or dates) and warm milk creates a hot chocolate that tastes rich without needing the Dutch-processed profile.
  • The dark chocolate question: Not all dark chocolate is Dutch-processed, but many mass-market dark chocolates are. Reading labels carefully or choosing brands that specifically state their cocoa is non-alkalized helps. A 70% cocoa dark chocolate that has not been Dutched will contain much more flavanol content than a 90% cocoa dark chocolate that has been.
  • The FDA qualified health claim: The FDA’s 2023 qualified health claim for cocoa flavanols specifies high-flavanol cocoa powder, not dark chocolate or other cocoa products generally, precisely because the flavanol content of common cocoa products is often insufficient to produce the cardiovascular effects.
  • The practical implication: Adding a tablespoon of natural cocoa powder to your morning oatmeal, coffee, or smoothie is the single easiest way to close a significant portion of the flavanol gap. Doing the same with Dutch-processed cocoa contributes much less. The specific choice of cocoa product matters more than the amount consumed.

How Many Flavanols Do You Need Per Day?

The specific daily target for flavanols is worth being clear about because it shapes every food decision that follows.

  • The Academy of Nutrition and Dietetics 2022 guideline: The professional guideline for cardiometabolic health is 400 to 600 mg per day of flavan-3-ols, with 500 mg as a reasonable central target.
  • The COSMOS trial dose: The trial used 500 mg of total cocoa flavanols including 80 mg of epicatechin per day. This is the reference point for most current recommendations.
  • The Danish longevity study: The mortality benefit associated with total flavonoid intake (a broader category than just flavan-3-ols) plateaued at approximately 500 mg per day.
  • The convergence: Three separate lines of evidence (professional guideline, largest cardiovascular trial, largest longevity cohort) converge on approximately 500 mg per day as a meaningful target. This convergence is one of the reasons to treat 500 mg per day as a working goal.
  • Whether more is better: Some trials have used higher doses (1000 mg per day for exercise capacity studies) and shown additional effects. The relationship between dose and benefit above 500 mg per day is not fully mapped, but there does not appear to be strong evidence for pushing well above 600 to 800 mg for most healthy adults.
  • Whether less is beneficial: Even amounts below 500 mg per day are almost certainly better than very low intake. The 500 mg target is a specific evidence-informed goal, not a minimum threshold below which the compound stops working. If you can move from 100 mg per day to 300 mg per day, that is meaningful progress even if you do not immediately reach the 500 mg mark.
  • Consistency matters: Daily intake produces stronger evidence-based effects than occasional intake. Building the flavanol-rich foods into a daily routine matters more than occasionally high-intake days.
  • Individual variability: Different people metabolize flavanols differently, and gut microbiome differences affect the specific metabolites produced. The 500 mg population target is a reasonable working goal but individual responses vary.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

How Can You Build a Flavanol-Rich Daily Framework?

Reaching 500 mg per day through food is achievable with a specific framework that adds flavanol-rich foods to the daily rhythm without disrupting the broader nutrition foundation.

  • The morning cocoa anchor: One tablespoon of natural (unalkalized) cocoa powder mixed into oatmeal, a protein shake, warm milk, or coffee contributes 200 to 400 mg of flavanols. This single practice provides the majority of the daily target. Adding a small amount of natural sweetness (a teaspoon of maple syrup, honey, or a chopped date) makes the taste enjoyable without turning the practice into a dessert.
  • Green or black tea throughout the day: Two to three cups of well-brewed tea contribute 100 to 300 mg of flavanols. Substituting tea for one cup of coffee is often easier than adding tea on top of an existing coffee habit.
  • Daily apple with skin: A whole apple with skin contributes 5 to 30 mg of flavanols. Choosing higher-flavanol varieties like Granny Smith, Fuji, or Red Delicious over lower-flavanol varieties helps.
  • Berries at least three times a week: A cup of strawberries or blackberries contributes meaningful flavanols. Frozen berries are as good as fresh for this purpose.
  • A small piece of high-quality dark chocolate: One ounce of 70% or higher non-alkalized dark chocolate contributes 20 to 100 mg of flavanols. As a dessert or afternoon snack, this is a pleasant addition rather than a restrictive imposition.
  • Cooking with cocoa: Beyond drinks, natural cocoa can be added to smoothies, oatmeal, chia pudding, energy bars, savory recipes (mole, chili), and baked goods. The bitterness of natural cocoa softens when balanced with other flavors.
  • The nutrition foundation underneath: Flavanols work best as an addition to an already-solid nutrition foundation of adequate protein, appropriate calorie balance, and whole-food emphasis. The free Macro Calculator and Macro Miracle Mediterranean Cookbook cover the foundation.
  • The realistic daily total: For most midlife women, a daily pattern of morning cocoa plus two to three cups of tea plus one apple plus modest berry intake reaches or exceeds 500 mg of flavan-3-ols without any exotic ingredients or complicated preparation.

“The morning cocoa is the most impactful single practice I have added to my own routine and to what I recommend to coaching clients in the last two years. It costs almost nothing, tastes better than most morning drinks, and delivers what the recent research suggests is a meaningful daily dose of the compound most associated with cardiovascular protection in this life stage. A tablespoon of natural cocoa powder, warmed with milk of choice, a teaspoon of maple syrup, and a pinch of salt. That is thirty seconds of preparation and about 200 to 300 mg of flavanols. Combined with two cups of tea and an apple, most women can hit the 500 mg mark by early afternoon without anything else changing about their diet. This is the kind of small, high-value change that makes evidence-based nutrition feel accessible rather than complicated.”

Terry Tateossian, Founder of The House of Rose

What Does a 7-Day Flavanol Framework Look Like?

The following 7-day framework provides a specific structure for building the flavanol-rich foods into a daily rhythm. Total daily flavanol content targets 500 mg or higher through food alone. All foods are compatible with the broader THOR nutrition framework.

Day 1: Anchor the Morning Cocoa

Meal

Flavanol source

Approx mg

Breakfast

1 tbsp natural cocoa in oatmeal

250

Morning

1 cup green tea

100

Lunch

Apple with lunch

15

Afternoon

1 cup green tea

100

Total

~465

Day 2: Add the Second Apple

Meal

Flavanol source

Approx mg

Breakfast

1 tbsp natural cocoa in coffee

250

Morning

1 cup black tea

60

Lunch

Apple with lunch

15

Afternoon

1 cup green tea

100

Snack

Apple with almonds

15

Total

~440

Day 3: Introduce Berries

Meal

Flavanol source

Approx mg

Breakfast

Berries with yogurt + 1 tbsp cocoa

300

Morning

1 cup green tea

100

Lunch

Apple with lunch

15

Afternoon

1 cup green tea

100

Total

~515

Day 4: Add Dark Chocolate

Meal

Flavanol source

Approx mg

Breakfast

1 tbsp natural cocoa in smoothie

250

Morning

1 cup green tea

100

Lunch

Apple with lunch

15

Afternoon

1 oz 85% dark chocolate

60

Evening

1 cup black tea

60

Total

~485

Day 5: Full Flavanol Day

Meal

Flavanol source

Approx mg

Breakfast

Berries + 1 tbsp cocoa oatmeal

320

Morning

1 cup green tea

100

Lunch

Apple with lunch

20

Afternoon

1 oz dark chocolate + green tea

160

Total

~600

Day 6: Simple Pattern

Meal

Flavanol source

Approx mg

Breakfast

1 tbsp natural cocoa in coffee

250

Morning

1 cup green tea

100

Lunch

Apple with lunch

15

Afternoon

1 cup green tea + berries

180

Total

~545

Day 7: Rest Day Pattern

Meal

Flavanol source

Approx mg

Breakfast

1 tbsp natural cocoa smoothie with berries

350

Lunch

Apple with lunch

15

Afternoon

1 cup green tea

100

Evening

1 oz dark chocolate

60

Total

~525

Continuing after the first week. The pattern is not complicated. Morning cocoa is the anchor. Tea throughout the day is the multiplier. Apple with lunch and berries several times a week are the reliable adds. Dark chocolate is the pleasant flexibility. Once these habits are installed, hitting 500 mg per day becomes automatic rather than deliberate.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

Should You Take Flavanol Supplements?

The supplement question is worth addressing directly because flavanol supplements are available and heavily marketed, and the honest picture is more nuanced than the marketing suggests.

Flavanol supplements versus food guide.
  • The COSMOS trial used a supplement: The trial itself used a specific standardized cocoa extract supplement, not food. This means the cardiovascular benefits shown in the trial were produced by supplemental flavanols rather than by dietary changes.
  • Whole-food advantages: Food sources of flavanols come with additional nutrients (fiber, vitamins, minerals, other polyphenols) that supplements do not provide. There may be synergistic effects between flavanols and other compounds in whole foods that supplements do not capture. Food-based practice also builds general dietary habits that produce many downstream benefits beyond flavanol intake.
  • Supplement advantages: Standardization is one advantage. A COSMOS-style supplement provides a known, consistent dose that food-based approaches cannot match exactly. For people who cannot or will not adopt the food-based habits, a supplement can close the intake gap that food would otherwise leave open.
  • Quality variation: As with most supplements, the market includes both well-formulated products and poor ones. Look for supplements that specify the flavan-3-ol content (not just total polyphenol content), that use standardized cocoa extract, and that have third-party testing.
  • Cost considerations: High-quality flavanol supplements cost more than the equivalent food-based approach. A month of natural cocoa powder plus tea plus apples typically costs less than one bottle of a good flavanol supplement.
  • A reasonable combined approach: For most midlife women, a food-first approach with supplementation as a backup on days when food intake falls short is a reasonable framework. For women with specific cardiovascular risk factors who want the trial-tested standardized dose, a COSMOS-style supplement in addition to a food-based practice is a defensible choice made in conversation with a healthcare provider.
  • What to avoid: Products marketed as flavanol supplements that do not specify their actual flavan-3-ol content on the label are not worth buying. Products that mix flavanols with a proprietary blend of other compounds at unspecified amounts are usually less useful than a straight cocoa extract. Products that make miracle-cure claims should be avoided.
  • Discussion with your provider: Any supplement decision should be discussed with your healthcare provider, particularly if you are on blood-thinning medications (some polyphenol supplements have mild anticoagulant effects) or have other medical conditions.

What Common Mistakes Can Undermine Your Flavanol Intake?

Six common mistakes consistently reduce the flavanol benefit for midlife women trying to close the intake gap.

  • Buying Dutch-processed cocoa without realizing it: Most grocery-store cocoa is Dutch-processed. Reading the label carefully is essential. If the label does not specify natural or unalkalized, assume it has been Dutched and buy something else.
  • Assuming all dark chocolate is flavanol-rich: Percentage of cocoa is only part of the picture. A 90% dark chocolate that has been Dutch-processed contains less flavanol than a 70% dark chocolate that has not. Read the ingredient list for processing method.
  • Eating flavanol-rich foods sporadically rather than daily: The evidence base is built on daily intake. Occasional bursts of flavanol-rich eating do not produce the same effects as consistent daily intake.
  • Overrelying on general produce recommendations: Eating more bananas, oranges, and lettuce does not close the flavanol gap. Specific high-flavanol foods matter more than general produce volume.
  • Skipping the tea because coffee is preferred: Tea is one of the most convenient flavanol delivery vehicles. Even substituting one afternoon coffee for tea makes a meaningful difference. Green tea has more flavanols than black, but black tea still contributes significantly.
  • Waiting for supplements to close the gap: Supplements can close the gap, but food-based practice provides broader nutritional benefits that supplements do not. Start with food. Consider supplements only if food-based practice consistently falls short.
  • Ignoring the nutrition foundation underneath: Flavanols cannot compensate for inadequate protein, poor sleep, chronic stress, or a diet built around processed foods. The flavanol layer sits on top of a foundational nutrition framework, not in place of one.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

What Are Your Next Steps for Increasing Flavanol Intake?

If the framework in this article resonates and you want to close the flavanol gap in your own diet, here are the four next steps in order of friction.

  1. Buy natural cocoa powder this week. Read labels carefully. Look for “natural cocoa powder” or “unalkalized cocoa powder.” Avoid anything labeled “processed with alkali,” “Dutch-processed,” or “European style.”
  2. Establish the morning cocoa habit. One tablespoon of natural cocoa in oatmeal, a protein shake, warm milk, or coffee every morning for the next four weeks. This single habit closes the majority of the flavanol gap.
  3. Add tea and apples on top. Two to three cups of green or black tea daily. An apple with lunch. Three servings of berries per week. These additions bring most women well past the 500 mg target.

Frequently Asked Questions

What are flavanols?

Flavanols are a subfamily of plant compounds within the flavonoid group of polyphenols. The specific flavan-3-ol group (which includes epicatechin and catechin) is the subgroup most linked to cardiovascular and cognitive health in recent research. The richest food sources are non-alkalized cocoa, tea, apples, grapes, and certain berries.

How much flavanols per day do I need?

The Academy of Nutrition and Dietetics 2022 guideline for cardiometabolic health recommends 400 to 600 mg per day of flavan-3-ols. The specific target of 500 mg per day aligns with the dose used in the COSMOS cardiovascular trial and with the plateau observed in the Danish longevity study. Most midlife women can reach this target through a combination of natural cocoa, tea, apples, and berries.

Are flavanols safe during menopause?

Flavanols from food sources are generally safe during perimenopause and menopause and may be particularly beneficial given the cardiovascular risk shifts of this window. Flavanol supplements should be discussed with your healthcare provider, particularly if you are on any medications.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

What is the difference between flavanols and flavonoids?

Flavonoids are the broader family of plant compounds. Flavanols (specifically flavan-3-ols) are one subfamily within flavonoids. Other flavonoid subfamilies include flavonols (like quercetin), anthocyanins, and isoflavones. The recent cardiovascular research on 500 mg per day addresses the flavan-3-ol group.

Can I get enough flavanols from a healthy diet?

Recent biomarker research suggests that roughly four out of five adults do not reach the 500 mg per day threshold even when following standard dietary recommendations. Closing the gap requires specific choices around cocoa, tea, apples, and berries rather than general produce increases.

What is the best cocoa powder for flavanols?

Look for natural (unalkalized) cocoa powder. Read labels carefully. Avoid anything labeled Dutch-processed, processed with alkali, or European style, because these processing methods destroy most of the flavanol content. Quality natural cocoa powder is widely available at reasonable cost.

How much dark chocolate should I eat for flavanols?

One ounce (approximately 28 grams) of high-quality non-alkalized dark chocolate at 70% cocoa or higher contributes 20 to 100 mg of flavanols depending on the specific product. Even the best dark chocolate typically requires larger amounts than most people would want to eat to reach 500 mg from chocolate alone. Cocoa powder is a more efficient source per calorie.

Do flavanol supplements work?

The COSMOS trial used a supplement and produced meaningful cardiovascular effects, so supplements can work when they contain standardized doses of actual flavan-3-ols. Look for products that specify flavan-3-ol content on the label. Discuss with your healthcare provider before starting any supplement, particularly if you are on blood-thinning medications.

What is the COSMOS trial?

COSMOS (Cocoa Supplement and Multivitamin Outcomes Study) is the largest randomized trial ever conducted on cocoa flavanols and cardiovascular outcomes. It enrolled more than 21,000 older adults and found a 27% reduction in cardiovascular death (a pre-specified secondary endpoint) with 500 mg per day of cocoa flavanols including 80 mg of epicatechin. The primary endpoint of the combined cardiovascular events was reduced 10%, which did not reach conventional significance.

Can flavanols help with menopause brain fog?

The COSMOS cognitive sub-study found that flavanol intervention appeared to restore hippocampal memory function in participants who started with the lowest baseline diet quality and flavanol intake, suggesting a depletion-repletion pattern. The direct research on menopause-specific brain fog is limited, but the mechanism is plausible and the food-based intervention is low-risk.

Are flavanols good for skin aging?

A 24-week randomized trial in women with moderate photo-aging found that 320 mg per day of cocoa flavanols reduced facial wrinkles and improved skin elasticity. This is one of the few flavanol trials in a female-specific population targeting a skin outcome. The evidence supports flavanols as a supportive intervention for skin aging alongside other approaches.

Can I take flavanols with my heart medication?

Some polyphenols including flavanols have mild anticoagulant effects. If you are on blood-thinning medications like warfarin or apixaban, discuss any significant change in flavanol intake or any flavanol supplement with your prescribing physician. Normal food-based intake of flavanol-rich foods is generally considered safe but disclosure to your provider is appropriate.

Do flavanols help with type 2 diabetes?

A meta-analysis of nineteen randomized trials of cocoa flavanols found significant improvements in fasting insulin, insulin resistance (HOMA-IR), and fasting glucose. A large observational cohort found that higher flavonoid intake was associated with 26% lower risk of developing type 2 diabetes. Discuss any dietary changes with your diabetes care team if you are managing diabetes.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

Is green tea or black tea better for flavanols?

Green tea contains higher amounts of flavanols per cup than black tea on average, but both contribute meaningfully. Black tea also contains flavanols along with other polyphenols. Choosing whichever tea you enjoy and will actually drink consistently matters more than optimizing for the specific type.

How long before I see benefits from flavanols?

Cardiovascular biomarkers like blood pressure and vascular function can improve within days to weeks of consistent flavanol intake. Deeper cardiovascular protection develops over years of consistent intake. The mortality signals in the observational literature are based on years to decades of dietary patterns. Flavanol optimization is a long-term intervention, not a short-term fix.

References

  • Sesso, H. D., Manson, J. E., Aragaki, A. K., et al. (2022). Effect of cocoa flavanol supplementation for the prevention of cardiovascular disease events: the COcoa Supplement and Multivitamin Outcomes Study (COSMOS) randomized clinical trial. American Journal of Clinical Nutrition, 115(6), 1490–1500.
  • Baker, L. D., Manson, J. E., Rapp, S. R., et al. (2023). Effects of cocoa extract and a multivitamin on cognitive function: a randomized clinical trial. Alzheimer’s and Dementia, 19(4), 1308–1319.
  • Crowe-White, K. M., Evans, L. W., Kuhnle, G. G. C., et al. (2022). Flavan-3-ols and cardiometabolic health: first ever dietary bioactive guideline. Advances in Nutrition, 13(6), 2070–2083.
  • Bondonno, N. P., Dalgaard, F., Kyrø, C., et al. (2019). Flavonoid intake is associated with lower mortality in the Danish Diet Cancer and Health Cohort. Nature Communications, 10(1), 3651.
  • Lin, X., Zhang, I., Li, A., et al. (2016). Cocoa flavanol intake and biomarkers for cardiometabolic health: a systematic review and meta-analysis of randomized controlled trials. Journal of Nutrition, 146(11), 2325–2333.
  • Miller, K. B., Hurst, W. J., Payne, M. J., et al. (2008). Impact of alkalization on the antioxidant and flavanol content of commercial cocoa powders. Journal of Agricultural and Food Chemistry, 56(18), 8527–8533.
  • Neshatdoust, S., Saunders, C., Castle, S. M., et al. (2016). High-flavonoid intake induces cognitive improvements linked to changes in serum brain-derived neurotrophic factor: two randomised, controlled trials. Nutrition and Healthy Aging, 4(1), 81–93.
  • Sansone, R., Rodriguez-Mateos, A., Heuel, J., et al. (2015). Cocoa flavanol intake improves endothelial function and Framingham Risk Score in healthy men and women: a randomised, controlled, double-masked trial: the Flaviola Health Study. British Journal of Nutrition, 114(8), 1246–1255.
  • Ostertag, L. M., O’Kennedy, N., Kroon, P. A., et al. (2010). Impact of dietary polyphenols on human platelet function: a critical review of controlled dietary intervention studies. Molecular Nutrition and Food Research, 54(1), 60–81.
  • Rodriguez-Mateos, A., Cifuentes-Gomez, T., Tabatabaee, S., et al. (2012). Procyanidin, anthocyanin, and chlorogenic acid contents of highbush and lowbush blueberries. Journal of Agricultural and Food Chemistry, 60(23), 5772–5778.
  • Buijsse, B., Weikert, C., Drogan, D., et al. (2010). Chocolate consumption in relation to blood pressure and risk of cardiovascular disease in German adults. European Heart Journal, 31(13), 1616–1623.
  • Yamashita, Y., Wang, L., Nakamura, A., et al. (2016). Cacao liquor procyanidins prevent postprandial hyperglycaemia by increasing glucagon-like peptide-1 activity and glucose uptake in mice. Journal of Nutritional Science, 5, e37.
  • Grassi, D., Desideri, G., & Ferri, C. (2013). Blood pressure and cardiovascular risk: what about cocoa and chocolate? Archives of Biochemistry and Biophysics, 501(1), 112–115.
  • Farah, A. R., Faramarzi, H., & Rafraf, M. (2020). The effect of dark chocolate consumption on facial wrinkles and skin elasticity in women with moderate photo-aging: a randomized clinical trial. Journal of Cosmetic Dermatology, 19(9), 2237–2243.
  • Sarriá, B., Martínez-López, S., Sierra-Cinos, J. L., et al. (2014). Regular consumption of a cocoa product improves the cardiometabolic profile in healthy and moderately hypercholesterolaemic adults. British Journal of Nutrition, 111(1), 122–134.
  • Ellinger, S., & Stehle, P. (2016). Impact of cocoa consumption on inflammation processes: a critical review of randomized controlled trials. Nutrients, 8(6), 321.
  • Corti, R., Flammer, A. J., Hollenberg, N. K., & Lüscher, T. F. (2009). Cocoa and cardiovascular health. Circulation, 119(10), 1433–1441.
  • Ottaviani, J. I., Britten, A., Lucarelli, D., et al. (2020). Biomarker-estimated flavan-3-ol intake is associated with lower blood pressure in cross-sectional analysis in EPIC Norfolk. Scientific Reports, 10(1), 17964.
  • Kroon, P. A., Iyer, A., Chunduri, P., et al. (2010). The cardiovascular nutrapharmacology of resveratrol: pharmacokinetics, molecular mechanisms and therapeutic potential. Current Medicinal Chemistry, 17(23), 2442–2455.
  • Tsang, C., Higgins, S., Duthie, G. G., et al. (2012). The effect of consumption of red wine on antioxidant status in healthy subjects. Journal of Human Nutrition and Dietetics, 25(3), 195–202.

Disclaimer: Always consult with a qualified healthcare professional before making significant changes to your diet or starting any new supplement, particularly if you have cardiovascular disease, diabetes, are taking blood-thinning medications, or have any specific health conditions that require dietary management. This article is educational and does not constitute medical advice.

Free Macro Calculator

Personalized to your body, goals, and measurements. You will receive detailed macros for meals, sample day of eating, food selection guidance, hydration + daily supplement suggestions, and more.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Ayurveda for Women Over 40: A Complete Guide to Doshas, Daily Routines, and What Midlife Women Should Know

Ayurveda is a living tradition rooted in South Asian civilization and developed over several thousand years. It is not a Western wellness trend, lifestyle brand, or aesthetic. Yet in Western wellness culture, it is often reduced to simple dosha quizzes, borrowed terms, and product marketing that does not reflect classical practice.

This article offers a respectful educational introduction from the perspective of a modern midlife women’s health coach, not an Ayurvedic practitioner. Where Ayurveda and evidence-based health practices overlap, I explain the connection. Where they differ, I address those differences honestly. The tradition belongs to South Asian communities and the trained practitioners who continue to preserve it.

Ayurveda appeals to many women over 40 because it recognizes that bodies, needs, and life stages differ. It also treats food, stress, digestion, sleep, hormones, and daily routines as interconnected rather than separate concerns. This whole-person framework can feel especially relevant during perimenopause, menopause, and post-menopause.

I am Terry Tateossian, founder of The House of Rose and a certified lifestyle medicine coach. I lead nutrition-focused wellness retreats for midlife women at our Smoky Mountains property in East Tennessee. THOR is not an Ayurvedic clinic, and my training is in evidence-based lifestyle medicine rather than classical Ayurveda. This guide draws from my study of the tradition, current research, and years of coaching women through the menopause transition.

Important: This article is educational and does not constitute medical advice. Consult a qualified healthcare provider before using herbal supplements, treatments, or making significant lifestyle changes.

What Is Ayurveda?

Ayurveda is a system of health and medicine that developed within the broader Vedic tradition of South Asia over a period of several thousand years. The word itself is derived from two Sanskrit terms: ayus (meaning life or lifespan) and veda (meaning knowledge or science). Ayurveda therefore translates roughly as the science of life or the knowledge of longevity.

Overview of Ayurveda and its key principles.
  • Its classical texts: The foundational texts of Ayurveda include the Charaka Samhita, the Sushruta Samhita, and the Ashtanga Hridayam. These works are extensive treatises on anatomy, physiology, diagnosis, treatment, surgery, pharmacology, ethics, and public health. They are not simple herbal manuals. They represent one of the most detailed pre-modern systems of medicine ever compiled.
  • Its scope: Ayurveda addresses individual constitution, seasonal and daily rhythms, nutrition, sleep, elimination, sexuality, relationships, meditation, ethics, herbal medicine, cleansing therapies, massage, oil applications, minor surgery, obstetrics, and geriatric care. In classical practice it functions as a complete healthcare system that has served entire populations for millennia.
  • Its living status: Ayurveda is not a historical curiosity. It is a living tradition practiced by thousands of qualified doctors in South Asia and by trained practitioners worldwide. In India specifically, Ayurvedic medicine is a recognized medical profession with formal education, licensure, and regulation.
  • Its philosophical grounding: Ayurveda emerges from a broader Vedic worldview that includes yoga, jyotish (traditional astrology), and darshanas (philosophical schools). These systems share the same underlying assumptions about consciousness, the body, and the natural world. Ayurveda cannot be fully understood without some familiarity with this broader philosophical context, which is covered in Section 3 of this article.
  • Its relationship to Western medicine: Ayurveda and Western biomedicine operate from different philosophical foundations, use different diagnostic categories, and often prescribe different interventions. They are not the same. They are also not always incompatible. The most productive framing is that they are complementary systems that address overlapping but not identical questions, and that midlife women can benefit from the insights of both when the recommendations are handled thoughtfully.
  • What it is not: Ayurveda is not a dosha quiz on a wellness website. It is not a brand of turmeric supplements. It is not a lifestyle aesthetic on Instagram. It is not a substitute for medical care for serious conditions. Reducing it to any of these is a disservice to the tradition and often to the person doing the reducing.

Why Are Midlife Women Exploring Ayurveda?

Search interest in Ayurveda among midlife women has grown substantially over the last five years, and the reasons are specific to this life stage.

  • Menopause is under-served in conventional Western medicine: Many midlife women have discovered that their conventional providers offer limited support for perimenopause and menopause beyond hormone therapy and antidepressants. When women seek a more comprehensive framework for the transition, they often begin exploring traditions that have always addressed life-stage transitions systematically. Ayurveda is one of those traditions.
  • The exhaustion of the reductionist approach: The Western medical model of one symptom, one diagnosis, one prescription often falls short for the interconnected, whole-body, hormonally-driven changes of midlife. Ayurveda’s insistence on treating the whole person over long time horizons resonates with women who have grown tired of fragmented care.
  • The daily routine emphasis: The Ayurvedic focus on daily routines (dinacharya) speaks to midlife women who have realized that occasional interventions do not produce the changes they need, and that consistent daily practice is where transformation actually happens.
  • The food-as-medicine framing: The Ayurvedic view that food is medicine, that meals should match the body’s constitution and the season, and that digestion is central to health, aligns with the intuitive understanding many midlife women have developed after years of trying to figure out why they feel differently after different foods.
  • The stress and nervous system framing: The Ayurvedic recognition that stress affects digestion, sleep, hormones, and mood as a unified system speaks directly to what most midlife women are experiencing.
  • The specific dosha resonance: Many midlife women immediately recognize themselves in one of the three dosha descriptions, and that recognition creates an experience of being seen and understood that conventional medicine often does not provide.
  • The cultural moment: Yoga has been mainstreamed in the West over the last several decades, and Ayurveda is now following a similar trajectory. High-profile books, podcasts, and wellness content have brought the tradition into general awareness in a way that was not true a decade ago.
  • The perimenopause peak: Perimenopause specifically produces the vata-imbalance pattern that Ayurveda has always addressed as one of its most common presentations. Women in this window often find Ayurvedic frameworks describing their experience with unusual precision.

“The most common way I see midlife women enter the Ayurveda conversation is through a specific moment of recognition. They read a description of vata imbalance, and something in them says, that is me. Or they read a description of the pitta pattern under stress, and they see a decade of their own frustration reflected back to them clearly for the first time. That moment of felt recognition is often what pulls them into the tradition. My role in coaching is not to be their Ayurvedic practitioner, because that is not my training. My role is to help them separate the parts of the tradition that overlap with the evidence base I do work in from the parts that require a qualified Ayurvedic practitioner. Where the overlap is strong, most notably in the daily routines, nutrition, sleep support, and nervous system regulation, the practical value is significant and easy to access. Where the tradition requires deeper knowledge, I refer them to a properly trained practitioner. That is the honest bridging role.”

Terry Tateossian, Founder of The House of Rose

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
What Is the Vedic Worldview Behind Ayurveda?

Ayurveda emerged from a specific philosophical worldview that shapes how the tradition thinks about the body, health, and disease. Understanding this worldview in accessible terms is essential for making sense of the specific recommendations that follow.

  • The universe as interconnected: The Vedic tradition views the universe as a single interconnected whole rather than as a collection of separate objects. Every part of nature is understood to be in continuous relationship with every other part. This is not mysticism. It is a specific philosophical position with implications for how the tradition views health.
  • The body as a small version of the universe: A well-known Ayurvedic principle holds that the human body reflects the same organizing patterns that shape the natural world. Not literally (the body does not contain miniature planets), but structurally (the same principles that produce rhythm in the seasons produce rhythm in the body).
  • The primacy of consciousness: The Vedic tradition places consciousness at the foundation of the natural world rather than viewing consciousness as a byproduct of brain activity. This is a significant philosophical difference from modern neuroscience, which generally holds the opposite view. Whether one accepts the Vedic position or the modern scientific position, the difference matters because it shapes how each system approaches health and disease.
  • The five great elements: The Vedic tradition describes the natural world as expressing five fundamental qualities: earth (structure and stability), water (cohesion and flow), fire (transformation and heat), air (movement and change), and space (openness and receptivity). These are not the elements of modern chemistry. They are qualities that appear at every level of the natural world and that combine in different proportions to produce different phenomena. Understanding this five-quality framework is essential for understanding the doshas that follow.
  • The concept of dosha: From the five elements arise three functional patterns called doshas: vata (space and air, governing movement and communication), pitta (fire and a small amount of water, governing transformation and metabolism), and kapha (earth and water, governing structure and cohesion). Every person contains all three doshas in some proportion. The specific proportion is called the individual constitution or prakriti.
  • The concept of imbalance: Health in Ayurveda is defined not as the absence of disease but as the presence of balance among the doshas, appropriate to the person’s constitution, life stage, season, and situation. Disease arises when the doshas fall out of the balance that person needs. The imbalance may be vata excess, pitta excess, kapha excess, or various combinations. Understanding the specific imbalance is the diagnostic goal, and correcting the imbalance is the therapeutic goal.
  • The role of consciousness in health: Because the tradition views consciousness as foundational, mental states are understood to affect physical health directly and continuously. Chronic anxiety, chronic anger, and chronic dullness are considered health issues in their own right, not just secondary consequences of physical illness. This is a framework that modern medicine has increasingly moved toward but that Ayurveda has held for millennia.
  • Modern parallels and modern differences: Modern systems biology has moved somewhat closer to the Ayurvedic view of interconnection over the last several decades, though the philosophical grounding remains different. The Vedic view that consciousness is fundamental has not been supported by modern neuroscience but also has not been definitively refuted, because the hard problem of consciousness remains an open question. The most productive attitude toward these philosophical differences is intellectual humility rather than false certainty in either direction.

What Are the Three Ayurvedic Doshas?

The three doshas are the most well-known concept in Ayurveda in the West, and they are also the most frequently misunderstood. Approaching them accurately requires setting aside the oversimplified wellness-website versions.

Three Ayurvedic doshas: Vata, Pitta, and Kapha.

Vata

The vata dosha combines the qualities of space and air. It governs all movement in the body: nervous system function, respiration, circulation, elimination, thought, speech, and every form of internal transport. When vata is balanced, movement is smooth, thought is clear, and the person feels light and energetic. When vata is in excess, movement becomes irregular (racing thoughts, insomnia, constipation, anxiety, dry skin, cracking joints, sensitivity to cold, difficulty with routine). Vata imbalance is one of the most common presentations in midlife women, particularly during perimenopause when the hormonal shift disrupts the systems that vata governs.

Pitta

The pitta dosha combines fire with a small amount of water. It governs all transformation in the body: digestion, metabolism, hormone conversion, enzymatic activity, temperature regulation, and mental clarity. When pitta is balanced, digestion is strong, energy is steady, mental focus is sharp, and the person is intelligent and confident. When pitta is in excess, transformation becomes overheated (irritability, criticism, perfectionism, heartburn, skin inflammation, rashes, sensitivity to heat, judgment of self and others). Pitta imbalance is common in midlife women who have been high-achievers with driving personalities and who often experience burnout in the perimenopause and menopause window.

Kapha

The kapha dosha combines earth and water. It governs all structure and cohesion in the body: bones, connective tissue, body fluids, immunity, patience, and endurance. When kapha is balanced, the person is stable, grounded, loyal, calm, and physically strong. When kapha is in excess, structure and cohesion become excessive (weight gain, water retention, congestion, lethargy, stubbornness, difficulty starting new things, depression that shows up as heaviness rather than agitation). Kapha imbalance can develop in post-menopausal women who have moved through the vata and pitta phases and settled into a more stable body composition with reduced activity levels.

What Should You Know About Your Dosha Constitution?

Understanding your dosha constitution involves more than identifying yourself as vata, pitta, or kapha. Every person has a unique combination of all three doshas, along with a natural birth constitution and a current state that can shift over time. These three points explain how dosha types work, why imbalances change, and why online quizzes should be treated as a starting point rather than a diagnosis.

  • The multi-dosha nature of every person: Every person contains all three doshas in some proportion. Some people are strongly single-dosha (mostly vata, mostly pitta, or mostly kapha). Many people are dual-dosha (vata-pitta, pitta-kapha, or vata-kapha). A smaller number are relatively balanced across all three (tri-doshic). Understanding your specific proportion is what makes personalized Ayurvedic recommendations possible.
  • Prakriti versus vikriti: The tradition distinguishes between your prakriti (your birth constitution, which does not change) and your vikriti (your current state of imbalance, which fluctuates with season, life stage, stress, and behavior). Meaningful Ayurvedic practice involves working with both.
  • A note on wellness-quiz doshas: Most online dosha quizzes are so simplified that they produce results of limited value. A ten-question quiz cannot capture the constitutional complexity that a trained Ayurvedic practitioner assesses through pulse reading, tongue examination, physical characteristics, medical history, family history, and extended conversation. Use online quizzes as a starting point for interest, not as a diagnostic.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How Can You Identify Your Dominant Dosha?

If you want to develop a working sense of your dominant dosha, the honest approach involves observing yourself across multiple dimensions over time rather than relying on a quick quiz. Below are the general patterns that characterize each dosha.

  • Physical characteristics: Vata-dominant people tend to be thin, with light bones, dry skin, cool hands and feet, small features, and difficulty gaining weight. Pitta-dominant people tend to be medium build, with warm skin, moderate features, tendency toward freckles or moles, and a moderate ability to gain or lose weight. Kapha-dominant people tend to be larger frame, with soft moist skin, thick hair, large features, tendency toward easy weight gain, and difficulty losing it.
  • Mental and emotional patterns: Vata-dominant people tend toward creativity, quickness, enthusiasm, and anxiety under stress. Pitta-dominant people tend toward intelligence, ambition, precision, and irritability under stress. Kapha-dominant people tend toward patience, loyalty, groundedness, and lethargy under stress.
  • Sleep patterns: Vata sleepers are light, easily disturbed, and often struggle with insomnia. Pitta sleepers are moderate, wake for a few hours in the middle of the night if imbalanced, and tend to run hot. Kapha sleepers are deep, long, and sometimes struggle to wake up.
  • Digestive patterns: Vata digestion is variable, with sensitivity to cold foods, tendency toward gas and bloating, and irregular appetite. Pitta digestion is strong, with intense hunger, tendency toward heartburn, and difficulty skipping meals. Kapha digestion is slow, with less hunger, tendency toward heaviness after eating, and better tolerance of skipped meals.
  • Response to stress: Vata under stress becomes anxious, scattered, and depleted. Pitta under stress becomes angry, critical, and burned out. Kapha under stress becomes withdrawn, heavy, and unmotivated.
  • Response to weather: Vata dislikes cold, wind, and dryness. Pitta dislikes heat, sun, and humidity. Kapha dislikes cold damp weather.
  • Movement style: Vata movement is quick, light, and sometimes uncoordinated. Pitta movement is purposeful, focused, and controlled. Kapha movement is steady, deliberate, and graceful.
  • A practical observation practice: For the next two weeks, notice your patterns across each of these dimensions. You may find you match one dosha across most dimensions, or you may find you are a combination. Both outcomes are legitimate. The point of the observation is to build a working understanding of your patterns rather than to arrive at a specific label.
  • If you want a professional assessment: A trained Ayurvedic practitioner can provide a much more accurate constitutional assessment than any self-directed approach. If you decide to pursue Ayurvedic care, that assessment is one of the primary values a practitioner offers.

How Do the Doshas Shift During Perimenopause and Menopause?

One of the most useful applications of Ayurvedic frameworks for midlife women specifically is the tradition’s clear articulation of how the doshas shift through life stages, and particularly through the perimenopause and menopause window.

The Life-Stage Framework

Ayurveda divides adult life into three broad stages according to the dominant dosha. Childhood and early adulthood are considered a kapha stage (growth, structure-building). Middle adulthood is considered a pitta stage (achievement, transformation, drive). Later adulthood is considered a vata stage (drying, thinning, more nervous system activity, greater sensitivity). Perimenopause and menopause represent the transition from the pitta stage into the vata stage, which is why so many midlife women experience the specific pattern of vata excess that this transition produces.

The Vata Excess of Perimenopause

The perimenopause window frequently produces or amplifies vata imbalance. This shows up as sleep disruption, anxiety, dry skin, thinning hair, joint aches, digestive irregularity, difficulty with routine, and a general felt-sense of ungroundedness. The Ayurvedic framing of this cluster as a single pattern (vata excess) rather than as several unrelated symptoms is one of the most immediately useful insights of the tradition for midlife women.

The Pitta Component

Many midlife women also experience pitta excess during the transition, particularly if they have been high-achievers running on ambition and driving through years of accumulated stress. The pitta excess shows up as irritability, hot flashes (which have a clear pitta quality), inflammation, criticism (of self and others), and burnout. Addressing this specific pattern is often required alongside the vata support.

The Kapha Component

Post-menopause frequently sees kapha excess develop, particularly as activity levels decline and body composition shifts. This shows up as weight gain, water retention, congestion, and reduced motivation. Addressing this pattern often becomes the focus once the vata and pitta transitions have stabilized.

The Traditional Recommendations for Each Pattern

For vata excess, the tradition recommends warm cooked foods, oil-rich meals, regular routine, warm sesame oil massage, calming practices, extra sleep, and reduced stimulation. For pitta excess, the tradition recommends cooling foods, reduced spice, cooling practices, appropriate rest, and reduced striving. For kapha excess, the tradition recommends lighter foods, warming spices, more movement, less sleep, and stimulation.

The Overlap With Modern Evidence

Most of these recommendations align surprisingly well with modern evidence-based recommendations for the specific patterns they describe. Warm cooked foods and regular routine for a stressed nervous system. Adequate rest and cooling practices for a burned-out achiever. More movement and less caloric density for post-menopausal weight management. The specific mechanisms are described differently in Ayurveda than in modern medicine, but the practical recommendations often converge.

The Specific Caution

The traditional Ayurvedic pharmacology for menopause includes some herbal formulations that have not been rigorously tested for safety or efficacy in modern studies. Some Ayurvedic herbs have documented interactions with common medications and some have been contaminated with heavy metals in commercial products. Any herbal Ayurvedic recommendation should be run by a qualified practitioner and, ideally, by your Western physician as well.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
What Is Dinacharya and How Does It Work?

Dinacharya is the traditional Ayurvedic daily routine. It is one of the most practical and immediately usable aspects of the tradition for modern midlife women, and it is one of the areas where the overlap with modern evidence-based recommendations is strongest.

Dinacharya daily routine and wellness practices.
  • The general shape of the traditional day: Rise before sunrise. Move through elimination and mouth, tongue, and face cleansing. Drink warm water. Apply oil to the body and self-massage. Bathe. Move through a chosen practice such as yoga or walking. Meditate. Eat breakfast if appropriate for the constitution. Move into work. Eat the largest meal at midday. Continue work. Eat a light early dinner. Wind down with quiet activity. Sleep before ten in the evening.
  • The specific practices worth adopting: Not every element of the traditional routine fits every modern life, and forcing all of it produces stress that undermines the point. The following elements are particularly well-supported by modern evidence and particularly accessible for midlife women.
  • Consistent wake time: Rising at the same time each day supports the circadian rhythm, which supports hormone balance, sleep quality, and mood. This is one of the most researched interventions in modern sleep science and one of the oldest recommendations in Ayurveda. The specific time (traditionally before sunrise) matters less than the consistency.
  • Warm water in the morning: Drinking a cup of warm water on waking supports digestion and hydration after the overnight fast. Modern evidence for this specific practice is limited but plausible. It is safe, cheap, and often subjectively pleasant.
  • Tongue scraping: Scraping the tongue with a copper or stainless steel scraper removes overnight bacterial buildup and may support oral health and taste sensitivity. Modern dental research broadly supports mechanical tongue cleaning.
  • Oil pulling: Swishing with sesame or coconut oil for five to ten minutes is a traditional oral hygiene practice. Some modern research supports oral health benefits, though evidence is not strong enough to replace conventional dental care.
  • Self-massage with warm oil (abhyanga): Traditional self-massage with warm sesame or coconut oil is deeply calming and often produces both physical and psychological benefit. Modern evidence supports touch therapy generally for cortisol reduction and parasympathetic activation.
  • Morning movement: Traditional Ayurveda recommends gentle to moderate morning movement. Modern evidence broadly supports morning exercise for circadian rhythm anchoring, mood, and metabolic health.
  • Meditation or quiet time: Even ten minutes of quiet sitting supports nervous system regulation and cognitive function. This is one of the most consistent recommendations across the tradition and one of the most researched in modern practice.
  • Largest meal at midday: Eating the biggest meal when digestive fire (agni) is strongest, and eating lighter in the evening, supports metabolic health, sleep, and body composition. Modern chrononutrition research broadly supports this pattern.
  • Early dinner: Finishing dinner three or more hours before sleep supports digestion and sleep quality. Modern research on early time-restricted eating aligns with this recommendation.
  • Consistent bedtime: Going to bed at a similar time each night supports circadian rhythm. Traditional recommendations of bedtime before ten in the evening are more consistent with agricultural life than with modern schedules, but the principle of a consistent, appropriately early bedtime is well-supported.
  • Screen limits in the evening: Not a traditional Ayurvedic practice per se, but consistent with the tradition’s emphasis on quieting activity in the evening. Modern evidence supports evening screen reduction for sleep quality.
  • How to introduce dinacharya practically: Do not attempt to install the entire traditional routine at once. Choose two or three practices that resonate most and install them for four weeks. Add another practice once the first ones feel automatic. Build the routine over months rather than weeks.

Which Ayurvedic Nutrition Principles Support Midlife?

Ayurvedic nutrition is one of the most immediately applicable areas of the tradition for midlife women. The general principles align well with modern evidence-based approaches to metabolic health while adding some specific frameworks that are worth understanding.

  • Six tastes at every meal: The tradition identifies six tastes (sweet, sour, salty, pungent, bitter, astringent) and suggests that a balanced meal includes some representation of all six. This principle roughly maps to modern dietary variety recommendations and often produces more nutritionally diverse meals than a Western diet built around a single main flavor per meal.
  • Match the food to the constitution: Different doshas benefit from different foods. Vata benefits from warm, cooked, moist, oily foods. Pitta benefits from cooling, moderately sweet, less spicy foods. Kapha benefits from lighter, warmer, drier foods with more pungent spices. Understanding your constitution helps you understand which foods support your specific pattern.
  • Eat the biggest meal at midday: The specific chrononutrition recommendation from the previous section. Digestive capacity is highest around noon, and heavier meals are better metabolized at that time than in the evening. Modern research broadly supports this.
  • Eat warm cooked food more than raw: Ayurveda generally prefers warm cooked foods over cold raw foods, particularly for vata and kapha constitutions. Modern research on food preparation is mixed. Some argument favors more cooked and less raw for improved digestion and nutrient absorption in the midlife body, particularly during periods of vata excess.
  • Eat mindfully and without distraction: The tradition emphasizes eating in a calm environment without work or screens. Modern mindful eating research supports this recommendation for improved digestion, portion regulation, and satiety recognition.
  • Include appropriate spices: Ayurvedic cooking uses spices intentionally for both flavor and physiological effect. Ginger and cumin support digestion. Turmeric has anti-inflammatory effects. Fennel supports post-meal comfort. Modern nutrition research supports many of these traditional uses.
  • Consider seasonal eating: The tradition adjusts recommendations by season. Summer favors cooling foods. Winter favors warming foods. Spring focuses on lighter foods to clear accumulated winter heaviness. This approach aligns with local, seasonal eating traditions in many parts of the world.
  • A caution on herbal supplements: Traditional Ayurvedic pharmacology involves complex herbal formulations that should not be self-prescribed based on internet reading. Some Ayurvedic herbs have documented drug interactions. Some commercial Ayurvedic supplements have been contaminated with heavy metals. Consult a qualified practitioner and your Western physician before taking any Ayurvedic herbal formulation.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How Does Ayurveda Support Sleep and the Nervous System?

The Ayurvedic approach to sleep and nervous system regulation is one of the areas where the traditional recommendations align most closely with modern evidence-based practice. This is worth understanding in detail because sleep and nervous system regulation are two of the largest levers for midlife women’s health.

  • Sleep timing: The tradition emphasizes consistent, appropriately early bedtimes. Modern circadian research strongly supports this recommendation.
  • Wind-down practices: The tradition includes specific evening practices to prepare the body for sleep: warm oil foot massage, warm milk with spices, gentle yoga, meditation, and reduced stimulation. Modern evidence supports evening parasympathetic activation practices, warm baths, and screen reduction.
  • Vata support at night: For women in perimenopause and menopause experiencing vata-driven sleep disruption, the tradition recommends specific warming and grounding practices. Modern approaches to menopause sleep support align with much of this. See our menopause sleep remedies article and midlife sleep stack article for the modern evidence-based framework.
  • Meditation and pranayama: The traditional practices of meditation and pranayama (breath work) are among the most well-supported interventions in modern research for stress reduction, cortisol regulation, and nervous system health. See our vagus nerve reset exercises article for ten specific modern practices that share ancestry with traditional pranayama.
  • Yoga: The traditional physical practice of yoga was developed alongside Ayurveda as part of the same framework. Modern research on yoga supports many of the traditional claims for mood, sleep, flexibility, and stress reduction. See our five yin yoga poses article for a specific home practice.
  • Massage and touch: Traditional oil massage (abhyanga) is understood as a nervous system regulation practice as much as a physical one. Modern research on touch therapy supports the cortisol-lowering and mood-supporting effects.
  • The framework overlap: The Ayurvedic recognition that sleep, nervous system regulation, digestion, hormonal function, and mood are a single interconnected system is one of the tradition’s most important contributions and one of the areas where modern medicine has moved closer to the traditional view over the last several decades. This overlap is where a midlife woman can most confidently draw on the tradition.

“The parts of Ayurveda that most reliably help midlife women are the parts that have always been true regardless of tradition. These practices include consistent sleep, warm cooked food eaten without distraction, daily movement matched to the season and the body, regular self-touch and self-care, reduced evening stimulation, and attention to the digestive system as a foundation of mood and hormonal health. These are the practices where the tradition and modern evidence agree, and they are the practices I can recommend without any qualification. The parts that require deeper training (specific herbal prescriptions, pulse-based constitutional assessment, panchakarma cleansing therapy) belong in the hands of qualified practitioners. Knowing where the line is between the accessible foundation and the deeper practice is what keeps this a respectful engagement with the tradition rather than a shallow appropriation of it.”

Terry Tateossian, Founder of The House of Rose

Where Do Ayurveda and Modern Medicine Overlap?

The overlap between Ayurvedic recommendations and modern evidence-based practice is more substantial than the surface differences suggest. Where these two systems agree is where the most confident practical value for midlife women shows up.

  • Daily routine and circadian rhythm: Both systems support consistent daily patterns of eating, sleeping, and moving as foundational to health.
  • Whole-food, minimally processed eating: Both systems favor whole foods, minimal processing, and appropriate variety.
  • Meal timing: Both systems favor eating the larger meal earlier in the day and a lighter meal earlier in the evening.
  • Movement: Both systems favor regular daily movement appropriate to age and constitution rather than sporadic intense exercise.
  • Meditation and breath work: Both systems recognize the health value of meditation and breath practices for stress reduction and cognitive function.
  • Nervous system regulation: Both systems recognize the interconnection between mental state, digestion, hormones, and general health.
  • Sleep as foundational: Both systems emphasize sleep as a foundation of health rather than as a lower priority.
  • Individual variability: Both systems recognize that different bodies benefit from different specific interventions, though they characterize the individual differences differently.
  • The importance of digestion: Both systems emphasize digestive health as central to overall health, though they use different specific frameworks.
  • The role of stress: Both systems recognize chronic stress as a major driver of disease.
  • Preventive care: Both systems emphasize prevention over treatment of established disease.
  • Multi-system integration: Both systems reject the reductionist single-cause single-treatment model in favor of multi-factor multi-intervention approaches.

This overlap is not incidental. It reflects the fact that both systems have observed the same human bodies over long time periods and have arrived at some of the same practical conclusions through different methods.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Where Do Ayurveda and Modern Medicine Differ?

Being honest about where Ayurveda and modern evidence-based practice diverge is as important as being clear about where they overlap. This honesty is what makes a thoughtful bridging position possible.

Ayurveda and modern medicine differences infographic
  • Herbal pharmacology: Ayurvedic herbal medicine involves complex formulations that have not been evaluated by modern pharmacological standards. Some formulations may be effective and safe, while others may not be, and some have documented drug interactions. Some commercial products have been contaminated with heavy metals. Modern evidence-based practice cannot endorse specific herbal recommendations without the safety and efficacy data that current evaluation methods require.
  • Panchakarma and cleansing therapies: Traditional cleansing protocols involve extended procedures that have not been evaluated by modern controlled research. Some elements may be beneficial. Others may be neutral or harmful. This is an area where modern medicine cannot make confident recommendations.
  • Specific dosha assessment: The pulse-based and tongue-based diagnostic methods used by trained Ayurvedic practitioners have not been validated by modern research. This does not mean they are without value, but it does mean that specific dosha assessments are not the equivalent of a laboratory diagnosis.
  • Consciousness and metaphysics: The Vedic view that consciousness is fundamental rather than emergent from brain activity is a philosophical position that modern neuroscience has not confirmed or refuted. Individuals can adopt whichever view fits their own worldview.
  • Astrology (jyotish): The traditional integration of Ayurveda with astrology is one of the areas where modern evidence-based practice cannot follow the tradition. There is no reliable evidence that planetary positions at birth affect health outcomes, and interventions based on this premise are not supported by the evidence base.
  • Specific claims about specific conditions: Some Ayurvedic claims for specific therapeutic effects of specific interventions have not been evaluated by modern research. Absence of evidence is not the same as evidence of absence, but it does mean these claims should be handled with appropriate caution.
  • The role of karma and past lives in health: Traditional Ayurveda includes concepts of karma and past-life influence that are outside the frame of modern medicine. Individuals can hold these views personally, but they cannot be integrated into evidence-based clinical practice.

The honest position is that the tradition contains some elements that modern evidence supports, some elements that modern evidence does not evaluate, and some elements that fall outside what modern science can address. All three categories are real, and being clear about which category any specific recommendation falls into is what allows a thoughtful engagement.

What Are the Most Common Misconceptions About Ayurveda?

Several common misconceptions about Ayurveda circulate in Western wellness culture and are worth naming directly.

  • Ayurveda is not a lifestyle brand: Ayurveda is a living medical tradition. The tea, the essential oils, the copper cups, and the tongue scrapers marketed as Ayurvedic products in Western stores are marketing, not medicine. Some of the products may be useful. Others are not. Distinguishing product marketing from the tradition itself matters.
  • Doshas are not personality types: The doshas are functional physiological patterns, not personality quizzes. Reducing them to Buzzfeed-quiz personality types trivializes the tradition and produces recommendations of limited practical value.
  • Ayurveda is not a religion: Ayurveda emerged from a specific cultural and philosophical context that includes religious elements, but the tradition itself is a medical system that can be studied and practiced by people of any religious background.
  • Ayurveda is not a magic bullet: The tradition is a long-term framework for maintaining balance over a lifetime, not a quick fix for specific symptoms. Approaching it as a source of miracle interventions produces disappointment.
  • Ayurveda is not the same as yoga: Yoga and Ayurveda are sister disciplines within the same broader Vedic tradition. They share some principles and often support each other, but they are distinct practices.
  • Ayurveda is not primitive: The tradition includes highly sophisticated frameworks for anatomy, physiology, diagnosis, and treatment that were developed over thousands of years by generations of educated practitioners. Dismissing it as pre-scientific misses the depth of the actual tradition.
  • Ayurveda is not always safe: Some traditional preparations contain herbs with known drug interactions or heavy metal content. The general public perception that natural means safe does not apply to Ayurvedic pharmacology, and any herbal use should involve qualified guidance.
  • Ayurveda is not a substitute for Western medicine for serious conditions: For acute medical emergencies, serious chronic diseases, mental health crises, and many other conditions, Western medicine offers evaluations and treatments that Ayurveda cannot replace. The most productive approach is complementary use of both systems where appropriate.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How Can You Explore Ayurveda Safely?

If the tradition interests you and you want to explore it in a way that respects both the tradition and your health, several principles apply.

  • Start with the lifestyle recommendations, not the pharmacy: The traditional daily routine, nutrition principles, and meditation practices are safe, accessible, and immediately useful. The herbal formulations require qualified guidance.
  • Do not self-prescribe herbs: Ayurvedic herbal preparations should be prescribed by trained practitioners after appropriate assessment, not selected from wellness websites.
  • Investigate any product carefully: If you decide to purchase Ayurvedic products, look for reputable brands with third-party testing for heavy metal content and other contaminants. Some commercial Ayurvedic supplements have been contaminated with lead, mercury, and arsenic.
  • Tell your Western physician about any Ayurvedic care you pursue: Drug and herb interactions can be significant. Your physician needs to know what you are taking.
  • Do not stop prescribed medications without professional guidance: Any decision to stop or modify Western medications requires consultation with the prescribing physician.
  • Approach the tradition with cultural humility: Ayurveda is a South Asian tradition with deep cultural roots. Engaging with it respectfully means learning from qualified practitioners from the tradition, supporting South Asian voices in the field, and not appropriating the tradition as a Western wellness brand.
  • Give it time: Ayurvedic changes work slowly. Six months of consistent daily routine will produce noticeable change. Six days will not.

What Should You Look for in an Ayurvedic Practitioner?

If you decide to pursue Ayurvedic care in the United States, the practitioner field is currently unregulated at the federal level, which means quality varies significantly.

  • Look for formal training: Legitimate Ayurvedic practitioners have completed multi-year formal training programs. In the United States, look for graduates of programs recognized by the National Ayurvedic Medical Association (NAMA). In India, look for BAMS (Bachelor of Ayurvedic Medicine and Surgery) graduates.
  • Look for professional membership: NAMA is the primary professional organization for Ayurveda in the United States. Membership is not required to practice but is a positive signal of engagement with the professional community.
  • Look for continuing education: Legitimate practitioners continue to study and update their practice.
  • Ask about intake: A qualified practitioner will conduct a thorough intake including medical history, current medications, family history, physical examination (often including pulse and tongue), and detailed conversation about lifestyle. Practitioners who prescribe from a brief conversation or an online quiz should be avoided.
  • Ask about the herbs: A qualified practitioner will use herbal formulations from suppliers with quality control processes and will be willing to explain what they are prescribing and why.
  • Ask about coordination with Western medicine: A qualified practitioner will support your continued relationship with your Western physicians and will communicate with them when appropriate.
  • Trust your judgment: If a practitioner discourages you from following your Western physician’s recommendations, discourages you from telling other providers what you are taking, or promises miraculous cures, look for someone else.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
When Should You See a Healthcare Professional?

Ayurvedic frameworks and lifestyle recommendations can complement standard medical care, but certain situations require Western medical evaluation.

  • Any acute or severe symptoms: Chest pain, shortness of breath, severe headaches, neurological symptoms, and other acute presentations require immediate medical evaluation.
  • Any persistent unexplained symptoms: Persistent unexplained fatigue, weight changes, mood changes, digestive changes, or other symptoms warrant medical workup regardless of any Ayurvedic exploration.
  • Any mental health crisis: Active suicidal ideation, severe depression, or severe anxiety require mental health care. Ayurvedic principles can complement but cannot substitute for appropriate mental health treatment.
  • Any decision about medications: Never stop prescribed medications based on Ayurvedic recommendations alone.
  • Any interest in Ayurvedic herbal treatment: Consult both a qualified Ayurvedic practitioner and your Western physician before taking any Ayurvedic herbal formulation.
  • Menopause symptoms that impair daily life: A menopause specialist can offer evaluation and evidence-based treatment options that Ayurveda alone may not fully address.
  • Pregnancy: Some Ayurvedic recommendations need modification during pregnancy. Work with practitioners familiar with prenatal care.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Frequently Asked Questions

What is Ayurveda in simple terms?

Ayurveda is a health tradition that developed in South Asia over several thousand years. It views health as balance among three functional patterns (vata, pitta, kapha) that combine differently in different people, and it prescribes daily routines, nutrition, herbal medicine, meditation, and other practices tailored to individual constitution, life stage, and season. It is a living tradition still practiced by qualified doctors worldwide.

Is Ayurveda safe for women over 40?

The lifestyle recommendations of Ayurveda (daily routine, nutrition principles, meditation, appropriate movement) are generally safe for women over 40 and often particularly well-suited to the perimenopause and menopause window. The herbal pharmacology requires qualified guidance because some Ayurvedic herbs have drug interactions and some commercial products have been contaminated with heavy metals. Consult a qualified practitioner and your Western physician before taking any Ayurvedic herbal formulation.

What is my dosha?

Determining your dosha accurately requires observation across many dimensions over time, and ideally an assessment by a trained Ayurvedic practitioner. Online dosha quizzes are usually too simplified to be reliable. Section 5 of this article gives you the dimensions to observe. If you want a professional assessment, look for a graduate of a program recognized by the National Ayurvedic Medical Association (NAMA).

Does Ayurveda help with menopause?

Ayurvedic principles align well with many of the challenges of perimenopause and menopause, particularly the vata-excess pattern that this transition often produces. The daily routine, nutrition principles, sleep support, and nervous system regulation practices are broadly supportive. Some Ayurvedic herbal formulations for menopause exist but should be evaluated with a qualified practitioner and your Western physician.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Can Ayurveda help with weight loss?

Ayurvedic principles can support the general framework for midlife weight loss (regular meals, appropriate portion sizes, digestive support, stress reduction, sleep), but Ayurveda alone is not a specific weight loss protocol. Most midlife weight loss for women requires the combined framework of adequate protein, appropriate calorie balance, strength training, sleep, and nervous system regulation covered in our broader THOR content.

Is Ayurvedic medicine evidence-based?

Some elements of Ayurveda have been evaluated in modern research and have supporting evidence (daily routine, meditation, some yoga applications, some herbal interventions). Other elements have not been evaluated. Some traditional practices fall outside what modern research can address. The most productive framing is that Ayurveda contains a mix of empirically supported, empirically untested, and philosophically-grounded elements, and thoughtful engagement means understanding which category any specific recommendation falls into.

What is dinacharya?

Dinacharya is the traditional Ayurvedic daily routine. Elements include consistent wake time, morning hygiene practices, oil self-massage, movement, meditation, meal timing, and consistent bedtime. Many elements have strong overlap with modern evidence-based recommendations for circadian rhythm, stress reduction, and metabolic health. Section 7 of this article covers the practices in detail.

Do I need to see an Ayurvedic practitioner?

For general lifestyle recommendations (daily routine, nutrition principles, meditation, appropriate movement), you can begin exploring on your own with reliable sources. For deeper personalized guidance including any herbal treatment, working with a qualified practitioner is important. Look for graduates of NAMA-recognized programs in the United States or BAMS graduates from India.

Are Ayurvedic supplements safe?

Some Ayurvedic supplements are safe and effective. Others have been contaminated with heavy metals in independent testing. Some interact with common medications. Any Ayurvedic supplement should be from a reputable brand with third-party testing, should be used under qualified guidance, and should be disclosed to your Western physician.

Is Ayurveda the same as yoga?

No, Ayurveda and yoga are related but distinct disciplines within the broader Vedic tradition. Yoga is primarily a system of physical, mental, and spiritual practice for personal development. Ayurveda is a system of medicine. They share underlying assumptions and often support each other, but they are not the same.

Can Ayurveda replace Western medicine?

For acute medical emergencies, serious chronic diseases, mental health crises, and many other conditions, Western medicine offers evaluations and treatments that Ayurveda cannot replace. Ayurveda is best understood as a complementary framework that can enhance overall health alongside appropriate Western medical care.

What is a good beginner book on Ayurveda?

Ayurveda: The Science of Self-Healing by Vasant Lad is a widely respected accessible introduction. The Complete Book of Ayurvedic Home Remedies by Vasant Lad is a practical starting resource. David Frawley’s books offer another accessible entry point. Books by qualified practitioners from the tradition itself are preferable to books by Western wellness writers who have adapted the material.

Does Ayurveda have anything to say about hormones?

Ayurveda addresses hormone-mediated conditions extensively, though it uses different terminology than modern endocrinology. The framework describes many of the same patterns Western medicine describes and prescribes different interventions. For hormone-specific concerns, work with both a qualified Ayurvedic practitioner and a Western physician or menopause specialist.

How long before Ayurvedic practices show results?

Ayurvedic changes work slowly. Some daily routine practices produce noticeable subjective changes within days (better sleep, easier digestion). Deeper constitutional rebalancing typically takes months of consistent practice. This is a long-term framework rather than a short-term intervention.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Is Ayurveda appropriate during pregnancy?

Some Ayurvedic practices are supportive during pregnancy and some need modification. Work with practitioners familiar with prenatal care. Herbal formulations should generally not be self-prescribed during pregnancy. Consult both a qualified Ayurvedic practitioner and your prenatal provider.

What is panchakarma?

Panchakarma is a traditional Ayurvedic cleansing and rejuvenation protocol involving specific therapies over a period of days to weeks. It is not something to attempt independently. If you are interested, seek a qualified practitioner and be aware that the specific safety and efficacy data supporting panchakarma is limited in modern research terms.

References

  • Lad, V. (2002). Textbook of Ayurveda: Fundamental Principles (Vol. 1). The Ayurvedic Press.
  • Lad, V. (1985). Ayurveda: The Science of Self-Healing. Lotus Press.
  • Frawley, D. (2000). Ayurvedic Healing: A Comprehensive Guide (2nd ed.). Lotus Press.
  • Frawley, D. (1997). Ayurveda and the Mind: The Healing of Consciousness. Lotus Press.
  • Svoboda, R. E. (1998). Prakriti: Your Ayurvedic Constitution (2nd ed.). Lotus Press.
  • Sharma, P. V. (Trans.). (1994). Charaka Samhita (Vols. 1–4). Chaukhambha Orientalia.
  • Bhishagratna, K. K. (Trans.). (2005). Sushruta Samhita. Chaukhambha Sanskrit Series.
  • Chopra, D., & Simon, D. (2000). The Chopra Center Herbal Handbook. Three Rivers Press.
  • Ranade, S., Deshpande, R. R., & Chobhe, S. (2011). Ayurveda and Marma Therapy: Energy Points in Yogic Healing. North Atlantic Books.
  • Patwardhan, B., Warude, D., Pushpangadan, P., & Bhatt, N. (2005). Ayurveda and traditional Chinese medicine: a comparative overview. Evidence-Based Complementary and Alternative Medicine, 2(4), 465–473.
  • Chopra, A., Saluja, M., Tillu, G., et al. (2013). Ayurvedic medicine offers a good alternative to glucosamine and celecoxib in the treatment of symptomatic knee osteoarthritis: a randomized, double-blind, controlled equivalence drug trial. Rheumatology, 52(8), 1408–1417.
  • Furst, D. E., Venkatraman, M. M., McGann, M., et al. (2011). Double-blind, randomized, controlled, pilot study comparing classic ayurvedic medicine, methotrexate, and their combination in rheumatoid arthritis. Journal of Clinical Rheumatology, 17(4), 185–192.
  • Saper, R. B., Phillips, R. S., Sehgal, A., et al. (2008). Lead, mercury, and arsenic in US- and Indian-manufactured Ayurvedic medicines sold via the Internet. JAMA, 300(8), 915–923.
  • National Center for Complementary and Integrative Health. (2023). Ayurvedic medicine: in depth. National Institutes of Health.
  • Sharma, H., Chandola, H. M., Singh, G., & Basisht, G. (2007). Utilization of Ayurveda in health care: an approach for prevention, health promotion, and treatment of disease. Part 1—Ayurveda, the science of life. Journal of Alternative and Complementary Medicine, 13(9), 1011–1019.
  • Sharma, H., Chandola, H. M., Singh, G., & Basisht, G. (2007). Utilization of Ayurveda in health care: an approach for prevention, health promotion, and treatment of disease. Part 2—Ayurveda in primary health care. Journal of Alternative and Complementary Medicine, 13(10), 1135–1150.
  • Wallace, R. K. (2020). Ayurgenomics and modern medicine. Medicina, 56(12), 661.
  • Payyappallimana, U., & Venkatasubramanian, P. (2016). Exploring Ayurvedic knowledge on food and health for providing innovative solutions to contemporary healthcare. Frontiers in Public Health, 4, 57.
  • Sarris, J., de Manincor, M., Hargraves, F., & Tsonis, J. (2019). Harnessing the four elements for mental health. Frontiers in Psychiatry, 10, 256.
  • Streeter, C. C., Gerbarg, P. L., Saper, R. B., et al. (2012). Effects of yoga on the autonomic nervous system, gamma-aminobutyric-acid, and allostasis in epilepsy, depression, and post-traumatic stress disorder. Medical Hypotheses, 78(5), 571–579.
  • National Ayurvedic Medical Association. (n.d.). NAMA scope of practice and code of ethics. Retrieved from ayurvedanama.org.

Additional Resources: For further information on qualified Ayurvedic practitioners in the United States, see the National Ayurvedic Medical Association (NAMA) at ayurvedanama.org. For information on evidence-based evaluation of complementary and integrative health practices, see the National Center for Complementary and Integrative Health at nccih.nih.gov.

Disclaimer: Always consult with a qualified healthcare professional before making any decisions about your health, particularly if you are considering herbal supplements, treatments, or lifestyle changes for specific health conditions. This article is educational and does not constitute medical advice, treatment recommendation, or endorsement of Ayurvedic care for any specific condition. THOR is not an Ayurvedic clinic and does not provide Ayurvedic services.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
5 Fascia Release Exercises for Weight Loss and Belly Fat in Midlife Women (Plus a 5-Day Program With Videos)

Fascia release exercises do not directly burn fat, despite what many articles claim. Their real value is supporting the conditions that make weight loss easier, especially during midlife.

Fascia work may help reduce physical tension, improve breathing, support lymphatic flow, encourage nervous system regulation, and make everyday movement feel more comfortable. Over time, these benefits can support the nutrition, strength training, and lifestyle habits that drive meaningful changes in weight and body composition.

I am Terry Tateossian, founder of The House of Rose and a certified lifestyle medicine coach. After experiencing early-onset menopause at 41 and an 80-pound change in my body composition, I made body-based practices, including fascia release, part of my recovery and the framework I now teach at our nutrition-focused wellness retreats.

The five exercises below were selected for their fascia benefits and their ability to support the midlife body. The included 5-day program combines them into a practical routine that takes about 10 to 20 minutes per day, with video placement notes to support clear demonstrations.

Important: Speak with your healthcare provider before beginning a new movement program, especially if you have a history of abdominal surgery, hernia, pregnancy, pelvic organ prolapse, hiatal hernia, or an acute abdominal condition.

What Is Fascia?

Fascia is the connective tissue network that runs throughout the entire body. It surrounds every muscle, wraps every organ, envelops every nerve and blood vessel, and forms continuous sheets that link every body region to every other body region. Understanding what fascia actually is helps make sense of what fascia release can and cannot do.

Fascia network and fascial lines infographic
  • Its physical form: Fascia is a web of collagen and elastin fibers embedded in a fluid ground substance. Healthy fascia is pliable, hydrated, and glides smoothly against itself and against the tissues it surrounds. Restricted fascia becomes stiff, dehydrated, and stuck to itself and to adjacent tissues.
  • Its architectural role: Fascia is not just a passive wrapping. It transmits force through the body, contributes to posture, participates in movement, and communicates mechanical information from one region of the body to another. When you feel tension in a shoulder that is actually driven by a restriction in the opposite hip, fascia is often the transmission line.
  • The fascial lines: Anatomists have mapped several continuous fascial lines that run through the body from one region to another. The superficial front line runs from the top of the foot to the side of the skull. The superficial back line runs from the sole of the foot to the top of the head. The lateral line runs along the side of the body from the ankle to the ear. The deep front line runs through the deep core, the pelvic floor, the inner leg, and up through the neck.
  • Its metabolic activity: Fascia is not metabolically inert. It contains cells that respond to mechanical stress, communicate with the nervous system, and participate in the inflammatory and immune systems. Chronically restricted fascia is often chronically inflamed, and chronic inflammation has direct effects on hormonal function, insulin sensitivity, and body composition.
  • Its lymphatic relationship: The lymphatic system is deeply integrated with fascial tissues. Lymph flows through fascial spaces and depends on movement and pressure to circulate. Restricted fascia often means restricted lymphatic flow, and restricted lymphatic flow contributes to the sluggish, puffy, inflammation-driven state that many midlife women recognize.
  • Its nervous system relationship: Fascia is densely innervated by sensory nerves. Restricted fascia sends different signals to the brain than healthy fascia, contributing to the felt-sense of chronic tension, poor body awareness, and reduced ease of movement. See our earlier articles on the fascia and lymphatic system connection and the lymphatic reset and fascia connection for deeper dives into these mechanisms.

Why Is Midlife Belly Fat Different From Other Belly Fat?

Midlife belly fat is not just the same body fat that showed up in your twenties. The physiology, the drivers, and the treatment approach are meaningfully different, and understanding the difference is what makes the fascia release intervention make sense.

  • The hormonal shift: As estrogen declines through perimenopause and menopause, body fat begins to redistribute from the hips and thighs toward the abdomen. This is not a lifestyle failure. It is a specific biological response to changing hormone ratios that happens to almost every woman in this window.
  • The visceral fat problem: The abdominal fat that accumulates in midlife is often visceral fat, meaning it sits deep in the abdomen around the organs rather than just under the skin. Visceral fat is metabolically active in a way that subcutaneous fat is not. It produces inflammatory signals, disrupts hormone balance, worsens insulin sensitivity, and reinforces its own accumulation.
  • The cortisol connection: Chronic cortisol elevation drives visceral fat storage specifically. The stress of midlife life, combined with sleep disruption, undereating from restrictive dieting, and often the anxiety of watching body composition change, keeps cortisol elevated in a pattern that feeds the belly fat cycle.
  • The insulin resistance shift: Perimenopause and menopause often produce measurable declines in insulin sensitivity. Reduced insulin sensitivity makes the body more likely to store carbohydrate calories as fat and specifically as belly fat.
  • The inflammatory state: The combination of visceral fat, disrupted sleep, chronic stress, and often reduced anti-inflammatory food intake produces a low-grade inflammatory state that promotes further weight gain and makes weight loss harder.
  • The muscle loss compounding: Sarcopenia in midlife reduces resting metabolic rate, which means the same food intake produces more fat storage than it would have a decade earlier. See our four muscle groups for aging well article for the strength training foundation that addresses this piece.
  • The sleep disruption compounding: Poor sleep raises cortisol, worsens insulin sensitivity, elevates hunger hormones, reduces prefrontal control, and increases cravings for calorie-dense foods, all of which feed into the belly fat pattern.
  • The fascial contribution: Chronic restriction of the abdominal fascia, the diaphragm fascia, and the fascial connections through the deep core contributes to reduced breath depth, restricted lymphatic flow in the abdomen, elevated sympathetic tone, and a physical sense of holding that layers on top of every other driver.

This last piece is where fascia release earns its place in the picture. It does not directly burn belly fat. It addresses the physical drivers that make the other drivers harder to correct.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Does Fascia Release Support Weight Loss?

The specific mechanisms by which fascia release supports midlife weight loss and belly fat reduction are worth understanding clearly because the mechanisms are the reason the intervention works, and understanding them helps you use the intervention correctly.

How fascia release supports weight loss
  • Cortisol reduction: Fascia release, particularly when combined with slow breath, produces measurable reductions in cortisol through parasympathetic nervous system activation. Lower cortisol reduces the biological signal that drives visceral fat storage. This is the largest single mechanism.
  • Improved breath depth: The fascial restrictions around the diaphragm, ribcage, and abdominal wall directly restrict the depth of the inhale. Fascia release in these regions consistently produces improvements in breath depth within days. Deeper breath activates vagal tone, reduces cortisol, and improves oxygen delivery to metabolically active tissues.
  • Lymphatic drainage: The lymphatic system does not have a heart. It depends on movement, breath, and the mechanical squeeze of surrounding tissues to circulate. Restricted fascia impairs this circulation. Fascia release, particularly in the abdominal region and the deep hip, supports lymphatic drainage that reduces the puffiness and inflammation that contribute to the felt-sense of belly fat.
  • Reduced systemic inflammation: Chronically restricted fascia is chronically inflamed. Restoring fascial mobility reduces the local inflammation and, over weeks, contributes to lower systemic inflammatory markers.
  • Improved movement capacity: When the psoas is chronically restricted, walking is harder. When the thoracic spine is chronically restricted, breathing during exercise is harder. When the abdominal fascia is chronically restricted, core engagement during strength training is harder. Fascia release removes friction from all of these movement patterns, which increases the likelihood that you will actually do the movement work that produces the fat loss.
  • Restoration of body agency: The felt-sense of a released body is dramatically different from the felt-sense of a chronically braced body. This subjective shift often produces psychological changes that support the sustained behavior change required for meaningful weight loss.
  • Support of sleep quality: The parasympathetic activation from evening fascia release practice supports the sleep quality that is essential for weight loss in midlife. Poor sleep is one of the largest single obstacles to midlife weight loss, and anything that supports sleep supports weight loss.
  • No direct fat burning: None of the above is fat burning. All of it is metabolic support that makes the actual fat loss interventions more effective. This distinction matters because it prevents disappointment when fascia release alone does not produce weight loss and it prevents overselling of the specific mechanism.

“The honest positioning of fascia release for midlife weight loss is that it removes several specific obstacles that keep the primary interventions (nutrition, strength training, sleep, nervous system regulation) from working as well as they should. When I coach a midlife woman who is doing all the right things nutritionally and still not seeing results, one of the first things I look at is whether her cortisol pattern, her breath depth, and her lymphatic flow are creating an internal environment that resists fat loss no matter what she eats. Fascia release is often the specific intervention that shifts that internal environment. Within four to six weeks of daily practice combined with the nutrition foundation, most women start seeing the movement of the scale, the tape measure, or the way clothes fit that had been stuck for months. It is not the fascia work that burned the fat. It is the fascia work that allowed the rest of the picture to actually produce results.”

Terry Tateossian, Founder of The House of Rose

What Does Fascia Release Not Do?

Being explicit about what fascia release does not do is as important as being clear about what it does do. This section prevents the disappointment and cynicism that come from overselling.

  • It does not burn fat directly: No exercise in this article, and no fascia release exercise anywhere, produces meaningful fat loss purely through fascial mechanisms. Fat loss requires an energy deficit, produced by some combination of dietary changes and increased activity.
  • It does not replace nutrition: The largest single lever for midlife body composition change is dietary intake, particularly adequate protein and appropriate calorie balance. The free Macro Calculator is where the nutrition foundation starts.
  • It does not replace strength training: Preserving and building lean muscle mass is the second largest lever. The four muscle groups for aging well article covers the strength training foundation.
  • It does not replace sleep: Sleep is the third largest lever. The midlife sleep stack article and menopause sleep remedies article cover the sleep interventions.
  • It does not spot-reduce belly fat: Belly fat is lost through overall body fat reduction. You cannot burn belly fat specifically by working on the belly. What abdominal fascia release does is support the systemic changes that produce overall fat loss.
  • It does not work in a week: Meaningful body composition changes take weeks to months. Fascia release supports those changes but does not accelerate them beyond what the underlying interventions can produce.
  • It does not substitute for medical evaluation of persistent weight issues: Thyroid dysfunction, PCOS, medication effects, and other medical conditions can drive weight patterns that lifestyle interventions alone will not resolve. Persistent unexplained weight changes warrant medical evaluation.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Does the Research Actually Show?

The research on fascia release for weight loss specifically is limited because the direct claim is not well-supported. What has been studied is the effect of fascia release on the intermediate mechanisms (cortisol, breath, lymphatic flow, inflammation, sleep, movement capacity) that in turn influence weight and body composition.

  • Fascia release and cortisol:Multiple studies of self-myofascial release and manual myofascial therapy have documented reductions in cortisol within a single session and over weeks of regular practice. The effect size is meaningful when combined with slow breath.
  • Fascia release and breath: Research on thoracic mobility work, foam roller thoracic extension, and diaphragmatic release has consistently documented improvements in breath depth, respiratory function, and vagal tone.
  • Fascia release and lymphatic flow:The research on manual lymphatic drainage, abdominal self-massage, and specific fascia work in the abdominal region has documented improvements in lymphatic circulation and reductions in the puffy, inflamed state associated with fluid stasis.
  • Fascia release and inflammation:Regular self-myofascial release has been associated with reductions in inflammatory markers in some studies, though the research is smaller than for the other mechanisms.
  • Fascia release and sleep: Evening-timed fascia release practice combined with slow breath has been documented to improve sleep quality and duration in multiple small studies.
  • Fascia release and movement performance: The strongest research base for fascia release specifically is in movement performance. Self-myofascial release before or after training consistently improves range of motion, reduces perceived soreness, and supports subsequent training performance.
  • The indirect weight loss argument: All of the above effects are documented. The direct effect on body composition of fascia release alone is not documented, and would not be expected based on the mechanism. The argument for fascia release as a weight loss support is the indirect argument: it addresses each of the intermediate factors that make midlife weight loss harder.

The overall picture supports fascia release as a legitimate supportive layer within a broader midlife weight loss framework, with realistic expectations set correctly.

What Should You Know Before Starting Fascia Release?

Several principles apply to all five exercises in this article and are worth internalizing before beginning.

  • Breath is essential: Every fascia release exercise is significantly more effective when combined with slow diaphragmatic breathing. Extended exhalation amplifies the parasympathetic effect and enhances the release.
  • Slow is the direction: Fascia responds to sustained gentle pressure and slow movement. Fast or forceful work is less effective and more likely to produce muscle guarding.
  • Comfort matters: Use props (folded blankets, small pillows, cushions) generously. If a position produces sharp pain, modify or skip it.
  • Consistency beats intensity: Ten to fifteen minutes a day for four weeks produces more benefit than an hour once a week.
  • Never work into sharp pain: Discomfort at a stretch is normal. Sharp pain, radiating pain, or pain in unrelated regions is a signal to stop and reassess.
  • Hydration matters: Well-hydrated fascia releases more readily than dehydrated fascia. Drink water throughout the day, particularly on practice days.
  • Equipment needed: A therapy ball or tennis ball, a foam roller, a yoga mat or comfortable surface, and a wall or countertop for support. Total investment approximately $30 to $50 for everything.
  • Time of day: Fascia release can be practiced any time. Morning practice supports the day. Evening practice supports sleep. Middle-of-the-day practice interrupts accumulated tension.
  • What to expect subjectively: Some releases feel immediate and satisfying, while others feel subtle or produce nothing observable during the session and only produce felt-sense changes hours or days later. Some produce emotional release. All of these responses are normal. Track how you feel over the week rather than expecting a specific response from each session.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
What Are the 5 Best Fascia Release Exercises for Weight Loss and Belly Fat?

These five fascia release exercises target common areas of fascia tightness in the abdomen, upper back, hips, side body, and front of the body. When practiced with slow breathing and gentle pressure, they can support better mobility, deeper breathing, lymphatic flow, posture, and nervous system relaxation. Follow the instructions carefully, use the suggested modifications when needed, and avoid forcing any movement or applying painful pressure.

Five fascia release exercises for mobility and relaxation

Exercise 1: Abdominal Fascia Release With a Ball

Abdominal fascia release is the most directly targeted exercise for the belly fat and midlife belly picture. It addresses the fascial restrictions in the abdominal wall, supports lymphatic drainage in the abdomen, and produces the parasympathetic activation that reduces cortisol.

This gentle abdominal release exercise helps relax tight tissue around the belly and improve comfort through slow, controlled pressure. Start with a softer ball and keep the pressure light, especially if you are new to this technique.

  1. Choose a therapy ball, tennis ball, or lacrosse ball. Beginners should use a softer ball, while a rolled-up towel can be used if a ball feels too intense.
  2. Lie face down on a comfortable, supportive surface.
  3. Place the ball about two inches to the right of your belly button, level with it or slightly above.
  4. Slowly lower your body onto the ball while supporting most of your weight with your forearms. Apply only gentle, comfortable pressure.
  5. Take slow, deep breaths into your belly for 60 to 90 seconds.
  6. Lift your body off the ball slowly and carefully.
  7. Move the ball slightly farther to the side, higher, or lower, then repeat the process.
  8. Cover four to six positions on the right side of your abdomen.
  9. Repeat the same steps on the left side.

This gentle abdominal release uses light, sustained pressure and slow breathing to ease fascial tension, support deeper breathing, and promote relaxation. Before beginning, review the safety guidance, proper technique, expected sensations, and common mistakes to ensure the practice remains comfortable and controlled.

  • Safety note: This exercise applies gentle pressure to the abdominal region. Skip this exercise entirely if you are pregnant, have a hernia, have had recent abdominal surgery, have a known abdominal aortic aneurysm, have active abdominal pain, or have any acute abdominal condition. Discuss with your provider if you have any concern.
  • How it works: Gentle sustained pressure on the abdominal fascia produces a release response through the myofascial system and the local nervous system. The prone or side-lying position uses body weight to provide the pressure without requiring active work. Combined with slow diaphragmatic breathing, the effect on cortisol and lymphatic flow is amplified.
  • Sets and reps: 4 to 6 positions per side. Total time approximately 8 to 12 minutes.
  • Common mistakes: Using too hard a ball, applying too much pressure, holding the breath, placing the ball directly on the belly button (which puts pressure on the aorta) or too close to the ribcage (which can be uncomfortable). Never apply significant weight to the ball. Gentle is the direction.
  • Why this exercise for midlife women: This exercise directly addresses the abdominal fascial restrictions that contribute to reduced breath depth, restricted lymphatic drainage, and chronic sympathetic activation. Many midlife women report a distinct softening in the belly and a felt-sense of lightness after regular practice.
  • What is normal: Some borborygmus (belly rumbling) during the practice is common and often indicates improved circulation and vagal activation. Some mild emotional response (a wave of feeling, a spontaneous sigh, brief tearfulness) is also common and generally passes quickly.

Exercise 2: Foam Roller Thoracic Extension

Foam roller thoracic extension is one of the most impactful single exercises for the midlife body. It addresses the chronic upper back rounding that limits breath depth, supports the diaphragm, and opens the ribcage in ways that directly support the parasympathetic and lymphatic effects.

This gentle foam roller exercise helps improve mobility through the mid and upper back while encouraging fuller ribcage expansion. Move slowly, keep the pressure comfortable, and avoid forcing the spine into a deeper arch.

  1. Place a foam roller horizontally on a yoga mat or another comfortable surface. Softer rollers are better for beginners.
  2. Sit on the floor with the roller positioned behind you.
  3. Slowly lie back so the roller rests across your mid-back, around bra-strap level.
  4. Bend your knees and place both feet flat on the floor.
  5. Support your head with your hands, keeping your elbows open to the sides.
  6. Take a slow breath in and gently allow your upper back to arch over the roller. Focus on feeling your ribcage expand.
  7. Exhale slowly and return your spine to a neutral position.
  8. Repeat the movement for 8 to 10 slow breaths.
  9. Slide your body slightly so the roller rests a few inches higher or lower along the thoracic spine.
  10. Repeat 8 to 10 breaths at each of three different positions.

This gentle foam roller exercise helps open the mid-back, improve posture, and create more space for deeper breathing. Below, you’ll learn how it works, how often to perform it, common mistakes to avoid, and ways to modify or progress the movement.

  • How it works: The foam roller placed horizontally across the mid-back allows the thoracic spine to extend gently over it. This releases the chronic upper-back rounding that decades of desk work produce and creates room for the ribs to expand and the diaphragm to move fully.
  • Sets and reps: 3 positions with 8 to 10 breaths at each. Total time approximately 5 to 8 minutes.
  • Common mistakes: Placing the roller on the lower back (which is not the target and can be uncomfortable), forcing the extension aggressively, holding the breath, letting the neck strain from unsupported weight.
  • Why this exercise for midlife women: The upper back rounding that develops from years of desk work and increasingly common phone use directly restricts the breath and contributes to the chronic sympathetic state that feeds the midlife weight pattern. This exercise addresses that restriction more effectively than almost any other single intervention.
  • Modification for beginners: Start with a softer roller. Reduce the depth of the extension. Support the head fully with the hands to reduce neck strain.
  • Progression: Extend the arms overhead during the extension for an additional stretch through the shoulders and front line.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Exercise 3: Deep Squat With Spinal Wave

The deep squat, sometimes called Malasana in the yogic tradition, addresses the deep pelvic fascia and the posterior chain simultaneously. The added spinal wave introduces a dynamic release that opens the fascial layers between the hips and the shoulders.

This deep squat exercise helps open the hips, improve lower-body mobility, and gently release tension through the spine. Slow breathing and controlled spinal waves make the movement more comfortable and effective.

  1. Stand with your feet slightly wider than hip-width apart and turn your toes slightly outward.
  2. Place a folded blanket or yoga block under your heels if they do not comfortably reach the floor in a deep squat.
  3. Slowly lower your hips into a deep squat, going only as low as feels comfortable.
  4. Bring your palms together at your chest and use your elbows to gently press your knees wider.
  5. Hold the position and breathe slowly for 30 seconds.
  6. On an inhale, gently arch your lower back and lift your chest.
  7. On an exhale, round your lower back and allow your chest to drop slightly.
  8. Continue moving slowly through 5 to 8 complete spinal waves.
  9. Rest in the deep squat for another 30 seconds while breathing steadily.
  10. Press through your feet and slowly return to standing.

The deep squat with a slow spinal wave helps open the hips, release tight fascia, and improve mobility through the pelvis and torso. The guidance below explains how the movement works, how often to perform it, common mistakes to avoid, and safe modifications for tight hips or knee concerns.

  • How it works: The deep squat position places the pelvis at its lowest habitual position, opens the deep hip fascia, and creates space for the pelvic lymphatic system. Adding a slow spinal wave (rounding and arching the spine while in the squat) mobilizes the fascial connections along the entire back and front of the torso.
  • Sets and reps: 2 to 3 rounds. Total time approximately 5 to 7 minutes.
  • Common mistakes: Forcing the depth of the squat beyond what is comfortable, letting the knees collapse inward, forgetting the breath timing on the spinal wave, coming up too quickly.
  • Why this exercise for midlife women: Deep squat opens the pelvic fascia, supports lymphatic drainage through the deep hip, and restores mobility that decades of chair-based sitting have taken away. Many midlife women cannot access a deep squat at all initially. Progress here is often rapid and produces meaningful subjective benefit.
  • Modification for tight hips: Support with a wall or countertop for balance, place folded blankets under the heels, and reduce the depth of the squat while holding for shorter periods. Progress over the following weeks as flexibility improves.
  • Modification for knee issues: Anyone with significant knee issues should skip the deep squat and substitute a supported low seat on a low bench or chair with the hips lower than the knees.

Exercise 4: Standing Lateral Line Sweep With Reach

The lateral line runs along the side of the body from the ankle to the ear. It gets chronically shortened by prolonged sitting, one-sided carrying patterns, and the general slumping posture that develops in midlife. This exercise addresses the entire line in one flowing movement.

This standing side stretch lengthens the outer line of the body from the feet to the fingertips. Slow breathing and gentle rotation help release tension through the waist, ribs, hips, and shoulders.

  1. Stand with your feet slightly wider than hip-width apart, keeping them parallel or turned slightly inward.
  2. Reach your right arm straight overhead while keeping your shoulders relaxed.
  3. Exhale slowly and gently bend to the left, reaching your right arm up and over toward the left side.
  4. Feel the stretch along the right side of your body, from the outer edge of your right foot to your right fingertips.
  5. Hold the position for 20 to 30 seconds while breathing slowly and evenly.
  6. Add a small rotation forward and backward to stretch different areas along the side of the body.
  7. Slowly return to the starting position.
  8. Repeat on the opposite side, reaching your left arm overhead and bending gently to the right.

This side-bending movement combines a long reach with gentle rotation to release tension along the outer body, from the foot and hip to the ribs, shoulder, and arm. Practicing it regularly can improve ribcage mobility, deepen the breath, and create a greater sense of space and length through the side body.

  • How it works: The combined side-bend and reach lengthens the lateral fascial line from the outer foot up through the outer hip, the ribs, the shoulder, and the arm. Adding gentle rotation into the reach amplifies the release through the spiral fascial connections.
  • Sets and reps: 2 to 3 rounds per side. Total time approximately 4 to 6 minutes.
  • Common mistakes: Bending forward instead of laterally (which stretches the wrong tissues), letting the hips shift toward the side you are bending away from, holding the breath, rushing the movement.
  • Why this exercise for midlife women: The lateral line restriction that develops from prolonged sitting contributes to reduced ribcage expansion, restricted breath, and the compressed chest and belly pattern that many midlife women recognize. Regular practice produces improvements in breath depth and a felt-sense of length through the side body.
  • Progression: Add a slight side bend at the knee of the standing leg for additional depth. Practice on a stability challenge (soft foam pad) for additional demand.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Exercise 5: Standing Wall Front Line Stretch

The front fascial line runs from the top of the foot up through the front of the leg, the belly, the chest, and up through the front of the neck. It gets chronically shortened by sitting, phone use, and general forward-leaning postures. This exercise addresses the entire front line and closes the sequence with an opening rather than a compression, which supports the parasympathetic finish.

This gentle wall stretch opens the front of the body while encouraging better posture and deeper breathing. Move slowly and keep the stretch comfortable from your feet through your chest and arms.

  1. Stand facing a wall with your feet hip-width apart, parallel, and about one foot away from the wall.
  2. Place both palms flat against the wall at shoulder height with your arms extended.
  3. Slowly walk your hands upward until your arms are fully extended overhead and your palms remain flat against the wall.
  4. Step your feet slightly farther back so your body forms a gentle diagonal line from your ankles to your fingertips.
  5. Allow the front of your body to lengthen, feeling the stretch through the tops of your feet, belly, chest, shoulders, and arms.
  6. Hold the position for 30 to 45 seconds while breathing slowly and evenly.
  7. Slowly walk your hands back down the wall and return to an upright standing position.

This full-body stretch lengthens the front fascial chain while encouraging deeper, more relaxed breathing. It includes guidance on proper form, recommended rounds, common mistakes, benefits for midlife women, and an easier arm position for those with shoulder discomfort.

  • How it works: With the arms extended overhead against a wall and the body leaning slightly forward, the front fascial chain from foot to fingertip lengthens along its entire path. Combined with slow breath, the stretch produces both fascial release and parasympathetic activation.
  • Sets and reps: 2 to 3 rounds. Total time approximately 3 to 5 minutes.
  • Common mistakes: Overarching the low back (which shifts the stretch to the wrong tissues), holding tension in the shoulders, holding the breath, standing too close to the wall.
  • Why this exercise for midlife women: The front line shortening that develops from years of forward-leaning posture is one of the most common invisible drivers of restricted breath, poor digestion, and the compressed felt-sense that many midlife women recognize. This exercise opens the front line in a way that supports both breath and digestive function.
  • Modification for shoulder issues: Keep the arms lower on the wall if fully extended overhead is uncomfortable. Even a lower arm position produces meaningful front line stretch.

How Does the 5-Day Progressive Fascia Release Program Work?

The five exercises above form the core of the practice. The 5-day program combines them into a structured progressive sequence designed to introduce the practice comfortably and produce meaningful benefit within one week. Total time commitment per day ranges from 8 to 20 minutes.

5-day progressive fascia release exercise plan.

Day 1: Foundation (10 minutes)

The first day establishes the foundation with two accessible exercises.

Exercise

Duration

Warm-up (walk in place, gentle hip circles)

2 min

Foam Roller Thoracic Extension

5 min

Standing Wall Front Line Stretch

3 min

Day 1 introduces the breath and posture components without the more intense targeted work.

Day 2: Add Lateral Line (12 minutes)

The second day adds the standing lateral line release.

Exercise

Duration

Warm-up

2 min

Foam Roller Thoracic Extension

5 min

Standing Lateral Line Sweep with Reach

4 min

Standing Wall Front Line Stretch

3 min

Day 3: Add Deep Squat (15 minutes)

The third day adds the deep squat for pelvic and posterior chain release.

Exercise

Duration

Warm-up

2 min

Foam Roller Thoracic Extension

5 min

Deep Squat with Spinal Wave

5 min

Standing Lateral Line Sweep with Reach

3 min

Standing Wall Front Line Stretch

2 min

Day 4: Add Abdominal Release (18 minutes)

The fourth day adds the targeted abdominal fascia work.

Exercise

Duration

Warm-up

2 min

Foam Roller Thoracic Extension

4 min

Abdominal Fascia Release with Ball

8 min

Deep Squat with Spinal Wave

3 min

Standing Wall Front Line Stretch

2 min

Day 5: Full Sequence (20 minutes)

The fifth day integrates all five exercises into the complete sequence.

Exercise

Duration

Warm-up

2 min

Foam Roller Thoracic Extension

4 min

Abdominal Fascia Release with Ball

6 min

Deep Squat with Spinal Wave

4 min

Standing Lateral Line Sweep with Reach

2 min

Standing Wall Front Line Stretch

2 min

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
What Should You Do After the 5-Day Program?

The first five days establish the pattern. From day six forward, the most effective practice is a daily session of 15 to 20 minutes, five or six days per week, cycling through the exercises with slight variation. Once a week, repeat the full Day 5 sequence for a deeper integration. The maintenance practice pairs well with any strength training or cardio program, either as a warm-up, a cool-down, or a separate short session.

Subjective release and easier breath is often noticeable within the first two or three sessions. Improved sleep, reduced puffiness, and better body composition response to nutrition efforts generally appear within three to six weeks of consistent daily practice combined with the nutrition foundation. Structural changes in fascial mobility develop over three to six months.

“The women who see the biggest changes from this program are always the ones who combine it with the nutrition foundation and adequate sleep. On its own, fascia release produces a felt-sense change that is meaningful but that does not move the scale much. Combined with 30 grams of protein at breakfast, consistent sleep, and appropriate strength training, the fascia work becomes the specific piece that allows the rest of the picture to actually work. That is the honest answer to the fascia-and-weight-loss question. It is a combination effect. Everything works better together than any single piece works alone.”

Terry Tateossian, Founder of The House of Rose

What Should You Combine With Fascia Release?

Fascia release produces its best weight loss support when combined with the other elements of a midlife-appropriate framework. The combination effect is real and worth understanding.

  • Combine with adequate protein: Protein at every meal, roughly 25 to 40 grams per meal for most midlife women, is the foundation. The free Macro Calculator provides a personalized starting point. The Macro Miracle Mediterranean Cookbook is the kitchen-side companion.
  • Combine with strength training: Two to three strength training sessions per week targeting the four major muscle groups (quadriceps, glutes, core, grip) preserves and builds the lean mass that drives resting metabolic rate. The four muscle groups for aging well article covers this foundation.
  • Combine with adequate sleep: Seven to nine hours per night, with consistent bed and wake times. The midlife sleep stack article and menopause sleep remedies article cover the sleep framework.
  • Combine with daily walking: Ten to fifteen thousand steps per day, ideally in shorter frequent walks rather than one long walk. The micro walks article covers the practical framework.
  • Combine with nervous system regulation: Daily vagal reset practice supports the cortisol reduction that is part of what fascia release contributes. The vagus nerve reset exercises article covers ten specific practices.
  • Combine with foundational supplements: Magnesium, omega-3s, and vitamin D support the anti-inflammatory picture and nervous system function. The THOR foundational supplement collection covers the priorities.
  • Combine with emotional eating awareness: The emotional eating article covers the specific pattern that undermines nutrition efforts for many midlife women. Addressing this pattern is often the specific missing piece that turns the entire framework from theoretical to actual.

What Common Mistakes Can Undermine Your Fascia Release Practice?

Six mistakes consistently reduce the effectiveness of fascia release practice for midlife women pursuing weight loss support.

  • Expecting fat loss from fascia work alone: This is the single most common mistake and the one most likely to produce disappointment. Fascia release supports the interventions that produce fat loss rather than replacing them, and setting expectations correctly at the start prevents the frustration that ends the practice prematurely.
  • Forcing the release: Fascia responds to sustained gentle pressure. Forcing produces muscle guarding and reduces the release, so the correct direction is slow, gentle, and patient work with the tissue.
  • Skipping the breath: Breath is not a nice addition. It is a core mechanism. Practice without conscious breath produces less than half the effect.
  • Practicing sporadically: Twice a week produces small effects. Five or six times a week for 15 to 20 minutes produces meaningful support of the metabolic picture. The daily rhythm matters.
  • Ignoring the nutrition foundation: Fascia release without adequate protein and appropriate calorie balance produces subjective improvements without body composition changes. The nutrition foundation is not optional.
  • Ignoring sleep: Poor sleep undermines every other intervention. Fascia release combined with poor sleep produces less benefit than fascia release combined with adequate sleep. Address sleep as a peer intervention rather than an afterthought.
  • Focusing only on the abdominal work: The abdominal fascia release is the most directly targeted exercise but the whole-body approach produces better outcomes. Do not skip the thoracic extension, the deep squat, and the standing releases in favor of only the belly work.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How Does Fascia Release Fit Into the Broader THOR Framework?

Fascia release is one supporting component of the broader lifestyle medicine framework I teach at THOR. Placing it in the correct position matters.

  • Nutrition foundation: The largest single lever for midlife body composition change, covered in the resources linked throughout this article.
  • Movement layer: Fascia release complements strength training and daily walking. It does not replace either.
  • Sleep and recovery: Sleep is one of the largest levers for midlife weight loss. Fascia release supports sleep quality but does not replace addressing sleep directly.
  • Nervous system regulation: Fascia release is itself a form of nervous system regulation. The vagus nerve reset exercises article covers the broader nervous system work.
  • Supplement foundation: The THOR foundational supplement collection covers the priorities.

For personalized support that combines all of these elements, the Monthly Personal Training and Nutrition Coaching Program is the coaching option. For the immersive version, our Yoga Retreats at our Smoky Mountains property installs the full framework in five days.

When Should You See a Healthcare Professional?

Most midlife women can safely begin this program on their own. Some situations require professional evaluation first.

  • Pregnancy: Skip the Abdominal Fascia Release with Ball. Modify other exercises with prenatal-certified guidance.
  • Recent abdominal surgery: Wait for surgical clearance before starting.
  • Hernia or abdominal wall issues: Skip the Abdominal Fascia Release with Ball. Discuss other exercises with your provider.
  • Persistent unexplained weight changes: Rapid unexplained weight gain or loss warrants medical evaluation for thyroid dysfunction, PCOS, medication effects, or other conditions.
  • Severe cardiovascular disease: Any exercise program warrants clearance if you have significant heart disease.
  • Chronic pelvic pain or pelvic floor issues: Work with a pelvic floor physical therapist for individualized guidance before starting deep squat work.
  • Any severe unresolved pain: Any pain that has not been evaluated warrants medical assessment.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Frequently Asked Questions

Can fascia release actually help with belly fat?

Fascia release does not directly burn belly fat, but it supports several factors that make belly fat reduction easier in midlife women. It reduces cortisol through parasympathetic activation, improves breath depth, supports lymphatic drainage, reduces inflammation, and improves movement capacity for the strength training and walking that drive actual fat loss. Combined with adequate nutrition, protein, and sleep, fascia release is a legitimate supportive layer within a midlife weight loss framework.

How long before I see results from fascia release?

Subjective release, easier breath, and reduced puffiness are often noticeable within the first two or three sessions. Body composition changes require the combination with adequate nutrition, protein, and sleep, and generally become visible within four to eight weeks of consistent daily practice combined with the nutrition foundation.

Is fascia release safe during menopause?

Yes, fascia release is generally safe and often particularly beneficial for women in perimenopause, menopause, and post-menopause. The specific hormonal changes of this window include increased fascial stiffness, elevated cortisol, and reduced lymphatic flow, all of which fascia release directly addresses. Some exercises need modification for specific conditions, which is covered in the individual exercise sections.

Can I do the abdominal fascia release if I have a hernia?

No, skip the Abdominal Fascia Release with Ball if you have a hernia. Discuss the other exercises in this article with your provider. The other four exercises in the program are generally safe for most people with abdominal wall issues.

Do I need any equipment for these exercises?

The two most impactful exercises (Foam Roller Thoracic Extension and Abdominal Fascia Release with Ball) require a foam roller and a therapy ball respectively. Total investment is approximately $30 to $50. The other three exercises can be done with no equipment beyond a comfortable surface and a wall.

How often should I practice fascia release?

Five or six sessions per week of 15 to 20 minutes produces meaningful support of the midlife metabolic picture. Once or twice a week produces smaller effects. Daily practice is fine and often preferred by women who find the practice enjoyable. The daily rhythm is where the training effects accumulate.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Can fascia release replace strength training for weight loss?

No, fascia release complements strength training but does not replace it. Preserving and building lean muscle mass is one of the largest levers for midlife body composition. The four muscle groups for aging well article covers the strength training foundation.

What is the best time of day for fascia release?

Any time of day works, and consistency matters more than timing. Morning practice supports the day and often produces a felt-sense of openness that carries into activity. Evening practice supports sleep by activating the parasympathetic nervous system. Middle-of-the-day practice interrupts accumulated tension from sitting. Choose the time that produces the highest adherence for you.

Does fascia release help with menopause bloating?

Yes, many midlife women report meaningful reductions in bloating and puffiness with regular fascia release practice, particularly the abdominal work combined with the deep squat and standing releases. The mechanism includes improved lymphatic drainage and reduced fluid stasis in the abdominal region.

Can I do fascia release if I have chronic low back pain?

Most of the exercises in this program are generally supportive for chronic low back pain, particularly the thoracic extension and the deep squat. Any acute or severe back pain should be evaluated by a healthcare provider before starting. Modify or skip exercises that produce sharp pain.

Does the foam roller hurt?

Foam roller work often produces mild discomfort at first, particularly in areas of significant restriction. Sharp pain is not appropriate. Start with a softer roller and reduce pressure until the sensation is manageable. Discomfort generally reduces over the first two weeks of consistent practice as the fascia becomes more mobile.

Can fascia release help with hormonal weight gain?

Fascia release supports the interventions that address hormonal weight gain (nutrition, strength training, sleep, cortisol management, nervous system regulation) rather than directly changing hormones. Combined with the broader framework, it is a legitimate supportive layer for women dealing with the specific weight patterns of perimenopause and menopause.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
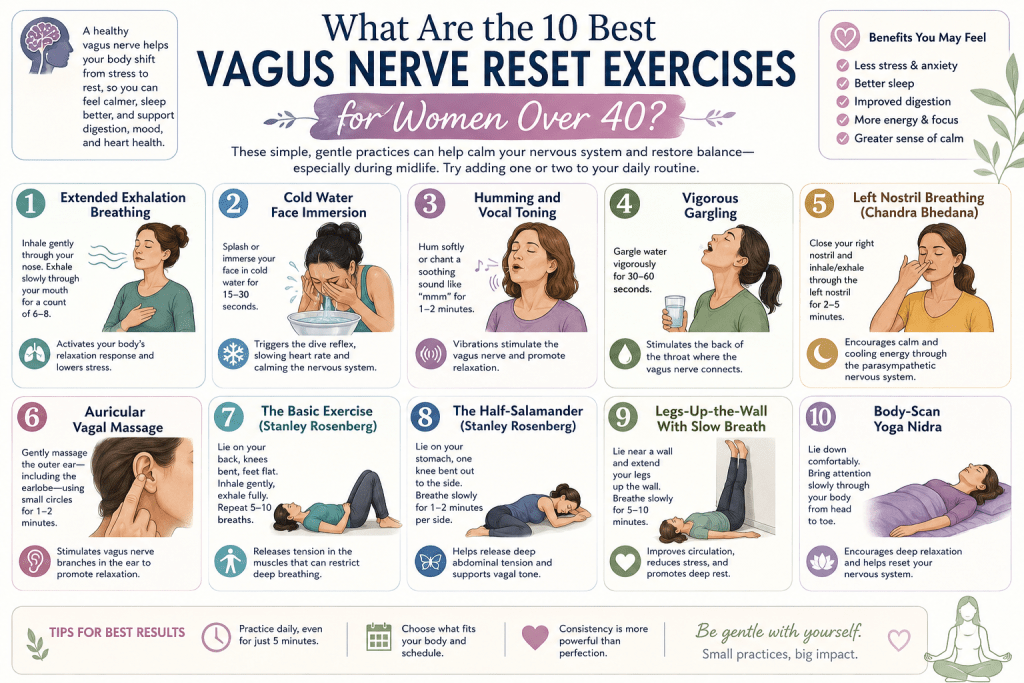
How is this different from yoga?

Yoga includes many fascia release elements and shares some principles, but the specific exercises in this article are more targeted at fascial release than at the broader mind-body practice of yoga. The five yin yoga poses article covers a specifically yin yoga sequence for myofascial release. Yoga and this fascia work are complementary rather than substitutes.

Should I combine this with walking?

Yes, walking is one of the strongest complementary practices for fascia release. Daily walking supports lymphatic flow, cardiovascular health, and mood, all of which amplify the benefits of the fascia work. The micro walks article covers the practical framework for building walking into a daily rhythm.

Can fascia release make me feel emotional?

Yes, some women experience emotional release during fascia work, particularly in the abdominal and hip regions. This is a documented phenomenon in body-based practice and is generally considered a healthy sign of stored tension releasing. The response usually passes quickly. If emotional response is intense or persistent, working with a trauma-informed body practitioner or therapist alongside the practice is often supportive.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.

References

  • Schleip, R., & Müller, D. G. (2013). Training principles for fascial connective tissues: scientific foundation and suggested practical applications. Journal of Bodywork and Movement Therapies, 17(1), 103–115.
  • Stecco, C., Stern, R., Porzionato, A., et al. (2011). Hyaluronan within fascia in the etiology of myofascial pain. Surgical and Radiologic Anatomy, 33(10), 891–896.
  • Ajimsha, M. S., Al-Mudahka, N. R., & Al-Madzhar, J. A. (2015). Effectiveness of myofascial release: systematic review of randomized controlled trials. Journal of Bodywork and Movement Therapies, 19(1), 102–112.
  • Beardsley, C., & Škarabot, J. (2015). Effects of self-myofascial release: a systematic review. Journal of Bodywork and Movement Therapies, 19(4), 747–758.
  • Behm, D. G., & Wilke, J. (2019). Do self-myofascial release devices release myofascia? Rolling mechanisms: a narrative review. Sports Medicine, 49(8), 1173–1181.
  • Wiewelhove, T., Döweling, A., Schneider, C., et al. (2019). A meta-analysis of the effects of foam rolling on performance and recovery. Frontiers in Physiology, 10, 376.
  • Cheatham, S. W., Kolber, M. J., Cain, M., & Lee, M. (2015). The effects of self-myofascial release using a foam roll or roller massager on joint range of motion, muscle recovery, and performance: a systematic review. International Journal of Sports Physical Therapy, 10(6), 827–838.
  • Bordoni, B., & Zanier, E. (2013). Anatomic connections of the diaphragm: influence of respiration on the body system. Journal of Multidisciplinary Healthcare, 6, 281–291.
  • Epel, E. S., McEwen, B., Seeman, T., et al. (2000). Stress and body shape: stress-induced cortisol secretion is consistently greater among women with central fat. Psychosomatic Medicine, 62(5), 623–632.
  • Vicennati, V., Pasqui, F., Cavazza, C., et al. (2009). Stress-related development of obesity and cortisol in women. Obesity, 17(9), 1678–1683.
  • van der Valk, E. S., Savas, M., & van Rossum, E. F. C. (2018). Stress and obesity: are there more susceptible individuals? Current Obesity Reports, 7(2), 193–203.
  • Beccuti, G., & Pannain, S. (2011). Sleep and obesity. Current Opinion in Clinical Nutrition and Metabolic Care, 14(4), 402–412.
  • Douchi, T., Yamamoto, S., Yoshimitsu, N., et al. (2002). Relative contribution of aging and menopause to changes in lean and fat mass in segmental regions. Maturitas, 42(4), 301–306.
  • Toth, M. J., Tchernof, A., Sites, C. K., & Poehlman, E. T. (2000). Effect of menopausal status on body composition and abdominal fat distribution. International Journal of Obesity, 24(2), 226–231.
  • Lovejoy, J. C., Champagne, C. M., de Jonge, L., et al. (2008). Increased visceral fat and decreased energy expenditure during the menopausal transition. International Journal of Obesity, 32(6), 949–958.
  • Tremollieres, F. A., Pouilles, J. M., & Ribot, C. A. (1996). Relative influence of age and menopause on total and regional body composition changes in postmenopausal women. American Journal of Obstetrics and Gynecology, 175(6), 1594–1600.
  • Chikly, B. J. (2005). Manual techniques addressing the lymphatic system: origins and development. Journal of the American Osteopathic Association, 105(10), 457–464.
  • Zaleska, M., Olszewski, W. L., Cakala, M., & Cwikla, J. (2013). Intermittent pneumatic compression enhances formation of edema tissue fluid channels in lymphedema of lower limbs. Lymphatic Research and Biology, 11(2), 76–83.
  • Field, T. (2016). Massage therapy research review. Complementary Therapies in Clinical Practice, 24, 19–31.
  • Ernst, E. (2009). Massage therapy for cancer palliation and supportive care: a systematic review of randomised clinical trials. Supportive Care in Cancer, 17(4), 333–337.

Disclaimer: Always consult with a healthcare professional before starting any new routines, programs, or nutrition plans to ensure you receive the best medical advice and strategy for your specific individual needs. Fascia release exercises support but do not replace evidence-based nutrition, resistance training, and medical care for weight-related concerns.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

5 Chair Tai Chi Exercises for Seniors (Plus a 5-Day Beginner Program With Videos)

Chair tai chi has become increasingly popular as more seniors and caregivers search for safe, gentle ways to stay active. Research has linked tai chi with better balance, fall prevention, cognitive function, cardiovascular health, sleep, pain management, and mood. Chair adaptations preserve the practice’s essential movements while making it more accessible for seniors who cannot safely perform standing exercises.

This guide is designed for seniors who find standing exercise uncomfortable or unsafe, as well as midlife women seeking evidence-based movement options for aging parents. It includes authentic tai chi movements adapted for seated practice, a structured 5-day beginner program, and video placement notes for readers who prefer visual demonstrations.

I am Terry Tateossian, founder of The House of Rose and a certified lifestyle medicine coach. I run nutrition-focused wellness retreats for women in perimenopause, menopause, and post-menopause at our Smoky Mountains property in East Tennessee. Many of my clients also care for aging parents, making safe movement options a frequent topic in our coaching program.

Important: Consult a healthcare provider before beginning a new movement program, especially for seniors with cardiovascular conditions, recent surgery, severe arthritis, dementia, dizziness, uncontrolled blood pressure, recent falls, or other acute health concerns. 

What Is Chair Tai Chi?

Chair tai chi is the adaptation of traditional tai chi principles and movements to a seated position. It preserves the essential elements of the practice while removing the balance demands of standing forms. Understanding what makes it authentic tai chi rather than just seated exercise is worth a moment of attention.

Chair Tai Chi vs Standing Tai Chi comparison infographic
  • The essential elements of tai chi: Tai chi is characterized by slow flowing movement, coordinated breath, gentle spinal rotation, weight-shifting patterns (in standing forms), and focused attention. The movements are traditionally sequenced into forms, which are structured sequences of postures performed in a continuous flow. Every posture has a name, a functional meaning, and a specific set of internal principles that guide the movement.
  • What chair adaptation changes: Chair versions modify the leg and weight-shifting elements while preserving the arm movements, breath coordination, spinal rotation, and attentional focus. Some chair forms include gentle leg lifts and heel raises when appropriate. The core practice remains recognizable to any traditional tai chi practitioner.
  • What chair adaptation preserves: The slow tempo, the continuous flow, the breath coordination, the attentional focus, the traditional posture names and their symbolic meaning, and the internal principles of relaxation, alignment, and gentle spiral movement.
  • The lineage question: Chair tai chi is not a modern invention. Traditional tai chi teachers have adapted the practice for elderly and disabled students for as long as the practice has existed. The current visibility of chair tai chi in senior communities and healthcare settings reflects both the growing evidence base and the recognition by traditional teachers that the practice can serve broader populations than the standing forms alone.
  • Distinction from chair yoga: Chair tai chi and chair yoga share some visual similarities but come from different traditions and produce somewhat different training effects. Chair yoga emphasizes flexibility, individual posture holds, and often more static stretching. Chair tai chi emphasizes continuous flowing movement, breath coordination, and the traditional internal principles of tai chi.

Why Is Tai Chi Well Suited to Seniors?

Several features of tai chi as a practice make it particularly well suited to older adults, and several features of chair adaptation extend that suitability to seniors who cannot safely stand for extended movement practice.

  • Low joint impact: Tai chi does not involve jumping, pounding, or high-force movements. The joints move through their full range of motion under low load, which is exactly what arthritic joints tolerate best.
  • Gradual progression: Tai chi is designed to be practiced across a lifetime. The learning curve is gentle. The movements can always be simplified. The intensity can always be modified. There is no minimum ability level required to begin.
  • Breath integration: The coordinated breathing in tai chi produces immediate parasympathetic activation and supports respiratory health, which becomes more important with age.
  • Balance without falls: The seated version specifically removes the balance risk while still training many of the neuromuscular patterns that support balance. Some standing balance components can be added back gradually as ability allows.
  • Cognitive engagement: Learning and remembering the sequences engages memory, attention, and coordination in ways that produce documented cognitive benefits.
  • Social component: Tai chi can be practiced alone or in groups. Group practice adds a social layer that is particularly protective for seniors who are at risk of isolation.
  • Cultural depth: The traditional names, meanings, and metaphors give the practice a richness that keeps many practitioners engaged for decades rather than months.
  • Time efficiency: A 10 to 15 minute daily practice produces meaningful benefit, which is a realistic time investment for most seniors.
  • Cost accessibility: No equipment beyond a chair, no membership required, and no specialized clothing needed. The economic accessibility matters at every income level.
  • Documented safety: Tai chi has one of the strongest safety records of any exercise intervention studied in older adults, with adverse event rates comparable to gentle walking.

“One of the most rewarding conversations I have with coaching clients is when they realize that their aging parent, who they had been quietly worrying about because Dad had stopped moving after his fall or Mom cannot do the walking group she used to love, actually has an accessible movement option that fits her current body. Chair tai chi is often that option. Within two or three weeks of daily practice, most seniors report better balance, easier breath, less joint stiffness, and often a noticeable shift in mood. That change is meaningful for the senior, and it is meaningful for the adult child who has been carrying the anxiety of watching a parent decline. This practice returns some sense of agency to a body that had lost it, and it does so in less time than most people expect.”

Terry Tateossian, Founder of The House of Rose

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Does Research Show About Tai Chi for Older Adults?

Tai chi is one of the most rigorously studied movement practices for older adults. The research base is substantial and consistent, and it directly supports the specific benefits most relevant to senior populations.

  • Fall prevention: Multiple meta-analyses have found that regular tai chi practice reduces fall risk in older adults by 20 to 45 percent depending on the study population and protocol. The effect size is comparable to or better than most other single-intervention fall prevention programs.
  • Balance improvement: Even for participants who cannot yet do standing tai chi, seated practice produces measurable improvements in trunk stability, coordination, and confidence in movement. These improvements often make it possible to progress to standing practice over months.
  • Cognitive function: Regular tai chi practice has been associated with improvements in memory, executive function, and processing speed in older adults, with several trials showing effects comparable to more effortful cognitive training programs. The cognitive engagement of learning and remembering forms appears to be part of the mechanism.
  • Cardiovascular health: Regular tai chi practice has been associated with modest improvements in blood pressure, cardiovascular function, and cardiac rehabilitation outcomes. It is safe for most cardiac patients when done at appropriate intensity.
  • Arthritis and joint pain: Tai chi has been specifically studied for knee osteoarthritis, hip pain, and general joint stiffness. It consistently produces reductions in pain and improvements in function comparable to standard physical therapy protocols in many trials.
  • Sleep quality: Regular practice has been associated with improved sleep quality and reduced insomnia in older adults, with effects that appear to build over weeks and months.
  • Mood and mental health: Multiple trials have documented reductions in symptoms of depression, anxiety, and general distress with regular tai chi practice. The effect is comparable to some other exercise interventions and is well-tolerated.
  • Chronic disease management: Tai chi has been studied as an adjunct in the management of Parkinson’s disease, chronic obstructive pulmonary disease, cancer survivorship, dementia, and various other conditions with generally positive findings in each area.
  • Adherence and enjoyment: One of the specific advantages of tai chi in seniors is that adherence rates are unusually high compared to other exercise interventions. People stick with it, which is part of why the outcomes are so consistent.

For a broader framing of tai chi in midlife women specifically, see our earlier articles on tai chi walking for seniors and tai chi for weight management, stress, and cortisol, which cover the standing and walking practices.

Who Is Chair Tai Chi For, and Who Should Avoid It?

Chair tai chi is safe for the great majority of adults, including many with significant limitations. Understanding the specific inclusion and exclusion criteria matters.

  • Clearly appropriate for: Seniors with mild to moderate balance concerns who cannot safely stand for long periods. Seniors recovering from illness, surgery, or hospitalization who need to rebuild activity gradually. Seniors with arthritis, joint pain, or reduced range of motion. Seniors with mild cognitive changes who benefit from the memory and coordination demands. Seniors with cardiovascular conditions that require low-intensity exercise. Adults with disabilities that make standing exercise difficult. Adults of any age recovering from injury.
  • Also appropriate for: Midlife women who want a gentle daily movement practice they can do at their desk during the workday. Adults with anxiety who benefit from the breath and attention components. Anyone recovering from a burnout period who needs low-demand movement to reintroduce daily activity.
  • Requires medical clearance: Anyone with recent cardiac events, active heart failure, uncontrolled arrhythmia, uncontrolled blood pressure, recent stroke, or acute illness should have physician clearance before beginning.
  • May need modification: Seniors with severe cognitive impairment may need direct hands-on guidance from a trained practitioner. Seniors with severe visual impairment may need adapted verbal instruction. Seniors with severe hearing impairment may need visual demonstration or written cues.
  • Not appropriate for: Adults in acute medical crisis. Adults with active chest pain, uncontrolled dizziness, or acute injuries that have not been evaluated. Adults for whom any movement produces sharp or severe pain that has not been evaluated.
  • The general rule: If a senior can sit comfortably in a chair for 15 minutes and can move the arms and torso without severe pain, chair tai chi is almost certainly safe. When in doubt, consult a physician.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Should You Prepare for Chair Tai Chi?

Several principles apply to all five exercises in this article and are worth internalizing before beginning.

  • The chair: Use a sturdy dining-height chair without arms if possible. A kitchen chair works well. Avoid armchairs, recliners, and soft chairs. The chair should be stable, and the feet should reach the floor when seated. If the feet do not reach, place a folded towel or a low footstool under the feet.
  • The seated posture: Sit toward the front half of the seat with the back straight and lengthened, feet flat on the floor roughly hip-width apart, knees bent at approximately 90 degrees, and hands resting on the thighs to start. The spine is upright but not stiff, and the shoulders are relaxed and low.
  • Breath is essential: Every tai chi movement is coordinated with breath. Inhale as the arms rise, exhale as they descend, unless otherwise noted. Breath is slow and diaphragmatic. Never hold the breath.
  • Slow is the direction: Tai chi is meant to be practiced slowly. Movements that would take one second to complete quickly should take three to five seconds in tai chi practice. The slowness is part of what produces the training effect.
  • Fluid, not jerky: The movements are continuous and flowing rather than segmented. One motion melts into the next without pauses.
  • Attention is part of the practice: Watch your hands as they move. Notice the sensation in your arms, spine, and breath. This attentional focus is what distinguishes tai chi from ordinary arm exercise and is part of what produces the cognitive benefits.
  • No pain: No exercise in this article should produce sharp pain. Some mild stretching sensation is normal. Sharp pain, joint pain, or pain that radiates is a signal to stop and reassess.
  • Consistency matters: Ten minutes a day, five days a week produces meaningful benefit within a month. Sporadic longer sessions produce less benefit.
  • Time of day: Any time works. Morning practice supports the day. Afternoon practice interrupts stiffness. Evening practice supports sleep. Choose the time that produces the highest adherence.

What Are the 5 Best Chair Tai Chi Exercises for Seniors?

The following chair tai chi exercises create a gentle, structured routine that combines slow breathing, coordinated arm movements, spinal rotation, and focused attention. Each movement can be performed while seated, making the sequence accessible for seniors with limited mobility, balance concerns, or joint discomfort.

Begin with the opening breath, progress through the flowing coordination exercises, and finish with the closing form to help the body and mind return to a calm, settled state.

Exercise 1: Seated Opening Breath

The Seated Opening Breath is the foundation of every chair tai chi session. It establishes the posture, the breath, and the attentional focus that carry through the rest of the practice. In traditional tai chi, this corresponds to the Wu Ji (empty stance) preparation and the opening movement of most forms.

This gentle arm-raising exercise combines slow movement with controlled breathing to support relaxation and upper-body mobility. Keep your movements smooth and comfortable throughout each repetition.

  1. Sit upright with your spine comfortably lengthened, shoulders relaxed, and both hands resting palms-down on your thighs.
  2. Inhale slowly for about four seconds as you gently raise both arms forward and upward.
  3. Continue lifting until your arms reach approximately shoulder height, allowing your palms to face downward.
  4. Pause briefly at the top of the inhalation with your arms extended in front of you.
  5. Exhale slowly for about four to six seconds as you gently lower your arms.
  6. Sweep your palms downward through the space in front of your body until your hands return to your thighs.
  7. This completes one repetition.
Seated Opening Breath chair tai chi infographic

The details below explain how the movement works, how many repetitions to perform, common mistakes to avoid, its benefits for seniors, and ways to modify it for shoulder discomfort.

  • How it works: The slow inhalation with rising arms activates the diaphragm and lengthens the spine. The slow exhalation with descending arms releases tension throughout the body. The combined movement establishes the coordinated breath-and-motion pattern that defines tai chi.
  • Sets and reps: 6 to 10 repetitions.
  • Common mistakes: Rushing the movement, holding the breath, hunching the shoulders as the arms rise, letting the spine collapse, forgetting the attentional focus.
  • Why this exercise for seniors: This is the safest and most accessible exercise in the sequence. It establishes the postural and breath foundation for everything else, and it produces immediate parasympathetic activation. Many seniors report feeling meaningfully calmer within two or three repetitions.
  • Modification for shoulder issues: If raising the arms to shoulder height is uncomfortable, keep the arms lower. Even raising the arms to belly level while coordinating with the breath produces meaningful benefit.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Exercise 2: Seated Wave Hands Like Clouds

Seated Wave Hands Like Clouds is the chair adaptation of one of the most beloved and studied movements in traditional tai chi. In Chinese it is called Yun Shou, and it appears in nearly every major tai chi form. It combines lateral arm movement with gentle trunk rotation and coordinated breath.

This gentle seated movement coordinates the arms, trunk, and breathing in a smooth side-to-side pattern. Move slowly and stay within a comfortable range throughout each repetition.

  1. Sit in the recommended position with your spine upright and shoulders relaxed.
  2. Raise your right hand to shoulder height in front of your right shoulder, with the palm facing you.
  3. Place your left hand at belly height in front of your abdomen, also with the palm facing you, forming a soft vertical stack with both hands.
  4. Slowly rotate your trunk to the right as your right hand sweeps horizontally toward the right side.
  5. At the same time, raise your left hand to shoulder height in front of your left shoulder.
  6. Finish with your left hand at shoulder height and your right hand at belly height, creating a mirror image of the starting position.
  7. Pause briefly, then slowly rotate your trunk to the left as your left hand sweeps across and your right hand rises.
  8. Continue alternating sides, inhaling as one arm rises and exhaling as the other arm sweeps across.
Seated Wave Hands Like Clouds infographic

This gentle chair tai chi movement combines flowing arm patterns with slow trunk rotation to challenge both the body and mind. The details below explain its benefits, recommended repetitions, common mistakes, and simple modifications for limited shoulder mobility.

  • How it works: The alternating arm movement combined with gentle trunk rotation trains coordination, working memory, spinal mobility, and left-right integration. The graceful cloud-like quality of the arm movements is what gives the posture its name.
  • Sets and reps: 8 to 12 rounds (one round is one full rotation to each side).
  • Common mistakes: Moving too fast, forgetting the trunk rotation and only moving the arms, holding tension in the shoulders, letting the hands drop below their proper heights.
  • Why this exercise for seniors: Wave Hands Like Clouds produces significant training effects in trunk stability, coordination, and cognitive engagement. It is one of the most cognitively demanding of the chair tai chi exercises and often the one that produces the most noticeable mental engagement.
  • Modification for shoulder mobility: Keep the hands lower if shoulder height is uncomfortable. Even a smaller version of the movement produces meaningful benefit.

Exercise 3: Seated Grasping the Bird’s Tail

Seated Grasping the Bird’s Tail is a chair adaptation of one of the most fundamental sequences in traditional tai chi. In Chinese it is called Lan Que Wei, and it contains four essential energies (Peng, Lu, Ji, An, which translate roughly to ward off, roll back, press, and push). This exercise gives the practitioner a taste of the deeper energetic principles of tai chi.

This flowing sequence combines four gentle tai chi movements to improve coordination, posture, and breath control. Move slowly through each step, allowing the arms, trunk, and breathing to work together smoothly.

  1. Begin in the Starting Position: Sit comfortably with proper posture and rest both hands on your thighs.
  2. Ward Off (Peng): Slowly raise your right arm to shoulder height in front of your body, with the palm facing you as though holding a large ball. Raise your left hand just below the right elbow with the palm facing downward, inhaling as both arms rise.
  3. Roll Back (Lu): Gently rotate your trunk to the right while drawing both hands backward and downward toward your right hip in a smooth arc. Exhale as the hands move back.
  4. Press (Ji): Place your left hand against the inside of your right wrist. Press both hands forward together at chest height, inhaling as the movement begins.
  5. Push (An): Separate the hands slightly, then press them forward and gently downward. Exhale as you complete the push.
  6. Return to the Starting Position: Slowly lower both hands back onto your thighs. This completes one full round.
Seated Grasping the Bird’s Tail infographic

Grasping the Bird’s Tail combines four flowing movements that build coordination, breath control, spatial awareness, and mental focus. The following guidance explains its benefits, recommended repetitions, common mistakes, and beginner-friendly modifications.

  • How it works: The four movements sequenced together train continuous flowing coordination, spatial awareness, breath control, and the internal principles of yielding and pressing that give tai chi its distinctive character. This is where chair tai chi begins to feel like a real practice rather than a set of isolated exercises.
  • Sets and reps: 4 to 6 rounds on the right side. Then repeat the entire sequence on the left side (mirror image) for 4 to 6 rounds.
  • Common mistakes: Trying to memorize the sequence too quickly, forgetting the breath coordination, moving mechanically without the flowing quality, holding tension in the shoulders. The sequence takes a few sessions to feel comfortable, so give it time to settle in.
  • Why this exercise for seniors: Grasping the Bird’s Tail produces the largest cognitive engagement of any exercise in this sequence and connects the practice to traditional tai chi principles that keep many practitioners engaged for years. The four-phase structure gives the brain the kind of learning demand that supports cognitive health.
  • Modification for beginners: For the first two or three sessions, practice only the first two phases (Ward Off and Roll Back). Add Press and Push once the first two feel comfortable.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Exercise 4: Seated Brush Knee With Rotation

Seated Brush Knee is a chair adaptation of the traditional Brush Knee and Twist Step (Lou Xi Ao Bu), one of the classic postures of tai chi. The seated version preserves the upper body coordination, spinal rotation, and breath integration while omitting the leg stepping component.

This gentle movement combines trunk rotation with coordinated pushing and brushing motions to improve upper-body mobility and balance. Move slowly with the breath, keeping the shoulders relaxed throughout.

  1. Sit in the recommended position with both hands resting on your thighs.
  2. Raise your right hand beside your right ear with the palm facing forward. Keep your left hand palm-down near your left thigh.
  3. Gently rotate your trunk to the right while inhaling.
  4. Slowly unwind and rotate to the left as you push your right hand forward at chest height, as though gently pressing against a wall.
  5. At the same time, sweep your left hand down and across your left thigh, as though brushing something off your knee.
  6. Exhale as you complete the pushing and brushing movements, then return to the neutral starting position.
  7. Raise your left hand beside your left ear and gently rotate your trunk to the left while inhaling.
  8. Unwind and rotate to the right as your left hand pushes forward and your right hand brushes across your right thigh.
  9. Exhale as the movement finishes, then return both hands to your thighs.
Seated Brush Knee with Rotation infographic

This movement combines gentle trunk rotation with coordinated pushing and brushing actions to improve mobility, balance, and cross-body control. It also helps maintain the natural turning and reaching patterns used in everyday activities.

  • How it works: The combined trunk rotation, one-hand-pressing, and one-hand-brushing motion trains cross-body coordination, spinal mobility, and the kind of spiral movement that keeps the middle back supple. The rotation component addresses the specific stiffness that develops in older adults from prolonged sitting and reduced daily rotation.
  • Sets and reps: 4 to 6 rounds per side (one round is one push-and-brush).
  • Common mistakes: Forgetting the trunk rotation and only moving the arms, moving too fast, holding tension in the shoulders, letting the pushing hand lock at the elbow.
  • Why this exercise for seniors: Brush Knee is one of the most functional tai chi movements because the coordinated rotation and reach mirrors many real-life motions like reaching to open a door while turning, or gesturing during conversation. Regular practice keeps these patterns available.
  • Modification for shoulder restriction: Reduce the height of the raised hand. Even a smaller version of the movement produces training benefit.

Exercise 5: Seated Closing Form and Gathering Qi

The Seated Closing Form is the traditional way to complete a tai chi session. It gathers the effects of the practice, quiets the nervous system, and prepares the body to move back into daily activity. In traditional forms this often includes a movement called Gathering Qi (Shou Shi), which is what this exercise adapts for chair practice.

This calming movement combines slow breathing with wide, flowing arm motions to encourage relaxation and body awareness. It finishes with the hands resting over the lower abdomen to create a quiet, centered pause.

  1. Sit in the recommended position with both hands resting on your thighs, palms facing upward if comfortable.
  2. Inhale slowly for about four seconds as you extend both arms outward in a wide arc.
  3. Continue raising the arms until your hands reach approximately shoulder height, keeping the palms facing upward and the elbows softly bent.
  4. Form a gentle bowl shape with both arms at the sides of the body.
  5. Exhale slowly for about four to six seconds as you bring both hands together in front of your body.
  6. Lower the hands slowly down the center of the torso, keeping the palms facing inward.
  7. When the hands reach the lower abdomen, rest them palm-over-palm. Traditionally, women place the right hand under the left, while men place the left hand under the right, although this may vary.
  8. Remain in this position and take three to five slow, relaxed breaths.
Seated Closing Form and Gathering Qi infographic

This gentle closing movement helps the body settle into a deeper state of calm while bringing the practice to a peaceful finish. It also gives seniors a quiet moment to focus on their breathing before returning gradually to daily activities.

  • How it works: The slow gathering movement combined with slow breath produces a final parasympathetic activation that consolidates the effects of the session. Traditionally the practitioner imagines drawing energy inward and storing it at the lower abdomen (the dantian in Chinese terminology). The imagery is not required for the physiological benefit but adds a meaningful attentional focus for practitioners who resonate with it.
  • Sets and reps: 3 to 5 rounds of the gathering movement. Finish with 30 to 60 seconds of quiet seated breathing.
  • Common mistakes: Rushing the closing, forgetting the pause at the end, standing up abruptly at the completion of the practice, dropping the attentional focus.
  • Why this exercise for seniors: The closing form is often the most subjectively pleasant part of the session. Many seniors report a distinct sense of calm settling after this exercise. It also functions as a transition ritual between practice and daily activity, which supports the sustainability of the daily habit.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Does the 5-Day Progressive Chair Tai Chi Program Work?

The five exercises above form the core of the practice. The 5-day program combines them into a structured progressive sequence designed to introduce the practice comfortably and to produce meaningful benefit within one week. Total time commitment per day ranges from 8 to 20 minutes.

Day 1: Introduction (8 minutes)

The first day introduces only the opening and closing movements, which are the safest and most accessible.

Exercise

Reps or Duration

Seated Opening Breath

8 reps

Rest and breathe

1 min

Seated Closing Form and Gathering Qi

3 rounds + 30 sec quiet breath

Day 1 is deliberately simple. The purpose is to establish the seated posture, the breath coordination, and the flowing quality of movement without introducing anything overwhelming.

Day 2: Add Wave Hands (12 minutes)

The second day adds the Wave Hands sequence for coordination and rotation.

Exercise

Reps or Duration

Seated Opening Breath

8 reps

Seated Wave Hands Like Clouds

10 rounds

Seated Closing Form

3 rounds + 30 sec quiet breath

Day 3: Add Grasping the Bird’s Tail (16 minutes)

The third day adds the four-energy sequence for the cognitive engagement layer.

Exercise

Reps or Duration

Seated Opening Breath

6 reps

Seated Wave Hands Like Clouds

8 rounds

Seated Grasping the Bird’s Tail

4 rounds each side

Seated Closing Form

3 rounds + 30 sec quiet breath

Day 3 is where the practice starts to feel like a real tai chi session. Give yourself extra time to learn the Grasping the Bird’s Tail sequence.

Day 4: Add Brush Knee (18 minutes)

The fourth day adds the rotation and reach pattern.

Exercise

Reps or Duration

Seated Opening Breath

6 reps

Seated Wave Hands Like Clouds

8 rounds

Seated Grasping the Bird’s Tail

4 rounds each side

Seated Brush Knee With Rotation

4 rounds each side

Seated Closing Form

3 rounds + 30 sec quiet breath

Day 5: Full Sequence (20 minutes)

The fifth day integrates all five exercises into the complete sequence with slightly more repetitions of each.

Exercise

Reps or Duration

Seated Opening Breath

8 reps

Seated Wave Hands Like Clouds

10 rounds

Seated Grasping the Bird’s Tail

5 rounds each side

Seated Brush Knee With Rotation

5 rounds each side

Seated Closing Form

5 rounds + 60 sec quiet breath

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Should You Do After Completing the 5-Day Program?

The first five days establish the practice. From day six forward, the most effective practice is a daily session of the full sequence (approximately 20 minutes) five or six days per week. Once the sequence feels familiar, most practitioners find that adding an extra round or two of their favorite exercises extends the session naturally. The practice becomes a friend rather than an assignment.

Subjective calm and easier breath is often noticeable within the first two or three sessions. Better balance, less joint stiffness, and improved sleep generally appear within two to three weeks of consistent daily practice. Deeper benefits including improved cognitive function and reduced fall risk develop over three to six months.

“The most common report I hear from coaching clients whose parents have started a chair tai chi practice is that within a month the parent starts asking for the daily video, looks forward to it, and treats it as one of the best parts of the day. Chair tai chi has a specific quality of being enjoyable rather than obligatory, which is the opposite of most exercise recommendations at any age. For seniors who have been quietly avoiding movement because everything felt hard or scary, having a practice that actually feels good is a significant psychological shift. That shift often opens the door to other movement over the following months, including gradual return to walking, gentle strength work, and social activity. Chair tai chi is often the beginning of a broader reawakening of the body in later life, not just an isolated intervention.”

Terry Tateossian, Founder of The House of Rose

What Common Mistakes Can Undermine Chair Tai Chi Practice?

Six mistakes consistently reduce the effectiveness of chair tai chi practice for seniors and for caregivers introducing the practice.

  • Moving too fast: Tai chi is defined by its slowness. Rushing through the movements converts the practice into ordinary arm exercise that misses most of the training effect. If in doubt, slow down further.
  • Holding the breath: Every movement is coordinated with breath. Practicing without conscious breath coordination reduces the benefits significantly. Inhale as the arms rise. Exhale as they descend.
  • Skipping the opening and closing: The opening establishes the practice state. The closing consolidates it. Many practitioners want to skip straight to the middle exercises. These bookends are part of what makes the practice work.
  • Practicing too infrequently: Once or twice a week produces small benefits. Five or six times a week for 15 to 20 minutes produces meaningful benefits. The daily rhythm is where the training effect accumulates.
  • Introducing too many exercises too fast: The 5-day progression is deliberate. Trying to learn all five exercises on day one produces overwhelm and reduces the likelihood of continuing, so follow the progression as designed.
  • Forcing form perfection: Perfect form matters less than consistent practice with reasonable form. A senior who practices imperfectly for a year produces vastly better results than one who waits for perfect instruction and does not practice.
  • Skipping the attentional focus: The mental focus (watching the hands, feeling the breath, noticing sensations) is part of what produces the cognitive benefits. Practicing while watching TV or thinking about other things reduces these benefits.

How Does Chair Tai Chi Fit Into a Broader Healthy Aging Framework?

Chair tai chi is one component of the broader framework for movement, mind, and body in later life. Placing it in context helps determine how to combine it with other practices.

  • Complements walking: Chair tai chi does not replace daily walking for seniors who can walk, and it complements walking rather than substituting for it. Daily walking builds cardiovascular fitness and outdoor exposure. Chair tai chi adds coordination, breath, cognitive engagement, and postural work.
  • Complements strength work: Chair tai chi is not primarily a strength intervention. Seniors who can do resistance training benefit from adding it. See our four muscle groups for aging well article for the strength framework adapted to older adults, and the tai chi walking for seniors article for the walking-based standing practice.
  • Complements nutrition: Adequate protein intake supports the muscle preservation that tai chi does not directly address. The free Macro Calculator gives a starting protein target. The Macro Miracle Mediterranean Cookbook is the kitchen-side companion for eating this way sustainably.
  • Complements sleep: The parasympathetic activation of chair tai chi supports the sleep quality that consolidates the training effects. The menopause sleep remedies article and the midlife sleep stack article cover the sleep framework.
  • Complements nervous system regulation: The breath and attention components of chair tai chi are themselves a form of vagal reset. The practice pairs well with the vagus nerve reset exercises article framework.
  • For midlife caregivers specifically: The Monthly Personal Training and Nutrition Coaching Program supports the caregiver’s own health, which is often neglected during periods of parental caregiving. The Deeply Restorative Yoga and Nature Retreat at our Smoky Mountains property is the deep-reset option for caregivers who need their own restoration time.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

When Should You See a Healthcare Professional?

Most seniors can safely begin chair tai chi on their own or with a caregiver’s support. Some situations warrant professional evaluation first.

  • Any acute or new symptoms: New chest pain, shortness of breath, dizziness, or neurological symptoms warrant medical evaluation before starting any exercise.
  • Recent cardiac events: Recent heart attack, arrhythmia, or heart failure exacerbation should be evaluated and cleared before beginning.
  • Recent stroke: Post-stroke movement work should be guided by a physical or occupational therapist for at least the first months.
  • Recent falls: A pattern of recent falls warrants a fall risk assessment and often a physical therapy consultation before beginning independent practice.
  • Uncontrolled dizziness or vertigo: Address the underlying cause before beginning movement practice that could exacerbate symptoms.
  • Severe cognitive impairment: Advanced dementia may require hands-on practitioner guidance rather than self-directed practice or family-guided practice.
  • Recent orthopedic surgery: Recent joint replacement, spinal surgery, or other significant orthopedic surgery needs surgical clearance and often physical therapy guidance.
  • Any severe unresolved pain: Any pain that has not been evaluated and is severe or worsening warrants medical assessment.

How Can Adult Children Introduce Chair Tai Chi to Their Parents?

Many readers of this article are midlife women thinking about introducing chair tai chi to an aging parent. This introduction is a specific relational moment that benefits from some thought.

  • Do not push the topic: Any suggestion to an aging parent that lands as a criticism of their current activity level tends to produce resistance. Present chair tai chi as something you are doing yourself, or as something you found interesting, or as an option they might enjoy exploring. Do not present it as an intervention for their perceived decline.
  • Offer to do it together: Practicing alongside a parent, either in person or over video call, removes the awkwardness of asking them to try something new alone. It also makes the practice a shared activity rather than a prescribed one.
  • Set up the space: If you visit your parent, take the extra minute to move a sturdy chair into a convenient space and cue up a video on their tablet or television. Removing the setup friction significantly increases the likelihood they will actually practice.
  • Do not overload them with information: Starting with just the opening breath is often enough for the first visit. Layer in additional exercises only as they express interest.
  • Respect their pace: Some parents will engage quickly, while others will resist for months and then quietly start practicing on their own. The relational approach is patience and consistency, not intensity.
  • Take care of yourself: Caregiver burnout is real. Your own health matters as much as your parent’s. The Monthly Personal Training and Nutrition Coaching Program is one option for sustained support during a caregiving period. The Deeply Restorative Yoga and Nature Retreat is the deep-reset option for caregivers who have been running on empty.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Are Your Next Steps for Starting Chair Tai Chi?

If the framework in this article resonates and you want to begin a chair tai chi practice for yourself or introduce it to a parent, here are the four next steps in order of friction.

  1. Start today with Day 1 of the program. Fifteen minutes and a sturdy chair. Seated Opening Breath followed by Seated Closing Form. No prior experience required.
  2. Complete the full 5-day program this week. Follow the daily protocols in section 11. Track how the body feels each day.
  3. Continue with the maintenance practice. After day five, keep the daily 20 minute practice going five or six days per week. Add the extra rounds of your favorite exercises as they emerge as favorites.
  4. Consider deeper support. If you are a midlife woman caring for an aging parent, the Monthly Personal Training and Nutrition Coaching Program supports your own health during the caregiving period. The Deeply Restorative Yoga and Nature Retreat at our Smoky Mountains property is the deep-reset option for caregivers who need restorative time for themselves.

Frequently Asked Questions

Is chair tai chi safe for seniors with balance problems?

Yes, chair tai chi is specifically designed to be safe for seniors with balance concerns. The seated position removes the fall risk of standing exercise while still training many of the neuromuscular patterns that support balance. Seniors with balance concerns can begin chair practice safely and progress gradually toward standing practice as balance improves. Seniors with recent falls should have a fall risk assessment before starting any new exercise.

How long does it take to see benefits from chair tai chi?

Subjective calm and easier breath is often noticeable within the first two or three sessions. Better balance, less joint stiffness, and improved sleep generally appear within two to three weeks of consistent daily practice. Deeper benefits including improved cognitive function and reduced fall risk develop over three to six months of regular practice.

Can seniors with arthritis do chair tai chi?

Yes, chair tai chi is particularly well suited to seniors with arthritis. The slow gentle movement takes joints through their full range of motion under low load, which is exactly what arthritic joints tolerate best. Many clinical studies of tai chi for knee osteoarthritis and other joint conditions have shown pain reduction and functional improvement comparable to standard physical therapy protocols.

How often should seniors practice chair tai chi?

Five or six sessions per week of 15 to 20 minutes each produces meaningful benefits. Once or twice a week produces smaller effects. Daily practice is fine and often preferred by seniors who find the practice enjoyable. The rhythm of daily practice is where the training effects accumulate.

Do I need special equipment for chair tai chi?

No, chair tai chi requires only a sturdy dining-height chair without arms, a small amount of open space, and comfortable clothing. No mat, no special shoes, no equipment. This economic and logistical accessibility is part of what makes the practice suitable for widespread senior use.

Can chair tai chi help with dementia or memory problems?

Regular tai chi practice has been associated with improvements in memory, executive function, and processing speed in older adults. The cognitive engagement of learning and remembering forms appears to be part of the mechanism. For seniors with mild cognitive impairment or early dementia, chair tai chi is a reasonable practice to include in a broader cognitive-support strategy. For seniors with advanced dementia, hands-on guidance from a trained practitioner is often needed rather than self-directed video-based practice.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Is chair tai chi the same as chair yoga?

No, they come from different traditions and produce somewhat different training effects. Chair yoga emphasizes flexibility, individual posture holds, and often more static stretching. Chair tai chi emphasizes continuous flowing movement, breath coordination, and the traditional internal principles of tai chi. Both are valuable, and many seniors benefit from doing both.

Can I do chair tai chi if I have heart problems?

Chair tai chi is generally safe for seniors with stable cardiovascular conditions and is often included in cardiac rehabilitation programs. Anyone with recent cardiac events, uncontrolled arrhythmia, uncontrolled blood pressure, or active heart failure should have physician clearance before beginning. When cleared, chair tai chi is one of the gentlest and most heart-friendly forms of exercise available.

How do I introduce chair tai chi to my elderly parent?

Present it as something you are doing yourself or as something interesting you found rather than as an intervention for their perceived decline. Offer to do it together in person or over video call. Set up the chair and cue up the video for them. Start with just the opening breath. Layer in more exercises only as they express interest. Respect their pace. Do not push.

What is the best time of day to practice chair tai chi?

Any time works, and consistency matters more than timing. Morning practice supports the day and often produces a calmer sense of purpose entering activities. Afternoon practice interrupts sitting-related stiffness. Evening practice supports sleep. Choose the time that produces the highest adherence for you or your loved one.

Can chair tai chi help with anxiety or depression in seniors?

Multiple studies have documented reductions in symptoms of depression, anxiety, and general distress with regular tai chi practice in older adults. The combination of movement, breath, focused attention, and often social engagement addresses several drivers of low mood in later life. Chair tai chi is not a substitute for appropriate mental health treatment for clinical depression, but it is a reasonable component of a broader mental wellness approach.

Is there research showing that chair tai chi actually works?

Yes, the tai chi research base is extensive. Multiple meta-analyses have documented benefits for balance, fall prevention, cognitive function, cardiovascular health, arthritis pain, sleep quality, and mood in older adults. Chair-adapted versions preserve many of these benefits while remaining safer for seniors who cannot do standing practice. The 5-day program in this article is a beginner introduction rather than a comprehensive replacement for group class practice or individual instruction.

What if I cannot follow the video?

The written instructions in this article are designed to be followable without video. If video does not fit your situation (visual impairment, no device, no internet), the written instructions plus the illustrations of each exercise are sufficient to establish the practice. Some seniors also benefit from having a family member read the instructions aloud while they practice.

Can I do chair tai chi if I am recovering from surgery?

Recent surgery is a reason to check with your surgeon before beginning any new exercise program. Once cleared, chair tai chi is often an appropriate re-entry point to movement because of its gentle nature. Many seniors find that chair tai chi during recovery periods maintains a sense of physical agency and supports the return to fuller activity as healing progresses.

How does chair tai chi compare to walking for seniors?

Both are excellent, and they address different things. Walking builds cardiovascular fitness, outdoor exposure, and simple stamina. Chair tai chi builds coordination, breath control, gentle rotation, cognitive engagement, and postural work. Seniors who can walk safely benefit from doing both. Seniors who cannot walk safely can still get significant benefit from chair tai chi alone. See our tai chi walking for seniors article for the walking-based practice option.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.


References

  • Wayne, P. M., & Fuerst, M. L. (2013). The Harvard Medical School Guide to Tai Chi. Shambhala Publications.
  • Lauche, R., Wayne, P. M., Dobos, G., & Cramer, H. (2016). Prevalence, patterns, and predictors of t’ai chi and qigong use in the United States: results of a nationally representative survey. Journal of Alternative and Complementary Medicine, 22(4), 336–342.
  • Huang, Z. G., Feng, Y. H., Li, Y. H., & Lv, C. S. (2017). Systematic review and meta-analysis: tai chi for preventing falls in older adults. BMJ Open, 7(2), e013661.
  • Lomas-Vega, R., Obrero-Gaitán, E., Molina-Ortega, F. J., & Del-Pino-Casado, R. (2017). Tai chi for risk of falls: a meta-analysis. Journal of the American Geriatrics Society, 65(9), 2037–2043.
  • Li, F., Harmer, P., Fitzgerald, K., et al. (2012). Tai chi and postural stability in patients with Parkinson’s disease. New England Journal of Medicine, 366(6), 511–519.
  • Wayne, P. M., Walsh, J. N., Taylor-Piliae, R. E., et al. (2014). Effect of tai chi on cognitive performance in older adults: systematic review and meta-analysis. Journal of the American Geriatrics Society, 62(1), 25–39.
  • Wang, C., Schmid, C. H., Iversen, M. D., et al. (2016). Comparative effectiveness of tai chi versus physical therapy for knee osteoarthritis: a randomized trial. Annals of Internal Medicine, 165(2), 77–86.
  • Yeh, G. Y., Wang, C., Wayne, P. M., & Phillips, R. S. (2008). The effect of tai chi exercise on blood pressure: a systematic review. Preventive Cardiology, 11(2), 82–89.
  • Chan, A. W., Yu, D. S., Choi, K. C., et al. (2016). Tai chi qigong as a means to improve night-time sleep quality among older adults with cognitive impairment: a pilot randomized controlled trial. Clinical Interventions in Aging, 11, 1277–1286.
  • Wang, F., Lee, E. K., Wu, T., et al. (2014). The effects of tai chi on depression, anxiety, and psychological well-being: a systematic review and meta-analysis. International Journal of Behavioral Medicine, 21(4), 605–617.
  • Chen, W., Ju, Y. J., & Sun, T. L. (2020). Chair-based tai chi for older adults: a systematic review. Journal of Clinical Nursing, 29(15-16), 2765–2776.
  • Yang, G. Y., Wang, L. Q., Ren, J., et al. (2015). Evidence base of clinical studies on tai chi: a bibliometric analysis of controlled trials. PLoS One, 10(3), e0120655.
  • Zheng, G., Lan, X., Li, M., et al. (2015). The effectiveness of tai chi on the physical and psychological well-being of college students: a study protocol for a randomized controlled trial. Trials, 15, 129.
  • Lan, C., Chen, S. Y., Lai, J. S., & Wong, A. M. (2013). Tai chi chuan in medicine and health promotion. Evidence-Based Complementary and Alternative Medicine, 2013, 502131.
  • Klein, P. J., & Adams, W. D. (2004). Comprehensive therapeutic benefits of tai chi: a critical review. American Journal of Physical Medicine and Rehabilitation, 83(9), 735–745.
  • Tsang, W. W., & Hui-Chan, C. W. (2004). Effect of 4- and 8-wk intensive tai chi training on balance control in the elderly. Medicine and Science in Sports and Exercise, 36(4), 648–657.
  • Field, T. (2011). Tai chi research review. Complementary Therapies in Clinical Practice, 17(3), 141–146.
  • Barrow, D. E., Bedford, A., Ives, G., et al. (2007). An evaluation of the effects of tai chi chuan and chi kung training in patients with symptomatic heart failure: a randomised controlled pilot study. Postgraduate Medical Journal, 83(985), 717–721.
  • Rogers, C. E., Larkey, L. K., & Keller, C. (2009). A review of clinical trials of tai chi and qigong in older adults. Western Journal of Nursing Research, 31(2), 245–279.

Disclaimer: Always consult with a healthcare professional before starting any new routines, programs, or nutrition plans to ensure you receive the best medical advice and strategy for your specific individual needs.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

5 Myofascial Release Exercises for Tight Psoas for Women Over 40 (Plus a 5-Day Release Program With Videos)

Exercises for a tight psoas are one of the most useful and overlooked movement practices for women over 40. The psoas connects the lower spine to the thigh and plays a major role in hip movement, posture, and stability. Because it shortens during prolonged sitting, decades of daily sitting can leave it chronically restricted by the time perimenopause and menopause begin.

A tight psoas can contribute to low back pain, pelvic tilt, shallow breathing, poor posture, and deep hip tension that is difficult to locate. Standard stretching does not always reach it effectively, which is why a more targeted approach is often needed.

This guide includes five exercises that address the psoas through passive release, active stretching, mobility, myofascial work, and functional movement. It also includes a five-day program that takes 10 to 20 minutes a day, with video placement notes for each exercise.

I am Terry Tateossian, founder of The House of Rose and a certified lifestyle medicine coach who runs nutrition-focused wellness retreats for women in perimenopause, menopause, and post-menopause. Psoas restriction is one of the most common movement issues I see in retreat guests, and this program reflects the practices we use to help them continue their progress at home.

Important: Consult your healthcare provider before beginning psoas work if you have a history of back injury, hip surgery, pelvic floor problems, hernia, pregnancy, or unexplained acute pain. Stop immediately if an exercise causes sharp, radiating, or low back pain.

What Is the Psoas and Why Does It Matter?

The psoas major (usually just called the psoas) is a long, deep muscle that runs from the vertebrae of the lower spine down through the pelvis and attaches to the top of the femur (thigh bone). Along with the iliacus muscle, which lines the inner bowl of the pelvis, the two together form what is often called the iliopsoas. When most people say psoas, they usually mean the iliopsoas group.

Psoas anatomy, function, and health connections infographic.
  • Its primary function: The psoas is the strongest hip flexor in the body. When it contracts, it draws the thigh toward the torso, which is what happens when you lift a knee, climb a stair, or take a step forward. It also stabilizes the lumbar spine and plays a role in maintaining upright posture.
  • Its anatomical position: The psoas sits deep in the body. It cannot be easily massaged from the outside. It is behind the abdominal organs, in front of the lumbar spine, and travels down through the pelvic bowl. This deep position is one of the reasons it is so often overlooked and undertreated.
  • Its unusual dual role: The psoas is one of only a small number of muscles that has both a structural role (supporting the spine and pelvis) and a movement role (flexing the hip). This dual identity is part of why it responds so differently to different interventions. Passive release addresses one aspect of it. Active stretching addresses another. Both are needed for a complete recovery from restriction.
  • Its emotional connection: The psoas is heavily innervated by the autonomic nervous system and is one of the muscles that reflexively contracts in response to fear and stress. This connection between the psoas and the nervous system is why some practitioners refer to it as an emotional muscle. Chronic stress can produce chronic psoas contraction, and chronic psoas contraction can reinforce a sympathetically activated nervous system state.
  • Its position relative to breath: The diaphragm and the psoas share fascial connections and functional relationships. Restricted breath contributes to psoas tension. Psoas tension restricts the depth of breath. This bidirectional loop is one of the reasons that combined breath-and-movement approaches to psoas release are more effective than pure stretching approaches.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Why Does the Psoas Tighten in Midlife Women?

Psoas restriction is common at every stage of adult life, and it becomes particularly common and particularly consequential in midlife women. Several factors converge to make the psoas one of the most restricted muscles in the perimenopause and menopause window.

  • Decades of prolonged sitting: Every hour spent seated is an hour in which the psoas is held in a shortened position. For most professional women, this adds up to six to ten hours per day for twenty or thirty years by the time perimenopause arrives. Muscles adapt to the position they spend the most time in, and the psoas has spent most of its life short.
  • Cortisol elevation and sympathetic tone: The stress of midlife life, combined with the cortisol dysregulation of perimenopause and menopause, keeps the sympathetic nervous system chronically activated. Because the psoas contracts reflexively with nervous system activation, chronic stress produces chronic psoas contraction.
  • Hormonal changes affect fascia and connective tissue: Declining estrogen changes the composition and behavior of fascia and connective tissue in ways that generally make them stiffer and less pliable. The psoas, which is surrounded by dense fascia, becomes harder to release with the same interventions that worked in younger years.
  • Less Sleep prevents recovery: The nightly repair that keeps the psoas from accumulating restriction depends on adequate deep sleep, which is often disrupted in the perimenopause and menopause window. Poor sleep means restriction accumulates faster than it releases.
  • Pelvic floor changes: The pelvic floor and the psoas are functionally connected, and the changes in pelvic floor tone that many women experience in midlife feed back into psoas tension patterns.
  • Reduced whole-body movement: Most midlife women move less than they did in their twenties and thirties. Less overall movement means fewer opportunities for the psoas to be taken through its full range of motion, which allows it to adapt to a progressively narrower range.
  • Historic core work patterns: The generation of women who grew up doing traditional sit-ups and crunches often overtrained the psoas as part of the core work of the 1990s and early 2000s. This decades-long overuse pattern layers on top of the sitting pattern to produce particularly stubborn psoas restriction in women now in their forties and fifties.
  • The compensatory pattern: Once the psoas is restricted, the body compensates by borrowing motion from the lumbar spine. This produces the arched lower back, tucked pelvis, or tilted pelvic pattern that many midlife women recognize in themselves. The compensatory pattern reinforces the restriction, which reinforces the compensation.

“The psoas is where I see the most retreat guests have their body-based aha moment during the week. They arrive with low back pain they have been managing for years, or with a sense of hip tension they cannot quite locate, or with a general body stiffness they thought was just aging. By the third day of daily psoas release work, most of them can feel the difference physically. By the fifth day, many of them describe standing taller, breathing deeper, and moving with a lightness they had forgotten was available. This is not because the psoas is a magic muscle. It is because it is the specific muscle that most midlife women’s bodies have been asking for attention on for years without getting it. When you finally address it, the whole body responds.”

Terry Tateossian, Founder of The House of Rose

What Are the Signs of a Restricted Psoas?

Not every hip issue is a psoas issue, but the pattern of signs below often indicates chronic psoas restriction and suggests that a targeted release program would produce meaningful benefit.

The clearest signs include chronic low back pain or tightness particularly in the lumbar region, deep hip tension that does not resolve with standard hip stretches, an anterior pelvic tilt (the lower back arches noticeably when standing relaxed), difficulty standing tall without effort, tightness in the front of the hip when climbing stairs, discomfort or pinching in the front of the hip when squatting deep, shortened stride when walking, an inability to fully extend the hip behind the body, restricted breath depth particularly on the inhale, and a general sense of feeling stuck or braced in the body. Any three or four of these together is a reasonable signal to begin a targeted psoas release program.

  • A simple self-test: Lie on your back with both legs extended straight. If your lower back cannot rest flat on the floor without effort, and if pulling one knee to your chest causes the opposite leg to lift off the floor, both patterns suggest psoas restriction. The specific test is called the modified Thomas test in clinical practice, and it is one of the standard clinical screens for iliopsoas tightness.
  • What normal versus restricted feels like: A healthy psoas allows the leg to swing freely behind the body during walking, allows the lower back to rest flat when lying down, and does not restrict deep breathing. When these functional patterns are absent, the psoas is a reasonable suspect.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Does Research Show About Psoas Function?

The clinical and research literature on the psoas has grown substantially over the last two decades. The current picture supports targeted psoas work as an effective intervention for a specific cluster of common midlife issues.

Research findings on psoas function and recovery.
  • The prevalence question: Studies of chronic low back pain populations consistently find high rates of iliopsoas restriction. Some estimates suggest that a significant portion of chronic non-specific low back pain has an iliopsoas contribution that is often overlooked in initial diagnostic workups.
  • The postural connection: Research on anterior pelvic tilt and lumbar hyperlordosis consistently identifies psoas tightness as one of the major contributing factors. Correcting the psoas restriction, along with addressing weak glutes and abdominal muscles, is one of the standard components of postural correction protocols.
  • The sitting connection: Multiple studies have documented that prolonged sitting produces measurable shortening of the hip flexors and reduced hip extension range of motion. The magnitude of the effect increases with cumulative sitting time.
  • The autonomic nervous system connection: The connection between the psoas and the sympathetic nervous system has support in both clinical practice and emerging research. Body-based therapies for trauma, including somatic experiencing and other trauma-informed movement practices, often specifically address the psoas as part of nervous system regulation.
  • The breath connection: The fascial and functional connections between the diaphragm and the psoas have been documented in anatomical research. Combined breath-and-movement approaches to psoas release consistently show better outcomes than pure stretching approaches.
  • The recovery timeline: Research on stretch-induced changes in muscle length suggests that meaningful changes in psoas resting length require regular daily practice for several weeks. Acute changes after a single session are largely neurological (reduced protective tension) rather than structural (actual tissue lengthening). Both matter, but the structural change requires the consistent time investment.

The overall picture supports targeted daily psoas release practice as an effective intervention for the specific cluster of restricted-psoas symptoms, with meaningful subjective and functional improvements typically appearing within two to four weeks of consistent practice.

What Should You Know Before Starting?

Several principles apply to all five exercises in this article and are worth internalizing before beginning.

  • Breath is not optional: Every psoas release exercise is significantly more effective when combined with slow, deep, diaphragmatic breathing. Do not hold your breath during any of these practices. Extended exhalation in particular helps the muscle release.
  • Slow is the direction: The psoas responds to sustained, gentle release rather than to forceful stretching. Never force any of these positions. Ease into each exercise and hold it for the recommended duration.
  • Comfort matters: Use props (pillows, folded blankets, a yoga bolster) generously. If a position produces pain or forcing, modify it. The whole point of psoas release is to signal safety to a muscle that is chronically contracted from stress and holding.
  • Consistency beats intensity: Ten minutes a day for two weeks produces more psoas release than one 45-minute session per week. Build a daily practice you can sustain.
  • Never stretch into pain: Any sharp pain, radiating pain, or pain in the low back is a signal to stop. Discomfort at the front of the hip during a stretch is normal. Pain in the lower back is not.
  • Warm up briefly: Two or three minutes of gentle walking or hip circles before the practice makes the release more effective. Cold psoas releases less than warm psoas.
  • Equipment needed: A yoga mat or comfortable surface, a folded blanket or small pillow, and a therapy ball or tennis ball for Exercise 4. Total investment under $30 for everything.
  • Time of day: Psoas release can be practiced any time. Morning practice supports the day. Evening practice supports sleep. Middle-of-the-day practice interrupts the sitting accumulation.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Are the 5 Best Psoas Release Exercises?

These five psoas release exercises combine passive relaxation, gentle stretching, targeted pressure, and functional movement to reduce deep hip tension and improve mobility. The sequence begins with the accessible Constructive Rest Position before progressing to more active techniques, allowing you to choose the exercises that match your comfort level, flexibility, and daily routine.

Five psoas release exercises for hip mobility.

Exercise 1: Constructive Rest Position (The Foundation)

The Constructive Rest Position is the foundational psoas release. It looks like doing nothing. It is one of the most effective single interventions available for chronic psoas restriction because it allows the muscle to release passively without any active stretching that could trigger a protective response.

  • How it works: When you lie on your back with your knees bent and your feet flat, the psoas is placed in its shortest and most rested position. The nervous system reads this as safety, and the muscle gradually releases its chronic protective tension. Combined with slow diaphragmatic breathing, the effect is significantly amplified.
  • Setup: Lie on your back on a comfortable surface. Bend both knees and place the feet flat on the floor, roughly hip-width apart. Your knees can either rest against each other or against opposite thighs if you want extra support. Rest your hands on your belly or beside your body. Use a small folded blanket under your head if your neck feels strained.
  • Execution: Once in position, focus on slow diaphragmatic breathing. Feel your belly rise on the inhale and soften on the exhale. Extend the exhalation slightly longer than the inhalation. Rest in the position for eight to twenty minutes. The longer, the better, up to about twenty minutes.
  • Common mistakes: Rushing the practice by cutting the duration short. Holding tension in the shoulders, jaw, or belly during the position. Falling asleep is fine and does not undermine the practice.
  • Why this exercise for midlife women: Constructive Rest Position is safe for almost every midlife body, requires no equipment, produces significant subjective release, and functions equally well as a nervous system reset. It is the single most accessible and most effective psoas practice for women who have not done this work before.
  • Modification for lower back pain: Place a small folded blanket under the hips if the lower back feels strained. This slight elevation reduces any pull on the lumbar spine.

Exercise 2: Half-Kneeling Hip Flexor Stretch

The Half-Kneeling Hip Flexor Stretch is one of the most effective active stretches for the psoas. It isolates the hip flexor of the back leg while stabilizing the pelvis, which allows for direct targeted lengthening of the psoas without recruiting compensatory movements.

  • How it works: The half-kneeling position places the hip of the back leg into extension, which lengthens the psoas. The forward pelvic tilt cue (tuck the tailbone slightly) increases the stretch specifically at the psoas rather than at the front of the thigh.
  • Setup: Start on all fours. Bring the right foot forward into a lunge position with the right knee directly over the right ankle. The left knee remains on the floor with the top of the left foot flat. Use a folded blanket or pillow under the back knee for comfort.
  • Execution: Tuck the tailbone slightly under (posterior pelvic tilt). Engage the glute of the back leg gently. You should feel a stretch in the front of the left hip and thigh. Hold for 60 to 90 seconds while breathing slowly. Switch sides.
  • Sets and reps: 2 to 3 rounds per side.
  • Common mistakes: Failing to tuck the tailbone (which shifts the stretch away from the psoas and into the quadriceps), leaning too far forward (which reduces the stretch), holding tension in the shoulders, holding the breath.
  • Why this exercise for midlife women: This stretch produces one of the most reliable subjective releases at the psoas specifically. Most women feel a distinct pull deep in the front of the hip that they can identify as the target muscle. Regular practice produces measurable improvements in hip extension range of motion within two to three weeks.
  • Progression: Add an overhead reach with the same-side arm as the back leg (right arm up when the right leg is back) to deepen the stretch through the fascial line. Advanced practitioners can also add a slight side bend away from the back leg for additional length through the quadratus lumborum.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Exercise 3: Low Lunge With Side Bend

The Low Lunge With Side Bend (called Anjaneyasana with a lateral variation in yoga) opens the psoas along with the entire front fascial line, addressing the psoas within its functional context rather than in isolation.

  • How it works: The deep low lunge position places the back-leg hip into significant extension while allowing the pelvis to sink downward. The side bend adds an oblique stretch through the quadratus lumborum and the side fascial line, which shares connections with the psoas.
  • Setup: Start on all fours. Bring the right foot forward between your hands. Lower the left knee to the floor and slide the left leg back until the front of the left thigh is on or close to the floor. Place a folded blanket under the back knee for comfort. Sink the hips forward and down.
  • Execution: Bring the arms overhead in a shape you can hold, hands together or apart. Take one full breath in the neutral position. On an exhalation, bend gently to the right (toward the front leg side), reaching the left arm up and over. Hold for 30 to 45 seconds. Return to center. Repeat on the other side by bending toward the left, reaching the right arm up and over. Hold for another 30 to 45 seconds. Come to standing. Switch legs and repeat the whole sequence.
  • Sets and reps: 2 rounds per side (each round includes both side bends).
  • Common mistakes: Collapsing into the low back rather than lengthening the spine, bending too far and losing the psoas stretch, holding the breath, letting the back knee slide out of alignment.
  • Why this exercise for midlife women: This variation opens the psoas along with the quadratus lumborum and the lateral fascial line, addressing multiple restricted areas at once. Most midlife women feel a strong stretch through the deep hip and side body that continues to release with each breath.
  • Modification for tight hips: If the low lunge position is too intense, keep the back knee more elevated by not sliding the back leg as far back. Reduce the depth of the side bend.

Exercise 4: Supine Psoas Release With a Ball

The Supine Psoas Release with a Ball uses gentle mechanical pressure on the muscle to produce release through the myofascial system. This is a more targeted intervention than pure stretching and can produce dramatic subjective release, particularly for stubbornly restricted psoas.

  • Safety note: This exercise applies pressure to an area that sits close to the abdominal organs and major blood vessels. It should always be gentle. Never apply hard pressure. Anyone with abdominal aortic issues, hernia, pregnancy, recent abdominal surgery, or any acute abdominal condition should skip this exercise entirely.
  • How it works: Gentle sustained pressure on the belly of the psoas muscle produces a release response through the myofascial system and the local nervous system. The prone position uses body weight to provide the pressure without requiring active work.
  • Setup: You need a therapy ball, tennis ball, or lacrosse ball. Softer balls are better for beginners. A rolled-up towel is a good alternative if a ball is too intense.
  • Execution: Lie face down on a comfortable surface. Place the ball on the floor and position it approximately two inches to the right of your belly button, just below the level of your navel. Slowly lower your body onto the ball. Support some weight with your arms. Do not put full body weight onto the ball. Breathe deeply into the belly. Hold the position for 60 to 90 seconds. Come off the ball slowly. Switch to the other side.
  • Sets and reps: 1 or 2 rounds per side.
  • Common mistakes: Using too hard a ball, applying too much pressure, holding the breath, placing the ball too close to the belly button (which puts pressure on the aorta) or too far to the side (which misses the muscle).
  • Why this exercise for midlife women: This is the most targeted psoas intervention in the sequence and often produces the most dramatic subjective release when done correctly. Many women feel a distinct softening in the deep hip and a noticeable improvement in low back tension immediately after this practice.
  • Modification: If prone position is uncomfortable, this can be done seated leaning forward onto a ball placed at the desk. The pressure is less but the mechanism is similar.
  • When to skip this exercise: Pregnancy, hernia, recent abdominal surgery, known abdominal aortic aneurysm, active abdominal pain, or any acute concern about the abdominal area. When in doubt, skip this exercise and rely on the other four.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Exercise 5: Standing Psoas Stretch With Countertop Support

The Standing Psoas Stretch is the functional integration exercise for the series. It addresses the psoas in an upright position, which is closer to how the muscle is used in real-life movement, and it can be done during a work break in less than five minutes.

  • How it works: The standing position with the back leg extended places the psoas into a functional lengthened position while the upright torso remains available for breath and posture work. The countertop support provides balance so the muscle can release without the body needing to hold tension for balance.
  • Setup: Stand facing a countertop, sturdy chair back, or wall. Place both hands lightly on the surface for balance.
  • Execution: Step the right foot forward into a mini-lunge, keeping the right knee slightly bent. Extend the left leg straight back with the left foot flat on the floor, heel down. Tuck the tailbone slightly. Engage the left glute. Lean slightly forward from the front hip while keeping the torso upright. Hold for 60 to 90 seconds while breathing deeply. Switch legs.
  • Sets and reps: 2 rounds per side.
  • Common mistakes: Allowing the back heel to lift off the floor (which reduces the psoas stretch), collapsing the low back, holding tension in the shoulders, forgetting to engage the glute of the back leg.
  • Why this exercise for midlife women: This is the exercise that most easily fits into a daily work life because it can be done at any countertop or desk. Practicing it as a two-minute break every couple of hours throughout the day interrupts the sitting-driven psoas shortening pattern in real time.
  • Progression: Add an overhead reach with the same-side arm as the back leg. Add a slight forward lean while keeping the tailbone tucked to intensify the stretch.

How Does the 5-Day Psoas Release Program Work?

The five exercises above form the core of the release practice. The 5-day program combines them into a structured progressive sequence designed to produce meaningful psoas release within one week. Total time commitment per day ranges from 15 to 25 minutes.

Day 1: Foundation (15 minutes)

The first day establishes the foundation with the most accessible practice.

Exercise

Duration

Warm-up (walk in place, gentle hip circles)

3 min

Constructive Rest Position with deep breathing

12 min


Day 1 is deliberately simple. The purpose is to allow the nervous system to begin releasing chronic protective tension in the psoas without introducing any active stretching that might produce a protective response.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Day 2: Add Active Stretch (20 minutes)

The second day adds the first active stretch and adds a short repeat of the foundation.

Exercise

Duration

Warm-up

3 min

Constructive Rest Position

8 min

Half-Kneeling Hip Flexor Stretch, both sides

6 min

Constructive Rest Position (close)

3 min

Day 3: Add Dynamic Release (22 minutes)

The third day adds the low lunge for a deeper functional stretch.

Exercise

Duration

Warm-up

3 min

Constructive Rest Position

6 min

Half-Kneeling Hip Flexor Stretch, both sides

5 min

Low Lunge with Side Bend, both sides

6 min

Constructive Rest Position (close)

2 min

Day 4: Add Myofascial Work (25 minutes)

The fourth day adds the targeted myofascial release, which often produces the most dramatic single-day change in the week.

Exercise

Duration

Warm-up

3 min

Constructive Rest Position

5 min

Half-Kneeling Hip Flexor Stretch, both sides

5 min

Low Lunge with Side Bend, both sides

5 min

Supine Psoas Release with Ball, both sides

5 min

Constructive Rest Position (close)

2 min

Day 5: Full Integration (25 minutes)

The fifth day integrates all five exercises into the complete sequence.

Exercise

Duration

Warm-up

3 min

Constructive Rest Position

4 min

Half-Kneeling Hip Flexor Stretch, both sides

5 min

Low Lunge with Side Bend, both sides

5 min

Supine Psoas Release with Ball, both sides

5 min

Standing Psoas Stretch with Countertop, both sides

3 min

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Should You Do After the 5-Day Program?

The first five days establish the pattern. From day six forward, the most effective practice is a shorter daily sequence of Constructive Rest Position (5 to 8 minutes) plus one or two active stretches (5 to 8 minutes), totaling 10 to 15 minutes daily. Once a week, repeat the full Day 5 sequence for a deeper integration. This maintenance practice produces sustained psoas health and prevents the return of chronic restriction.

Expected timeline for results. Subjective release is often noticeable within the first two or three sessions. Meaningful reductions in low back tension and improvements in hip mobility generally appear within two to three weeks of consistent practice. Postural changes and deeper structural release develop over two to three months.

“The pattern I have seen with hundreds of retreat guests and coaching clients is that the 5-day program produces enough felt change by day three or four that the practice starts to earn its own place in the daily routine. The women who follow through beyond the first week almost always continue for months and years because the felt benefit of a released psoas is so distinct and so different from what most midlife women have been carrying without realizing it. The chronic bracing pattern of a shortened psoas is invisible until you release it. Once you release it, you cannot unfeel the difference. That felt-sense change is what makes the practice sustainable in a way that most fitness programs are not.”

Terry Tateossian, Founder of The House of Rose

Which Mistakes Can Undermine Psoas Release?

Six mistakes consistently reduce the effectiveness of psoas release practice for midlife women.

Common psoas release mistakes to avoid.
  • Forcing the stretch: The psoas responds to sustained gentle pressure, not to forceful stretching. Trying to muscle through the release produces a protective response that undermines the intent.
  • Holding the breath: Breath is one of the most powerful tools for psoas release, and breath holding reliably reduces the effectiveness of every exercise in the sequence. Practice extended exhalation throughout.
  • Skipping the Constructive Rest Position: The foundation exercise looks unimpressive, and many practitioners want to skip straight to the active stretches. This is a mistake. The Constructive Rest Position signals safety to a chronically contracted muscle in a way that active stretching cannot replicate. Do not skip it.
  • Practicing inconsistently: The psoas has adapted to its short position over years or decades. Reversing that adaptation requires consistent daily practice for weeks. Sporadic practice produces sporadic results.
  • Rushing individual holds: The recommended hold durations (60 to 90 seconds for stretches, 8 to 20 minutes for Constructive Rest) are based on the time needed for the muscle to release. Cutting the holds short produces smaller effects.
  • Applying too much pressure with the ball: The Supine Psoas Release is a gentle intervention. Too much pressure produces muscle guarding and reduces the release, which is the opposite of what you want.
  • Ignoring the sitting pattern: Even the best release practice is limited if you return to eight hours of continuous sitting immediately after. Break up the sitting throughout the day with the standing psoas stretch or brief walks. The micro walks article covers the everyday-movement layer.

How Does Psoas Release Fit the THOR Framework?

Psoas release is one component of the broader movement and lifestyle medicine framework I teach at THOR. It amplifies and is amplified by the rest of the system.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

When Should You See a Healthcare Professional?

Most midlife women can safely complete the 5-day program on their own. Some situations require professional evaluation first.

  • Acute low back pain: Any acute or severe back pain should be evaluated by a healthcare provider before starting a new movement program.
  • Radiating pain down the leg: Radiating pain, numbness, or tingling suggests possible nerve involvement and needs evaluation before starting movement work.
  • History of significant back or hip surgery: Prior spinal fusion, hip replacement, or other significant surgery may require modification.
  • Pregnancy: Some of the exercises need modification during pregnancy. Skip the ball release entirely. Work with a prenatal-certified practitioner for individualized guidance.
  • Pelvic organ prolapse: Anyone with prolapse should work with a pelvic floor physical therapist before beginning targeted psoas work.
  • Hernia: Skip the Supine Psoas Release with Ball. The other exercises are generally safe but should be discussed with your provider.
  • Abdominal aortic issues: Do not do the Supine Psoas Release with Ball. Discuss the other exercises with your provider.
  • Persistent tightness despite practice: If eight to twelve weeks of consistent practice has not produced meaningful improvement, consider working with a physical therapist or manual therapist for individualized assessment and treatment.

What Are Your Next Steps?

If the framework in this article resonates and you want to release chronic psoas tension, here are the four next steps in order of friction.

  1. Start today with Day 1 of the program. All you need is a comfortable surface, about fifteen minutes, and a willingness to lie down in Constructive Rest Position with deep breathing. No equipment, no preparation, no perfect conditions required.
  2. Complete the full 5-day program this week. Follow the daily protocols in section 11. Track how your body feels each day.
  3. Continue with the maintenance practice. After day five, keep the daily 10 to 15 minute maintenance practice going. Repeat the full Day 5 sequence once a week.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

What causes a tight psoas in women over 40?

Tight psoas in women over 40 is driven by decades of prolonged sitting, chronic stress and cortisol elevation, hormonal changes in fascia and connective tissue, sleep disruption that prevents nightly repair, pelvic floor changes, reduced overall movement, and often a history of traditional core work that overtrained the psoas. Most midlife women experience multiple of these factors simultaneously.

How do I know if my psoas is tight?

Common signs include chronic low back pain particularly in the lumbar area, deep hip tension that does not resolve with standard hip stretches, an anterior pelvic tilt (arched lower back when standing), tightness in the front of the hip when climbing stairs, restricted breath depth on the inhale, and difficulty fully extending the hip behind the body. The modified Thomas test (lying on your back with both legs straight and observing whether the lower back can rest flat) is a simple self-screen.

How long does it take to release a tight psoas?

Subjective release is often noticeable within the first two or three sessions. Meaningful reductions in low back tension and improvements in hip mobility generally appear within two to three weeks of consistent daily practice. Postural changes and deeper structural release develop over two to three months. The 5-day program in this article produces meaningful initial change within one week.

Can I release my psoas without a ball or equipment?

Yes, the first three exercises in this article (Constructive Rest Position, Half-Kneeling Hip Flexor Stretch, Low Lunge with Side Bend) require no equipment other than a comfortable surface. Together these three produce significant psoas release. The ball release adds a targeted layer, but it is not essential for meaningful progress.

Is psoas release safe during pregnancy?

Some psoas exercises need modification during pregnancy, and one exercise should be skipped entirely. Skip the Supine Psoas Release with Ball entirely. The Constructive Rest Position, Half-Kneeling Hip Flexor Stretch, and Standing Psoas Stretch are generally safe with modification. Work with a prenatal-certified practitioner or physical therapist for individualized guidance.

Can tight psoas cause low back pain?

Yes, tight psoas is one of the most common invisible contributors to chronic low back pain in midlife women. When the psoas is short, it pulls the lumbar spine forward and creates an exaggerated arch that can produce chronic tension and pain in the low back. Releasing the psoas often resolves back pain that has not responded to other interventions.

Should I stretch my psoas every day?

Yes, daily practice is significantly more effective than occasional longer sessions because the psoas has adapted to its short position over years, and reversing that adaptation requires consistent daily signaling. Ten to fifteen minutes of daily practice produces better results than an hour once a week.

What is the best time of day to release the psoas?

Any time of day works. Morning practice supports posture and mobility throughout the day. Evening practice supports sleep by releasing accumulated tension. Middle-of-the-day practice interrupts the sitting-driven shortening pattern in real time. Choose the time that produces the highest adherence for you.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Does yoga help with tight psoas?

Yes, yoga includes many postures that specifically address the psoas, including low lunge (Anjaneyasana), lizard pose, camel pose, and bridge pose. A dedicated yin yoga or restorative yoga practice is particularly effective. The five yin yoga poses article covers a specific home practice sequence. The retreat at our Smoky Mountains property includes daily yoga programming specifically for this purpose.

Can tight psoas affect breathing?

Yes, the psoas shares fascial connections with the diaphragm, and a tight psoas can restrict the depth of the inhale. Many women notice that their breath becomes deeper and easier after consistent psoas release practice. This bidirectional connection is why combined breath-and-movement approaches produce better results than pure stretching.

Is the ball release safe for everyone?

No, the Supine Psoas Release with Ball should be skipped by anyone who is pregnant, has a hernia, has had recent abdominal surgery, has a known abdominal aortic aneurysm, has active abdominal pain, or has any acute abdominal concern. When in doubt, skip this exercise and rely on the other four.

Can psoas tightness cause hip pain?

Yes, tight psoas can produce deep hip tension, restricted hip range of motion, and discomfort or pinching in the front of the hip during activities like squatting or climbing stairs. Releasing the psoas often resolves hip tension that had been attributed to other causes.

What if I only have five minutes?

If you only have five minutes, do the Constructive Rest Position with deep breathing. This is the single highest-impact exercise per minute in the sequence and produces meaningful release even in short sessions. Any minute spent in this position is a minute the psoas has to release.

Can psoas release help with digestion?

Some women report improvements in digestion after consistent psoas release practice. The mechanism is likely related to the reduction of chronic tension in the abdominal region and possibly to improvements in vagal tone through the sympathetic-nervous-system connection with the psoas. This is anecdotal rather than well-studied, but the reports are consistent enough to be worth noting.

Should I combine psoas release with strength training?

Yes, and the combination is more effective than either alone. Psoas release addresses the restriction. Strength training addresses the strength and stability of the muscles that support the pelvis and spine. Together they produce better and more sustainable results than either alone. The four muscle groups for aging well article and the standing ab exercises article cover the strength training pieces that complement psoas release.

References

  • Sajko, S., & Stuber, K. (2009). Psoas major: a case report and review of its anatomy, biomechanics, and clinical implications. Journal of the Canadian Chiropractic Association, 53(4), 311–318.
  • Bordoni, B., & Varacallo, M. (2023). Anatomy, abdomen and pelvis: iliopsoas muscle. StatPearls, StatPearls Publishing.
  • Konrad, A., Močnik, R., & Titze, S. (2019). The influence of stretching on the position of the pelvis and the trunk. International Journal of Environmental Research and Public Health, 16(21), 4266.
  • Hu, H., Meijer, O. G., van Dieën, J. H., et al. (2011). Understanding the active straight leg raise: an electromyographic study of pelvic and lower limb muscle recruitment patterns. Manual Therapy, 16(4), 401–406.
  • Kim, D. H., Kim, C. J., & Son, S. M. (2018). Neck pain in adults with forward head posture: effects of craniovertebral angle and cervical range of motion. Osong Public Health and Research Perspectives, 9(6), 309–313.
  • Nourbakhsh, M. R., & Arab, A. M. (2002). Relationship between mechanical factors and incidence of low back pain. Journal of Orthopaedic and Sports Physical Therapy, 32(9), 447–460.
  • Mills, M., Frank, B., Goto, S., et al. (2015). Effect of restricted hip flexor muscle length on hip extensor muscle activity and lower extremity biomechanics in college-aged female soccer players. International Journal of Sports Physical Therapy, 10(7), 946–954.
  • Winters, M. V., Blake, C. G., Trost, J. S., et al. (2004). Passive versus active stretching of hip flexor muscles in subjects with limited hip extension: a randomized clinical trial. Physical Therapy, 84(9), 800–807.
  • Kim, K., & Yoo, W. G. (2015). The effects of self-myofascial release exercise on the muscle activity of tibialis anterior. Journal of Physical Therapy Science, 27(9), 2933–2934.
  • Beardsley, C., & Škarabot, J. (2015). Effects of self-myofascial release: a systematic review. Journal of Bodywork and Movement Therapies, 19(4), 747–758.
  • Behm, D. G., & Wilke, J. (2019). Do self-myofascial release devices release myofascia? Rolling mechanisms: a narrative review. Sports Medicine, 49(8), 1173–1181.
  • Streeter, C. C., Gerbarg, P. L., Saper, R. B., et al. (2012). Effects of yoga on the autonomic nervous system, gamma-aminobutyric-acid, and allostasis in epilepsy, depression, and post-traumatic stress disorder. Medical Hypotheses, 78(5), 571–579.
  • Bordoni, B., & Zanier, E. (2013). Anatomic connections of the diaphragm: influence of respiration on the body system. Journal of Multidisciplinary Healthcare, 6, 281–291.
  • Vleeming, A., Schuenke, M. D., Danneels, L., & Willard, F. H. (2014). The functional coupling of the deep abdominal and paraspinal muscles: the effects of simulated paraspinal muscle contraction on force transfer to the middle and posterior layer of the thoracolumbar fascia. Journal of Anatomy, 225(4), 447–462.
  • Falla, D., & Hodges, P. W. (2017). Individualized exercise interventions for spinal pain. Exercise and Sport Sciences Reviews, 45(2), 105–115.
  • Woolery, A., Myers, H., Sternlieb, B., & Zeltzer, L. (2004). A yoga intervention for young adults with elevated symptoms of depression. Alternative Therapies in Health and Medicine, 10(2), 60–63.
  • Sherman, K. J., Cherkin, D. C., Wellman, R. D., et al. (2011). A randomized trial comparing yoga, stretching, and a self-care book for chronic low back pain. Archives of Internal Medicine, 171(22), 2019–2026.
  • Chang, D. G., Holt, J. A., Sklar, M., & Groessl, E. J. (2016). Yoga as a treatment for chronic low back pain: a systematic review of the literature. Journal of Orthopedics and Rheumatology, 3(1), 1–8.

Disclaimer: Always consult with a healthcare professional before starting any new routines, programs, or nutrition plans to ensure you receive the best medical advice and strategy for your specific individual needs.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Get 11 Free Macro-Friendly Sample Recipes

Download 11 macro-friendly sample recipes from our cookbook that will give you everything you need to start eating like a woman who’s done with the guesswork.

Emotional Eating in Perimenopause and Menopause: The Complete Guide to Breaking the Cycle

Emotional eating in perimenopause and menopause is one of the most common and misunderstood experiences in midlife women’s health. It may look like an evening pantry visit, reaching for sugar after a stressful call, or turning a small snack into dinner. This pattern is not a moral failure or lack of discipline. It is often the predictable response of a hormonally shifting, sleep-disrupted, stress-loaded nervous system.

I built The House of Rose after experiencing early-onset menopause at 41, an 80-pound body composition shift, and the demands of running businesses while raising two children. Emotional eating was one of the hardest patterns I had to work through. The framework in this article is not a diet or another set of rigid rules. It is a practical system for understanding the real drivers behind the behavior and addressing them directly.

This guide explains why emotional eating can intensify during perimenopause and menopause, how stress and brain chemistry affect cravings, and which evidence-based interventions support lasting change. Every principle is one I use in coaching and with retreat guests.

Important: Emotional eating is different from clinical eating disorders such as binge eating disorder, bulimia, and anorexia nervosa. If you are experiencing symptoms of an eating disorder, work with a qualified specialist rather than relying on this guide alone.

What Is Emotional Eating?

Emotional eating is the use of food to soothe, distract, numb, or regulate feelings that are not hunger. That is the entire definition. The specific feelings vary from woman to woman and from day to day, but the pattern is consistent: an internal state that is uncomfortable, a decision to reach for food that is not physically needed, a temporary reduction in the intensity of the uncomfortable state, and then a return of that state along with additional feelings that often include shame, self-criticism, and a sense of powerlessness.

Emotional eating triggers, cycle, and warning signs.
  • The specific feelings that most often drive it: Stress is the most common single driver. Anxiety, loneliness, boredom, sadness, frustration, resentment, overwhelm, disappointment, and low-grade daily grief are all common. The pattern is often triggered less by acute distress than by a background sense of being asked to hold too much for too long without adequate support, which is a state most midlife women recognize.
  • Why food specifically: Food is available, socially acceptable, quick to access, and produces a real short-term shift in brain chemistry. Carbohydrates and sugar cause a rapid rise in blood glucose and trigger serotonin production, which produces a short window of felt calm. Fat and salt produce a dopamine response. The brain files this away and returns to the pattern under future stress. Over time, food becomes the primary self-soothing tool for many women, particularly women who were taught in childhood to suppress emotions and who have therefore never developed a wider toolkit of emotional regulation.
  • Why this is not weakness: Emotional eating is a coping strategy that once worked. It is often the strategy that got a young girl through a difficult family situation, a stressful school environment, a lonely period, or a hard relationship. The brain remembered that food helped, and now it reaches for food any time the internal state feels uncomfortable. This is not a character defect. It is the predictable result of an efficient learning brain that once found a working solution and returns to it under similar conditions.
  • How it becomes a problem: Occasional emotional eating is part of being human. It becomes a problem when it becomes the primary or only tool for regulating uncomfortable feelings, when it consistently pushes food intake above the body’s actual needs, when it drives the food choice pattern toward high-sugar and high-fat foods that undermine metabolic health, and when it produces the shame-and-secrecy loop that damages self-trust and body relationship.

Get 11 Free Macro-Friendly Sample Recipes

Download 11 macro-friendly sample recipes from our cookbook that will give you everything you need to start eating like a woman who’s done with the guesswork.

Why Does Emotional Eating Intensify in Perimenopause and Menopause?

Emotional eating is not new for most women in midlife. What is new for many is that a pattern they had managed reasonably well in their thirties suddenly becomes harder to manage in their forties and fifties. Several distinct threads converge in this window.

  • Estrogen decline changes brain chemistry: Estrogen has a supportive relationship with serotonin, dopamine, and other neurotransmitters that regulate mood and reward. As estrogen falls through perimenopause and menopause, mood regulation becomes harder for many women, background anxiety often rises, and the brain looks for external sources of the neurochemical support that it used to receive internally. Sugar and simple carbohydrates provide exactly that short-term neurochemical support, which is why cravings for these foods intensify.
  • Cortisol rhythm dysregulation: The cortisol curve tends to shift in midlife, often producing higher evening cortisol and blunted morning cortisol. High evening cortisol drives evening cravings, which is why so many women recognize the six-to-nine PM pantry pattern as the peak emotional eating window. This is not a coincidence. It is a specific hormonal driver.
  • Sleep disruption compounds everything: Poor sleep the night before produces elevated ghrelin (the hunger hormone), reduced leptin (the fullness hormone), and impaired prefrontal cortex function, which is the part of the brain responsible for impulse control and decision-making. The result is that after a poor night of sleep, hunger feels louder, fullness feels quieter, and the brain has less ability to override the pull toward comfort food. Multiple studies have documented this pattern in detail.
  • The life-load intensifies: Perimenopause typically arrives during the years when careers are at maximum demand, children are teenagers or launching, aging parents may be requiring support, and financial responsibility is at peak load. The nervous system is being asked to hold more with fewer buffers than it had a decade earlier.
  • Body composition shifts produce more shame: The redistribution of body fat toward the abdomen during menopause, along with the general weight gain that many women experience without any change in habits, produces a specific psychological load that often drives more restrictive dieting, which then produces more binge cycling, which then produces more emotional eating. The cycle self-reinforces if it is not addressed at the level of the drivers.
  • Alcohol tolerance declines: Many women drink more socially in their forties and fifties than they did in earlier decades, and metabolism of alcohol declines simultaneously. Alcohol lowers prefrontal control and directly drives evening eating patterns.

The overall picture is that perimenopause and menopause are not merely a passive backdrop against which emotional eating happens to worsen. They are active drivers of the pattern through specific neurochemical and hormonal mechanisms.

“The single biggest shift in my own recovery from emotional eating was the moment I understood that this was not a character issue and it was not a moral issue. It was a neurochemical issue that was being amplified by my hormonal transition and my cortisol dysregulation and my sleep debt and my life load. Once I saw that clearly, the shame started to fall away, and the space that the shame had been occupying became available for actual repair. That is the shift I want every coaching client and retreat guest to have. You are not broken. You are not weak. You are a hormonally shifting midlife woman whose nervous system is asking for a different set of tools than the ones you were given. This article is those tools.”

Terry Tateossian, Founder of The House of Rose

What Happens in Your Brain During a Stress Craving?

Understanding what actually happens neurochemically during a craving is one of the most useful pieces of the recovery framework. It replaces the mystified sense of being pulled by an unknown force with a clear picture of specific biological signals that can be identified and worked with.

  • The initial trigger: A trigger enters awareness. This can be a stressful email, a critical comment, an unresolved conflict, a wave of loneliness, a moment of boredom, a difficult conversation, a physical sensation, or a memory. The trigger produces a small activation of the sympathetic nervous system and a release of stress hormones.
  • The amygdala responds: The amygdala (the brain region that handles threat detection) processes the trigger as a survival signal and pushes for action. In an ancestral environment, that action would have been fight or flight. In modern life, the action is often to reach for food, which is one of the few available and socially acceptable responses to acute stress.
  • Cortisol and craving pathways activate: The stress response elevates cortisol, which increases appetite specifically for high-fat and high-sugar foods. This is not a psychological preference. It is a hardwired biological pathway. Cortisol activates specific brain regions that increase reward-value assignment to calorie-dense foods.
  • The prefrontal cortex loses power: Under stress and low blood sugar and sleep debt, the prefrontal cortex (the impulse control and decision-making region) becomes less able to override the reward pull. The brain is now in a state where the pull toward food is amplified and the ability to resist it is reduced.
  • The food produces a short-term neurochemical hit: Sugar and simple carbs produce a serotonin release and a dopamine hit. Fat produces additional dopamine. The stress state reduces temporarily. The nervous system files this away as a successful stress-management strategy.
  • The rebound arrives: Within 30 to 90 minutes, blood sugar crashes, cortisol rebounds, the original emotional state returns, and shame and self-criticism arrive. The nervous system is now in a worse state than before the craving started, and often the response is another round of eating.

Understanding this sequence changes everything. Every intervention in this article addresses a specific part of this sequence rather than trying to muscle through the pull with willpower after it has already peaked.

Get 11 Free Macro-Friendly Sample Recipes

Download 11 macro-friendly sample recipes from our cookbook that will give you everything you need to start eating like a woman who’s done with the guesswork.

How Does the Cortisol-Sugar-Belly Fat Loop Work?

The specific relationship between stress, cortisol, sugar cravings, and menopause belly fat is one of the most important pieces to understand because it explains why midlife emotional eating produces such visible body composition changes.

Cortisol, sugar cravings, belly fat, and sleep cycle infographic.
  • Chronic stress elevates cortisol: Life-load, poor sleep, restrictive dieting, and unaddressed nervous system dysregulation all keep cortisol chronically elevated.
  • Elevated cortisol drives sugar cravings: This is the specific biological pathway described in the previous section.
  • Sugar and simple carbs drive belly fat storage: The specific fat distribution pattern of midlife women (increasing abdominal fat) is partly driven by the metabolic effects of chronic high insulin from repeated blood sugar spikes and the effect of cortisol on adipose tissue distribution.
  • Belly fat produces its own inflammation: Visceral abdominal fat is metabolically active and produces inflammatory signals that further elevate cortisol and disrupt sleep.
  • The disrupted sleep feeds back into the pattern: Poor sleep raises cortisol further, worsens insulin sensitivity, increases hunger hormone signaling, and reduces impulse control.

This is why isolated interventions like willpower-based dieting rarely work in midlife. The system is a loop, and it needs to be interrupted at multiple points simultaneously. See the cortisol and menopause weight gain article for a deeper dive into this specific pathway.

How Can You Tell Emotional Hunger From Physical Hunger?

One of the most useful practical skills in emotional eating recovery is learning to distinguish physical hunger from emotional hunger. They feel different once you know what to look for.

  • Physical hunger builds gradually: Physical hunger tends to appear slowly, build over 30 minutes to a few hours, and involve specific physical signals including a rumbling stomach, mild low blood sugar sensations, slight fatigue, and often a mild irritability. Physical hunger is generally open to a range of foods, including foods you might not immediately crave. Physical hunger stops when you are physically full.
  • Emotional hunger arrives suddenly: Emotional hunger tends to appear quickly, feel urgent, and demand a specific food or food type (usually sweet, salty, or high in fat). Emotional hunger does not stop reliably when you are physically full. Emotional hunger is often located in the head or the chest rather than the stomach. Emotional hunger frequently arrives in specific windows (evenings after work, weekend afternoons alone, immediately after difficult conversations, during boring meetings).
  • The three-question check: When you notice a food urge, ask three questions. First, when did I last eat, and how much? Second, would I eat something simple and unglamorous right now (a plain apple, a hard-boiled egg, a plain piece of chicken)? Third, what am I feeling right now? Physical hunger will say yes to the plain food. Emotional hunger will resist plain food and want something specifically comforting.
  • The location check: Physical hunger is felt in the stomach. Emotional hunger is often felt higher (chest, throat) or as a mental itch rather than a stomach signal. Learning to check the location of the urge is a fast diagnostic.
  • Neither is wrong: Emotional hunger is not a bad state. It is a signal that something is happening in the internal life that needs attention. The point is not to shame the emotional hunger. The point is to recognize it accurately so you can respond appropriately, which usually means addressing the emotional signal rather than feeding it with food.

Get 11 Free Macro-Friendly Sample Recipes

Download 11 macro-friendly sample recipes from our cookbook that will give you everything you need to start eating like a woman who’s done with the guesswork.

What Are the Hidden Costs of Emotional Eating?

The obvious cost of an unaddressed emotional eating cycle is weight gain and its metabolic consequences. The less-obvious costs are often larger.

  • Erosion of body trust: Repeated cycles of eating past fullness, ignoring physical hunger cues, and using food as a substitute for other needs damages the fundamental trust between a woman and her body. The body becomes something to be managed rather than partnered with, which makes every subsequent nutrition and movement intervention harder to sustain.
  • Loss of energy and clarity: The blood sugar rollercoaster of emotional eating produces significant swings in energy, mood, and cognitive function that make everything else in life harder.
  • Shame and secrecy: The eating-in-secret pattern that emotional eating often produces is corrosive to self-image and to relationships. Women often describe hiding evidence of a binge as one of the most damaging emotional experiences of the whole cycle.
  • Missed emotional information: Emotional eating substitutes food for the information that emotions are trying to deliver. That information is often about needs, boundaries, or unresolved situations that are not going to resolve on their own. When food is the go-to response, the underlying issue keeps sending louder signals.
  • Compounding metabolic damage: Repeated cycles of high sugar intake, high insulin spikes, and cortisol dysregulation compound over years and produce insulin resistance, visceral fat accumulation, and increased risk for the metabolic diseases that shorten healthy lifespan.
  • The passing of time: Perhaps the largest hidden cost. Every year spent in the cycle is a year not spent building the systems and relationships and body that will support the next thirty or forty years of life.

Which Emotional Eating Strategies Do Not Work?

The pattern of interventions that most women try first is the pattern that most often makes the cycle worse. Understanding what does not work is as important as understanding what does.

  • Restrictive dieting: The most common response to emotional eating is a stricter diet. This almost always makes the cycle worse. Restrictive eating produces hormonal changes (elevated cortisol, elevated ghrelin, reduced leptin) that increase cravings, worsen sleep, and reduce impulse control. It produces psychological effects (scarcity mindset, food obsession, all-or-nothing thinking) that set up the next binge. Nearly every clinical guideline for emotional eating recovery specifically warns against restrictive dieting as an intervention.
  • Willpower: Emotional eating is often framed as a willpower problem, but it is a mismatched frame. Willpower is a limited resource that depletes throughout the day, is heavily reduced by stress and sleep debt, and is not available in useful amounts at the evening peak of emotional eating windows. Trying to solve emotional eating with willpower is asking the least available resource in your system to do the hardest job.
  • Cutting out specific foods: The idea that if only chocolate or wine or bread were removed from the house, the problem would resolve, is almost never correct. The pull is at the emotional level. The specific food is interchangeable. Removing one option produces substitution with another.
  • Rigid rules: Elaborate rule systems around food (no eating after 7 PM, only certain foods on certain days) often produce more emotional eating because the rules themselves become sources of stress and the inevitable rule violations become triggers for the shame-binge cycle.
  • Self-shame: Speaking harshly to yourself after an emotional eating episode reliably makes the next episode more likely. Self-shame elevates cortisol, worsens sleep, and reduces the emotional resources available for healthier coping. This is one of the most important insights in the whole recovery framework.
  • Trying to think your way out: Emotional eating happens at a lower brain level than cognitive analysis can easily reach. Thinking harder about it while continuing to be sleep-deprived, cortisol-dysregulated, and nutrient-depleted does not produce change.
Guide to Emotional Eating Perimenopause

Get 11 Free Macro-Friendly Sample Recipes

Download 11 macro-friendly sample recipes from our cookbook that will give you everything you need to start eating like a woman who’s done with the guesswork.

Which 10 Interventions Help Break Emotional Eating?

These ten interventions are what actually produce sustainable change. They work by addressing the specific drivers of the pattern rather than the surface behavior. Most women do not need all ten to see meaningful change. Choosing three or four that fit your situation and practicing them consistently for eight to twelve weeks typically produces significant improvement.

10 interventions to break emotional eating.

Intervention 1: Stabilize Your Blood Sugar Foundation

The single most impactful intervention for most midlife women is stabilizing the blood sugar curve. When blood sugar is stable, cravings drop dramatically because the biological signal to seek fast carbohydrates goes quiet. The specific practices are eating protein at every meal (roughly 25 to 40 grams), including fiber and healthy fats with every meal, avoiding standalone carbohydrate meals, and not going more than four to five hours between meals during the day.

The free Macro Calculator gives you a personalized protein and macronutrient target. The Macro Miracle Mediterranean Cookbook is the kitchen-side companion with recipes designed around this pattern. See also the menopause diet plan for the full framework.

Intervention 2: Prioritize Sleep as the Meta-Lever

Poor sleep multiplies every other driver of emotional eating. Adequate sleep reduces cortisol, restores ghrelin and leptin balance, improves prefrontal function, and reduces cravings for calorie-dense foods within a single night. Any recovery framework that does not address sleep as a foundation will produce less than half the results of one that does.

The specific practices are consistent bed and wake times, a wind-down routine that starts one hour before sleep, cool dark bedroom, screen restriction after 9 PM, and appropriate use of vagal reset practices from our vagus nerve reset article. The menopause sleep remedies article and the midlife sleep stack article cover the sleep framework in depth.

Intervention 3: Name the Trigger Before the Bite

The practice of pausing between the food urge and the food action long enough to name what is actually happening is one of the most powerful behavior changes available. The practice is simple in structure and hard in execution. When the urge arrives, notice it and do not act on it yet. Ask what am I feeling right now, and answer honestly even if the answer is I do not know. Sit with the not-knowing for two minutes if that is what is available, then make the decision from that steadier ground.

This practice does not eliminate emotional eating episodes overnight. What it does is start to insert space between trigger and action, which over weeks builds the capacity for different choices. Most women see a meaningful reduction in unconscious eating within two to three weeks of consistent practice.

Get 11 Free Macro-Friendly Sample Recipes

Download 11 macro-friendly sample recipes from our cookbook that will give you everything you need to start eating like a woman who’s done with the guesswork.

Intervention 4: The 10-Minute Pause

A specific implementation of the pause is the 10-minute rule. When you notice a food urge that is not physical hunger, set a timer for ten minutes and do something else during that time, whether that is walking around the block, drinking a glass of water, practicing extended exhalation breathing from our vagus nerve reset article, or texting a friend. After the ten minutes, if the urge is still there and you still want the food, eat it. Often, the urge has significantly reduced or disappeared. This is not deprivation. It is inserted space.

Intervention 5: Mindful Eating Practice

Mindful eating is the practice of paying full attention to the sensory experience of eating without distraction, which means no phone, no TV, and no email during the meal. The only two elements present are the food and the body. The specific practices include noticing the color, smell, and temperature of the food, chewing thoroughly, pausing between bites, checking fullness at intervals, and stopping when the body signals satisfaction rather than when the plate is empty.

Mindful eating produces a range of documented benefits including reduced portion sizes without any deliberate restriction, improved digestion, better recognition of hunger and fullness cues, and reduced emotional eating over time. Start with one mindful meal per day and build from there over the following weeks.

Intervention 6: Journaling the Pattern

A simple daily food and mood journal produces remarkable insight over four to six weeks. The practice is to note what you ate, roughly when, what you were feeling right before, and how you felt afterward. The point is not restriction or judgment. The point is data. Within a few weeks, most women see clear patterns: specific triggers, specific time windows, specific foods that show up in emotional eating episodes versus physical hunger episodes.

The simple structure is three lines per meal covering what you ate, what you were feeling before, and what you felt after. Continue for eight weeks and review the log weekly rather than daily. The insight this practice produces is often the biggest single lever for change.

Intervention 7: Nervous System Regulation Practice

Because emotional eating is fundamentally a nervous system regulation problem (the body is asking for regulation and food is the currently available tool), building a wider set of regulation tools directly addresses the driver. Daily practice of extended exhalation breathing, humming, gargling, cold face immersion, and the other exercises in our vagus nerve reset article gives the nervous system access to non-food regulation. Over weeks, the availability of these tools reduces the frequency of food-based regulation.

Intervention 8: Yoga and Body-Based Practice

Yoga combines breath, movement, mindfulness, and body awareness in a way that consistently reduces emotional eating in the research literature. The mechanism is likely multiple: reduced cortisol, improved body awareness, improved emotional regulation, better sleep, and a repaired relationship with the body. See our five yin yoga poses article for a specific home practice sequence.

For deep immersive body-based reset, the Deeply Restorative Yoga and Nature Retreat at our Smoky Mountains property combines daily yoga, guided restorative practice, and the nutrition foundation into a five-day intensive that consistently produces measurable shifts in emotional eating patterns.

Intervention 9: Strength Training and Meaningful Movement

Regular resistance training and daily movement address emotional eating from a different direction. Movement metabolizes stress hormones directly, improves sleep, supports body composition, and produces the felt-sense of embodied capability that reduces the psychological load driving food-seeking. The four muscle groups for aging well article covers the strength training foundation. The micro walks article covers the everyday movement layer.

Intervention 10: Professional Support When Appropriate

Some emotional eating patterns are woven into deeper histories that benefit from professional support. If your pattern feels compulsive, if it involves clinical binge eating (large quantities in short windows with a sense of loss of control), if it involves purging or compensatory behaviors, or if it is tied to significant unresolved trauma, please work with a qualified eating disorder specialist or therapist alongside any lifestyle changes.

For the coaching version of the framework focused on the midlife lifestyle medicine drivers, the Monthly Personal Training and Nutrition Coaching Program is the primary CTA for this article. This is where I work directly with women on installing the full framework over three, six, or twelve months.

Get 11 Free Macro-Friendly Sample Recipes

Download 11 macro-friendly sample recipes from our cookbook that will give you everything you need to start eating like a woman who’s done with the guesswork.

“The two highest-impact interventions from that list of ten, in my experience with hundreds of midlife women, are blood sugar stabilization and the ten-minute pause. If a woman does nothing else from this list except eat 30 grams of protein at breakfast and pause for ten minutes before every food decision that is not on a mealtime, she will see her emotional eating cut in half within two months. That is a real claim from years of coaching data. Everything else in the list amplifies that foundation, and the retreat and coaching work at the higher levels of the framework, but if resources are limited and time is short, start with those two. That is the eighty-twenty answer to emotional eating in midlife.”

Terry Tateossian, Founder of The House of Rose

How Can You Build a Personal Emotional Eating Toolkit?

The ten interventions are a menu. Not every woman needs all of them, and not every intervention will fit every situation. Building a personal toolkit means choosing the specific interventions that fit your particular pattern and life.

  • Start with the foundation: Blood sugar stabilization (Intervention 1) and sleep prioritization (Intervention 2) belong in almost every toolkit because they address the biological drivers that make everything else harder. Install these as the foundation before adding anything else.
  • Add the daily pause practice: The 10-minute pause (Intervention 4) and the trigger-naming (Intervention 3) are low-friction and high-impact. Add them within the first two weeks.
  • Layer the nervous system regulation: Daily vagal reset practice (Intervention 7) supports the emotional regulation the body is asking for. Add within the first month.
  • Layer the movement: Strength training and daily movement (Intervention 9) provide the metabolic and psychological support that makes the rest sustainable. Add within the first six weeks.
  • Add mindful eating and journaling: Mindful eating practice (Intervention 5) and food and mood journaling (Intervention 6) require more effortful attention. Add when the earlier layers are in place.
  • Consider the deeper layers: Yoga (Intervention 8) and professional support (Intervention 10) fit into the toolkit based on personal preference, resources, and clinical need. The Monthly Personal Training and Nutrition Coaching Program is the primary CTA for the coaching layer. The retreat is the immersive option.
  • A sample first-month plan: Week 1: install 30 grams of protein at breakfast, establish a consistent bedtime. Week 2: add the 10-minute pause practice. Week 3: add ten minutes of daily vagal reset. Week 4: begin twice-weekly strength training. Continue building layers month by month.

What Should You Do After an Emotional Eating Slip?

Every woman working through emotional eating recovery will have episodes where the pattern reasserts itself. How those episodes are handled determines whether they become part of the recovery or become the start of a new spiral.

Six steps to recover after emotional eating.
  • Do not self-shame: Self-shame after an episode is the strongest single predictor of the next episode. This is the counterintuitive but repeatedly documented finding. The more compassionate you are with yourself after a slip, the less likely a subsequent slip becomes.
  • Do not skip meals to compensate: Restricting food after an emotional eating episode reliably triggers the next episode within 24 to 48 hours by producing the biological state that drives cravings. Return to your normal eating pattern immediately, even if that means eating breakfast the next morning after a difficult evening.
  • Get curious about the trigger: Once the immediate emotional intensity has passed, ask what actually happened. What was going on before the episode. What emotion was present. What need was underneath. This is data, not a case for prosecution.
  • Restore the foundation: Return to the interventions. Get an early sleep. Eat protein and vegetables at your next meal. Do ten minutes of nervous system reset. The pattern is self-correcting when the interventions are re-engaged.
  • Talk to someone: If the slip is confusing or if it reveals something you did not know about your pattern, talking with a coach, therapist, or trusted friend often accelerates the insight. Silence and secrecy are the fuel of the shame cycle. Language is one of the antidotes.
  • Do not restart from zero: A slip is not a failure and does not require starting the whole process over. It is one data point in an ongoing practice. Return to the practice and continue.

Get 11 Free Macro-Friendly Sample Recipes

Download 11 macro-friendly sample recipes from our cookbook that will give you everything you need to start eating like a woman who’s done with the guesswork.

Which Mistakes Can Undermine Emotional Eating Recovery?

Six mistakes consistently derail emotional eating recovery for midlife women.

  • Trying to fix everything at once: The temptation is to install all ten interventions in week one and quit the pattern by force. This produces overwhelm, fatigue, and a rebound to the old pattern within a few weeks. Layer the interventions gradually.
  • Skipping the foundation: Blood sugar and sleep are not optional. Trying to work the higher-level interventions without these in place produces disappointing results and the false impression that the framework does not work.
  • Weighing yourself constantly: Body composition change during emotional eating recovery is not linear. Daily weight tracking produces emotional volatility that itself triggers eating episodes. Track weekly at most, or ignore the scale entirely for the first eight weeks and use other metrics like sleep quality, energy, mood, and clothing fit.
  • Comparing your recovery to someone else’s: Every woman’s timeline and pattern is different. Comparing your third-month progress to another woman’s third-month progress produces demoralization without producing information. Track your own trend, not the comparison.
  • Restricting food after slips: Discussed above. Do not do it.
  • Waiting until conditions are perfect to start: The perfect week never arrives. Start with imperfect implementation of one intervention this week.

Get 11 Free Macro-Friendly Sample Recipes

Download 11 macro-friendly sample recipes from our cookbook that will give you everything you need to start eating like a woman who’s done with the guesswork.

When Should You See a Healthcare Professional?

Most emotional eating patterns can be addressed through the lifestyle framework in this article, in combination with coaching or self-directed practice. Some situations require professional support first or alongside.

  • Clinical binge eating: If you experience episodes of eating large amounts of food in short windows with a sense of loss of control, occurring twice a week or more for three months or longer, this may indicate binge eating disorder and warrants evaluation by a mental health professional.
  • Purging or compensatory behaviors: Any pattern of vomiting, laxative use, excessive exercise, or restrictive eating in response to food intake indicates a clinical eating disorder and requires specialized treatment.
  • Depression or anxiety that is not resolving: If underlying depression, anxiety, or trauma is not responding to lifestyle interventions and appears to be driving the eating pattern, working with a mental health provider is important.
  • History of eating disorders: Any personal history of anorexia, bulimia, or binge eating disorder means that emotional eating recovery should be done in partnership with a qualified specialist.
  • Medical concerns: Significant weight fluctuations, cardiovascular symptoms, or other medical concerns arising from the eating pattern warrant medical evaluation.
  • Resources: The National Eating Disorders Association helpline (call or text 800-931-2237 in the US) is one starting point for professional referral. Ask your primary care provider for local resources.

What Are Your Next Steps?

If the framework in this article resonates and you want to begin the work of ending the emotional eating cycle, here are the four next steps in order of friction.

  1. Install the foundation this week. Aim for 30 grams of protein at breakfast, a consistent bedtime, and one glass of water before every food decision that is not a scheduled meal. These three changes alone will produce noticeable reduction in cravings within seven to ten days.
  2. Add the 10-minute pause next week. Every food urge that is not scheduled hunger gets a 10-minute pause with a walk, breath work, or a glass of water. Then decide.
  3. Layer in nervous system regulation. Choose two exercises from our vagus nerve reset article and practice them daily for a total of about ten minutes.
  4. Consider personalized support. The Monthly Personal Training and Nutrition Coaching Program is the primary CTA for this article. This is where I work directly with midlife women on installing the full framework. For the immersive version, the Deeply Restorative Yoga and Nature Retreat at our Smoky Mountains property installs the framework in five days.

Get 11 Free Macro-Friendly Sample Recipes

Download 11 macro-friendly sample recipes from our cookbook that will give you everything you need to start eating like a woman who’s done with the guesswork.

Frequently Asked Questions

What is emotional eating in menopause?

Emotional eating in menopause is the use of food to soothe or regulate difficult feelings, intensified specifically by the hormonal changes of perimenopause and menopause. The pattern is driven by declining estrogen (which affects serotonin and dopamine), cortisol dysregulation, sleep disruption, and the increased life-load typical of the midlife years. It is not a willpower problem. It is a specific hormonal and neurochemical pattern that responds well to targeted lifestyle interventions.

Why do I crave sugar and carbs in perimenopause?

Cravings for sugar and simple carbohydrates in perimenopause are driven by several converging biological factors. Declining estrogen reduces serotonin production. Cortisol elevation drives specific cravings for calorie-dense foods. Poor sleep raises hunger hormones. The combination produces a strong biological pull toward the exact foods that would provide the fastest neurochemical relief. Understanding this makes it easier to respond with the right interventions rather than blaming yourself.

How do I stop stress eating in menopause?

The most effective interventions for stress eating in menopause are stabilizing blood sugar (30 to 40 grams of protein at every meal, adequate fiber and fat), prioritizing sleep, adding daily nervous system regulation practices, and inserting a 10-minute pause between food urges and food actions. Restrictive dieting and self-shame reliably make the pattern worse and should be avoided.

Is emotional eating the same as binge eating disorder?

Emotional eating and binge eating disorder are different but overlapping. Emotional eating is a common pattern involving the use of food to regulate feelings. Binge eating disorder is a clinical diagnosis involving recurrent episodes of eating large amounts of food in short windows with a sense of loss of control, occurring frequently over a defined time period. Not every emotional eater has binge eating disorder, but every case of binge eating disorder involves emotional eating. If your pattern feels clinically severe, please consult a qualified mental health professional.

Can I stop emotional eating without dieting?

Yes, and dieting typically makes emotional eating worse rather than better. The most effective approach is to stop restricting food and instead address the drivers of the pattern (blood sugar instability, sleep debt, nervous system dysregulation, unmet emotional needs). Weight change often happens as a byproduct of the emotional eating recovery rather than as the primary target.

How long does emotional eating recovery take?

Meaningful reduction in emotional eating frequency typically appears within two to eight weeks of consistent practice. Deeper changes in the emotional patterns and body relationship develop over six to twelve months. This is not a quick fix, but the trajectory of improvement is generally steady if the foundation interventions are in place.

What is the connection between cortisol and emotional eating?

Cortisol drives specific cravings for high-fat and high-sugar foods through documented biological pathways. Chronically elevated cortisol (common in midlife due to stress, sleep loss, and hormonal changes) keeps this craving pathway activated. Cortisol also drives abdominal fat storage, which is part of why emotional eating produces such visible body composition changes in midlife women. Addressing cortisol through sleep, movement, nervous system regulation, and stress management is a central piece of recovery.

Why do I emotionally eat at night specifically?

Evening emotional eating is one of the most common patterns and is driven by several factors. Cortisol curves often shift in midlife toward higher evening levels. Willpower and prefrontal control are depleted by the end of the day. Alcohol consumption in the evening reduces impulse control further. Sleep debt from previous nights compounds. Emotional stress from the day accumulates. Evenings are often the first quiet moment after a full day of external demands, which allows suppressed emotions to surface.

Get 11 Free Macro-Friendly Sample Recipes

Download 11 macro-friendly sample recipes from our cookbook that will give you everything you need to start eating like a woman who’s done with the guesswork.

Does yoga help with emotional eating?

Yoga has documented benefits for emotional eating recovery, likely through multiple mechanisms including reduced cortisol, improved body awareness, better emotional regulation, improved sleep, and repaired body relationship. Regular practice of gentle or restorative yoga specifically appears to help. The Deeply Restorative Yoga and Nature Retreat at our Smoky Mountains property includes daily yoga programming specifically for this purpose.

What foods should I avoid to stop emotional eating?

The framing of foods to avoid is usually counterproductive. Restrictive food rules tend to worsen emotional eating rather than help it. The more effective approach is to build the foundation of what to eat consistently (adequate protein, fiber, healthy fats, colorful vegetables, whole foods) so that cravings for less nutritious foods reduce naturally. Occasional inclusion of comfort foods without the drama is often part of a healthy relationship with food.

Can medications help with emotional eating?

Some medications can play a supporting role. Antidepressants may help when emotional eating is driven by underlying depression. GLP-1 medications reduce appetite and may reduce emotional eating in some users, though they do not address the emotional drivers directly and should be combined with the lifestyle framework in this article. Any medication decision should be made in partnership with a qualified healthcare provider.

Get 11 Free Macro-Friendly Sample Recipes

Download 11 macro-friendly sample recipes from our cookbook that will give you everything you need to start eating like a woman who’s done with the guesswork.

What is mindful eating and does it work?

Mindful eating is the practice of paying full attention to the sensory experience of eating without distraction. Research supports its effectiveness for reducing portion sizes, improving satiety recognition, and reducing emotional eating over time. Start with one mindful meal per day and build from there. The specific practice is to remove phones and screens, chew thoroughly, pause between bites, and notice when the body signals fullness.

Should I keep a food journal?

A simple food and mood journal (what you ate, when, what you felt before, what you felt after) is one of the most powerful diagnostic tools for emotional eating recovery. The point is not restriction or judgment. The point is data. Most women see clear patterns within four to six weeks of consistent journaling. Reviewing weekly is more useful than reviewing daily.

How do I forgive myself after an emotional eating episode?

Self-shame after an episode is the strongest predictor of the next episode. The practical antidote is deliberate self-compassion, which usually needs to be practiced rather than felt naturally. Speak to yourself as you would speak to a friend who had had a difficult evening. Get curious rather than critical. Return to the foundation interventions immediately without restricting. Talk to someone you trust if the shame is overwhelming. Over time, the shame cycle loosens.

Can a retreat help with emotional eating?

An immersive retreat setting can produce shifts in emotional eating patterns that are difficult to achieve at home because the environment removes many of the daily triggers and provides intensive practice of the foundation interventions. The Deeply Restorative Yoga and Nature Retreat at our Smoky Mountains property is specifically designed for this purpose and consistently produces meaningful shifts for guests who arrive with emotional eating patterns as one of their focus areas.

References

  • van Strien, T. (2018). Causes of emotional eating and matched treatment of obesity. Current Diabetes Reports, 18(6), 35.
  • Adam, T. C., & Epel, E. S. (2007). Stress, eating and the reward system. Physiology and Behavior, 91(4), 449–458.
  • Dallman, M. F., Pecoraro, N., Akana, S. F., et al. (2003). Chronic stress and obesity: a new view of comfort food. Proceedings of the National Academy of Sciences, 100(20), 11696–11701.
  • Epel, E., Lapidus, R., McEwen, B., & Brownell, K. (2001). Stress may add bite to appetite in women: a laboratory study of stress-induced cortisol and eating behavior. Psychoneuroendocrinology, 26(1), 37–49.
  • Yau, Y. H. C., & Potenza, M. N. (2013). Stress and eating behaviors. Minerva Endocrinologica, 38(3), 255–267.
  • Konttinen, H., van Strien, T., Männistö, S., et al. (2019). Depression, emotional eating and long-term weight changes: a population-based prospective study. International Journal of Behavioral Nutrition and Physical Activity, 16(1), 28.
  • Frayn, M., Livshits, S., & Knäuper, B. (2018). Emotional eating and weight regulation: a qualitative study of compensatory behaviors and concerns. Journal of Eating Disorders, 6, 23.
  • Warren, J. M., Smith, N., & Ashwell, M. (2017). A structured literature review on the role of mindfulness, mindful eating and intuitive eating in changing eating behaviours. Nutrition Research Reviews, 30(2), 272–283.
  • Katterman, S. N., Kleinman, B. M., Hood, M. M., et al. (2014). Mindfulness meditation as an intervention for binge eating, emotional eating, and weight loss: a systematic review. Eating Behaviors, 15(2), 197–204.
  • Kristeller, J. L., & Wolever, R. Q. (2011). Mindfulness-based eating awareness training for treating binge eating disorder: the conceptual foundation. Eating Disorders, 19(1), 49–61.
  • Chao, A. M., Jastreboff, A. M., White, M. A., et al. (2017). Stress, cortisol, and other appetite-related hormones: prospective prediction of 6-month changes in food cravings and weight. Obesity, 25(4), 713–720.
  • Sominsky, L., & Spencer, S. J. (2014). Eating behavior and stress: a pathway to obesity. Frontiers in Psychology, 5, 434.
  • Greeno, C. G., & Wing, R. R. (1994). Stress-induced eating. Psychological Bulletin, 115(3), 444–464.
  • Torres, S. J., & Nowson, C. A. (2007). Relationship between stress, eating behavior, and obesity. Nutrition, 23(11-12), 887–894.
  • Spencer, S. J., & Tilbrook, A. (2011). The glucocorticoid contribution to obesity. Stress, 14(3), 233–246.
  • Beccuti, G., & Pannain, S. (2011). Sleep and obesity. Current Opinion in Clinical Nutrition and Metabolic Care, 14(4), 402–412.
  • Chaput, J. P. (2014). Sleep patterns, diet quality and energy balance. Physiology and Behavior, 134, 86–91.
  • Douglas, S., Cartmill, R., Brown, R., et al. (2020). The Women’s Health Initiative: menopause and cardiovascular disease. Menopause, 27(9), 1094–1099.
  • Herriot, H., Wrosch, C., Hamm, J. M., & Pruessner, J. C. (2020). Stress-related trajectories of diurnal cortisol in older adulthood over 12 years. Psychoneuroendocrinology, 121, 104826.
  • Stanton, A. V., James, K., Brennan, M. M., et al. (2021). Perimenopause: the complex, transitional time of the menopause. Irish Journal of Medical Science, 190(4), 1359–1368.

Disclaimer: Always consult with a healthcare professional before starting any new routines, programs, or nutrition plans to ensure you receive the best medical advice and strategy for your specific individual needs. If you are experiencing symptoms of a clinical eating disorder, please contact a qualified mental health professional or the National Eating Disorders Association helpline (call or text 800-931-2237 in the US).

Get 11 Free Macro-Friendly Sample Recipes

Download 11 macro-friendly sample recipes from our cookbook that will give you everything you need to start eating like a woman who’s done with the guesswork.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

10 Vagus Nerve Reset Exercises for Women Over 40 (With Videos)

Vagus nerve reset exercises have become a major topic in midlife women’s health for good reason. The vagus nerve helps regulate stress recovery, sleep, digestion, mood, heart rate variability, and inflammation. During perimenopause and menopause, hormonal changes, disrupted sleep, and ongoing stress can keep the nervous system stuck in low-grade activation, making deliberate regulation especially important.

I am Terry Tateossian, founder of The House of Rose and a certified lifestyle medicine coach who runs nutrition-focused wellness retreats for women in perimenopause, menopause, and post-menopause. Nervous system regulation is one of the foundational pillars I teach through retreats and coaching. The exercises in this guide draw from vagal tone research, polyvagal theory, clinical practice, breathwork, and the techniques that consistently help the women I coach.

Each exercise includes step-by-step instructions, a suggested video placement, its specific benefits for the midlife body, and modifications for common concerns such as neck tension, sinus issues, and low blood pressure.

Important: Consult your healthcare provider before trying a new nervous system practice, especially if you have cardiovascular concerns, low blood pressure, glaucoma, seizure disorders, or another significant medical condition.

What Is the Vagus Nerve and How Does It Work?

The vagus nerve is the tenth cranial nerve, and it is the longest nerve in the human body. It emerges from the base of the skull, travels down through the neck, and branches extensively through the throat, heart, lungs, liver, stomach, intestines, and other organs. The word vagus comes from the Latin for wandering, which is a good description of how widely this nerve travels.

Functionally, the vagus nerve is the primary conduit of the parasympathetic nervous system, which is the branch of the autonomic nervous system responsible for rest, digestion, recovery, and repair. When the vagus nerve is active, the body downshifts from stress activation into the physiological state that allows healing and restoration.

When vagal tone is low, the body remains in a background state of stress activation, which is a common pattern in midlife women whose sleep, hormones, and life stress are all pulling in the wrong direction at once.

Vagus nerve pathway and functions infographic.
  • What vagal tone means: Vagal tone refers to the ongoing activity of the vagus nerve, often measured indirectly through heart rate variability. Higher vagal tone is associated with better stress recovery, better sleep, better digestion, better mood regulation, lower inflammation, and better cardiovascular function. Lower vagal tone is associated with the opposite pattern.
  • The two branches of the vagus: Stephen Porges’s polyvagal theory distinguishes between the ventral vagal branch (associated with social engagement, calm alertness, and connection) and the dorsal vagal branch (associated with shutdown and immobilization). The exercises in this article are targeted at supporting the ventral vagal system, which is the state most women in midlife need more of.
  • The gut-brain connection: The vagus nerve carries approximately 80 percent afferent (sensory) fibers, meaning that most of the traffic on the vagus is information flowing from the body up to the brain. This is why gut health, breath, posture, and interoceptive practices have such powerful effects on mood and cognition. It is not woo. It is the specific neural anatomy of a nerve that sends most of its signal from the body to the brain.

For a deeper conceptual grounding, see our earlier article on the vagus nerve and gut health connection and our parasympathetic nervous system and aging article, which cover the underlying physiology in more depth. This article focuses on the specific reset exercises.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Why Does Vagus Nerve Support Matter in Midlife?

Nervous system regulation becomes especially important during perimenopause, menopause, and post-menopause. Hormonal changes, disrupted sleep, and heavier life demands can all make it harder for the body to return to a calm, restorative state.

  • Estrogen and Vagal Function: Estrogen supports parasympathetic nervous system activity and healthy heart rate variability. As estrogen declines, many women experience greater sympathetic activation and more difficulty shifting into rest and recovery.
  • Sleep Disruption: Fragmented midlife sleep can lower vagal tone the following day, making stress harder to regulate. This can create a repeating cycle of poor sleep, nervous system activation, and reduced recovery.
  • Cortisol Dysregulation: Midlife hormonal changes can contribute to elevated evening cortisol and lower morning energy. Vagal reset practices may help reinforce a healthier daily rhythm that supports sleep, mood, and metabolic health.
  • Peak Life Stress: Career demands, parenting responsibilities, aging parents, and financial pressures often converge during midlife. Regular nervous system regulation gives the body a practical way to manage this heavier load with fewer hormonal buffers.
  • Digestion and Gut Health: The vagus nerve helps regulate digestive motility, gut signaling, and the transition into the rest-and-digest state. Supporting vagal tone may help reduce bloating, irregularity, and stress-related digestive discomfort. See the midlife hydration article and the best probiotics article for the broader gut context.
  • Systemic Inflammation: Vagal activation helps regulate inflammation through the cholinergic anti-inflammatory pathway. Regular reset practices may support a lower inflammatory burden during a stage of life when inflammation often increases.

What Are the Signs Your Vagus Nerve Needs a Reset?

Not every midlife symptom points to low vagal tone. However, a recurring cluster of the following signs may suggest that your nervous system is struggling to return to its healthy resting baseline.

  • Disrupted Sleep: You may feel exhausted but still struggle to fall asleep or wake between 2:00 and 4:00 a.m. with a racing mind. Feeling wired but tired in the evening is another common sign of persistent nervous system activation.
  • Digestive Changes: Chronic bloating, irregular bowel movements, or new food sensitivities can appear when the body has difficulty entering the rest-and-digest state. These symptoms may become more noticeable during periods of sustained stress.
  • Declining Heart Rate Variability: A gradual drop in HRV over several months or years may reflect reduced parasympathetic activity. The long-term trend on your wearable is more informative than any single reading.
  • Rising Resting Heart Rate: A resting heart rate that has slowly increased without a clear change in fitness, medication, or health may indicate greater sympathetic activation. Tracking the pattern over time can help reveal changes in recovery capacity.
  • Cold Hands and Feet: Frequently cold extremities without an obvious medical cause may reflect changes in circulation linked to chronic stress activation. This sign is more meaningful when it appears alongside sleep, digestive, or emotional symptoms.
  • Persistent Anxiety or Overwhelm: A constant background sense of tension can signal that the nervous system is spending too much time in a heightened state. Small demands may begin to feel disproportionately difficult or draining.
  • Difficulty Resting: You may struggle to relax even when you have enough time and a calm environment. The body remains alert because it has lost some of its ability to transition smoothly into parasympathetic recovery.
  • Increased Stress Reactivity: Minor inconveniences or ordinary pressures may trigger stronger emotional or physical reactions than they once did. This can indicate that the nervous system has less capacity to absorb stress before becoming overwhelmed.

Occasional episodes of these symptoms are a normal part of life. When several appear together most days for weeks or months, a consistent vagal reset practice may help restore nervous system balance.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Does Research Show About Vagal Tone?

Research on vagal tone has expanded considerably, but the strength of the evidence varies across practices. Some methods have well-established physiological effects, while others remain promising but less thoroughly studied.

Research findings on vagal tone practices.
  • Heart Rate Variability and Vagal Tone: HRV is the most widely used indirect measure of vagal activity and autonomic flexibility. Higher HRV is associated with better stress recovery, cardiovascular health, psychological resilience, and longevity, while long-term improvements can reflect stronger parasympathetic regulation.
  • Breathwork and Parasympathetic Activation: Slow diaphragmatic breathing, particularly at around six breaths per minute, can activate the baroreflex and increase short-term vagal activity. Extending the exhale often strengthens this calming effect by helping the body shift away from sympathetic arousal.
  • Cold Exposure and the Dive Reflex: Applying cold water to the face can trigger the mammalian dive reflex, slowing the heart and producing a rapid parasympathetic response. Full-body cold exposure may create similar effects, although the intensity and safety considerations are greater.
  • Vibration, Sound, and Vocalization: Humming, chanting, and sustained vocal sounds create vibration around the throat and larynx, where branches of the vagus nerve are present. Early research links these practices with changes in HRV, breathing patterns, mood, and perceived calm.
  • Auricular Vagus Stimulation: The auricular branch of the vagus nerve can be targeted through regulated clinical stimulation devices used in research and medical settings. Ear massage and acupressure are gentler at-home approaches, but their evidence is more limited and should not be treated as equivalent to clinical stimulation.
  • The Polyvagal Framework: Polyvagal theory has strongly influenced trauma-informed therapy and somatic practices, but some of its broader explanations remain debated. Many exercises associated with the framework are low risk and may support relaxation, even when their proposed mechanisms have not been fully established.

Overall, the strongest evidence supports short-term improvements in HRV, breathing, and subjective calm. Research on lasting effects on sleep, mood, inflammation, and cardiovascular health is promising but still developing.

“The women who see the biggest change from vagus nerve reset practice are almost always the ones who resisted it the longest. There is a strong pattern of high-achieving midlife women assuming that nervous system work is soft, that it is not serious, and that their time is better spent on strategies that feel more productive. Then something forces the issue, whether it is a sleep crisis, a digestive collapse, or a period of anxiety that will not resolve. They finally add ten minutes of daily vagal reset practice, and within a month the sleep, the digestion, the mood, and the sense of internal weather all shift. What was invisible becomes visible. What felt soft becomes obviously load-bearing. This is one of the most reliably underestimated levers I have ever seen in midlife women’s health.”

Terry Tateossian, Founder of The House of Rose

How Can You Measure Your Progress?

Nervous system change is often invisible in the short term and dramatic in the medium term. Having some way to measure progress keeps the practice from feeling directionless during the first weeks.

  • Heart rate variability tracking: If you use an Oura Ring, Whoop, Garmin, Apple Watch, or similar wearable, note your baseline HRV before starting daily vagal reset practice. Track it weekly. Expect fluctuations day to day. Over four to eight weeks of consistent practice, most women see a meaningful upward trend in their overnight HRV average.
  • Resting heart rate: Resting heart rate tends to fall as vagal tone improves. This is a slower signal than HRV, but it is easily tracked on most wearables and phones.
  • Subjective sleep quality: Track sleep quality on a simple one-to-ten scale each morning, or use your wearable’s sleep score. Look for the average over weeks rather than any single night.
  • Subjective calm and stress recovery: A simple one-to-ten rating at the end of each day for how easily you moved between activation and calm during the day. Look for the average trend over weeks.
  • Digestion and elimination regularity: Improvements in digestion are one of the earliest signals for many women. Regular bowel movements, less bloating, and better appetite regulation are all reasonable signals to notice.

Warning: Do not obsess over daily metrics. Vagal tone fluctuates naturally with sleep, stress, hormones, and life events. A single bad HRV reading is not a failure. Look at the four-week average, not the single reading.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Should You Know Before Starting?

Several principles apply to every exercise in this article and are worth internalizing before beginning.

  • Consistency beats intensity: Ten minutes a day for eight weeks produces bigger nervous system change than an hour once a week. Build a small daily practice you can actually sustain.
  • Nasal breathing is the default: Unless an exercise specifically instructs mouth breathing, breathe through the nose. Nasal breathing produces different physiological effects than mouth breathing and is generally more parasympathetic-activating.
  • Slow is the direction: The vagus nerve responds to slowing down. Every exercise below can be done too fast. If in doubt, slow down further.
  • Comfort matters more than form perfection: Force in nervous system work is counterproductive. If a position or exercise creates significant discomfort, modify or skip it. Ease is the goal.
  • Do not hyperventilate: Some breath practices can trigger dizziness or light-headedness if done incorrectly. If you feel dizzy, stop, sit down, and breathe normally until it resolves. Never practice breath retention while driving or operating machinery.
  • Cold exposure precautions: The cold water face immersion exercise is safe for most healthy adults but should be avoided by anyone with severe cardiovascular disease, uncontrolled high blood pressure, or a history of vasovagal syncope. Talk to your provider if you have any concerns.
  • Pregnancy and specific conditions: Some of the more intense breath and cold practices need modification during pregnancy. If pregnant, work with a prenatal-certified practitioner.
  • Time of day: Vagus nerve reset can be practiced any time. Morning practice supports the day. Evening practice supports sleep. Middle-of-the-day practice supports stress recovery. Choose the time that produces the highest adherence for you.

What Are the 10 Best Vagus Nerve Reset Exercises for Women Over 40?

Vagus nerve reset exercises can help women over 40 calm the nervous system, reduce stress, and feel more grounded throughout the day. These simple practices support the body’s natural shift from a tense, alert state into a more relaxed and restorative one.

They can be especially helpful during midlife, when hormonal changes, poor sleep, and ongoing stress may affect nervous system balance. The following 10 exercises are gentle, practical, and easy to incorporate into a daily routine.

10 vagus nerve reset exercises for women over 40.

Exercise 1: Extended Exhalation Breathing

Extended exhalation breathing is the foundation of every vagus nerve reset practice. It reliably shifts the nervous system toward parasympathetic dominance within a few minutes and requires no equipment.

The vagus nerve activation is stronger during exhalation than during inhalation. Extending the exhalation relative to the inhalation therefore concentrates the parasympathetic effect. Slow breathing at roughly six breaths per minute has been shown in multiple studies to acutely increase heart rate variability and reduce sympathetic activation.

  • Setup: Sit comfortably upright with a tall spine, or lie on your back with a small pillow under the head. Rest hands on the belly if it helps you feel the breath.
  • The pattern: Inhale gently through the nose for four seconds. Exhale slowly through the nose for six to eight seconds. If eight seconds is comfortable, work up to it over weeks.
  • Duration: Practice for five to ten minutes. Longer sessions are fine but not required.
  • Common mistakes: Forcing the breath, holding tension in the chest or shoulders, breathing shallowly in the chest rather than deeply in the belly, rushing the exhalation.
  • Why this exercise for midlife women: This is the safest, most accessible vagal reset available. It requires no equipment, no clothing change, no privacy, and can be done for two minutes in a parking lot or ten minutes before sleep. If you only add one exercise from this list, add this one.
  • Modification for anxiety spikes: If you notice anxiety rising during the practice, shorten the exhalation slightly and focus more on the inhalation until the anxiety subsides. Extended exhalation is powerful and occasionally amplifies anxious sensations before it soothes them.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Exercise 2: Cold Water Face Immersion

Cold water face immersion is one of the most powerful acute vagal activators available. It works through the mammalian dive reflex, the ancient physiological response that shifts the body into parasympathetic dominance the moment the face touches cold water.

Cold receptors on the face, particularly around the eyes and forehead, are directly wired to the trigeminal nerve, which activates a parasympathetic cascade including slowed heart rate, peripheral vasoconstriction, and increased vagal tone. The effect is measurable within seconds.

  • Setup: Fill a bowl with cold water. If comfortable, add a few ice cubes to bring the temperature down to roughly 50 to 60 degrees Fahrenheit. Have a towel nearby.
  • Execution: Take a full breath in. Lean forward and immerse the face in the water up to the temples, holding the breath. Stay submerged for 15 to 30 seconds. Come up, dry the face, and rest for 30 seconds. Repeat two to three times.
  • Duration: The whole practice takes three to five minutes.
  • Common mistakes: Water that is too cold (below 45 degrees F can be too intense), submerging for too long (staying under longer than 30 seconds does not add benefit), rushing between rounds without allowing recovery.
  • Why this exercise for midlife women: Cold face immersion produces one of the fastest and most reliable subjective calming effects available. It is particularly useful for the wired-but-tired evening state, for pulling out of an anxious spiral, or for calming down before a difficult conversation.
  • Modification for beginners: If full facial immersion feels too intense, start with a cold washcloth pressed over the eyes and forehead for one minute. Progress to the bowl immersion as tolerance builds.
  • Safety note: Do not do this practice if you have severe cardiovascular disease, uncontrolled high blood pressure, or a history of fainting from vasovagal responses. Discuss with your provider first.

Exercise 3: Humming and Vocal Toning

Humming activates the vagus nerve through vibration in the throat and larynx, which are innervated by branches of the vagus. Regular humming practice has documented effects on heart rate variability, mood, and sinus function.

The vibration produced by humming stimulates the vagal branches that innervate the throat and larynx, and it also produces measurable nitric oxide release in the sinuses. The combination of vagal stimulation and sinus activation is why humming often feels immediately settling.

  • Setup: Sit comfortably upright with a tall spine. Rest your hands wherever feels good.
  • Execution: Inhale gently through the nose. On the exhalation, produce a low, steady hum. The specific note does not matter. Feel the vibration in the throat, chest, and face. Continue for the full exhalation. Inhale, and repeat.
  • Duration: Practice for three to five minutes.
  • Variations: The traditional yogic version is called Bhramari (bee breath) and involves gently closing the ears with the fingers to amplify the internal vibration. Ocean humming with the mouth slightly open produces a different vibrational pattern. Chanting the sound “om” produces vibration in the abdomen as well.
  • Common mistakes: Straining the voice, humming too loudly, forcing a specific pitch. The point is the vibration, not the sound.
  • Why this exercise for midlife women: Humming is accessible in almost any setting. It can be done in the car, in the shower, walking, or as a five-minute morning practice. Many women find it particularly effective for the transition from work stress to home presence at the end of the day.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Exercise 4: Vigorous Gargling

Gargling activates the pharyngeal branches of the vagus nerve through mechanical stimulation of the throat muscles. It is one of the simpler and more overlooked vagal exercises.

The pharyngeal muscles that produce the gargling motion are innervated by the vagus nerve. Vigorous gargling produces mechanical stimulation of these muscles, which appears to increase vagal tone and stimulate saliva production, which is also a parasympathetic marker.

  • Setup: A glass of water at any temperature. Cool or slightly warm water is easier than very cold water.
  • Execution: Take a mouthful of water. Tip the head back slightly and gargle vigorously for 30 to 60 seconds. The gargle should be strong enough to produce sound and visible bubbling. Spit the water out. Repeat with a second and third mouthful.
  • Duration: The whole practice takes two to three minutes.
  • Common mistakes: Gentle gargling produces less vagal stimulation. The vigor of the gargle matters. If you are barely audible, gargle harder.
  • Why this exercise for midlife women: Gargling is a natural companion to morning teeth-brushing routines, which builds a daily practice with almost no additional time cost. Adding two minutes of vigorous gargling to your morning routine is one of the lowest-friction vagal practices available.

Exercise 5: Left Nostril Breathing (Chandra Bhedana)

Left nostril breathing, called Chandra Bhedana in the yogic tradition (moon-piercing breath), has some research support for shifting the nervous system toward parasympathetic dominance more reliably than symmetric breath practices.

The mechanism is not fully understood, but multiple studies show that unilateral left nostril breathing tends to produce shifts toward parasympathetic dominance while right nostril breathing tends toward sympathetic activation. The vagus nerve appears to be part of the pathway.

  • Setup: Sit comfortably upright with a tall spine. Rest the left hand in the lap. Bring the right hand to the face, using the thumb to close the right nostril and the ring finger available to close the left when needed.
  • Execution: Close the right nostril with the right thumb. Inhale slowly through the left nostril for four to six seconds. At the top of the inhalation, release the thumb and use the ring finger to close the left nostril. Exhale slowly through the right nostril for six to eight seconds. That is one round. Repeat by inhaling through the left and exhaling through the right, keeping the left as the entry point throughout.
  • Duration: Practice for five to ten minutes.
  • Common mistakes: Alternating nostrils (that is a different practice called Nadi Shodhana), forcing the breath, gripping the nostrils too tightly, holding the shoulders up around the ears.
  • Why this exercise for midlife women: Left nostril breathing is particularly effective for the evening wind-down or for the wired-but-tired state that many midlife women recognize from perimenopause and menopause. It is a good pre-sleep practice.
  • Modification for stuffy sinuses: If one nostril is congested, do this practice sitting up with a warm shower running in the bathroom, or after using saline nasal rinse. Do not force air through a blocked nostril.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Exercise 6: Auricular Vagal Massage

The auricular (ear) branch of the vagus nerve is the target of the transcutaneous vagus nerve stimulation devices used clinically. The at-home version uses gentle massage or acupressure to specific points on the ear.

The auricular branch of the vagus nerve emerges through several specific points on the outer ear, including the cymba conchae (the deeper bowl of the ear near the ear canal) and the tragus (the small flap at the front of the ear canal). Gentle stimulation of these points activates the vagal afferent fibers that project to the brainstem.

  • Setup: Sit comfortably. Warm hands help. A small amount of oil (jojoba, almond, or unscented) is optional but often makes the massage more comfortable.
  • Execution: Using the index finger and thumb, gently massage the cymba conchae (the deep bowl of the ear just above the ear canal) in slow circles for 30 to 60 seconds per ear. Then move to the tragus (the small flap at the front of the ear canal) and pinch and release gently for 30 to 60 seconds per ear. Then work along the outer edge of the ear (the helix) from top to bottom in slow strokes for 60 seconds per ear.
  • Duration: The whole practice takes three to five minutes.
  • Common mistakes: Pressing too hard, moving too fast, treating the practice as a checklist rather than a settling. The touch should be gentle and slow.
  • Why this exercise for midlife women: This practice pairs well with the extended exhalation breathing (Exercise 1) as a longer evening reset. It is also a good stress-recovery tool that can be done seated at a desk during a difficult work day.

Exercise 7: The Basic Exercise (Stanley Rosenberg)

The Basic Exercise is drawn from Stanley Rosenberg’s book Accessing the Healing Power of the Vagus Nerve. It uses gentle eye movement combined with head positioning to release tension in the suboccipital muscles at the base of the skull, which lie close to several important cranial nerve structures.

The exercise increases mobility in the upper cervical spine, which houses several cranial nerve structures including the accessory nerve, which coordinates with the vagus. The eye-and-head coordination produces a gentle unwinding of chronic tension patterns that often develop from prolonged desk work.

  • Setup: Lie on your back on a comfortable surface with a small folded towel under the head if needed. Interlace the fingers behind the head with the elbows resting on the floor. The head is fully supported by the hands.
  • Execution: Keeping the head still, look as far to the right as your eyes will comfortably go, without moving your head. Hold the gaze there. Within 30 to 60 seconds, most people will spontaneously yawn, sigh, or swallow. That is the sign of nervous system release. Return the eyes to center. Rest for a moment. Then look as far to the left as the eyes will comfortably go and hold until the same release response occurs. Return to center.
  • Duration: The whole practice takes three to five minutes.
  • Common mistakes: Moving the head with the eyes, straining the eye position, giving up before the release response occurs.
  • Why this exercise for midlife women: The suboccipital tension that this exercise releases is extremely common in women who have spent decades at desks. Many women report immediate softening of chronic neck and jaw tension after this practice, which improves both vagal function and general comfort.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Exercise 8: The Half-Salamander (Stanley Rosenberg)

The Half-Salamander is another Stanley Rosenberg exercise that pairs eye movement with subtle head positioning to release nervous system holding patterns.

The exercise uses lateral eye movement combined with subtle side-bending of the head to release specific tension patterns in the neck and jaw. It complements the Basic Exercise by working slightly different structures.

  • Setup: Sit comfortably upright with a tall spine. Rest the hands wherever comfortable.
  • Execution: Look with the eyes to the right, keeping the head facing forward. Then tilt the head slightly to the right, bringing the right ear toward the right shoulder while the eyes remain looking to the right. Hold for 30 to 60 seconds until you notice a release response (yawn, sigh, swallow, or a sense of settling). Return to neutral. Rest. Then repeat on the other side.
  • Duration: The whole practice takes three to five minutes.
  • Common mistakes: Tilting the head too far, moving the eyes and head in opposite directions, expecting immediate results in the first session.
  • Why this exercise for midlife women: This practice is particularly effective for the chronic jaw and neck tension that many midlife women carry from stress, teeth grinding, and prolonged screen use. It is one of the gentlest exercises in the list and is safe for most bodies.

Exercise 9: Legs-Up-the-Wall With Slow Breath

Legs-up-the-wall (Viparita Karani in the yogic tradition) is a restorative posture that combines gentle inversion with the breath practices from earlier exercises. It is one of the most effective evening wind-down positions available.

The mild inversion produces a shift in blood pressure that activates baroreceptors in the neck and chest, which stimulate vagal response. The combination of the physical position and the slow breath work produces a strong parasympathetic activation.

  • Setup: You need clear wall space and a folded blanket or yoga bolster for under the hips.
  • Execution: Sit sideways with your hip against the wall. Slowly lie back and swing your legs up the wall so that the body forms an L shape with the buttocks close to the wall and the legs extending straight up. If your hamstrings are tight, move your buttocks slightly away from the wall. Rest the arms in a comfortable position. Close your eyes. Practice extended exhalation breathing (Exercise 1) or humming (Exercise 3) for the duration of the position.
  • Duration: Ten to fifteen minutes is a strong baseline, and longer sessions are fine if time allows.
  • Common mistakes: Forcing the buttocks against the wall despite tight hamstrings, holding tension in the shoulders and jaw, treating the practice as passive rather than actively softening.
  • Why this exercise for midlife women: This is one of the best evening practices for midlife women dealing with sleep onset difficulties. Ten minutes of legs-up-the-wall before bed shifts the nervous system state substantially and often produces meaningfully improved sleep onset within the same evening.
  • Modification: If lying flat is uncomfortable, place a folded blanket under the head. If the inversion is contraindicated (some blood pressure conditions, glaucoma), practice legs-on-a-chair instead, with the calves resting on a chair seat and the thighs vertical.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Exercise 10: Body-Scan Yoga Nidra

Yoga Nidra (yogic sleep) is a guided body-scan practice that produces measurable shifts toward parasympathetic dominance and deep restorative rest. It is one of the most effective daily reset practices for accumulated nervous system load.

The guided body scan directs attention systematically through each part of the body, producing a shift in the balance between sympathetic and parasympathetic nervous system activity. Regular practice has documented effects on sleep quality, stress recovery, and heart rate variability.

  • Setup: Lie on your back on a comfortable surface. Cover yourself with a light blanket for warmth. Have the audio guide ready.
  • Execution: Follow the guided body scan for the duration of the recording. The typical pattern is a slow attention movement through the toes, feet, ankles, calves, knees, thighs, hips, abdomen, chest, back, shoulders, arms, hands, neck, face, and top of the head. Longer versions include more detailed attention.
  • Duration: Fifteen to thirty minutes for most sessions.
  • Common mistakes: Falling deeply asleep is actually fine and does not undermine the practice. Trying to force staying awake produces tension that undermines the practice. Rushing through the body regions defeats the purpose.
  • Why this exercise for midlife women: This is the deepest single practice in the list and produces significant nervous system reset. It is particularly powerful as an afternoon practice for restoration or as an evening pre-sleep practice. Many women find that a regular Yoga Nidra practice is one of the most effective non-pharmaceutical interventions for the sleep disruption of perimenopause and menopause.

“The retreat schedule at the Smoky Mountains property includes a guided Yoga Nidra almost every day, and it is consistently one of the practices that guests are most surprised by. Women arrive assuming they will get the most from the workouts and the food, and they leave saying that the Yoga Nidra was the thing that shifted them the most. This is because most midlife women are chronically under-rested at a nervous system level even when their sleep hours look fine on paper. A daily deep-rest practice fills a hole that most women did not realize was there. If you can only add one longer practice from this article to a weekly routine, this is the one.”

Terry Tateossian, Founder of The House of Rose

How Can You Build a Daily Vagus Nerve Reset Practice?

The ten exercises can be arranged into a daily practice in several ways. The right approach depends on how much time you have, when it works, and which practices your nervous system responds to most.

  • The five-minute daily reset (minimum viable practice): Choose two exercises from the list and pair them into a five-minute daily habit. A common effective pairing is one minute of vigorous gargling in the morning (Exercise 4) and four minutes of extended exhalation breathing in the evening (Exercise 1). This is the lowest-friction version of the practice and produces meaningful change within four to eight weeks.
  • The ten-minute daily reset (recommended baseline): Add auricular massage (Exercise 6) and humming (Exercise 3) to the morning routine. Add left nostril breathing (Exercise 5) or the Rosenberg Basic Exercise (Exercise 7) to the evening routine. Total time about ten minutes per day.
  • The fifteen-minute daily reset: The full baseline plus ten minutes of legs-up-the-wall (Exercise 9) in the evening. This is a strong practice for women who are dealing with sleep issues or chronic stress load.
  • The weekly deep reset: Add a full 20 to 30 minute Yoga Nidra session (Exercise 10) once or twice per week, and one cold water face immersion session (Exercise 2) two or three times per week as needed for acute stress recovery.

Here’s a sample weekly schedule:

Day

Morning

Evening

Monday

Gargling + humming (3 min)

Extended exhalation + legs-up-wall (12 min)

Tuesday

Auricular massage (3 min)

Left nostril breathing (10 min)

Wednesday

Basic Exercise (5 min)

Yoga Nidra (25 min)

Thursday

Gargling + humming (3 min)

Extended exhalation + legs-up-wall (12 min)

Friday

Half-Salamander (5 min)

Left nostril breathing (10 min)

Saturday

Cold face immersion (5 min)

Extended exhalation (10 min)

Sunday

Rest day, gentle humming while walking

Yoga Nidra (25 min)

Weeks 1 to 4 focus on installing the daily habit and learning what each exercise feels like in your body. Weeks 5 to 8 focus on refining the mix based on what your nervous system responds to most. By month three or four, the practice is fully installed as background daily routine and produces the sleep, HRV, and mood benefits at their full magnitude.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Which Mistakes Can Undermine Your Vagus Nerve Practice?

Several patterns consistently reduce the effectiveness of vagus nerve reset practice for midlife women.

Seven mistakes that weaken vagus nerve practice.
  • Practicing sporadically: Vagal tone responds to consistent daily practice, not occasional intense sessions. Five minutes every day beats an hour once a week.
  • Forcing intensity: Nervous system work responds to ease, not effort. Trying harder to relax is a category error. The correct move is to slow down further and do less, because that is the direction the vagus nerve responds to.
  • Skipping the boring exercises: Extended exhalation breathing and humming look unimpressive on paper, and they are the most reliably effective practices in the list. Do not skip them for the more novel-seeming practices.
  • Expecting overnight change: HRV, sleep, and subjective calm change over weeks and months, not days. Track the four-week trend, not the daily reading.
  • Practicing only when stressed: The best time to practice is when you are already calm. This builds capacity that becomes available when you are under stress.
  • Ignoring the foundational lifestyle layer: Nervous system practice works best when it sits on top of adequate sleep, movement, protein intake, and hydration. If those foundations are missing, the practice will produce smaller results.
  • Turning it into a performance: Rigid perfectionism about the practice defeats its purpose. Some days you will do five minutes, some days you will do fifteen, and some days you will forget entirely. All of that is fine, and the practice simply returns the next day without self-criticism.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

When Should You See a Healthcare Professional?

Most midlife women can safely add all ten exercises to their daily routine. Some situations require professional evaluation first.

  • Cardiovascular disease: Cold exposure and breath retention practices need clinician approval for anyone with significant heart disease, uncontrolled blood pressure, or a history of arrhythmia.
  • History of fainting: Vasovagal syncope history is a reason to avoid the cold face immersion and to be careful with breath retention practices.
  • Glaucoma: Inverted positions like legs-up-the-wall may increase intraocular pressure and should be discussed with an ophthalmologist.
  • Seizure disorders: Breath work practices need clinician guidance for anyone with a seizure history.
  • Severe anxiety or PTSD: Some breath practices and interoceptive exercises can amplify anxiety in vulnerable populations before they soothe it. Working with a trauma-informed practitioner is often better than solo practice for these situations.
  • Persistent symptoms despite practice: If sleep, mood, digestion, or anxiety symptoms are severe and are not responding to daily practice after eight to twelve weeks, that is a reason to consult a healthcare provider for a broader clinical evaluation.

What Are Your Next Steps?

If the framework in this article makes sense and you want to install a daily vagus nerve reset practice, here are the four next steps in order of friction.

  1. Choose two exercises to start with tonight. Extended exhalation breathing (Exercise 1) and one other of your choice. Do them for five minutes before sleep.
  2. Establish the morning practice tomorrow. Add vigorous gargling and humming to your morning routine. This takes about three minutes and produces almost no schedule friction.
  3. Track a simple metric for eight weeks. Sleep quality on a one-to-ten scale each morning is the easiest. HRV if you have a wearable. Look at the four-week average.
  4. Consider personalized coaching or the retreat. The Deeply Restorative Yoga and Nature Retreat at our Smoky Mountains property is the primary CTA for this article and is where the full nervous system framework is installed in five days. For ongoing sustained support, the Monthly Personal Training and Nutrition Coaching Program is the coaching option.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

How long does it take for vagus nerve reset exercises to work?

Acute effects on breath, heart rate, and subjective calm are often noticeable within the first session. Meaningful changes in HRV, sleep quality, and stress resilience generally develop over four to eight weeks of consistent daily practice. Deeper changes in mood, digestion, and inflammation continue to develop over three to six months.

Can I do all ten exercises every day?

You can, though most women do not need to. A daily practice of two to four exercises for a total of five to fifteen minutes produces the majority of the benefit. Reserve the longer practices like Yoga Nidra and cold face immersion for two or three days per week.

Are vagus nerve reset exercises safe during pregnancy?

Most of the exercises are safe during pregnancy with modification. Cold face immersion and breath retention practices need modification during pregnancy. Work with a prenatal-certified practitioner for individualized guidance.

What is the fastest vagus nerve reset for an anxiety spike?

Cold water face immersion (Exercise 2) produces the fastest acute parasympathetic shift. Extended exhalation breathing (Exercise 1) is the most accessible when cold water is not available. Both produce noticeable calming effects within one to three minutes.

Do I need any equipment?

None of the exercises require equipment beyond what you already have at home. A bowl for cold water, a wall for legs-up-the-wall, and a comfortable surface to lie on are the only items needed.

Can these exercises help with menopause symptoms?

Vagus nerve reset practices are one of the accessible interventions for the sleep disruption, anxiety, digestive changes, and stress reactivity that are common in perimenopause and menopause. They do not replace medical treatment when it is indicated, but they consistently produce meaningful improvement in the daily quality of life for women who practice them regularly. Discuss with your provider as part of a broader menopause management strategy.

Are these exercises safe for women with high blood pressure?

Most of the exercises are safe. Cold face immersion and breath retention practices need clinician approval for uncontrolled high blood pressure. Legs-up-the-wall may need modification for some blood pressure conditions. Extended exhalation breathing, humming, gargling, and the Rosenberg exercises are generally safe.

Can vagus nerve exercises help with sleep?

Regular daily practice consistently improves subjective sleep quality and overnight HRV in most practitioners. Evening-timed practices (extended exhalation, legs-up-the-wall, Yoga Nidra) are particularly effective for sleep onset. Multiple studies support the sleep-related effects of these categories of practice.

What is the difference between the vagus nerve and the parasympathetic nervous system?

The vagus nerve is the primary anatomical conduit of the parasympathetic nervous system, but the parasympathetic system also includes sacral nerves and some cranial nerves other than the vagus. In practice, the vagus nerve is where most of the parasympathetic activity happens, which is why vagus-focused practices are so effective.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Can I overdo vagus nerve exercises?

The exercises in this article are safe at reasonable daily volumes. Extremely long sessions of breath work or cold exposure can produce fatigue or over-activation of the parasympathetic system in sensitive individuals. If you notice excessive fatigue or lightheadedness during or after the practice, reduce the duration.

Do I need to see a therapist alongside these exercises?

For most women, the exercises can be practiced safely as a self-directed daily practice. For women with a history of significant trauma, PTSD, or severe anxiety, working with a trauma-informed therapist alongside the practice often produces better results and reduces the risk of trigger responses to interoceptive practices.

How do I know if my vagus nerve is working properly?

Higher heart rate variability, easy transitions between activation and rest, regular digestion, restorative sleep, resilient mood, and steady energy through the day are all signs of good vagal function. The signs listed in section 3 of this article are the common indicators of reduced vagal function.

Can I do these exercises at work?

Several of them are workable in an office setting. Humming can be done softly at your desk. Auricular massage takes three minutes. The Rosenberg Basic Exercise can be done during a break with the head resting on the desk on interlaced fingers. Extended exhalation breathing works anywhere.

Are the Stanley Rosenberg exercises safe for everyone?

The Basic Exercise and Half-Salamander are gentle and safe for most bodies. Anyone with significant neck injury, cervical spine surgery history, or acute pain should discuss with their healthcare provider before starting.

What if I do not feel a release response during the Basic Exercise?

Some people do not experience the spontaneous yawn or sigh in the first few sessions. Continue the practice for several weeks. Most people begin to experience the release response as the nervous system learns the pattern. If nothing changes after several weeks, that is not a failure. The other exercises may work better for your particular nervous system.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.


References

  • Porges, S. W. (2011). The Polyvagal Theory: Neurophysiological Foundations of Emotions, Attachment, Communication, and Self-Regulation. W. W. Norton.
  • Porges, S. W. (2017). The Pocket Guide to the Polyvagal Theory: The Transformative Power of Feeling Safe. W. W. Norton.
  • Rosenberg, S. (2017). Accessing the Healing Power of the Vagus Nerve: Self-Help Exercises for Anxiety, Depression, Trauma, and Autism. North Atlantic Books.
  • Laborde, S., Allen, M. S., Borges, U., et al. (2022). Effects of voluntary slow breathing on heart rate and heart rate variability: a systematic review and a meta-analysis. Neuroscience and Biobehavioral Reviews, 138, 104711.
  • Zaccaro, A., Piarulli, A., Laurino, M., et al. (2018). How breath-control can change your life: a systematic review on psycho-physiological correlates of slow breathing. Frontiers in Human Neuroscience, 12, 353.
  • Russo, M. A., Santarelli, D. M., & O’Rourke, D. (2017). The physiological effects of slow breathing in the healthy human. Breathe, 13(4), 298–309.
  • Bernardi, L., Sleight, P., Bandinelli, G., et al. (2001). Effect of rosary prayer and yoga mantras on autonomic cardiovascular rhythms: comparative study. BMJ, 323(7327), 1446–1449.
  • Kox, M., van Eijk, L. T., Zwaag, J., et al. (2014). Voluntary activation of the sympathetic nervous system and attenuation of the innate immune response in humans. Proceedings of the National Academy of Sciences, 111(20), 7379–7384.
  • Vickhoff, B., Malmgren, H., Åström, R., et al. (2013). Music structure determines heart rate variability of singers. Frontiers in Psychology, 4, 334.
  • Lundberg, J. O., Weitzberg, E., & Gladwin, M. T. (2008). The nitrate-nitrite-nitric oxide pathway in physiology and therapeutics. Nature Reviews Drug Discovery, 7(2), 156–167.
  • Telles, S., Nagarathna, R., & Nagendra, H. R. (1994). Breathing through a particular nostril can alter metabolism and autonomic activities. Indian Journal of Physiology and Pharmacology, 38(2), 133–137.
  • Yoo, H. J., Nashiro, K., Min, J., et al. (2022). Heart rate variability biofeedback increases vagal tone and improves cognitive function in older adults. Applied Psychophysiology and Biofeedback, 47(2), 129–142.
  • Yuan, H., & Silberstein, S. D. (2016). Vagus nerve and vagus nerve stimulation, a comprehensive review: Part I, II, and III. Headache: The Journal of Head and Face Pain, 56(1-3), 71–91, 259–266, 479–490.
  • Butt, M. F., Albusoda, A., Farmer, A. D., & Aziz, Q. (2020). The anatomical basis for transcutaneous auricular vagus nerve stimulation. Journal of Anatomy, 236(4), 588–611.
  • Streeter, C. C., Gerbarg, P. L., Saper, R. B., et al. (2012). Effects of yoga on the autonomic nervous system, gamma-aminobutyric-acid, and allostasis in epilepsy, depression, and post-traumatic stress disorder. Medical Hypotheses, 78(5), 571–579.
  • Datta, K., Tripathi, M., & Mallick, H. N. (2017). Yoga Nidra: an innovative approach for management of chronic insomnia. Sleep Science and Practice, 1(1), 7.
  • Pal, G. K., Velkumary, S., & Madanmohan. (2004). Effect of short-term practice of breathing exercises on autonomic functions in normal human volunteers. Indian Journal of Medical Research, 120(2), 115–121.
  • Gerritsen, R. J. S., & Band, G. P. H. (2018). Breath of life: the respiratory vagal stimulation model of contemplative activity. Frontiers in Human Neuroscience, 12, 397.
  • Bordoni, B., Marelli, F., Morabito, B., & Sacconi, B. (2018). Depression and anxiety in patients with chronic heart failure. Future Cardiology, 14(2), 115–119.
  • Woodyard, C. (2011). Exploring the therapeutic effects of yoga and its ability to increase quality of life. International Journal of Yoga, 4(2), 49–54.

Disclaimer: Always consult with a healthcare professional before starting any new routines, programs, or nutrition plans to ensure you receive the best medical advice and strategy for your specific individual needs.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.