Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How to Increase Bone Density After 40: 6 Exercises That Work (Videos)

Denise’s mother broke her hip getting out of a bathtub. No stairs. No major fall. Her foot caught the mat, and at sixty-eight, an emergency-room X-ray revealed bone loss that had been progressing quietly for years.

Denise is fifty-one now, and her own DEXA scan shows osteopenia at the hip. She was told to do “weight-bearing exercise,” so she started walking more. A good start, but not a complete plan.

Bone is constantly remodeling. During the menopause transition, falling estrogen can allow bone breakdown to outpace bone formation, increasing the importance of exercise that gives the skeleton enough mechanical stimulus to adapt.

And not all movement does that equally. Walking supports cardiovascular health, but on its own, it usually does not provide enough load to meaningfully improve bone density. This guide covers six exercise categories supported by research, how they load bone, and how to progress them safely over time.

Important: This article is educational and does not replace individualized medical advice. Women with osteoporosis, a prior fragility fracture, or significant balance concerns should speak with a physician or physical therapist before starting a new exercise program, especially higher-impact exercise.

Why Doesn’t Walking Alone Build Bone?

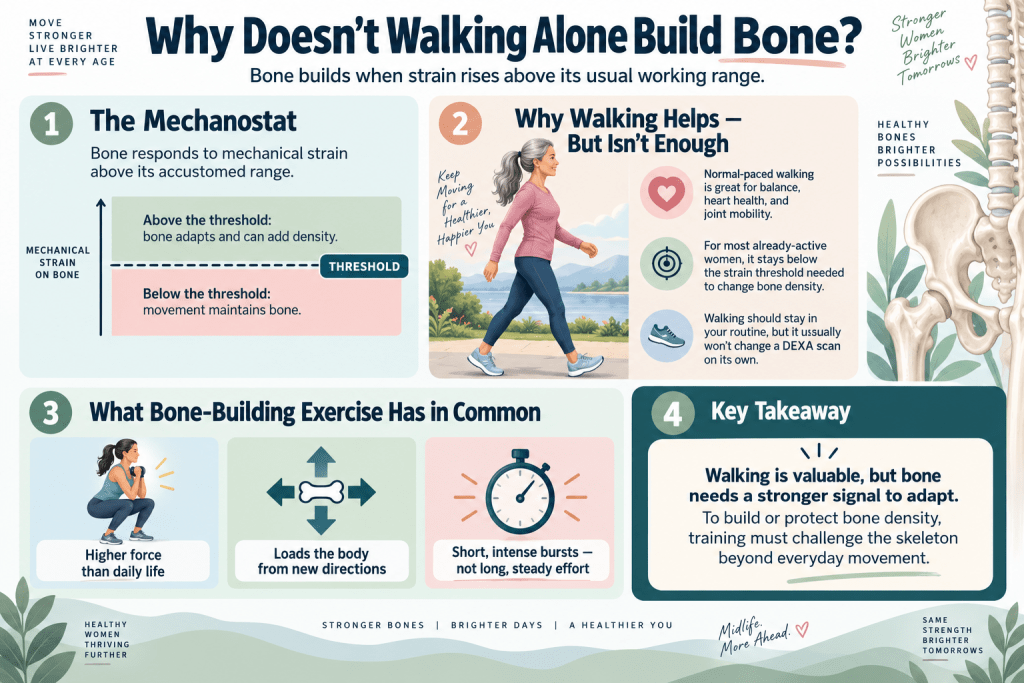
Bone responds to mechanical strain above its accustomed working range, a concept researchers call the mechanostat. Below a certain threshold of strain, a movement maintains bone. Above that threshold, bone adapts by adding density.
Why walking alone doesn’t build bone density

Walking at a normal pace, for most already-active women, sits below that threshold. It’s excellent for balance, cardiovascular health, and joint mobility, and it should stay part of any weekly routine, but it isn’t the lever that changes a DEXA scan on its own.

The exercises that do change bone density share three features: they load the skeleton with more force than daily life requires, they load it from directions the body isn’t used to, and they load it in short, intense bursts rather than long, steady efforts. The six categories below cover all three.

“I hear ‘I already walk 10,000 steps a day, isn’t that enough?’ constantly in coaching sessions. Walking is a wonderful habit and I’ll never discourage it, but if bone density is the specific goal, walking needs a partner, not a replacement. I learned this the hard way managing my own bone health after an early menopause diagnosis at 41. Cardio alone did nothing for my scan. Loading did.”

Terry Tateossian, Founder of The House of Rose

What Are the 6 Best Exercises for Building Stronger Bones After 40?

A complete bone-strengthening routine needs more than walking or light resistance work. These six exercise categories combine impact, progressive resistance, power, loaded movement, balance, and multi-directional loading to challenge the skeleton in different ways while also improving the strength and stability that help reduce fracture risk.

Six bone-strengthening exercises for women over 40

Exercise 1: High-Impact Loading (Jumping and Rebounding)

Why It Works

Ground reaction force, the force that travels back up through the skeleton on landing, is one of the most direct bone-building stimuli available. Jumping and rebounding generate that force in a low-injury-risk way because the landing is absorbed across both legs and, on a rebounder, across a surface with some give.

How to Do It

  • Start with 10-20 small jumps or rebounder bounces, feet staying close to the mat or floor
  • Progress to jumping jacks, higher-amplitude rebounder bounces, or jump rope as tolerance builds
  • Aim for 2-3 sessions per week, 5-10 minutes per session
  • Land softly through the whole foot, not just the toes, to protect the ankles and knees

Research on jump training protocols in postmenopausal women has found measurable hip bone density improvements from as few as 10-20 jumps performed several times per week over multiple months, with minimal injury risk when landings were performed correctly.

Important: Women with a current osteoporosis diagnosis, a recent fracture, or significant knee or hip joint damage should get clearance from a physician before beginning any jumping or rebounding protocol.

For a gradual progression from gentle health bounces to longer rebounder sessions, THOR’s rebounding guide provides a structured starting point for women in midlife.

Why Does the Rebounder Specifically Work for Sensitive Joints?

A mini trampoline absorbs a portion of the landing force before it reaches the joints, which lowers impact on the knees and hips relative to jumping on a hard floor while still generating enough ground reaction force to register as a bone-loading stimulus. This makes it a reasonable starting point for women who want the impact-loading benefit without the joint stress of running or floor-based jumping.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Exercise 2: Heavy Progressive Resistance Training

Why It Works

Muscle attaches to bone through tendon, and every contraction pulls on that attachment point. Heavier loads recruit more muscle fibers and pull harder on bone, which is why resistance training with real, progressively increasing weight outperforms light-weight, high-repetition training for bone density specifically.

How to Do It

  • Focus on compound, multi-joint movements: squats, deadlift patterns, rows, presses
  • Work in the 6-10 repetition range with a weight that feels truly challenging by the last 2 reps
  • Progress load every 2-3 weeks as the current weight starts to feel easier
  • Train 2-3 times per week, allowing 48 hours between sessions for the same muscle groups

A weight that feels “fine” for 15 easy repetitions isn’t doing the same job on bone as a weight that makes rep 8 hard. This is one of the most common mistakes in home workout routines: not lifting heavy enough to register as a novel stimulus.

Creatine monohydrate can help support the strength and training adaptations that make resistance exercise more effective, indirectly strengthening the bone-loading side of the equation.

For a deeper look at the research, dosing, and midlife-specific benefits, THOR’s guide to creatine for women over 40 breaks down the evidence, while Thorne Creatine provides a straightforward creatine monohydrate option for adding it to your daily routine.

Worked Example: Choosing a Starting Weight

Woman

Current Fitness

Starting Squat Load

Target Rep Range

New to resistance training

Never lifted weights

Bodyweight or empty barbell (bar only)

8-10 reps, focus on form

Some experience

Lifts occasionally, unsure of loads

Weight that feels moderate for 12 reps

8-10 reps, add 5 lbs when easy

Regular lifter

Trains 2x/week already

Weight that’s truly hard by rep 8

6-8 reps, progressive overload

Load Approach

Typical Rep Range

Bone-Building Signal

Light resistance bands, high reps

15-25 reps

Low, insufficient mechanical strain

Moderate dumbbells, muscle endurance focus

12-15 reps

Low to moderate

Heavy compound lifts, progressive overload

6-10 reps

High, this is the target zone

Bodyweight only, no added load

Varies

Low unless combined with impact or power work

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Exercise 3: Power-Based Training (Speed of Force)

Why It Works

Power, defined as force produced quickly rather than slowly, appears to matter for bone and for fall prevention in a way that slow strength training alone doesn’t fully replicate. Moving a weight or your own bodyweight explosively, even a small amount of weight, creates a different rate of loading on bone than moving it slowly.

How to Do It

  • Sit-to-stand transfers: Perform as quickly as control allows, 3 sets of 8-10.
  • Step-ups: Perform with an explosive push off the working leg, 3 sets of 8 per side.
  • Medicine ball chest passes: Perform against a wall, 3 sets of 10, focusing on speed of release.
  • Begin with bodyweight versions: Progress to external load once control and technique are established.

This category is frequently skipped entirely in midlife fitness routines because it looks less like traditional “toning” work, but the missing piece is often speed, not weight.

Understanding the difference between power and strength helps explain why lifting heavier is only part of the equation. Power training focuses on producing force quickly, which supports faster reactions, more responsive movement, and the ability to recover from an unexpected stumble.

“Clients are often surprised that ‘explosive’ doesn’t mean advanced or dangerous. A sit-to-stand performed a little faster than usual, with good form, is a completely appropriate starting point. I’ve coached hundreds of women through this exact progression, and the ones who stick with power work are almost always the ones who feel steadiest walking down stairs a few months later.”

Terry Tateossian, Founder of The House of Rose

Exercise 4: Axial Loading (Carries and Loaded Walking)

Why It Works

Carrying weight while walking loads the spine and hips through a vertical, compressive path, which is exactly the direction hip and spine fractures tend to occur from bone weakness. This category is under-used in most fitness programming despite being simple to add to an existing walking habit.

How to Do It

  • Farmer’s carries: Hold a moderately heavy dumbbell or kettlebell in each hand, walk 30-40 steps, rest, and repeat for 3-4 rounds.
  • Weighted vest walking: Start with 5-10% of bodyweight added and walk your normal route.
  • Single-arm suitcase carries: Use these to add a rotational stability demand.
  • Progress load gradually: Increase the load the same way as any resistance exercise.

Worked Example

A 150-pound woman starting weighted vest walking might begin with a 10-12 pound vest for two 20-minute walks per week, adding roughly 2-3 pounds every few weeks as the current load stops feeling challenging by the walk’s second half.

Bodyweight

Starting Vest Load (5-8%)

Progression Pace

130 lbs

7-10 lbs

+2 lbs every 3-4 weeks

150 lbs

8-12 lbs

+2-3 lbs every 3-4 weeks

170 lbs

9-14 lbs

+3 lbs every 3-4 weeks

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Exercise 5: Balance and Fall-Prevention Training

Why It Works

Bone density is only half of fracture risk. The other half is whether a fall happens at all. Balance training doesn’t build bone directly, but it reduces the single largest risk factor for the fractures that bone density work is trying to prevent, which makes it inseparable from a real bone health plan.

How to Do It

  • Single-leg stance: Work toward 30 seconds per side without support.
  • Tandem walking: Walk heel-to-toe across a room for 3-4 passes.
  • Standing on an unstable surface: Use a folded towel or balance pad while holding light support.
  • Practice near a counter or wall: Use nearby support for safety as difficulty increases.

THOR has a full testing and improvement protocol at Single-Leg Stance Test for Women Over 40, including how to track progress over time.

Why Does Balance Training Belong in a Bone Density Article?

It’s tempting to treat balance work as a separate category from “real” bone-building exercise, but the research on fracture prevention treats fall risk and bone strength as two sides of the same equation. A woman with excellent bone density who falls hard still fractures. A woman with lower bone density who never falls often doesn’t. Both matter, and neither replaces the other.

Exercise 6: Multi-Directional Loading

Why It Works

Most daily movement and most traditional exercise happens in a single plane, forward and back. Bone that’s only ever loaded in one direction adapts to that one direction and stays vulnerable to forces from the side, which is how many hip fractures actually happen, from a sideways stumble rather than a forward fall.

How to Do It

  • Lateral lunges: Perform 2-3 sets of 8-10 per side.
  • Diagonal step-and-reach patterns: Step at a 45-degree angle while reaching the opposite arm.
  • Side-stepping with a resistance band: Place the band around the ankles and perform 2-3 sets of 10 steps in each direction.
  • Curtsy lunges: Add these once basic lateral lunges feel controlled.

Muscle groups that support these multi-directional movements, particularly the hip abductors and rotators, are covered in Muscles That Matter Most for Aging Well.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Can You Put the Six Exercises Together in a Sample Week?
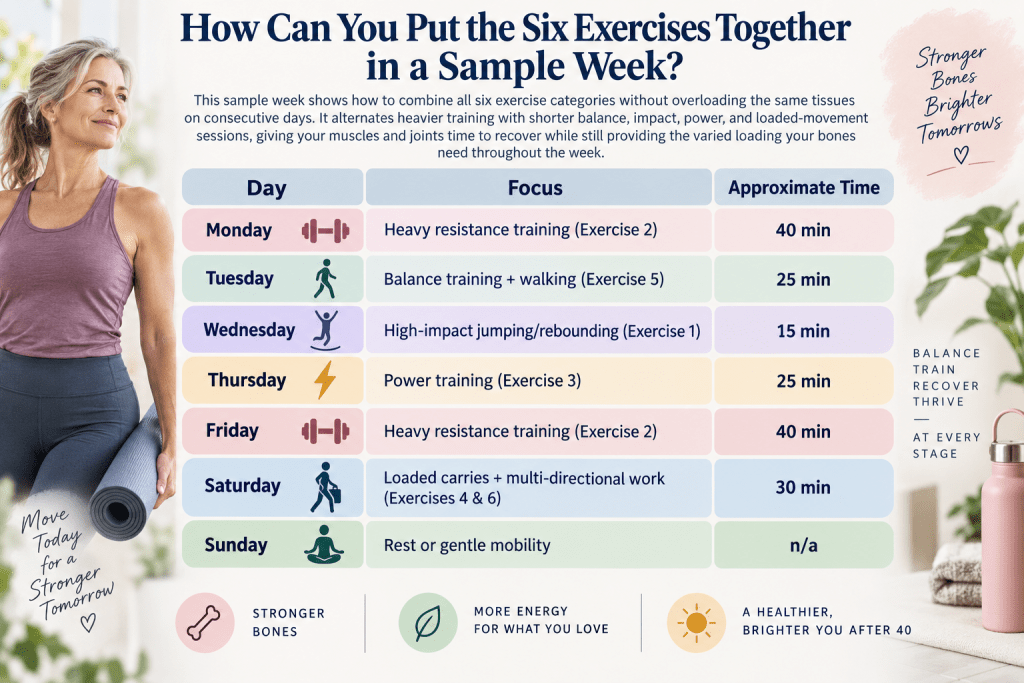
This sample week shows how to combine all six exercise categories without overloading the same tissues on consecutive days. It alternates heavier training with shorter balance, impact, power, and loaded-movement sessions, giving your muscles and joints time to recover while still providing the varied loading your bones need throughout the week.

Weekly bone-strength exercise plan for women over 40.

Day

Focus

Approximate Time

Monday

Heavy resistance training (Exercise 2)

40 min

Tuesday

Balance training + walking (Exercise 5)

25 min

Wednesday

High-impact jumping/rebounding (Exercise 1)

15 min

Thursday

Power training (Exercise 3)

25 min

Friday

Heavy resistance training (Exercise 2)

40 min

Saturday

Loaded carries + multi-directional work (Exercises 4 & 6)

30 min

Sunday

Rest or gentle mobility

n/a

This isn’t the only way to sequence these six categories, but it spaces heavy resistance days 48 hours apart and keeps impact work to days when joints feel fresh.

“I tell clients to think of this as a rotation, not a checklist to finish in one workout. Two categories done well on a given day beats all six done poorly. That’s the same principle I build every retreat program around at our Smoky Mountain property: fewer things, done with real intent, beats a packed schedule nobody can sustain once they go home.”

Terry Tateossian, Founder of The House of Rose

What Does the Research Actually Show?

Bone density research in midlife and postmenopausal women consistently points toward a few conclusions worth stating plainly, without overselling them:

  • Multi-component programs: Combining resistance training, impact loading, and balance work shows more consistent bone density benefits at the hip and spine than any single exercise type alone.
  • Loss rates during the menopause transition: These are real and measurable, but exercise-based interventions have shown the ability to slow that loss and, in some studies, modestly increase density at specific sites, particularly the hip.
  • Consistency over months and years: This matters more than any single “best” exercise. Bone remodeling is slow, and meaningful DEXA-detectable change typically takes 6-12 months of consistent training, not weeks.
  • Exercise does not replace medical evaluation: For women already diagnosed with osteoporosis, it’s a complement to, not a substitute for, whatever a physician recommends based on individual fracture risk and bone density scores.

Nutrition also plays a supporting role alongside training. Adequate protein intake supports the muscle side of the muscle-bone connection, and THOR’s free macro calculator can help set a personalized protein target to train against.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

When Should You Talk to a Doctor Before Starting?

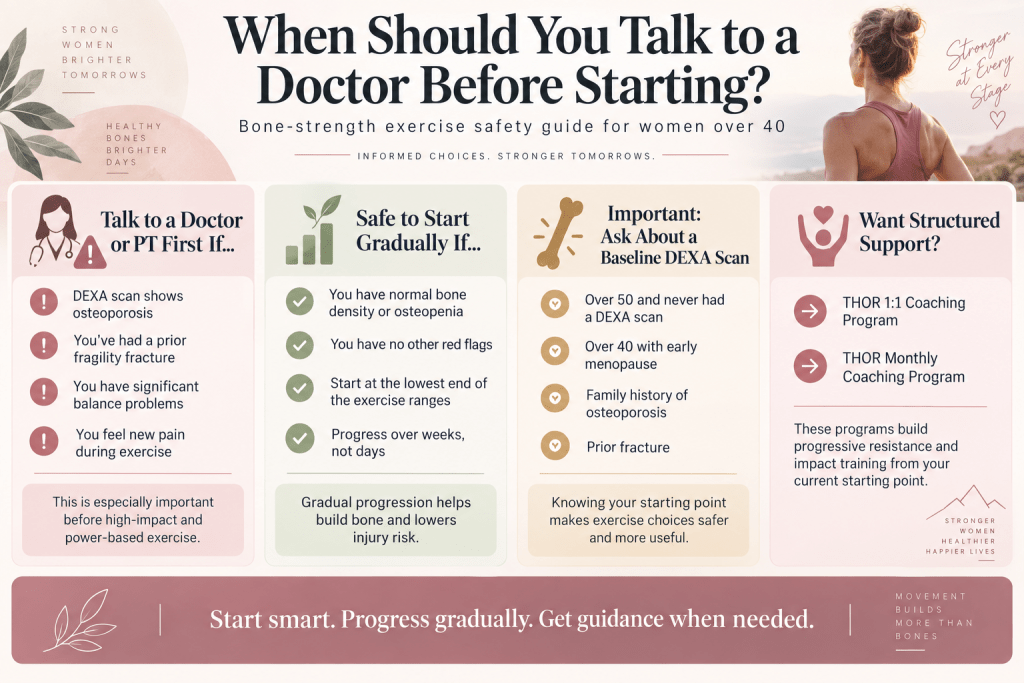
A DEXA scan showing osteoporosis, a prior fragility fracture, significant balance problems, or any new pain during exercise are all reasons to loop in a physician or physical therapist before starting a program like this one, particularly the high-impact and power categories.
When to see a doctor before bone exercise

For women with normal bone density or osteopenia and no other red flags, these categories are generally considered safe to begin gradually, but “gradually” is doing real work in that sentence. Starting at the lowest end of any of the ranges above and progressing over weeks, not days, is the difference between building bone and getting hurt.

Important: If you have never had a DEXA scan and are over 50, or over 40 with early menopause, a family history of osteoporosis, or a prior fracture, ask your doctor whether a baseline scan makes sense before starting a new training program. Knowing your starting point makes every exercise choice in this article more useful.

What Are Your Next Steps?

  1. If you’re over 50, or over 40 with early menopause or a family history of osteoporosis, ask your doctor about a baseline DEXA scan before starting.
  2. Pick two of the six exercise categories to start with this week, ideally one resistance-based and one impact or balance-based.
  3. Use THOR’s free macro calculator to set a protein target that supports the muscle-bone connection.
  4. Build toward the sample week above over 4-6 weeks, adding one category at a time rather than all six at once.
  5. Revisit this article every few months to check your progression against the load and rep ranges listed for each exercise.

Building bone density is not a single workout, it’s a rotation practiced consistently over months. For a done-for-you approach to structuring these six categories into a weekly plan tailored to your current fitness level, THOR’s 1:1 coaching program builds progressive resistance and impact training safely from wherever you’re starting.

Supporting nutrients for bone health, including calcium, vitamin D, and vitamin K2, are covered in THOR’s Advanced Bone Support formula, and pairing a training plan with real food is easiest with THOR’s Macro Miracle Mediterranean Cookbook, which was built around the same protein-forward approach this article recommends.

If you’re weighing a longer-term reset, THOR’s women’s yoga retreats build guided strength and movement programming, including several of the six categories above, into a supported week away.

Important: This article is educational and does not replace individualized medical advice. Please consult a physician before beginning a new exercise program, especially if you have an existing bone density diagnosis, a prior fracture, or a cardiovascular or joint condition.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

Can you really increase bone density after 40, or only slow the loss?

Both are possible, though slowing loss is the more common and more reliably documented outcome. Increases in bone density have been shown in research at specific sites, most consistently the hip, with consistent multi-component training over 6-12 months or longer.

Is rebounding as good as running for bone density?

Rebounding provides meaningful ground reaction force with lower impact on the joints than running on pavement, making it a reasonable substitute for women with joint concerns. Running on a hard surface may provide a stronger stimulus for some, but the injury tradeoff should factor into the decision.

How long before I’d see a difference on a DEXA scan?

Most research protocols run 6-12 months before rescanning, since bone remodeling is a slow process. A single month of consistent training won’t show up on a scan, but it’s still the month that starts the process.

Do I need weights, or can bodyweight exercises build bone density?

Bodyweight exercise can work for the impact and power categories (jumping, sit-to-stand speed work), but the heavy resistance category generally requires external load, since bodyweight alone stops providing a new stimulus once a woman is already strong enough to perform the movement easily.

Is walking with a weighted vest enough on its own?

It’s a strong addition to a walking habit and covers the axial loading category well, but it works best alongside resistance training and impact work rather than as a complete stand-alone bone density program.

What’s the difference between osteopenia and osteoporosis?

Osteopenia is a bone density measurement lower than normal but not low enough to meet the diagnostic threshold for osteoporosis. It’s often described as an early warning stage where lifestyle intervention, including the exercises in this article, has the most opportunity to change the trajectory before density drops further.

Can I do these exercises if I already have osteoporosis?

Some can be adapted, but high-impact jumping and certain power movements may need modification or physician clearance first, particularly if there’s been a prior fragility fracture. A physical therapist familiar with osteoporosis exercise guidelines can help tailor the six categories safely.

Does menopause hormone therapy affect how much exercise helps?

Hormone therapy addresses the estrogen side of bone loss directly, while exercise addresses the mechanical loading side. The two work through different pathways and are generally considered complementary rather than substitutes for one another, though any decision about hormone therapy should be made with a physician.

How many days a week is realistic for a beginner?

Three focused sessions a week, combining one resistance day, one impact or power day, and one balance-focused day, is a reasonable and sustainable starting point for someone new to structured bone-loading exercise.

Is it too late to start if I’m already in my sixties or seventies?

No. Research on exercise interventions in older postmenopausal women, including women in their seventies, has shown bone and fall-risk benefits from starting a structured program, though starting loads and progression pace should be more conservative and ideally supervised.

Do I need special equipment to get started?

A rebounder, a pair of moderate dumbbells, and a resistance band cover most of the six categories. None of it requires a full home gym, though a gym membership with access to a squat rack and heavier dumbbells allows more progression room over time.

What role does protein play in bone density specifically?

Protein supports the muscle mass that pulls on and loads bone during resistance and power training, making adequate intake a supporting factor rather than a direct bone-building mechanism on its own. THOR’s free macro calculator can help set a personalized target.

Should I do cardio at all if I’m focused on bone density?

Cardiovascular exercise remains important for heart health and should stay in a weekly routine, but it should sit alongside, not instead of, the six loading categories in this article if bone density is a specific goal.

Can supplements replace exercise for bone density?

No. Supplements such as calcium, vitamin D, and vitamin K2 support the raw materials bone needs to remodel, but without a mechanical loading stimulus from exercise, those raw materials have less signal telling the body where to direct them.

References

  • Finkelstein, J.S., et al. “Bone mineral density changes during the menopause transition in a multiethnic cohort of women.” Journal of Clinical Endocrinology & Metabolism.
  • Frost, H.M. “Bone’s mechanostat: a 2003 update.” The Anatomical Record.
  • Bailey, C.A., & Brooke-Wavell, K. “Optimum frequency of exercise for bone health: randomised controlled trial of a high-impact unilateral intervention.” Bone.
  • Multicomponent exercise interventions and bone mineral density outcomes in postmenopausal women, systematic review data.
  • Watson, S.L., et al. “High-intensity resistance and impact training improves bone mineral density and physical function in postmenopausal women with osteopenia and osteoporosis: the LIFTMOR randomized controlled trial.” Journal of Bone and Mineral Research.
  • Power training versus traditional strength training outcomes in fall risk and functional performance in older adults, comparative training studies.
  • Farmer’s carry and axial loading biomechanics research on spinal and hip compressive load patterns.
  • Sherrington, C., et al. “Exercise for preventing falls in older people living in the community.” Cochrane Database of Systematic Reviews.
  • National Osteoporosis Foundation clinician’s guide to prevention and treatment of osteoporosis.
  • Mayo Clinic patient education materials on osteoporosis exercise recommendations and safety guidelines.
  • Cleveland Clinic patient education materials on bone density and weight-bearing exercise.
  • Vainionpää, A., et al. “Effect of impact exercise on bone mineral density in premenopausal women: a 10-year follow-up study.” Osteoporosis International.
  • Beck, B.R., et al. “Exercise and bone health in postmenopausal women.” Journal of Science and Medicine in Sport.
  • Zhao, R., et al. “Efficiency of jumping exercise in improving bone mineral density among premenopausal women: a meta-analysis.” Sports Medicine.
  • Giangregorio, L.M., et al. “Too Fit To Fracture: exercise recommendations for individuals with osteoporosis or osteoporotic vertebral fracture.” Osteoporosis International.
  • National Institute on Aging patient guidance on exercise, balance, and fall prevention in older adults.

Disclaimer: This article is educational and does not constitute medical advice. Bone-loading exercises such as jumping, rebounding, heavy resistance training, power movements, and weighted carries require appropriate progression and may not be suitable for everyone. If you have osteoporosis, osteopenia with additional risk factors, a prior fragility fracture, significant balance problems, cardiovascular or joint conditions, or new pain with exercise, consult a physician or physical therapist before starting the framework in this article.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Strength Training for Women Over 40 – A Complete Guide

If a doctor handed you a prescription that lowered your risk of fractures, helped you sleep, kept your blood sugar in check, made your clothes fit better, slowed cognitive decline, and added healthy years to the back end of your life – you’d take it. You’d take it twice a day if they asked you to.

That prescription exists. It’s strength training.

I’m not exaggerating. The evidence on strength training for women over 40 is now strong enough that the American College of Sports Medicine, the American Heart Association, the U.S. Department of Health and Human Services, and the North American Menopause Society all recommend resistance exercise at least twice a week for adults — and the case for women in midlife is the clearest of all because of what’s happening with estrogen.

Here’s the part most women over 40 weren’t told: in your 40s and 50s, the loss of estrogen accelerates the loss of both muscle and bone. You can lose 3% to 8% of your muscle mass per decade after 30, and that rate speeds up after menopause if you do nothing about it. Bone density follows a similar curve. The good news – the part that should make you cancel everything and get to a gym this week – is that strength training is the single most effective intervention we have for slowing, stopping, and in many cases reversing both of those losses.

This guide is everything I wish someone had handed me when I started lifting in midlife. We’ll cover what’s happening to your body and why lifting is the answer, the four lifts that matter most, how often to train, how heavy to go, what to eat, what changes after menopause, and the mistakes that send most women back to the elliptical. By the end of this, you’ll have a real plan you can start this week.

Free macro calculator for midlife menopause women over 50

What Strength Training Actually Means (and What It Doesn’t)

Strength training, also called resistance training or weightlifting, is any form of exercise where you make your muscles work against an external load. That load can be a barbell, dumbbells, kettlebells, resistance bands, machines, or your own body weight in moves like push-ups, squats, and pull-ups.

It is not the same as cardio. Cardio trains your heart and lungs. Strength training trains your muscles, your bones, your nervous system, and your metabolic machinery. You need both, but for women over 40, the strength side is the one that’s been chronically underdosed.

It’s also not the same as the “toning” workouts most of us were sold in our 20s and 30s — light pink dumbbells, 3 sets of 15, candle-lit yoga blocks. Those workouts feel productive. They build very little. To trigger the adaptations we want — more lean mass, stronger bones, better insulin sensitivity, a metabolism that doesn’t quit — the muscle has to be challenged. That means loads heavy enough that the last 1 to 3 reps of a set are genuinely hard.

If “lifting heavy” makes you nervous, stay with me. Heavy is relative. For a woman who hasn’t lifted in years, a 10-pound dumbbell can be heavy enough to start. We’re going to build you up.

Why Strength Training for Women Over 40 Is a Different Conversation

Three things change in your 40s and 50s that make strength training non-negotiable, not optional.

1. Estrogen drops, and estrogen is anabolic.

Estrogen helps you build and keep muscle. As ovarian estrogen production declines through perimenopause and into menopause, the rate of muscle protein synthesis falls and the rate of muscle breakdown rises. Without resistance training to push back, the math goes the wrong way fast. A 2019 review in the journal Maturitas summarized this as a state of “anabolic resistance” — meaning your muscles become harder to build, which means you have to send a stronger signal to wake them up. Lifting is that signal.

2: Bone density falls off a cliff.

Women lose roughly 10% of their bone mass in the five years surrounding menopause, and the loss continues at about 1% to 2% per year afterward. Bones, like muscles, respond to load. They get stronger when you put force through them and weaker when you don’t. The exercise types that build bone are the ones with the highest forces — heavy resistance training, jumping, and impact. Walking is wonderful for many things, but it does almost nothing for bone density once you’re past 40.

3: Insulin sensitivity declines.

As muscle mass shrinks, your body’s biggest glucose sink shrinks with it. Less muscle means more circulating blood sugar, more insulin, and a metabolism that’s increasingly geared toward storage. This is part of why so many women in midlife find themselves gaining weight on the same diet that used to maintain them. More muscle is more glucose disposal. More muscle is a better metabolism, full stop.

Add the mood, sleep, cognitive, and longevity benefits on top, and the picture becomes clear: strength training isn’t a vanity workout for midlife women. It’s healthcare.

The Benefits of Strength Training for Women Over 40, Backed by Research

Let me run through what the science actually shows. None of this is theoretical.

Lean muscle mass.

A 2018 systematic review in Sports Medicine found that resistance training in postmenopausal women produced significant increases in lean mass, with the largest effects when training was at least twice weekly with progressive overload (meaning the weights got heavier over time). Even women in their 60s, 70s, and 80s built measurable muscle.

Bone density.

A 2018 study in the Journal of Bone and Mineral Research (the LIFTMOR trial) had postmenopausal women with low bone density perform high-intensity resistance and impact training twice a week for eight months. Lumbar spine bone density increased 2.9%, hip strength improved, and there were no fractures. Standard “low-impact, light-weight” exercise programs in comparison studies typically show no improvement in bone density at all.

Body composition.

Women who lift while in a calorie deficit lose more fat and preserve more muscle than women who only do cardio in the same deficit. A 2017 American Journal of Clinical Nutrition trial in midlife women showed strength training plus a moderate deficit produced better body-composition outcomes than diet alone.

Insulin sensitivity and blood sugar.

Resistance training improves glucose disposal independent of weight loss. A 2017 meta-analysis in Diabetes Care found significant improvements in HbA1c, fasting glucose, and insulin sensitivity in adults doing structured resistance training.

Cardiovascular health.

A 2019 Medicine and Science in Sports and Exercise study tracking nearly 13,000 adults found that even an hour or less of strength training per week reduced cardiovascular event risk by 40% to 70%, independent of cardio. An hour. Per week.

Mental health.

A 2018 JAMA Psychiatry meta-analysis of 33 trials found resistance training significantly reduced depressive symptoms in adults, with effect sizes comparable to many pharmacologic interventions.

Cognitive function.

Resistance training has been shown to improve executive function, working memory, and processing speed in older adults — including in randomized trials in women.

Longevity and frailty.

Grip strength is one of the most reliable predictors of all-cause mortality in adults over 50. Stronger people live longer. They also stay independent longer and recover from illness faster.

If you read all that and feel a small surge of “why didn’t anyone tell me this,” you’re not alone. Most of this research is recent enough that it didn’t make it into the cardio-first messaging most of us absorbed in our 20s.

Free macro calculator for midlife menopause women over 50

How to Start Strength Training Over 40 (When You’ve Never Lifted Before)

Here’s the uncomfortable truth that nobody puts on Instagram: starting is the hardest part. Once you’ve trained for six months, the workouts run on momentum. Months one through three are where almost everyone quits. Plan for that.

Week one: keep it stupidly simple.

Two short sessions, 25 to 30 minutes each, on non-consecutive days. Pick five compound movements — one squat pattern, one hinge pattern, one upper-body push, one upper-body pull, one core. That’s it. Three sets of 8 to 12 reps for each. Use weights light enough that you finish each set with 2 to 3 reps in the tank. Track what you did.

Weeks two through four: add weight slowly.

Add a small amount of weight (or one rep per set) any time the previous session felt easier than a 7 out of 10. Do not skip ahead. Do not try to copy what you see on TikTok.

Months two and three: stretch the sessions.

Sessions can grow to 45 minutes. You can add a third weekly session if you have the time and recovery is good. Start to push some working sets closer to a 9 out of 10 — meaning you finish with 1 rep in the tank, not 3.

Months four through six: introduce structured progression.

This is where periodization (planned increases in volume or intensity) starts to matter. This is also typically where a coach pays for itself, because the difference between someone who keeps progressing and someone who plateaus at month four is almost always programming.

If you want a structured framework rather than figuring this out alone, Age With Strength is the 16-week 1:1 coaching program we built for exactly this stage. It’s not a generic plan — it’s programming, nutrition, and accountability calibrated to where you actually are.

For exercise selection within those compound patterns, our existing guides on the deadlift, the Romanian deadlift, the barbell squat, the bench press, the hip thrust, and the pull-up walk you through proper technique on each one.

The Four Lifts That Matter Most for Women Over 40

If I could only pick four exercises for a midlife woman, I’d pick these four. Master them and you cover almost every joint, every major muscle group, and every functional movement pattern you’ll need in daily life.

The squat. The single best lift for legs, glutes, and trunk strength. It also builds bone density in the hip and lumbar spine — the two most common fracture sites in older women. Start with bodyweight, progress to goblet squats with a dumbbell, then to back squats with a barbell when your form is solid. Our barbell squats guide walks through the muscles worked and the cues that matter.

The deadlift. The single best lift for posterior chain — glutes, hamstrings, lower back, mid-back, grip. The deadlift teaches you how to pick things up off the floor without hurting yourself, which becomes more important every year. Start with a Romanian deadlift (less technical, easier on the lower back), progress to a conventional or trap-bar deadlift. The deadlift guide and the Romanian deadlift guide cover both.

The press (push). The single best lift for upper-body pushing strength — chest, shoulders, triceps. Start with push-ups (kneeling or against a wall is fine), then dumbbell bench press, then barbell bench press if you have access. Overhead pressing builds shoulder stability and is gold for shoulder health as you age. Bench press fundamentals covers the basics.

The row or pull-up (pull). The single best lift for upper-body pulling strength — upper back, lats, biceps, posterior shoulder. This one matters extra for women over 40 because most of us spend our days hunched over a phone or a laptop, and pulling exercises pull our shoulders back where they belong. Start with assisted band rows or dumbbell rows, work toward pull-ups over time.

Add a hip thrust and a few core exercises (planks, dead bugs, suitcase carries) and you have a complete program. If you don’t have access to a gym, our no equipment, no problem guide and the home gym guide cover bodyweight progressions and how to outfit a small space at home.

How Often Should Women Over 40 Lift Weights?

The research-backed answer is two to four sessions per week. The honest answer is more nuanced.

Two sessions per week is the floor. Most studies showing meaningful gains in muscle, bone, and strength use a minimum of two weekly sessions. Below that, the signal isn’t strong enough to drive consistent adaptation. If you can only do two, do two — and make them count.

Three sessions per week is the sweet spot. Three full-body sessions (or a two-day upper/lower split with one extra session) is where most midlife women see the best return on time. Two days off between hard sessions is enough recovery for most.

Four sessions per week is for people who already have a base. If you’ve been training for a year or more, splitting your week into four sessions (often upper/lower or push/pull/legs) lets you spread volume more evenly and recover better than three longer sessions would.

What about lifting every day? You can — but the daily sessions need to be either short and skill-focused, or rotate which muscle groups are worked. Pounding the same muscles every day with no rest is how you end up injured at 47.

A note on cardio: you should do some. Zone-2 walking or easy jogging two to three times a week, plus one short higher-intensity session, plays nicely with strength training without eating into recovery. Our cardio zones cheat sheet lays out the framework.

How Heavy Should Women Over 40 Lift?

Heavier than you think. Lighter than the worst-case scenario in your head.

The research on hypertrophy (muscle growth) shows you can build muscle effectively anywhere in the 6 to 30 rep range, as long as you take sets close to failure. For most midlife women new to lifting, the 8 to 12 rep range is the sweet spot — heavy enough to build strength and muscle, light enough that form holds up, and forgiving enough to learn the lifts safely.

Here’s a simple calibration: pick a weight where the last 1 to 3 reps of a set feel hard. If you finish a set and feel like you could have done 5 more reps, the weight is too light. If your form breaks down on rep 6, the weight is too heavy. If you finish on a hard but clean rep 10, that’s the right weight for today.

The other piece is progressive overload — over weeks and months, the weights need to creep up. Either add a small amount of weight, or do one more rep at the same weight, or do one more set, or take less rest between sets. Some week, every few weeks, something should be harder than it was last time. Without progressive overload, the body has no reason to keep adapting.

Strength Training and Menopause: What Actually Changes

A lot of midlife women come to lifting through perimenopause. The body that responded to one thing in your 30s now seems to respond to something else, and the workouts that used to leave you feeling great suddenly leave you exhausted and inflamed. This is real, it’s hormonal, and it changes what strength training looks like.

Recovery slows down.

Estrogen has anti-inflammatory effects and supports muscle repair. As estrogen drops, recovery from hard sessions takes longer. The fix isn’t to train less — it’s to recover better. That means sleep, protein, and not stacking three hard sessions back-to-back. We cover the recovery piece more thoroughly in our perimenopause weight gain guide.

Volume matters more than intensity for most.

Going to absolute failure on every set chews up midlife women faster than it does someone in their 20s. Most women in perimenopause and menopause do better leaving 1 to 2 reps in the tank and accumulating slightly more total volume.

Protein matters more than ever.

Anabolic resistance means you need more protein to trigger the same muscle-building response — generally 0.7 to 1.0 grams per pound of bodyweight, with 30 to 40 grams per meal. We dig into this in the midlife nutrition hierarchy and protein sources guide.

Sleep, stress, and alcohol have outsized effects.

A bad week of sleep used to mean a bad workout. Now it means a week of bad workouts. Alcohol, which used to bounce off you, now wrecks your recovery and your hormones in ways that show up the next day. The brutal truth is that the lifestyle that worked at 32 doesn’t work at 48 — see our alcohol and menopause and sleep coverage for why.

Your cycle, while you still have one, affects how you feel.

Strength tends to peak in the follicular phase (the first half of your cycle) and dip in the late luteal phase. None of this means you can’t train — it means you might give yourself more grace on the harder weeks.

Free macro calculator for midlife menopause women over 50

Nutrition That Supports Strength Training in Midlife

You cannot out-train poor nutrition past 40. The mileage you used to get from “eat a little less and move a little more” stops working. What replaces it is structured eating that supports the work you’re doing in the gym.

Protein first.

Aim for 0.7 to 1.0 g per pound of bodyweight per day, distributed across 3 to 4 meals of roughly 30 to 40 g each. Lean meats, fish, eggs, dairy, soy, legumes, and protein powders all count. Whey protein digests fast and is well-supported as a post-workout option.

Enough total calories.

This is where most midlife women undereat. Chronic restriction makes you weaker, not leaner. If you’ve been dieting for years, the move is often reverse dieting before you try to build, then a focused building phase, then a controlled cut.

Carbohydrates around training.

Carbs fuel your sessions and replenish muscle glycogen afterward. Eat them. The “low-carb plus heavy training” combo is a classic midlife trap.

Creatine.

The most well-researched supplement in sports nutrition, and one of the few that’s been specifically studied in postmenopausal women. Three to five grams per day, every day, supports strength and lean mass gains. Read creatine for women over 40 for the full breakdown.

Use the calculator.

Before guessing at any of this, run your numbers through our free menopause protein macro calculator — it gives you protein, carb, and fat targets calibrated to your weight, age, and training schedule.

For a deeper food framework, the Macro Miracle Mediterranean Cookbook is built around exactly this — high-protein, macro-friendly, anti-inflammatory eating that supports a midlife woman who’s actually training.

Common Mistakes That Sabotage Strength Training Over 40

I see the same mistakes over and over. Avoiding these will put you ahead of 80% of women your age in the gym.

Mistake 1: lifting too light, too long.

The 5-pound pink dumbbell trap. If your sets always feel easy, you’re not training — you’re rehearsing.

Mistake 2: lifting too heavy, too soon.

The other side of the same coin. Form before load, always. A back tweak at 47 takes 8 weeks to heal and ruins your training block.

Mistake 3: chasing soreness instead of progress.

Soreness is not a reliable signal of a productive workout. Progressive overload is.

Mistake 4: doing too much cardio alongside lifting.

If you’re lifting hard three days a week, the answer is not also doing 90-minute cardio sessions four other days. You’ll undercut recovery and stall every other goal.

Mistake 5: skipping the warm-up.

Five minutes of mobility, two warm-up sets, then your working sets. Cold lifting at 47 is how you end up with shoulder pain at 48.

Mistake 6: not eating enough protein.

Half the women I talk to are eating 60 grams of protein a day and wondering why they’re not building muscle. Sixty grams is not enough. Get to 100+, then 130+, and watch what changes.

Mistake 7: program-hopping.

Switching programs every two weeks because the new one looked exciting on Instagram. You can’t outrun consistency. Pick one program, run it for at least 8 weeks, evaluate honestly, then change one thing.

Mistake 8: training through pain.

“Pushing through” something sharp or persistent is how injuries become chronic. Pain that doesn’t resolve in 2 to 3 days needs attention.

Free macro calculator for midlife menopause women over 50

A Sample Week of Strength Training for Women Over 40

Here’s what a beginner-friendly week looks like in practice.

Monday — full body A

Goblet squat: 3 sets of 8 to 10 – Romanian deadlift: 3 sets of 8 to 10 – Dumbbell bench press: 3 sets of 8 to 10 – One-arm dumbbell row: 3 sets of 8 to 10 each side – Plank: 3 sets of 30 to 45 seconds

Wednesday — full body B

Hip thrust: 3 sets of 10 to 12 – Bulgarian split squat: 3 sets of 8 to 10 each leg – Dumbbell shoulder press: 3 sets of 8 to 10 – Lat pulldown or band pulldown: 3 sets of 10 to 12 – Dead bug: 3 sets of 8 each side

Friday — full body A (or B again, alternate)

Same as Monday or Wednesday, alternating week to week

On the other days: walking, easy yoga, mobility, restorative work, or rest. One zone-2 cardio session of 30 to 45 minutes per week is plenty when you’re starting.

Six weeks of that, with progressive overload, is enough to feel different in your body. Twelve weeks is enough to see it in the mirror. Twenty-four weeks is enough to change your bone density numbers on a scan.

When to Hire a Coach (and When You Don’t Need To)

A coach is worth it when: – You’re new to lifting and want to skip 6 months of trial and error. – You’ve been training for a while and have plateaued. – You’re navigating perimenopause or menopause and want a programming and nutrition setup calibrated to that. – You need accountability — meaning you know what to do and you’re not doing it.

A coach is not worth it when: – You’re 8 weeks in, you’re progressing, and you’re enjoying it. Keep going. – You’re shopping for a coach as a way to avoid actually starting.

If you fall in the first group, Age With Strength is the 16-week 1:1 coaching program built specifically for midlife women starting or restarting strength training.

Frequently Asked Questions: Strength Training for Women Over 40

At what age should women start strength training?

Yesterday. Failing that, today. There’s no minimum age and no upper age — randomized trials in women in their 80s and 90s show meaningful gains in strength, balance, and bone density. The earlier you start, the bigger the bank you build, but it’s never too late. The biggest predictor of where you end up at 80 is what you’re doing at 50.

Will strength training make women over 40 bulky?

No. Building “bulky” muscle requires testosterone levels you don’t have, calorie surpluses you’re probably not in, and training volume far beyond what most midlife women do. What strength training will do is replace some of the soft tissue you’ve been losing with denser, more functional muscle. Most women report feeling smaller and more toned after they start lifting, even when their weight on the scale stays the same — because muscle is denser than fat.

How long does it take to see results from strength training over 40?

Strength gains in the first 6 to 8 weeks are mostly neurological — your brain getting better at recruiting muscle. You’ll feel stronger before you look different. Visible body composition changes typically show up between weeks 8 and 16 with consistent training and adequate protein. Bone density changes take 6 months or longer to register on a scan. Patience is part of the program.

Is it safe to lift heavy weights after 40?

Yes — with good technique. The 2018 LIFTMOR trial put postmenopausal women with low bone density through high-intensity deadlifts, squats, and overhead presses for 8 months with no fractures and significant improvements in bone density. The risk of not lifting heavy at this stage of life is much greater than the risk of lifting heavy with proper form.

How many days a week should a woman over 40 lift?

Two days a week is the floor. Three days a week is the sweet spot for most. Four is appropriate for women with a year or more of training behind them. Going beyond four full sessions per week without strategic programming is usually a recipe for burnout in midlife.

Do I need a gym, or can I strength train at home?

You can do real, productive strength training at home with a few pieces of equipment — adjustable dumbbells, a bench, a pull-up bar, and resistance bands cover most of what you’d need for years. A gym makes barbell training easier and gives you heavier loads for the lifts where that matters most (squat and deadlift). Both work. Our home gym guide and no equipment guide cover both setups.

What about strength training during perimenopause specifically?

Two key adjustments: prioritize recovery (sleep, protein, not stacking too many hard sessions), and accept that your week-to-week capacity will fluctuate more than it used to. Some weeks you’ll PR. Some weeks you’ll feel like everything weighs more than it did. Both are normal. The women who keep training through perimenopause come out the other side stronger than they went in.

Should women over 40 do more reps with lighter weights or heavier weights with fewer reps?

For general strength and muscle, 8 to 12 reps with weights heavy enough that the last 1 to 3 reps are hard is the sweet spot. For bone density specifically, lower-rep, heavier work (4 to 6 reps) is more potent. Most well-designed programs include some of both across the week.

Will strength training help with menopause symptoms?

Yes — directly and indirectly. Resistance training has been shown to improve sleep, mood, hot flash frequency in some studies, body composition, and insulin sensitivity, all of which interact with menopausal symptoms. The mechanisms include better blood sugar regulation, improved nervous system function, and the simple confidence boost of getting visibly stronger during a season when so much else feels out of your control.

What should I eat before and after strength training over 40?

A small protein-and-carb meal 1 to 2 hours before training (oatmeal with Greek yogurt, eggs and toast, a smoothie). Within an hour or two after, another meal with at least 30 to 40 grams of protein and some carbs to refill glycogen. Hydration matters too — most women in midlife are slightly under-hydrated. Use our free macro calculator to set your daily targets first.

Is creatine safe for women over 40?

Yes. Creatine is one of the most-studied supplements in sports science, with consistent safety data including in postmenopausal women. Three to five grams per day supports strength gains, lean mass, and (in newer research) brain function. Full breakdown in our creatine guide.

Can strength training reverse osteoporosis?

Strength training, especially heavy and high-impact resistance training, can increase bone mineral density and reduce fracture risk in postmenopausal women — even those with osteopenia and osteoporosis. The LIFTMOR trial showed measurable improvements at the spine and hip in 8 months. Whether you can fully reverse a diagnosis depends on starting point, severity, and program adherence, but you can almost always improve from where you are.

The Bottom Line on Strength Training for Women Over 40

The single most powerful thing a woman over 40 can do for her future health is build and keep muscle. Strength training is the tool. Two to three sessions a week, for the rest of your life, is the dose. Compound lifts, progressive overload, enough protein, and enough recovery is the program.

You don’t need to do this perfectly. You don’t need to start with a barbell. You don’t need a fancy gym or a coach you can’t afford. You need to start, and you need to keep going.

If you want a structured 16-week framework with accountability built in — programming, nutrition, and check-ins calibrated to where you actually are — Age With Strength is built for this. If you want the food side dialed in first, run your numbers through the free macro calculator and grab the Macro Miracle Mediterranean Cookbook for 80 high-protein recipes that fit a real lifting week.

The women who will be strong at 70 are training right now. Your 70-year-old self is watching.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.

Sources & References

  1. Wolfe RR. The underappreciated role of muscle in health and disease. American Journal of Clinical Nutrition. 2006;84(3):475-482.
  2. Volpi E, Nazemi R, Fujita S. Muscle tissue changes with aging. Current Opinion in Clinical Nutrition and Metabolic Care. 2004;7(4):405-410.
  3. Maltais ML, Desroches J, Dionne IJ. Changes in muscle mass and strength after menopause. Journal of Musculoskeletal and Neuronal Interactions. 2009;9(4):186-197.
  4. Nedergaard A, Henriksen K, Karsdal MA, et al. Menopause, estrogens and frailty. Gynecological Endocrinology. 2013;29(5):418-423.
  5. Watson SL, Weeks BK, Weis LJ, et al. High-intensity resistance and impact training improves bone mineral density and physical function in postmenopausal women with osteopenia and osteoporosis: the LIFTMOR randomized controlled trial. Journal of Bone and Mineral Research. 2018;33(2):211-220.
  6. Cermak NM, Res PT, de Groot LC, et al. Protein supplementation augments the adaptive response of skeletal muscle to resistance-type exercise training: a meta-analysis. American Journal of Clinical Nutrition. 2012;96(6):1454-1464.
  7. Liu Y, Lee DC, Li Y, et al. Associations of resistance exercise with cardiovascular disease morbidity and mortality. Medicine and Science in Sports and Exercise. 2019;51(3):499-508.
  8. Gordon BR, McDowell CP, Hallgren M, et al. Association of efficacy of resistance exercise training with depressive symptoms: meta-analysis and meta-regression. JAMA Psychiatry. 2018;75(6):566-576.
  9. Strasser B, Pesta D. Resistance training for diabetes prevention and therapy: experimental findings and molecular mechanisms. BioMed Research International. 2013;2013:805217.
  10. Westcott WL. Resistance training is medicine: effects of strength training on health. Current Sports Medicine Reports. 2012;11(4):209-216.
  11. Devries MC, Phillips SM. Supplemental protein in support of muscle mass and health: advantage whey. Journal of Food Science. 2015;80(S1):A8-A15.
  12. Candow DG, Forbes SC, Chilibeck PD, et al. Effectiveness of creatine supplementation on aging muscle and bone. Journal of Clinical Medicine. 2019;8(4):488.
  13. Smith-Ryan AE, Cabre HE, Eckerson JM, Candow DG. Creatine supplementation in women’s health: a lifespan perspective. Nutrients. 2021;13(3):877.
  14. Beck BR, Daly RM, Singh MA, Taaffe DR. Exercise and Sports Science Australia (ESSA) position statement on exercise prescription for the prevention and management of osteoporosis. Journal of Science and Medicine in Sport. 2017;20(5):438-445.
  15. Cruz-Jentoft AJ, Sayer AA. Sarcopenia. The Lancet. 2019;393(10191):2636-2646.
  16. Phillips SM, Chevalier S, Leidy HJ. Protein “requirements” beyond the RDA: implications for optimizing health. Applied Physiology, Nutrition, and Metabolism. 2016;41(5):565-572.