Free 28-Day Fascia Reset Email Course
Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
The Menopause Fitness Truth: Five Common Myths That Are Wasting Midlife Women’s Time and Money (And What the Research Shows)
Menopause is finally receiving the health attention it has long deserved. Perimenopause and menopause are major physiological transitions, yet women’s symptoms were dismissed or minimized by conventional medicine for decades.
However, this growing attention has also created a crowded market filled with fear-based claims, cherry-picked research, overpriced supplements, and fitness advice that does not match the evidence. Midlife women deserve better than marketing designed to make them feel broken.
I am Terry Tateossian, founder of The House of Rose and a certified lifestyle medicine coach. I built THOR after experiencing early-onset menopause at 41, an 80-pound midlife body composition shift, and 25 years of running businesses while raising two children.
Through coaching clients and hosting yoga retreats for women in perimenopause, menopause, and post-menopause, I have seen the difference between what research supports and what the wellness industry sells. This guide examines five persistent menopause fitness myths, the evidence behind them, the marketing tactics used to mislead women, and the practical framework that produces results.
The truth is more hopeful than the marketing suggests. Menopause is not a metabolic apocalypse and it’s not a diagnosis. Research supports many of the same training, nutrition, and body composition principles that benefit healthy adults at any age, with thoughtful adjustments for hormonal changes and age-related anabolic resistance.
Understanding what works can help you stop wasting time and money and start building an approach that supports your body during this stage of life.
Important: This article is educational and does not constitute medical advice. Menopause symptoms may require medical care, including possible hormone therapy. Discuss your circumstances with a qualified healthcare provider, ideally a menopause specialist. This article focuses on fitness, nutrition, and body composition and does not replace clinical evaluation.
Why the Menopause Fitness Conversation Has Become So Misleading?
Understanding why the menopause fitness conversation has become so misleading matters because it explains the specific pattern of misinformation and how to see through it.
- The market opportunity is enormous: The wellness industry for women is estimated in the tens of billions of dollars annually. Menopause is a segment where a large population is dealing with real symptoms, has real concerns about aging, and often has significant purchasing power. This combination attracts significant marketing investment.
- The information vacuum was real: For decades, conventional medicine dismissed or minimized menopause symptoms and offered women few evidence-based options beyond hormone therapy (which was itself misrepresented for years due to poor interpretation of the Women’s Health Initiative findings). This vacuum created legitimate demand for better menopause-focused information.
- The vacuum attracted both good and bad actors: Some properly qualified voices have filled the vacuum with evidence-based content. Many others have filled it with pseudoscience, fear-based marketing, cherry-picked studies, and unproven supplements.
- Fear sells more than truth: Content that tells women they are broken, that their bodies are working against them, that they need a specific secret protocol or supplement to survive menopause, generates significantly more engagement than content that tells them the fundamentals still work.
- Complexity sells more than simplicity: Content that promises unique menopause-specific hacks, protocols, and cycles generates more sales than content that says the honest answer is the same one for most healthy adults: nutrition, movement, sleep, and stress management.
- The credential shield: Some of the worst offenders in menopause fitness misinformation hold formal credentials (physicians, PhDs, certified specialists) that create the appearance of authority even when their specific claims are not supported by the evidence they cite. Credentials are not the same as being correct on a specific topic.
- The influencer economy: Social media rewards contrarian claims and dramatic before-and-after narratives more than measured evidence-based content. This creates specific incentives to make bigger claims than the research supports.
- The specific menopause vulnerability: Women in perimenopause and menopause are often experiencing real symptoms, real body changes, and real distress. This makes them a vulnerable audience for marketing that promises solutions to those symptoms. Vulnerability is being monetized.
Why Are Midlife Women Being Targeted?
The specific targeting of midlife women by wellness marketing is worth understanding because it explains the intensity of the messaging directed at this population.
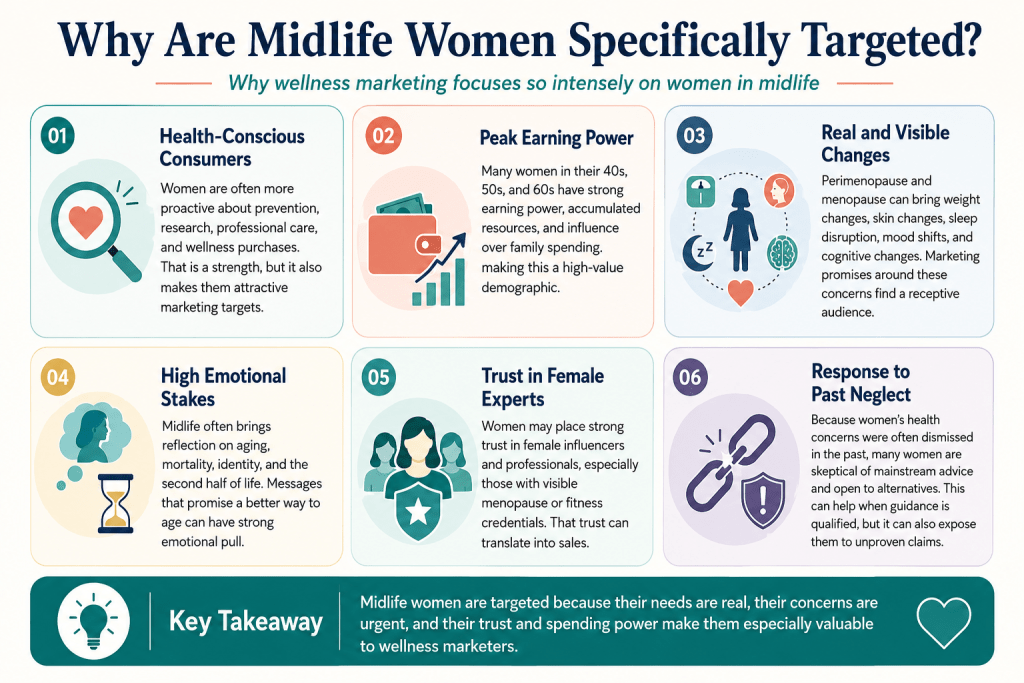
- Women are more conscientious health consumers: Multiple studies of health behavior show that women are more attentive to preventive health, more likely to research options, more likely to seek professional care, and more likely to invest in supplements and wellness products than men in comparable life stages. This is a positive trait. It also makes women more valuable as marketing targets.
- Midlife women often have peak earning power: Women in their forties, fifties, and sixties are often at peak career earning years, have accumulated financial resources, and have decision-making authority about family spending. This is a well-resourced demographic that marketers pursue aggressively.
- The specific concerns are real and visible: The changes of perimenopause and menopause are visible and felt. Weight redistribution, skin changes, sleep disruption, mood changes, and cognitive changes are all real and often distressing. Marketing that promises specific solutions to these specific concerns has a receptive audience.
- Emotional stakes are high: Midlife often brings existential reflection about aging, mortality, and the trajectory of the second half of life. Marketing that speaks to these emotional stakes and promises a specific way to age differently produces powerful emotional responses.
- The trust factor: Women often extend more trust to other women, particularly women with visible expertise credentials, than they extend to marketing generally. Female influencers with credentials in menopause fitness therefore generate significant trust that translates into significant sales.
- The correcting of past neglect: The historical dismissal of women’s health concerns by conventional medicine has produced legitimate skepticism of mainstream advice and an openness to alternative sources. This openness is valuable when directed at qualified alternative voices. It is dangerous when it directs women toward unqualified voices selling unproven interventions.
“The specific pattern I see with coaching clients is that they arrive having spent significant money on peptides, specialty supplements, cortisol-cycling protocols, or specific menopause-branded programs that promised transformation and produced disappointment. What they often have not done is the actual foundational work of adequate protein at every meal, appropriate resistance training, quality sleep, and specific nervous system regulation. When we install those fundamentals as the foundation and then evaluate what specific additions add value on top, the results appear reliably within eight to sixteen weeks. It is not that supplements never help or that specific interventions never matter. It is that the fundamentals produce the majority of the results and are what should be installed first. This is not what the marketing machine sells because the fundamentals are unfashionable and inexpensive. But they are what works, and midlife women deserve to know this before they spend thousands of dollars on the unfashionable and expensive alternatives.”
Terry Tateossian, Founder of The House of Rose
Free 28-Day Fascia Reset Email Course
Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
What Are the Most Common Myths About Menopause Fitness?
Menopause fitness advice is often shaped by exaggerated claims about metabolism, muscle loss, strength training, gender-specific workouts, and cardiovascular exercise. Understanding what current research shows can help midlife women avoid fear-based marketing, make informed decisions, and focus on practical habits that support long-term strength, body composition, cardiovascular health, and overall well-being.
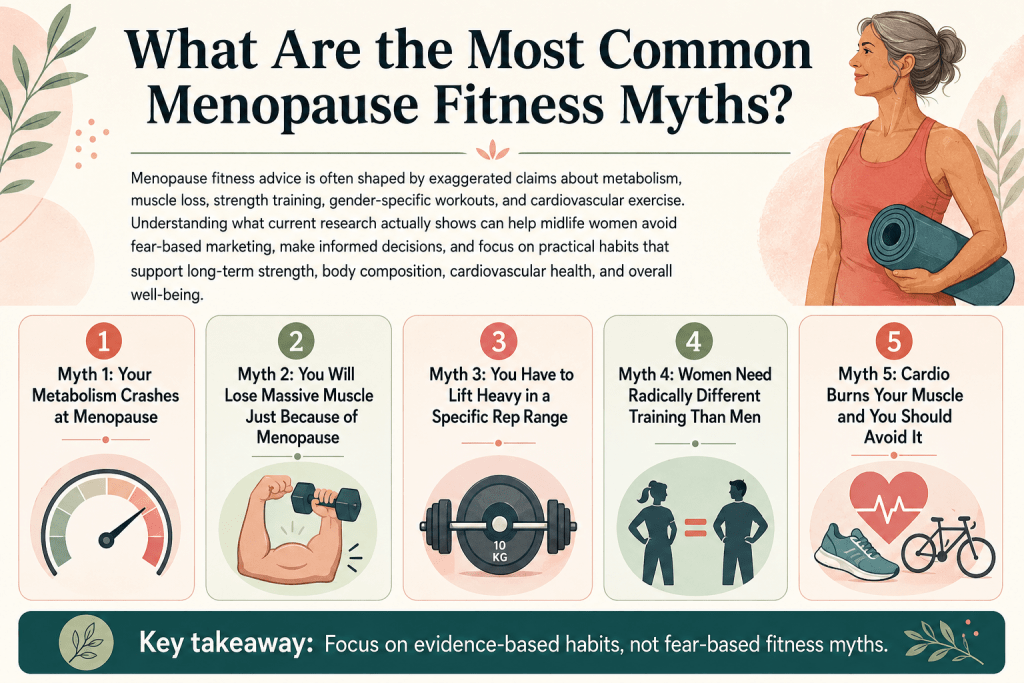
Myth 1: Your Metabolism Crashes at Menopause
The claim that metabolism crashes at menopause is one of the most commonly repeated statements in menopause fitness content. The specific research shows this claim is not supported at the population level.
- The specific research: The 2021 landmark study published in Science by Pontzer and colleagues used doubly labeled water (the gold-standard method for measuring energy expenditure in free-living humans) in a very large sample across the lifespan. The finding relevant to this myth: total daily energy expenditure and basal metabolic rate remain remarkably stable from age 20 to age 60. The rate at which metabolism declines is approximately 0.7 percent per year after age 60, not the dramatic drop at menopause that marketing content claims.
- What this means: Menopause itself does not produce a measurable crash in metabolic rate in the population studies that have investigated this rigorously. The metabolic changes that women experience through midlife are largely explained by age (which affects both men and women), by changes in physical activity levels, by changes in muscle mass, and by changes in behavior around food.
- The specific cited studies that suggest otherwise: Some influencer content cites smaller studies with contrary findings. These studies typically have very small sample sizes (twenty women or fewer), do not reach statistical significance in their actual findings, or have methodological limitations that make their conclusions less reliable than the large-cohort research.
- What changes: What does change measurably in menopause is body composition (with redistribution toward abdominal fat when caloric intake exceeds expenditure), muscle mass over decades (a slow decline that accelerates modestly), and various metabolic markers including insulin sensitivity. These changes are real. They are also gradual and responsive to intervention. They are not the metabolic crash that marketing suggests.
- Practical implication: If you gained weight through the menopause transition without changing your habits, the likely explanation is not a metabolic crash. More likely explanations include modestly reduced physical activity, modestly reduced non-exercise thermogenesis, modestly reduced muscle mass, changes in food choices, or increased caloric intake without noticing it (which is common during a period of poor sleep, stress, and general life turbulence). All of these are addressable through the same interventions that address weight in any adult population.
Myth 2: You Will Lose Massive Muscle Just Because of Menopause
The claim that menopause produces dramatic muscle loss regardless of what a woman does is another commonly repeated marketing message. The specific research shows this claim is significantly exaggerated.
- The specific research: The SWAN Study (Study of Women’s Health Across the Nation) is one of the largest and most rigorous longitudinal studies of the menopause transition ever conducted, following thousands of women across the full transition. The findings relevant to this myth: over the approximately 3.5 to 4-year period of the menopause transition, after adjusting for the age-related changes that would happen to any adult, the average untrained woman gained approximately 3.5 pounds of fat mass and lost less than half a pound of muscle mass. Read that again. Half a pound of muscle over the entire menopause transition, above and beyond age-related changes.
- Why the marketing exaggerates: Some marketing content correctly notes that muscle loss during menopause is somewhat greater than in comparable pre-menopause years, and then frames this as dramatic accelerated loss. Mathematically, doubling a very small number produces a slightly larger small number. Twice half a pound is still only one pound. The direction of the finding is real. The magnitude is not the catastrophe marketing suggests.
- The training and nutrition modifier: The SWAN study data reflects untrained women who were not eating for muscle preservation. Women who continue appropriate resistance training and maintain adequate protein intake through the menopause transition maintain muscle mass and often build additional muscle. The muscle loss that concerns women is largely a function of behavior change, not a hormonal inevitability.
- The specific anabolic resistance factor: Some age-related anabolic resistance (reduced muscle protein synthesis response to a given protein intake) does develop in midlife. This is one of the specific reasons protein intake targets are higher for midlife adults than for younger adults. The 1.6 to 2.2 grams per kilogram of body weight target that supports midlife women accounts for this specific consideration. See our free Macro Calculator for your personalized target and our Macro Miracle Mediterranean Cookbook for the kitchen-side companion.
- The specific resistance training research: Multiple studies have evaluated whether women in perimenopause and menopause can build muscle at rates comparable to pre-menopausal women or comparable to men. The specific findings: when relative gains (percentage improvement from baseline) are compared, postmenopausal women build muscle and strength at roughly the same rates as pre-menopausal women and as men of similar age when placed on the same training protocols. Absolute gains differ because starting baselines differ, but the responsiveness to training does not disappear.
- Practical implication: Your body has not stopped responding to appropriate training. If you strength train appropriately and eat adequate protein, you can build muscle in perimenopause, menopause, and post-menopause. The specific research supports this claim clearly.
Free 28-Day Fascia Reset Email Course
Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Myth 3: You Have to Lift Heavy in a Specific Rep Range
The claim that women in menopause must lift heavy in a specific rep range (typically four sets of four to six reps) to build muscle is another commonly repeated message. The specific research does not support this narrow prescription.
- The specific research: Multiple systematic reviews and meta-analyses over the last decade have consistently shown that muscle hypertrophy occurs across a wide range of loading schemes (from approximately five repetitions per set to approximately thirty repetitions per set) as long as two conditions are met. First, sets are taken close to failure (typically within zero to four reps of muscular failure). Second, total training volume is equated across conditions.
- What this means: Whether you prefer to train with heavy weights and fewer reps (say, five reps per set) or moderate weights and more reps (say, twelve to fifteen reps per set), the muscle-building result will be similar as long as you take your sets close to failure and complete an adequate number of sets. Both approaches build muscle. Both approaches build strength. Neither is inherently superior.
- Where the confusion comes from: The word “heavy” is a relative term. Heavy for you is whatever load challenges you within your chosen rep range. If you can complete fifteen reps of a given exercise with clean form and could have done another two or three, that specific set was probably not close enough to failure to produce optimal muscle-building stimulus. If you can complete five reps and could not have done another, that set was close to failure regardless of the specific weight involved. Effort, not the absolute weight, is what drives adaptation.
- The specific application to midlife women: For midlife women, the practical implication is that you have flexibility in how you structure your training. If you enjoy lower-rep heavier sets, use them. If you enjoy moderate-rep sets, use them. If you have joint issues that make very heavy loading uncomfortable, moderate loads with more reps produce the same result. What matters is that the sets you complete are close enough to failure to produce adaptation.
- The specific caution: The often-cited advice to “lift heavy, ladies” was well-intentioned as a correction to the earlier culture of women avoiding strength training entirely or using extremely light weights that were not close to failure. The correction was necessary. The specific numerical prescription that emerged from it (must lift very heavy for very few reps) is not supported by the current evidence base as a specific requirement.
- Proximity to failure for beginners and advanced: For beginners, sets performed with meaningful effort even five or six reps short of failure often produce significant muscle building because the training stimulus is new. As training age increases, closer proximity to failure becomes more necessary to continue producing adaptation. Advanced trainees generally need to work within two reps of failure or closer on many sets to continue progressing.
Myth 4: Women Need Radically Different Training Than Men
The claim that women in menopause need training protocols radically different from what men receive is another commonly repeated marketing message. The specific research does not support this claim.
- The specific research: Multiple systematic reviews have compared training responses between men and women, across age groups, and across menstrual and menopausal status. The consistent finding: when placed on the same training protocol, men and women build muscle and strength at roughly the same relative rates. Absolute values differ because of body size and baseline strength differences. Relative responsiveness does not.
- What this means: The programming principles that apply to human strength and hypertrophy (progressive overload, appropriate volume, appropriate frequency, appropriate proximity to failure, adequate recovery, adequate protein intake) apply to women in perimenopause and menopause in the same way they apply to any other adult population. The specific modifications are minor and are more about age than about gender.
- The specific modifications that do apply: Age-related anabolic resistance suggests slightly higher protein targets for midlife adults than for younger adults. Recovery may be slightly longer between demanding sessions. Joint issues that accumulate with age may require exercise selection modifications. Sleep quality changes may affect training capacity on specific days. All of these apply to midlife men as much as to midlife women.
- The specific hormonal considerations: The hormonal changes of perimenopause and menopause do affect the body. They do not eliminate the ability to respond to training. Some research suggests that specific training approaches may be somewhat more effective at specific menstrual cycle phases in pre-menopausal women, but the practical significance of these differences is modest and the underlying principle (train hard, eat well, sleep well) does not change.
- The specific marketing incentive: Selling women a menopause-specific training program has more commercial appeal than telling them the training they were doing at forty is still appropriate at fifty-five with minor modifications. The specific incentive is to sell a specialized product, not to communicate the honest research finding.
- Practical implication: You do not need to abandon what has been working for you and adopt a completely different menopause-specific program. If your training has been producing results, continue it with age-appropriate adjustments. If your training has been generic or ineffective, learn to train well, which is a different question than learning to train “for menopause.”
Free 28-Day Fascia Reset Email Course
Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Myth 5: Cardio Burns Your Muscle & You Should Avoid It
The claim that cardiovascular exercise burns muscle and should be minimized or avoided in menopause is another commonly repeated message. The specific research does not support the aggressive version of this claim.
- The specific research: Cardiovascular exercise does not meaningfully burn muscle mass at reasonable volumes when combined with resistance training and adequate protein intake. The concern about “cardio burning muscle” arises from studies of very high-volume endurance training performed by athletes in caloric deficit without resistance training. In this specific extreme scenario, some muscle loss can occur. In the practical scenarios that apply to almost every midlife woman, cardio and strength training coexist without cardio undermining strength gains.
- The specific cardiovascular benefits for midlife women: Cardiovascular exercise supports the cardiovascular protection that becomes particularly important as estrogen declines through the menopause transition. Cardiovascular disease is the leading cause of death in women over fifty. Regular cardiovascular activity is one of the most evidence-supported interventions for reducing this risk. Avoiding cardio to protect muscle when muscle is already being supported by strength training and protein intake is not a good trade.
- The specific Randall effect: Some marketing content invokes something like the Randall effect to argue that cardio burns fat during exercise but reduces fat burning during rest, producing no net benefit. The Randall effect is real, but the interpretation is misleading. Total daily energy balance is what matters for body composition. Regular cardiovascular exercise increases total daily energy expenditure and supports the metabolic health that facilitates weight management, regardless of when the fat is being burned during the day.
- The specific balance for midlife women: For most midlife women, the appropriate movement framework combines two or three strength training sessions per week, daily walking or gentle activity, and one or two moderate cardiovascular sessions per week (which can include tai chi, brisk walking, cycling, or other forms). This combination supports muscle preservation, cardiovascular health, metabolic health, and general functional capacity.
- The specific caution: Very high-volume cardio (multiple hours per day) in the setting of aggressive caloric restriction is not supportive of body composition or general health for most midlife women. Moderate cardio in the context of adequate nutrition and resistance training is broadly beneficial.
What Does the Research Support?
Cutting through the myths reveals a specific evidence-supported framework for midlife women’s fitness. It is straightforward, practical, and effective, even if it is less fashionable than the complicated protocols often promoted online.
Prioritize Protein and Resistance Training
Muscle preservation begins with adequate protein intake and consistent resistance training:
- Adequate protein at every meal: Aim for approximately 1.6 to 2.2 grams of protein per kilogram of body weight daily. For most midlife women, this means distributing protein across meals and consuming approximately 25 to 40 grams per meal. This is the foundational nutritional intervention for muscle preservation and body composition.
- Resistance training two to three times per week: Follow a program that targets the major muscle groups, progresses over time, and takes sets close to failure. Rep ranges within the 5-to-30 range work equivalently when total training volume is equated.
Support Cardiovascular Health and Recovery
Strength training matters, but cardiovascular activity and quality sleep support the systems that allow the body to remain healthy, active, and resilient:
- Regular cardiovascular activity: Use daily walking as a foundation, along with one or two moderate cardiovascular sessions per week. Cardiovascular disease is the leading cause of death in women over fifty, and cardiovascular fitness is one of the strongest predictors of healthy aging.
- Consistent quality sleep: Aim for seven to nine hours per night with consistent bed and wake times. Sleep is when recovery, hormonal regulation, and cognitive consolidation happen. Compromised sleep undermines every other intervention.
Regulate Stress and Cover Foundational Nutrients
Fitness outcomes are also influenced by chronic stress and whether the body receives the nutrients required to support recovery:
- Nervous system regulation: Use daily practices that reduce chronic sympathetic activation and support parasympathetic recovery. These practices may include vagus nerve reset exercises, breath work, and appropriate stress management.
- Attention to specific foundational nutrients: Vitamin D, magnesium, omega-3s, adequate calcium, and adequate protein form the foundational supplement stack. Additional supplements produce diminishing returns above this foundation.
Seek Individual Care and Focus on Consistency
No general fitness framework replaces individualized medical care, and no intervention produces lasting results without consistency:
- Individual medical care: Menopause symptoms can be significant. Hormone therapy is appropriate for many women and is safer than the misinterpreted Women’s Health Initiative narrative suggested. Discuss your options with a menopause specialist to evaluate whether hormone therapy fits your specific situation.
- Sustainable behavior over time: The interventions above do not need to be performed perfectly. They need to be practiced consistently over years. A merely good execution sustained for a decade produces vastly better results than a brilliant execution sustained for a month.
Free 28-Day Fascia Reset Email Course
Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
What Are the Six Fundamentals That Work?
The specific fundamentals that produce results for midlife women fitness are simple to name and hard to execute consistently. Naming them clearly matters because the marketing machine works hard to distract from them.
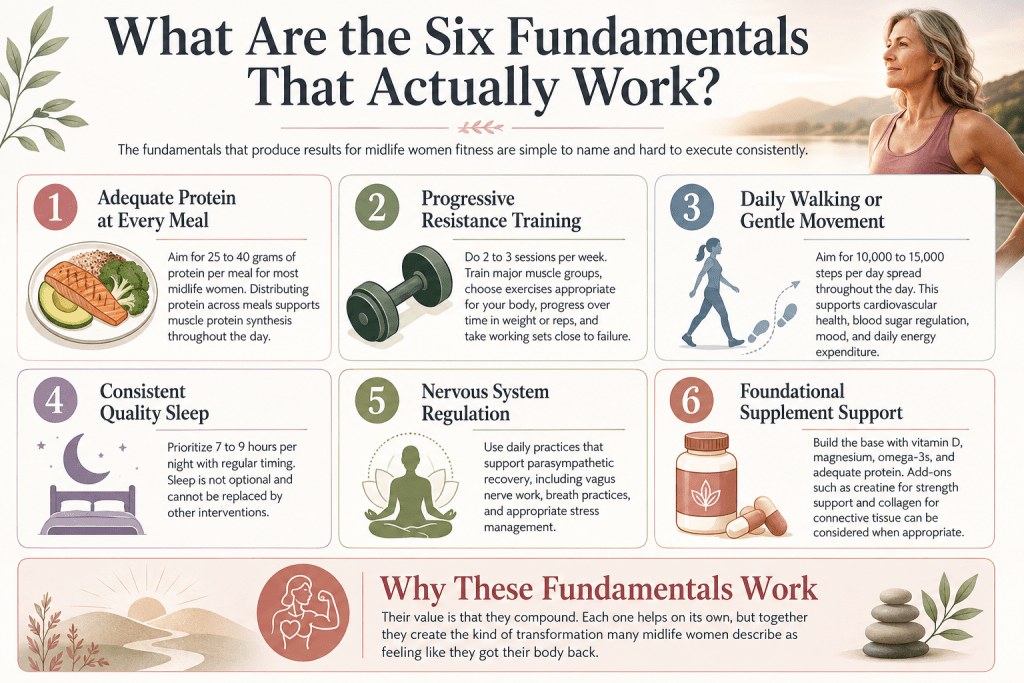
- Fundamental 1: Adequate protein at every meal. Not just adequate daily total protein, but adequate protein distributed at each meal (25 to 40 grams for most midlife women). This distribution supports muscle protein synthesis throughout the day. The free Macro Calculator provides your personalized target.
- Fundamental 2: Progressive resistance training. Two to three sessions per week that target major muscle groups, use exercises appropriate for your body, progress over time in weight or reps, and take working sets close to failure.
- Fundamental 3: Daily walking or gentle movement. Ten to fifteen thousand steps per day distributed throughout the day. This foundational movement supports cardiovascular health, blood sugar regulation, mood, and general non-exercise activity thermogenesis.
- Fundamental 4: Consistent quality sleep. Seven to nine hours per night with regular timing. Sleep is not optional and is not compensated for by other interventions.
- Fundamental 5: Nervous system regulation. Daily practices that support parasympathetic recovery including vagus nerve work, breath practices, and appropriate stress management.
- Fundamental 6: Foundational supplement support. Vitamin D, magnesium, omega-3s, and adequate protein form the base. Specific additions (creatine for strength training support, collagen for connective tissue support, others based on individual assessment) can be considered on top.
The specific value of these fundamentals is that they compound. Any single one produces modest results in isolation. The combination produces the specific transformation that midlife women often describe as feeling like they got their body back. This is not marketing hyperbole. It is what happens when the fundamentals are installed consistently.
“The specific pattern I see with coaching clients who succeed is not that they discovered some special protocol or supplement. It is that they finally installed the fundamentals consistently for long enough that the compounding started to show. Six months of adequate protein, consistent strength training, regular walking, quality sleep, and daily nervous system practice produces the specific results that most midlife women were hoping to buy from a peptide or a specialty supplement. The results appear reliably when the fundamentals are installed. The reason marketing content does not sell this is that fundamentals do not have a good margin, cannot be trademarked, and require sustained personal effort that is unfashionable in a culture that wants shortcuts. But this is the honest picture. And once women see it clearly and commit to the sustained work, the results appear reliably enough that they wonder why nobody told them this ten years ago.”
Terry Tateossian, Founder of The House of Rose
How To Recognize Manipulation Tactics in Menopause Marketing?
Recognizing the specific manipulation tactics used in menopause fitness marketing helps midlife women protect themselves from expensive and often counterproductive interventions.
- Tactic 1: Rodent studies presented as human evidence. Menopause fitness content often cites studies performed in mice or rats as if they translated directly to adult women. They do not. When someone cites a study to support a claim about your menopause, check whether the study was performed in humans. Women are not large mice.
- Tactic 2: Small studies presented as definitive. A study of twenty women is not the equivalent of a study of two thousand women. Small studies produce more noise, more chance findings, and less reliable conclusions. When someone cites a study, note the sample size before accepting the conclusion.
- Tactic 3: Study titles quoted without reading the actual findings. Some influencer content cites the title of a study without reading the methodology or results. A study titled “Metabolism Declines at Menopause” may report findings that were not statistically significant and did not show meaningful decline. Read past the title before accepting the claim.
- Tactic 4: Cherry-picking against the weight of evidence. Many claims cited in menopause marketing are based on single studies that produce findings contrary to the larger body of research. When one small study contradicts multiple large studies, the larger body of research usually reflects reality better.
- Tactic 5: Credential shielding. Credentials do not equal correctness on a specific topic. A physician can be wrong about a specific fitness claim. A PhD can misrepresent research. Evaluate claims on their evidence, not on the credentials of who is making them.
- Tactic 6: Emotional alignment. Marketing content often describes the specific experiences that midlife women recognize (fatigue, weight gain, sleep disruption) and then attributes them to a specific cause the product claims to address. Recognition of your experience does not validate the causal attribution. Something can be true about your experience without the specific explanation offered being correct.
- Tactic 7: The contrarian claim. Being contrarian generates attention. Marketing content often positions its claims as contrary to what “mainstream” recommends. Sometimes contrarian claims are correct. Often they are contrarian precisely because the evidence does not support them.
- Tactic 8: The urgency and scarcity manipulation. Limited-time offers, “special access” pricing, and countdown timers are marketing manipulation tactics rather than evidence-based recommendations. Legitimate interventions do not depend on urgency to sell.
- Tactic 9: The transformation before-and-after. Dramatic transformation photos often reflect factors beyond the specific intervention being marketed (professional photography, lighting, posing, potential use of physique-enhancing drugs, potential genetic factors). Do not accept transformation photos as evidence.
- Tactic 10: The private group or membership tactic. Some marketing funnels lead to expensive private groups or memberships that promise proprietary information not available elsewhere. When someone claims to have proprietary menopause information not available through legitimate sources, be skeptical. The actual evidence base is public.
Free 28-Day Fascia Reset Email Course
Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How To Distinguish Autoregulation From Excuses?
The concept of autoregulation (adjusting training based on how you feel on a specific day) is important for midlife women but needs to be distinguished from using autoregulation as an excuse to avoid training.
- Legitimate autoregulation: Some days you will feel worse than others. Poor sleep, hormonal fluctuations, stress load, illness, and other factors reduce capacity on specific days. Adjusting your training to what your body can honestly handle that day is appropriate autoregulation. On a low-capacity day, do a shorter or lighter session rather than skipping. On a high-capacity day, push harder.
- The specific autoregulation for midlife women: Perimenopause and menopause can produce days when you truly feel unable to train at your usual intensity. Chronic pushing through severe fatigue undermines recovery and often worsens the pattern. On those days, doing something rather than nothing is the pattern that supports long-term consistency.
- The distinction from excuses: Autoregulation is not “I do not feel like training.” Autoregulation is “I am experiencing specific reduced capacity today and will adjust accordingly.” The distinction matters. Most training days you will not feel like training and will feel better after training. Only some days is your body asking for a reduced session.
- How to tell the difference: If you start the session and your warmup sets feel harder than expected, if your usual weights feel significantly heavier, if your motivation truly does not return after the first few sets, if you feel worse rather than better as the session progresses, these are signs of a legitimate low-capacity day. On the other hand, if you start reluctantly and feel better as you move, if your body responds to the warmup, and if the resistance is more mental than physical, these are signs that pushing through is appropriate.
- The framework in menopause: Give yourself grace on days when your body is truly asking for it. Do not use “menopause” as a category-wide excuse to reduce your consistency. Both extremes undermine progress. The middle path of honest self-assessment combined with sustained effort produces the results.
- The specific role of consistency: Consistency matters more than intensity. A midlife woman who trains four days per week at 80 percent effort for a year produces vastly better results than one who trains occasionally at 100 percent effort. Show up. Adjust the intensity to what your body can honestly handle. Come back tomorrow.
What To Know About Supplements and Peptides?
Supplements and peptides are one of the specific categories where menopause marketing runs particularly hot. Understanding the honest picture matters.
Which Foundational Supplements Have Real Evidence?
The foundational supplements with solid evidence bases and reasonable safety profiles at recommended doses include:
- Vitamin D: Widely deficient in midlife women and supports bone and general health.
- Magnesium: Supports sleep, nervous system health, and muscle function.
- Omega-3s: Support cardiovascular and cognitive health.
- Adequate protein: Supports muscle preservation, recovery, and general health.
These form the foundation.
Which Additional Supplements Have Reasonable Evidence?
Some specific additions also have reasonable evidence bases:
- Creatine monohydrate: Supports strength training and possibly cognitive function in older adults.
- Collagen: Has modest evidence for skin and joint benefits.
- Specific nutrients for identified deficiencies: Nutrients addressed to specific deficiencies identified through appropriate testing can be beneficial.
Which Products Require the Most Caution?
Several supplement categories deserve additional scrutiny because of limited safety data, unclear labeling, or the possibility of undisclosed ingredients.
Peptides
Peptide products marketed for menopause, weight loss, muscle building, or general anti-aging are a specific category worth flagging.
Most peptides sold outside FDA-approved medical channels do not have safety data supporting long-term use. Many are illegal to sell for the purposes claimed. Some have real potential for adverse effects that have not been characterized because they have not been studied in the population being sold to.
The specific pattern of influencers selling peptides is a strong red flag, regardless of the specific product.
Proprietary Blends
Products with unspecified amounts of multiple ingredients in “proprietary blends” typically hide the fact that meaningful doses of active ingredients are not present.
Look for supplements that list specific amounts of specific ingredients so you can evaluate whether the dose matches the evidence.
Physique-Enhancing Drugs Marketed as Supplements
Some products marketed as natural or as supplements contain undisclosed pharmaceuticals or physique-enhancing drugs.
Testing has identified several undisclosed substances in supplement products, including:
- Anabolic steroid analogs
- Stimulants
- Hormones
Reputable brands with third-party testing, such as NSF, Informed Sport, or USP Verified, offer better safety assurance.
What Is the Honest Picture?
The foundational supplements plus one or two specific additions based on your situation typically produce ninety percent of the supplement benefit available for most midlife women.
Additional spending on complex protocols, peptides, and specialty products typically produces diminishing returns while adding significant cost.
Free 28-Day Fascia Reset Email Course
Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How Can You Build Your Own Evidence-Based Framework?
Building your own framework based on the evidence-supported fundamentals is the specific work that produces results. This is not exciting content. It is what works.
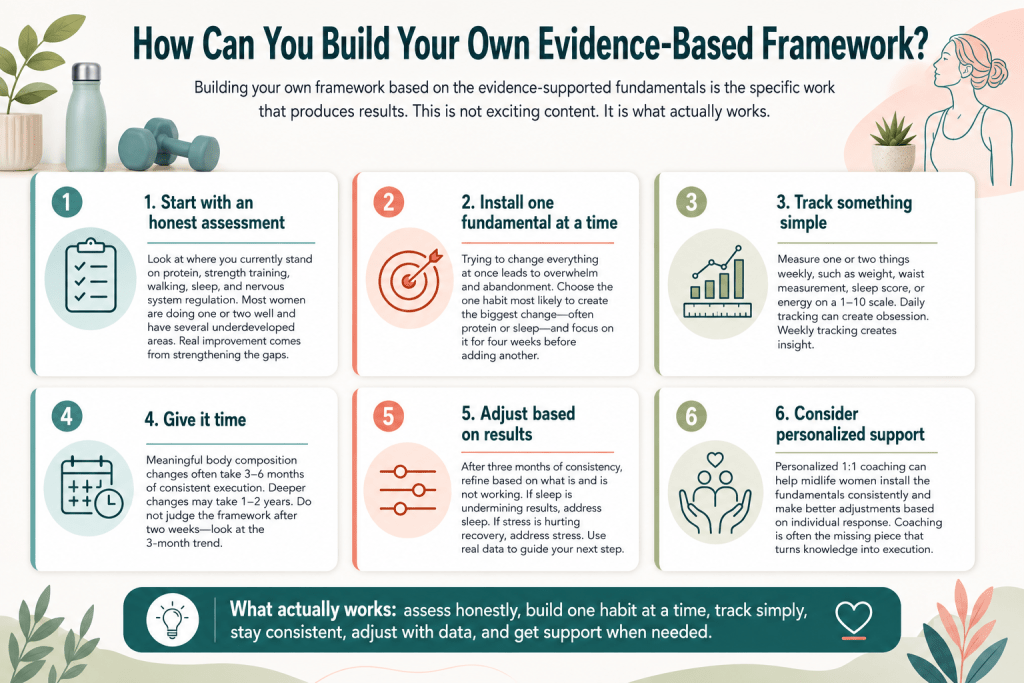
- Start with an honest assessment: Where are you currently on protein, strength training, walking, sleep, and nervous system regulation? For most women, one or two of these are being done reasonably well and three or four are underdeveloped. The improvements come from installing the underdeveloped fundamentals.
- Install one fundamental at a time: Trying to change everything at once produces overwhelm and abandonment. Choose the single fundamental most likely to produce the biggest change (often protein or sleep for midlife women) and install it for four weeks before adding another.
- Track something simple: Weekly measurement of one or two metrics (weight, waist measurement, sleep score, energy on a one-to-ten scale) provides feedback that supports adherence. Daily tracking produces obsession. Weekly tracking produces insight.
- Give it time: Meaningful body composition changes take three to six months of consistent execution. Deeper changes take one to two years. If you evaluate the framework based on two weeks, you will always be disappointed. Evaluate it based on the trend at three months.
- Adjust based on results: After three months of consistent execution, adjust based on what is or is not working. If protein and training are in place but sleep is undermining everything, address sleep. If sleep is in place but stress is undermining recovery, address stress. Progressive refinement based on actual data.
Free 28-Day Fascia Reset Email Course
Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
When Should You See a Healthcare Professional?
Fitness framework in this article is one component of midlife women’s health. Several situations warrant professional medical care beyond the fitness picture.
- Any acute or severe symptoms: Chest pain, shortness of breath, severe fatigue, persistent unexplained weakness, or other significant symptoms warrant medical evaluation.
- Menopause symptoms that impair daily function: A menopause specialist or gynecologist can evaluate options including hormone therapy that may be appropriate for your specific situation. Hormone therapy is safer than the misinterpreted Women’s Health Initiative narrative suggested and is appropriate for many women.
- Cardiovascular concerns: Family history of cardiovascular disease, hypertension, or other cardiac concerns warrant regular medical follow-up.
- Bone health concerns: DEXA scanning is appropriate for many midlife women to assess bone density. Osteopenia and osteoporosis benefit from specific medical management alongside lifestyle interventions.
- Metabolic concerns: Elevated fasting glucose, elevated hemoglobin A1c, or other metabolic markers warrant medical management alongside lifestyle interventions.
- Mental health concerns: Persistent depression, anxiety, or mood changes warrant mental health evaluation. The mood changes of menopause can benefit from both lifestyle interventions and appropriate medical care.
- Suspected undisclosed use of physique-enhancing drugs: If you are considering products marketed as natural but which produce results that seem too dramatic, discuss with your provider before starting.
Free 28-Day Fascia Reset Email Course
Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Frequently Asked Questions
Does metabolism really slow down at menopause?
The large-cohort research on human energy expenditure (Pontzer and colleagues, 2021, Science) shows that total daily energy expenditure and basal metabolic rate remain remarkably stable from age 20 to age 60 across the population. The rate declines approximately 0.7 percent per year after age 60. Menopause itself does not produce the metabolic crash that marketing content commonly claims. The weight changes women experience in midlife are largely explained by age, activity levels, muscle mass changes, and behavior around food, all of which are addressable.
Can you build muscle after menopause?
Yes. Multiple studies show that when placed on the same training protocol, postmenopausal women build muscle and strength at roughly the same relative rates as pre-menopausal women. Absolute values differ because of starting baselines. The specific claim that menopause makes muscle building impossible is not supported by the research. Adequate protein and progressive resistance training produce meaningful muscle building in perimenopause, menopause, and post-menopause.
How much muscle do women lose in menopause?
The SWAN Study, one of the largest longitudinal studies of the menopause transition, showed that untrained women lose less than half a pound of muscle mass over the approximately 4-year menopause transition beyond age-related changes. Women who continue appropriate resistance training and maintain adequate protein intake maintain muscle mass and often build additional muscle. The dramatic muscle loss commonly cited in marketing is significantly exaggerated for the general untrained population and does not apply to trained women.
Do I have to lift heavy weights for muscle building in menopause?
No. Current research shows that muscle building occurs across a wide range of loading schemes (roughly 5 to 30 reps per set) as long as sets are taken close to failure and total training volume is adequate. Both lower-rep heavier sets and higher-rep moderate sets produce similar results. Choose the approach that fits your body, joint health, and preferences.
Do women need different training programs than men in menopause?
The core principles of strength training (progressive overload, adequate volume, adequate frequency, appropriate proximity to failure, adequate recovery) apply to men and women equivalently. Age-related modifications matter more than gender-based modifications. The training that works for a healthy adult applies to a menopausal woman with minor adjustments primarily related to age rather than to menopause.
How much protein do women need in menopause?
Approximately 1.6 to 2.2 grams per kilogram of body weight daily, distributed across meals with 25 to 40 grams per meal for most midlife women. This is higher than the general adult recommendations because of age-related anabolic resistance. The free Macro Calculator provides your personalized target.
Should I do cardio if I am trying to build muscle in menopause?
Yes, moderate cardiovascular exercise combined with resistance training and adequate protein intake supports overall health without meaningfully undermining muscle building. Cardiovascular disease is the leading cause of death in women over 50, and cardiovascular fitness is one of the strongest predictors of healthy aging. Avoiding cardio to protect muscle is generally not a good trade for most midlife women.
Are peptides safe for menopause fitness?
Peptide products marketed for menopause fitness, weight loss, muscle building, or general anti-aging outside of FDA-approved medical channels do not have long-term safety data supporting their use. Many are illegal to sell for the purposes claimed. The specific pattern of influencers selling peptides is a strong red flag regardless of the specific product. Discuss with a qualified healthcare provider before considering any peptide product.
What supplements help with menopause fitness?
The evidence-supported foundation includes vitamin D, magnesium, omega-3s, and adequate protein. Specific additions with reasonable evidence include creatine monohydrate for strength training support and collagen for skin and joint support. Additional supplements produce diminishing returns above this foundation for most midlife women. Reputable brands with third-party testing offer better safety assurance.
Why am I gaining weight if my metabolism has not really changed?
Weight gain in midlife that is not explained by a metabolic crash is usually explained by some combination of reduced physical activity, reduced non-exercise thermogenesis, reduced muscle mass over time, changes in food choices, or increased caloric intake without full awareness of it (common during periods of poor sleep, stress, and life turbulence). All of these are addressable through the fundamentals in this article.
Should I follow a specific menopause diet plan?
The evidence-supported nutrition framework for menopause is largely the same as for any adult population with modest modifications. Adequate protein at every meal. Plenty of colorful vegetables. Whole-food emphasis. Minimal processed food. Adequate hydration. The Mediterranean pattern with attention to protein is broadly supportive. See our menopause diet plan for the full framework.
How can I tell if a menopause fitness influencer is trustworthy?
Look for specific citation of human studies with adequate sample sizes rather than rodent studies or small studies. Check whether their claims align with the broader body of evidence or are contrarian to nearly all other experts. Note whether they are selling proprietary supplements or peptides (a red flag). Note whether they acknowledge nuance and individual variation or claim universal protocols. Note whether they promise dramatic transformation from their specific intervention or emphasize the fundamentals.
Free 28-Day Fascia Reset Email Course
Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Does hormone therapy replace the need for fitness in menopause?
No. Hormone therapy addresses specific menopause symptoms and may reduce some of the physiological headwinds of the transition. It does not build muscle, prevent weight gain, or replace the need for the fundamentals. Hormone therapy is one option worth discussing with a menopause specialist as part of a broader framework that includes the fitness fundamentals.
How long before I see results from the fundamentals?
Subjective improvements in energy and mood often appear within four weeks. Body composition changes typically become measurable at eight to twelve weeks. Meaningful body composition transformation typically develops over six to twelve months. The specific compounding pattern of the fundamentals continues to produce benefits over years.
Should I work with a coach for menopause fitness?
Personalized coaching is often the specific missing piece that turns knowledge into consistent execution. The Monthly Personal Training and Nutrition Coaching Program is where midlife women install the framework with 1:1 accountability and appropriate personalization. For the immersive experience, the Deeply Restorative Yoga and Nature Retreat at our Smoky Mountains property installs the full framework in five days.
References
- Pontzer, H., Yamada, Y., Sagayama, H., et al. (2021). Daily energy expenditure through the human life course. Science, 373(6556), 808–812.
- Greendale, G. A., Sternfeld, B., Huang, M., et al. (2019). Changes in body composition and weight during the menopause transition. JCI Insight, 4(5), e124865.
- Sowers, M., Zheng, H., Tomey, K., et al. (2007). Changes in body composition in women over six years at midlife: ovarian and chronological aging. Journal of Clinical Endocrinology and Metabolism, 92(3), 895–901.
- Refalo, M. C., Helms, E. R., Trexler, E. T., et al. (2023). Influence of resistance training proximity-to-failure on skeletal muscle hypertrophy: a systematic review with meta-analysis. Sports Medicine, 53(3), 649–665.
- Schoenfeld, B. J., Grgic, J., Van Every, D. W., & Plotkin, D. L. (2021). Loading recommendations for muscle strength, hypertrophy, and local endurance: a re-examination of the repetition continuum. Sports, 9(2), 32.
- Roberts, B. M., Nuckols, G., & Krieger, J. W. (2020). Sex differences in resistance training: a systematic review and meta-analysis. Journal of Strength and Conditioning Research, 34(5), 1448–1460.
- Peterson, M. D., Rhea, M. R., Sen, A., & Gordon, P. M. (2010). Resistance exercise for muscular strength in older adults: a meta-analysis. Ageing Research Reviews, 9(3), 226–237.
- Fragala, M. S., Cadore, E. L., Dorgo, S., et al. (2019). Resistance training for older adults: position statement from the National Strength and Conditioning Association. Journal of Strength and Conditioning Research, 33(8), 2019–2052.
- Bauer, J., Biolo, G., Cederholm, T., et al. (2013). Evidence-based recommendations for optimal dietary protein intake in older people: a position paper from the PROT-AGE Study Group. Journal of the American Medical Directors Association, 14(8), 542–559.
- Deutz, N. E. P., Bauer, J. M., Barazzoni, R., et al. (2014). Protein intake and exercise for optimal muscle function with aging: recommendations from the ESPEN Expert Group. Clinical Nutrition, 33(6), 929–936.
- Antonio, J., Candow, D. G., Forbes, S. C., et al. (2021). Common questions and misconceptions about creatine supplementation: what does the scientific evidence really show? Journal of the International Society of Sports Nutrition, 18(1), 13.
- Manson, J. E., Chlebowski, R. T., Stefanick, M. L., et al. (2013). Menopausal hormone therapy and health outcomes during the intervention and extended poststopping phases of the Women’s Health Initiative randomized trials. JAMA, 310(13), 1353–1368.
- North American Menopause Society. (2022). The 2022 hormone therapy position statement of The North American Menopause Society. Menopause, 29(7), 767–794.
- Karvinen, S., Jergenson, M. J., Hyvärinen, M., et al. (2019). Menopausal status and physical activity are independently associated with cardiovascular risk factors of healthy middle-aged women. Frontiers in Endocrinology, 10, 589.
- Sipilä, S., Törmäkangas, T., Sillanpää, E., et al. (2020). Muscle and bone mass in middle-aged women: role of menopausal status and physical activity. Journal of Cachexia, Sarcopenia and Muscle, 11(3), 698–709.
- Distefano, G., Standley, R. A., Zhang, X., et al. (2018). Physical activity unveils the relationship between mitochondrial energetics, muscle quality, and physical function in older adults. Journal of Cachexia, Sarcopenia and Muscle, 9(2), 279–294.
- Saper, R. B., Phillips, R. S., Sehgal, A., et al. (2008). Lead, mercury, and arsenic in US- and Indian-manufactured Ayurvedic medicines sold via the Internet. JAMA, 300(8), 915–923.
- Kanaley, J. A., Colberg, S. R., Corcoran, M. H., et al. (2022). Exercise/physical activity in individuals with type 2 diabetes: a consensus statement from the American College of Sports Medicine. Medicine and Science in Sports and Exercise, 54(2), 353–368.
- El Khoudary, S. R., Aggarwal, B., Beckie, T. M., et al. (2020). Menopause transition and cardiovascular disease risk: implications for timing of early prevention: a scientific statement from the American Heart Association. Circulation, 142(25), e506–e532.
- Wang, X., Ouyang, Y., Liu, J., et al. (2014). Fruit and vegetable consumption and mortality from all causes, cardiovascular disease, and cancer: systematic review and dose-response meta-analysis of prospective cohort studies. BMJ, 349, g4490.
Disclaimer: This article is educational and does not constitute medical advice. Menopause can involve significant symptoms that benefit from medical care including possible hormone therapy. Discuss your specific situation with a qualified healthcare provider, ideally a menopause specialist. Do not start, stop, or change any medication or supplement without appropriate medical guidance.
Free 28-Day Fascia Reset Email Course
Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.