Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Can You Sit Down and Stand Up Without Using Your Hands? What the Sitting-Rising Test Predicts

Every retreat week, there’s a moment during our floor-based movement sessions where I can tell, almost instantly, which guests are going to have the easiest week physically and which ones are going to need extra support getting in and out of certain postures. It’s not when we’re standing.

It’s the transition to and from the mat. Some women drop to the floor and spring back up without a second thought. Others lower themselves in stages, a hand here, a knee there, a small negotiation with gravity at every step, and getting back up takes visible effort and usually a piece of furniture within reach.

I used to think of this as flexibility, or maybe just a quirk of who happened to do yoga more often. After four years of watching this exact pattern repeat across dozens of women’s yoga retreats, I don’t think that anymore. What I was watching, without having the research language for it yet, was a real, measurable marker that clinicians have been studying for over two decades: how a person gets up off the floor predicts far more about their underlying health than it has any right to.

There’s a specific test built around this exact movement, and a body of published research tracking what a person’s score on it says about their long-term health. It started in a single exercise medicine clinic and has since been studied in thousands of people over more than a decade of follow-up. Here’s what it actually shows, how to score yourself, and, more usefully, what to do if your score isn’t where you’d like it to be.

Important: This article is educational and does not replace individualized medical advice. Women with joint replacements, recent surgery, significant balance impairment, or uncontrolled dizziness should consult a physician or physical therapist before attempting this test.

How Does the Sitting-Rising Test Work?

The sitting-rising test (SRT) was developed by Dr. Claudio Gil Araújo, a physician who runs an exercise medicine clinic in Rio de Janeiro, after he noticed a pattern among his patients: the ones who struggled to get down to the floor and back up without support tended to be the same patients whose overall health trajectory looked worse, often well before it showed up in standard lab work.
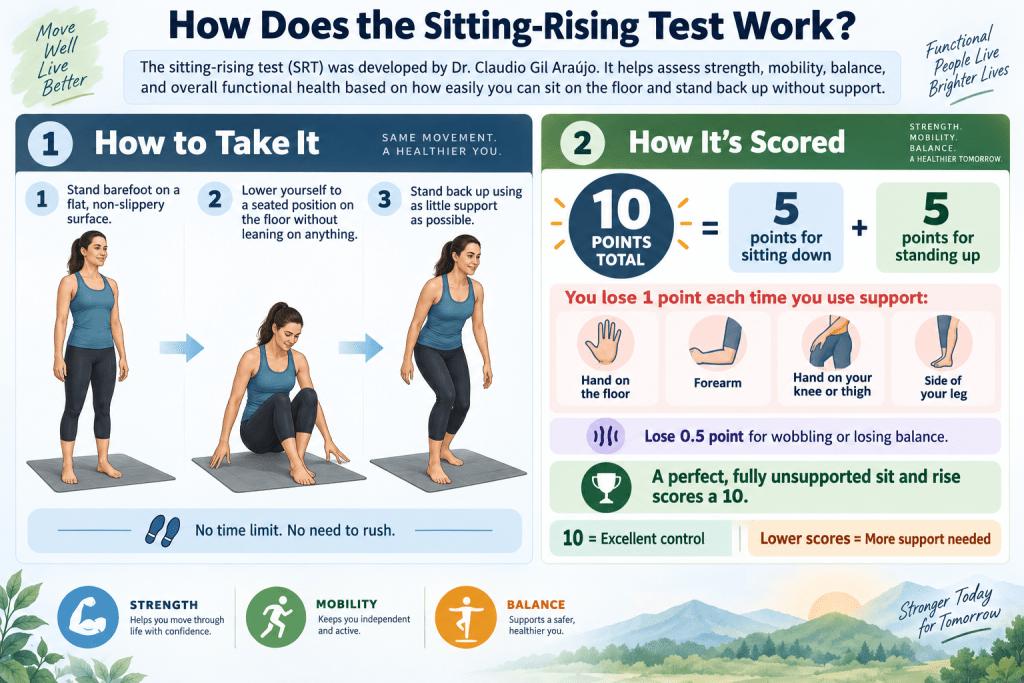
Sitting-rising test steps and scoring guide.

How to Take It

Stand barefoot on a flat, non-slippery surface, ideally with a carpeted or matted floor for comfort. Without leaning against anything, lower yourself to a seated position on the floor, then stand back up, using as little support as possible. There’s no time limit and no need to rush.

How It’s Scored

You start at 10 points, 5 allotted for sitting down and 5 for standing up. Each time you use a support, a hand on the floor, a forearm, a hand on your knee or thigh, or the side of your leg, you lose one point from that half of the movement. If you wobble or lose your balance at any point, you lose half a point. A perfect, fully unsupported sit and rise scores a 10.

Why Does This One Movement Reveal So Much?

Most fitness assessments test one system at a time. A treadmill test measures cardiovascular capacity. A grip strength test measures upper body strength. A flexibility screen measures range of motion.

Getting down to the floor and back up without support asks several systems to work together at once: leg strength, core strength, balance, flexibility through the hips and ankles, and coordination. If any one of those is significantly compromised, the score reflects it, because there’s no way to compensate for a weak link the way you might on a single-system test.

That’s part of why the test has held up so well across different research populations. It’s not measuring one narrow capacity. It’s measuring whether the whole functional system still works together the way it’s supposed to.

“I’ve watched women who look perfectly healthy standing up struggle to get off a yoga mat, and I’ve watched women who’d never call themselves ‘fit’ pop up like it’s nothing. It has almost nothing to do with how someone looks and almost everything to do with what’s actually happening in their hips, ankles, and core. That’s exactly why I think every woman should know her own score instead of guessing.”

Terry Tateossian, Founder of The House of Rose

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Did the Research Actually Find?

The first major test of the SRT followed just over 2,000 adults aged 51 to 80 for a median of 6.3 years, tracking their SRT scores against all-cause mortality.

Participants who scored in the lowest range, 0 to 3, had a substantially higher mortality risk than those who scored in the highest range, 8 to 10, and the gap between groups was large enough that researchers reported each single-point improvement in SRT score was associated with roughly a 21% reduction in all-cause mortality risk over the follow-up period.

One fewer hand needed on the floor was measurably associated with better long-term survival odds. That study was published in the European Journal of Preventive Cardiology in 2014, and it’s been cited widely since, in part because the test costs nothing, takes under a minute, and requires no equipment.

A larger, more recent follow-up study from the same research group has since extended these findings to a bigger cohort with a longer follow-up period, and has reported that the association holds, including a specific link to cardiovascular mortality, though the precise statistics from that expanded study weren’t independently verifiable at the time of writing and are noted here directionally rather than with specific figures.

Important: An SRT score is a marker associated with mortality risk in population-level research. It is not a diagnosis, and a lower score doesn’t mean a fixed outcome. It’s a signal worth acting on, not a verdict.

How Does the Companion Single-Leg Stance Test Work?

The same research group behind the SRT also studied an even simpler assessment: standing on one leg, unsupported, for 10 seconds. In a study of roughly 1,700 adults aged 51 to 75, published in the British Journal of Sports Medicine in 2022, about one in five participants couldn’t complete the 10-second single-leg stance.
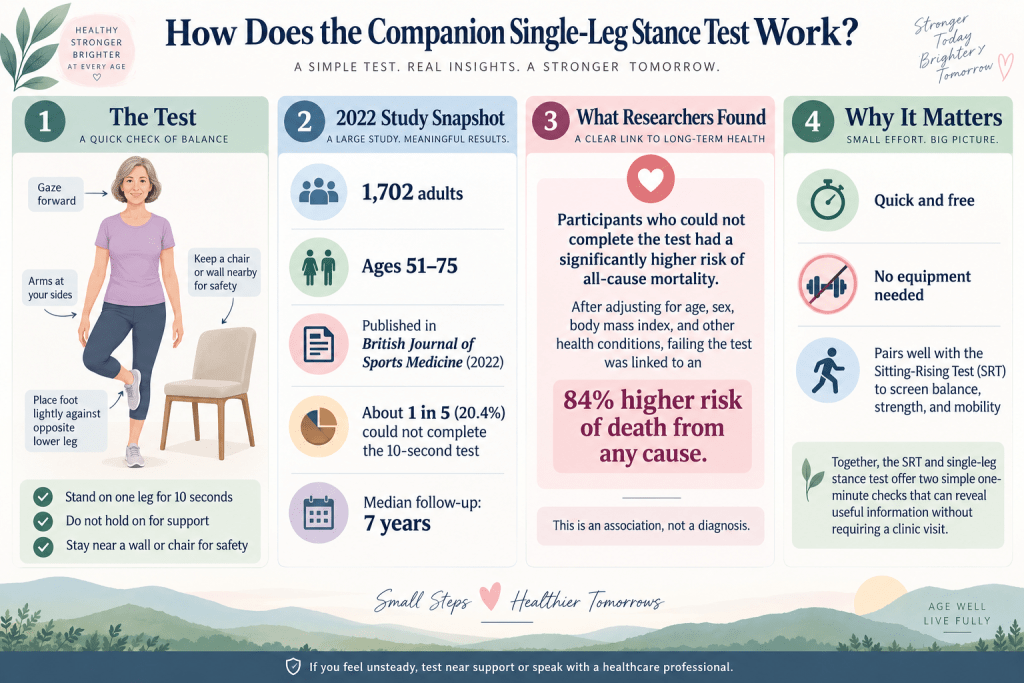
Single-leg stance test infographic for balance and health.

Over a median follow-up of about seven years, those who failed the test had a meaningfully higher risk of all-cause mortality than those who passed, even after adjusting for age, sex, body mass index, and other health conditions.

The single-leg stance test adds another quick way to assess balance, with clear scoring thresholds and a practical progression for improving your result. Together, the SRT and single-leg stance test provide two free, one-minute assessments that can reveal useful information about strength, mobility, and balance without requiring a clinical visit.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Why Can a Simple Floor Test Outperform Some Clinical Measures?

A cardiovascular fitness test can tell you your heart and lungs are working well while saying nothing about whether your ankles have the mobility to get you off the ground. A blood panel can come back completely normal while muscle mass and balance are quietly declining in the background.
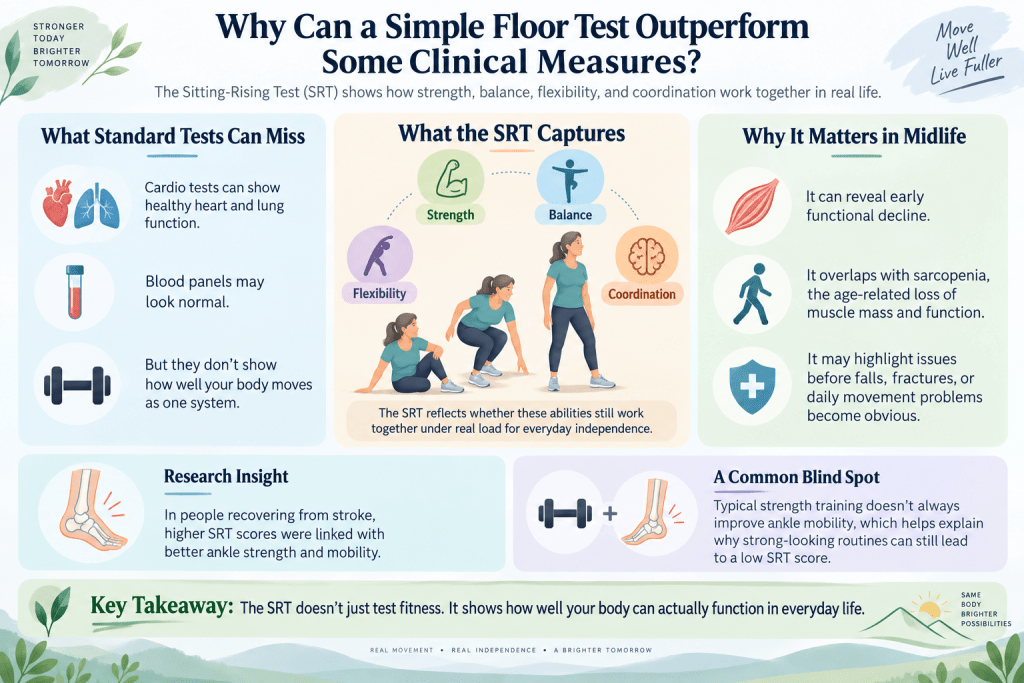
SRT showing strength, balance, flexibility, and coordination.

The SRT captures something those measures miss: whether strength, balance, flexibility, and coordination are all still functioning together, under real load, the way they need to for everyday independence.

This overlaps directly with sarcopenia, the age-related loss of muscle mass and function that can become increasingly important in midlife. The SRT offers one practical way to spot early functional changes in strength, mobility, and coordination before they become more obvious through falls, fractures, or difficulty with everyday movement.

Research on the SRT in populations recovering from conditions like stroke has found that rising scores correlate specifically with ankle strength and mobility, since getting up from the floor without using your hands requires meaningful work from the ankles, not just the legs and core.

Ankle mobility is rarely a focus of typical strength training, which is part of why a strong-looking training routine can still leave someone with a lower-than-expected SRT score.

What Does a Good Score Look Like by Age?

Reference data collected from thousands of non-athlete adults, organized by age and sex, gives a useful benchmark for where a given score falls relative to typical values.

Score Range General Interpretation
10 Full, unsupported sit and rise. Common in younger adults, uncommon after 55.
8-9 Strong functional capacity with minor support needed.
6-7 Moderate functional capacity; room for improvement in one or more systems.
4-5 Meaningful functional limitation; worth structured attention.
0-3 Significant functional limitation; consider professional guidance alongside training.

A perfect score of 10 is common among younger adults but becomes uncommon after age 55, and research suggests fewer than roughly 8% of adults over 55 achieve it. The test tends to be most useful for distinguishing meaningful differences in functional capacity roughly between ages 46 and 80, which is precisely the window where catching early decline matters most for long-term independence.

It’s also worth noting that people with a lifelong habit of floor-sitting or squatting, common in some cultures and less common in Western furniture-heavy lifestyles, tend to score higher across all age groups, meaning the test reflects movement habits over a lifetime, not just current-day fitness.

Guest A shows stronger overall function, while Guest B needs more strength, mobility, and balance training.

Guest A Guest B
Age 54 54
SRT Score 9 (used one hand briefly) 4 (needed both hands, a knee, and wobbled)
Likely contributing factors Good ankle mobility, regular strength training Limited hip/ankle mobility, minimal strength training, sedentary work
Suggested focus Maintenance, refine balance Structured strength, mobility, and balance program

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Can You Improve Your Score Based on What’s Actually Holding You Back?

Improving an SRT score isn’t about “exercising more” in a general sense. It’s about identifying which specific system cost you points and training that system directly.
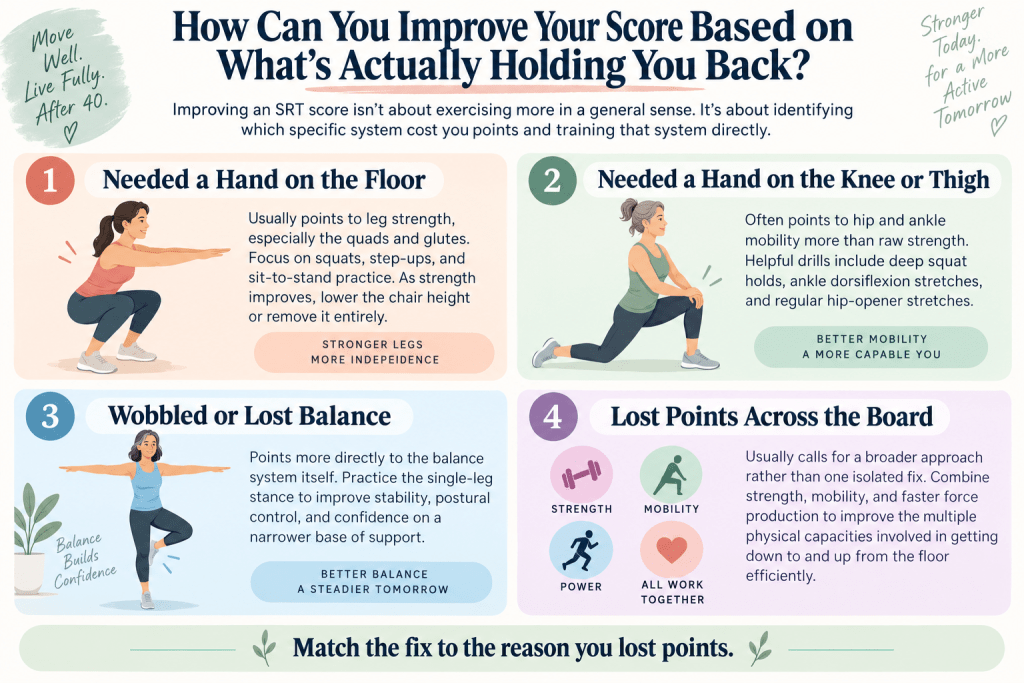
Improve SRT score with strength, mobility, and balance training.
  • If you lost points because you needed a hand on the floor: This usually points to leg strength, particularly the quads and glutes. Focus on squats, step-ups, and sit-to-stand practice from a chair, gradually lowering the chair height or removing it entirely as strength improves.
  • If you lost points because you needed a hand on your knee or thigh: This often points to hip and ankle mobility rather than raw strength. Deep squat holds, ankle dorsiflexion stretches, and hip-opener stretches performed regularly can meaningfully improve this over several weeks.
  • If you lost points because you wobbled or lost balance: This points more directly to the balance system itself. Practicing the single-leg stance gives you a simple, targeted way to work on stability, postural control, and confidence on a narrower base of support.
  • If you lost points across the board: A lower score in several areas usually calls for a broader approach rather than one isolated fix. Combining strength, mobility, and faster force production—and understanding the role of power vs strength – can help address the multiple physical capacities involved in getting down to and up from the floor efficiently.

What Safety Notes Should You Know Before You Try It?

Practice near a sturdy chair or counter the first few times, especially if balance is a known concern.
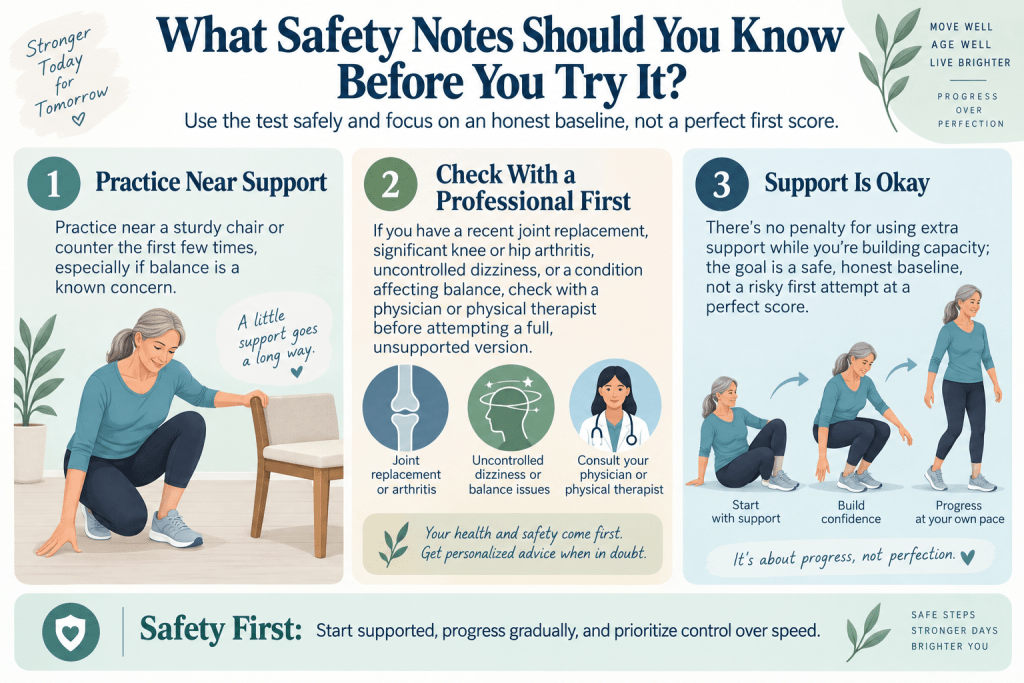
Woman using chair support during a safe floor test.

If you have a recent joint replacement, significant knee or hip arthritis, uncontrolled dizziness, or a condition affecting balance, check with a physician or physical therapist before attempting a full, unsupported version.

There’s no penalty for using extra support while you’re building capacity; the goal is a safe, honest baseline, not a risky first attempt at a perfect score.

Your Next Steps

  1. Take the sitting-rising test once, safely, near a chair or counter for support if needed, and record your honest score.
  2. Identify which system cost you points—strength, mobility, or balance—using the breakdown above.
  3. If balance was the main issue, use the single-leg stance as a simple way to train stability and postural control directly.
  4. If strength was the broader limitation, understanding the difference between power and strength can help you build a more complete training plan around both force and speed.
  5. Retest in 4 to 8 weeks and track your score alongside your training. You can also use the free macro calculator to make sure your calorie and protein targets are supporting the muscle you’re working to build.

For a more immersive approach, THOR’s women’s wellness & yoga retreats incorporate guided movement, mobility, and strength work into the retreat experience, giving you a supportive setting to practice the same functional skills the SRT is designed to assess.

If you want a plan built around your own results, 1:1 nutrition coaching can help translate your SRT score into a more targeted training strategy focused on the areas that need the most attention.

Important: This article is educational and does not replace individualized medical advice. Please consult a physician or physical therapist before attempting this test if you have a joint replacement, recent surgery, or a condition affecting balance.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Frequently Asked Questions

What’s the difference between the sitting-rising test and the sit-to-stand test?

They’re related but distinct. The sitting-rising test (SRT), covered in this article, involves lowering all the way to the floor and standing back up. The sit-to-stand test typically refers to a chair-based assessment, often counting how many times someone can stand up and sit back down in 30 seconds, used commonly in physical therapy and geriatric settings.

What’s considered a “good” SRT score?

Generally, a score at or above the 50th percentile for your age and sex is considered a reasonable target, which for most midlife women falls somewhere in the 7 to 9 range, though this varies by age.

Can I improve my score, or is it fixed by genetics and age?

It can be improved. Strength, mobility, and balance are all trainable at any age, and the specific deficiency behind a low score (strength, mobility, or balance) points directly to what to train.

Is a low score a diagnosis of something serious?

No. It’s a marker associated with mortality risk at a population level in research studies, not an individual diagnosis. A low score is a signal to pay attention to, not a medical verdict.

How often should I retest my score?

Every 4 to 8 weeks is reasonable while actively working on the systems behind a low score, since meaningful strength and mobility changes typically take several weeks to show up.

Is it normal to lose points even if I consider myself fit?

Yes. Cardiovascular fitness and general “fitness” don’t always translate to floor mobility, since the SRT specifically tests a combination of strength, hip and ankle mobility, and balance that many training programs don’t directly address.

Does the test work the same for someone with knee or hip arthritis?

The test can still be informative, but modifications and physician guidance are appropriate, since arthritis can affect the movement independent of overall functional capacity. Don’t force a full unsupported attempt if it causes pain.

Why does ankle mobility matter so much for this test?

Getting up from the floor without using your hands requires meaningful ankle dorsiflexion (the ability to bring your shin toward your foot), a range of motion that’s rarely trained directly and tends to decline with age and sedentary habits.

Can children or very fit young adults score below 10?

Rarely, but it can happen, particularly if flexibility or coordination is limited despite good strength. The test is most useful and most differentiating in adults roughly 46 and older.

Does practicing the test itself count as training?

Practicing the movement pattern helps with coordination and confidence, but true score improvement usually requires targeting the underlying strength, mobility, or balance deficit directly, not just repeating the test.

Is the sitting-rising test culturally biased toward people who squat regularly?

To some degree, yes. People with a lifelong habit of floor-sitting or squatting tend to score higher, which researchers have noted as a limitation. It doesn’t invalidate the test’s value as a personal baseline and tracking tool, but it’s a reasonable caveat when comparing scores across very different lifestyle backgrounds.

Should I do this test alone or with someone watching?

Either works for a general self-assessment, but having someone watch the first attempt, especially if balance is a concern, adds a safety margin and can help catch small support movements you might not notice yourself doing.

How does this relate to sarcopenia?

The SRT is one practical way to catch the functional consequences of sarcopenia, age-related muscle loss, before they show up as a fall or loss of independence. THOR’s Sarcopenia guide covers the full picture of why this muscle loss happens and how to address it.

What if I can’t get to the floor at all right now?

That’s valuable information on its own and a strong reason to start with the individual components (chair-based sit-to-stand practice, hip and ankle mobility work) before attempting the full floor version, ideally with guidance from a physical therapist.

I write 3 essays per week on Lifestyle Medicine for women in midlife on what is happening in the body and what to do about it. No fluff, no hype. Free.

References

  • de Brito, L. B. B., Ricardo, D. R., Araújo, D. S. M. S., Ramos, P. S., Myers, J., & Araújo, C. G. S. (2014). Ability to sit and rise from the floor as a predictor of all-cause mortality. European Journal of Preventive Cardiology, 21(7), 892-898.
  • Araújo, C. G., de Souza e Silva, C. G., Laukkanen, J. A., Fiatarone Singh, M., Kunutsor, S. K., Myers, J., et al. (2022). Successful 10-second one-legged stance performance predicts survival in middle-aged and older adults. British Journal of Sports Medicine, 56(17), 975-980.
  • Araújo, C. G., et al. Age- and sex-specific reference values for the sitting-rising test in a large non-athlete adult population. European Journal of Preventive Cardiology.
  • National Institute on Aging patient guidance on functional fitness assessments and fall risk.
  • American Physical Therapy Association clinical guidance on sit-to-stand testing in older adults.

Disclaimer: This article is educational and does not constitute medical advice. The sitting-rising test requires adequate strength, mobility, coordination, and balance, and may not be appropriate for everyone. If you have a joint replacement, recent surgery, significant knee or hip pain, dizziness, balance problems, or another condition affecting safe movement, consult a physician or physical therapist before attempting the test or following the exercises in this article.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
Sarcopenia: The Capacity Crisis Starts Small

Denise is fifty-eight and manages an office on the third floor of a building with no working elevator. Somewhere over the past year, the stairs started to feel different. Not painful, not injured, just harder, enough that she began timing her arrival to avoid climbing them right before a meeting.

Around the same time, she noticed she was choosing parking spots closer to the store entrance without really deciding to, and she had quietly stopped getting down on the living room floor to play with her grandchildren, telling herself she preferred the couch anyway. None of these felt like anything. Each one had a perfectly reasonable explanation on its own.

Denise did not have an injury. She did not have a diagnosis. What she had, without knowing the name for it, was the opening chapter of sarcopenia, the slow, largely painless loss of muscle mass and strength that begins for most people in their forties, not their eighties, and quietly narrows the range of what a body can do, one small accommodation at a time.

This is a word that deserves far more attention than it gets, precisely because it does not announce itself. It does not show up as an injury or a diagnosis you can point to. It shows up as a series of small, easy-to-explain-away choices, avoided stairs, closer parking, a preference for the couch over the floor, that quietly compound into something much larger: a shrinking capacity for independent living, years before most people think to worry about it.

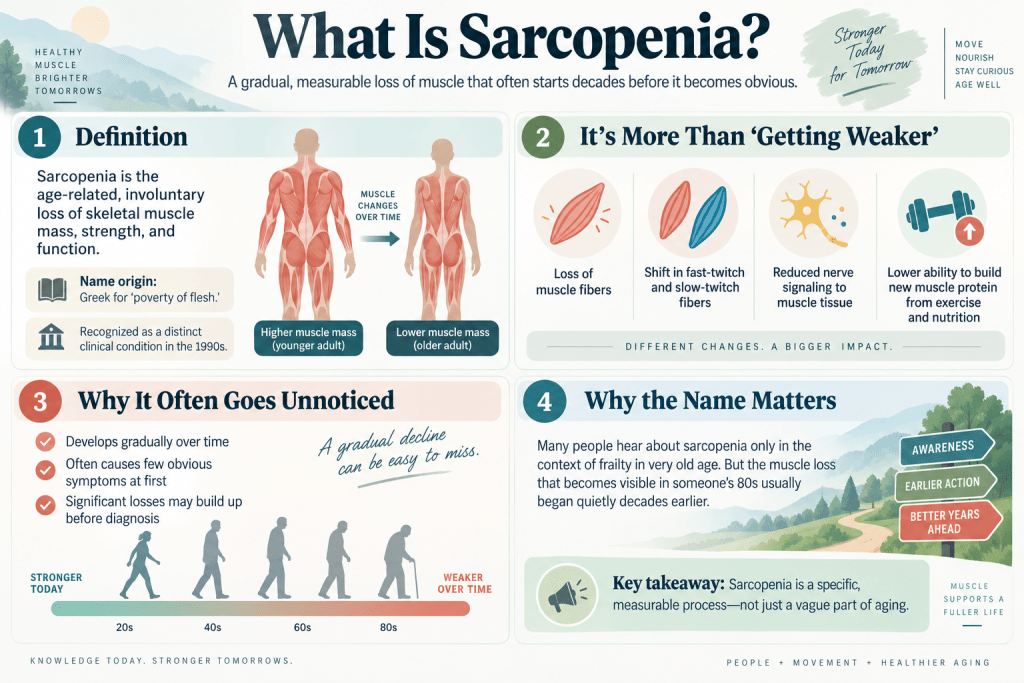
What Is Sarcopenia?

Sarcopenia is the age-related, involuntary loss of skeletal muscle mass, strength, and function. The term comes from Greek roots meaning “poverty of flesh,” and it was formally defined as a distinct clinical condition (rather than just a vague part of aging) in the 1990s, with diagnostic criteria refined significantly since then by international working groups.

Sarcopenia muscle loss infographic

Sarcopenia is not simply “getting weaker with age” in a vague sense. It is a specific, measurable process involving the loss of muscle fibers, a shift in the ratio of fast-twitch to slow-twitch fibers, reduced nerve signaling to muscle tissue, and a decline in the body’s ability to build new muscle protein in response to exercise and nutrition, all happening gradually and mostly without symptoms severe enough to prompt a doctor’s visit until the losses have already accumulated substantially.

The reason the name matters is that most people encounter sarcopenia, if they encounter the word at all, in the context of frailty in very elderly patients. That framing is exactly backward. The condition that becomes visible and disabling in someone’s eighties began decades earlier, quietly, in the exact way it began for Denise.

Why Does Sarcopenia Start in Your 40s, Not Your 80s?

Muscle mass generally peaks in the late twenties to early thirties. From roughly age 40 onward, most adults lose muscle mass at a rate of approximately 1 to 2 percent per year if no deliberate intervention (primarily resistance training and adequate protein intake) counteracts it. That rate of loss tends to accelerate further after age 60.

This means the muscle available to you at 70 is substantially determined by what happens in your 40s and 50s, not by anything that starts at 70 itself. By the time frailty becomes clinically obvious, in the form of difficulty rising from a chair, a slow walking pace, or a fall, the underlying muscle loss has typically been building for twenty to thirty years.

This is the central, underappreciated fact about sarcopenia: it is not an old-age problem that you will eventually need to deal with later. It is a midlife problem with an old-age price tag, and the years when it is most possible to prevent or reverse are the exact years, like Denise’s, when nothing feels wrong enough yet to act on.

“The thing that struck me most researching this topic is how ordinary the early signs are. Nobody in their forties or fifties thinks ‘I am experiencing early sarcopenia’ when they start parking closer to the store or avoiding a second flight of stairs. They think they are just busy, or tired, or getting older in the completely normal way everyone does. The problem is that ‘normal’ and ‘preventable’ are not the same thing, and this is one of the clearest cases I have found where the two get confused, with real consequences decades down the line.”

Terry Tateossian, Founder of The House of Rose

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.
How Does Frailty Creep Instead of Crash?

One of the most important things to understand about sarcopenia is the shape of its progression. It does not announce itself with a dramatic event. It advances through an accumulation of small, individually forgettable adjustments, each one reasonable on its own, that only reveal their true significance when looked at together, in hindsight, the way Denise’s story only made sense once she noticed the pattern across the stairs, the parking, and the floor.

This creeping pattern is precisely why sarcopenia is so often missed until it has already progressed significantly. There is no single moment that triggers concern. There is a slow, almost invisible narrowing of what feels comfortable and possible, until one day an ordinary task, a flight of stairs, a low chair, a full grocery bag, requires a level of effort or a workaround that would have seemed absurd a decade earlier.

Understanding this pattern is itself a form of protection. If you know that early sarcopenia looks like small, explainable avoidances rather than a dramatic loss of function, you can recognize those avoidances in your own life for what they might actually be, rather than dismissing each one individually the way most people, understandably, do.

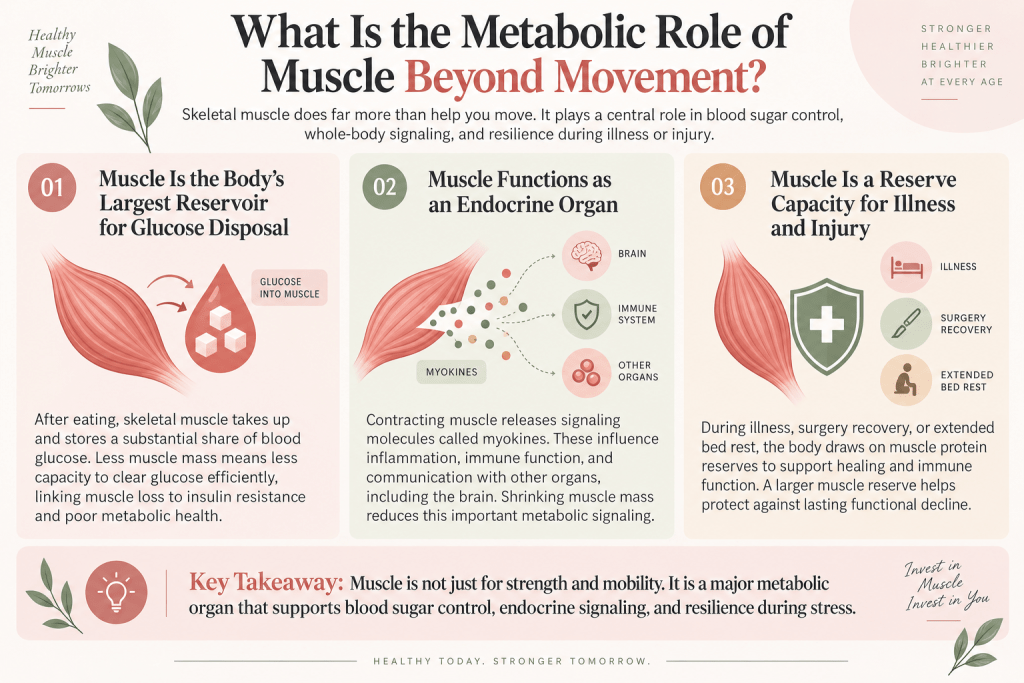
What Is the Metabolic Role of Muscle Beyond Movement?

Skeletal muscle is often thought of purely in mechanical terms, the tissue that lets you walk, lift, and climb. Its role in the body is considerably larger than that, which is part of why its loss carries consequences well beyond physical movement.

Muscle metabolic role infographic showing glucose, myokines, and recovery.

Muscle Is the Body’s Largest Reservoir for Glucose Disposal

After eating, skeletal muscle is where a substantial share of blood glucose is taken up and stored. Less muscle mass means less capacity to clear glucose from the bloodstream efficiently, directly connecting sarcopenia to insulin resistance and metabolic health, an underappreciated link for a condition usually discussed only in terms of strength and mobility.

Muscle Functions as an Endocrine Organ

Contracting muscle releases signaling molecules called myokines, which influence inflammation, immune function, and communication with other organs, including the brain. A shrinking muscle mass means a reduced signal from one of the body’s most metabolically active tissues.

Muscle Is a Reserve Capacity for Illness and Injury

This is perhaps the least discussed but most consequential role muscle plays. During illness, surgery recovery, or an extended period of bed rest, the body draws on muscle protein reserves to support immune function and healing. Someone with a larger muscle reserve going into an illness has considerably more capacity to withstand that draw without a lasting functional decline.

Someone already running a muscle deficit has far less room to absorb the same hit, which is precisely why a bout of flu or a minor surgery can trigger a permanent drop in baseline function for one person and barely register for another of the same age.

This last point deserves particular emphasis, because it reframes what muscle actually is for. It is not simply about looking a certain way or performing well in a gym. It is a buffer against the unpredictable physical demands life places on the body, and a shrinking buffer means a shrinking margin for error.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Why Do Midlife Women Face Added Risk?

The Menopause Transition Accelerates Muscle Loss Beyond the Baseline Rate

Estrogen plays a supportive role in muscle protein synthesis and maintenance. Its decline through perimenopause and menopause is associated with an acceleration of muscle loss beyond the general age-related rate that affects both sexes, meaning the “1 to 2 percent per year” figure in Section 2 likely understates the rate many women experience specifically through this transition.

Historical Underrepresentation in Strength Training

Women have historically been less likely than men to engage in resistance training, often steered instead toward cardio-focused exercise for decades of fitness culture.

Cardio exercise offers real cardiovascular benefits but does not provide the same targeted stimulus for building and preserving muscle mass that resistance training does, meaning many women reach midlife with less accumulated muscle reserve to draw on in the first place.

Bone and Muscle Loss Compound Each Other

Menopause-related bone density decline (osteopenia and osteoporosis) and sarcopenia frequently occur together, sometimes described as “osteosarcopenia,” and each condition makes the consequences of the other more serious: weaker bones increase fracture risk from a fall, and weaker muscles increase the likelihood of the fall itself.

Underdiagnosis

Sarcopenia in women is frequently underrecognized in clinical settings, partly because standard body weight and BMI measurements do not distinguish between muscle and fat mass, meaning a woman who is not classified as underweight or who has stable body weight can still be losing meaningful muscle mass without it being flagged by routine measurements.

What Are the Warning Signs Nobody Names?

Because sarcopenia progresses gradually, the early warning signs tend to look exactly like ordinary life adjustments rather than symptoms:

  • Avoiding stairs when a similar route without stairs is available, even if it takes longer
  • Choosing closer parking spots than you used to, without a specific reason
  • A growing reluctance to get down onto the floor, or difficulty getting back up without using your hands or furniture for support
  • Needing two trips to carry groceries that used to take one
  • A noticeably slower walking pace compared to a few years ago, or being the person who consistently lags behind in a group
  • Difficulty opening jars, twisting off tight lids, or other grip-strength-dependent tasks
  • A general sense of “I used to be able to do that more easily” about ordinary physical tasks, without a specific injury to explain it

None of these signs, on their own, is alarming. That is exactly the point. The value of naming them is not to create anxiety about ordinary tasks, but to help you notice a pattern across several of them, the way Denise eventually did, rather than writing off each one individually as unrelated to anything.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

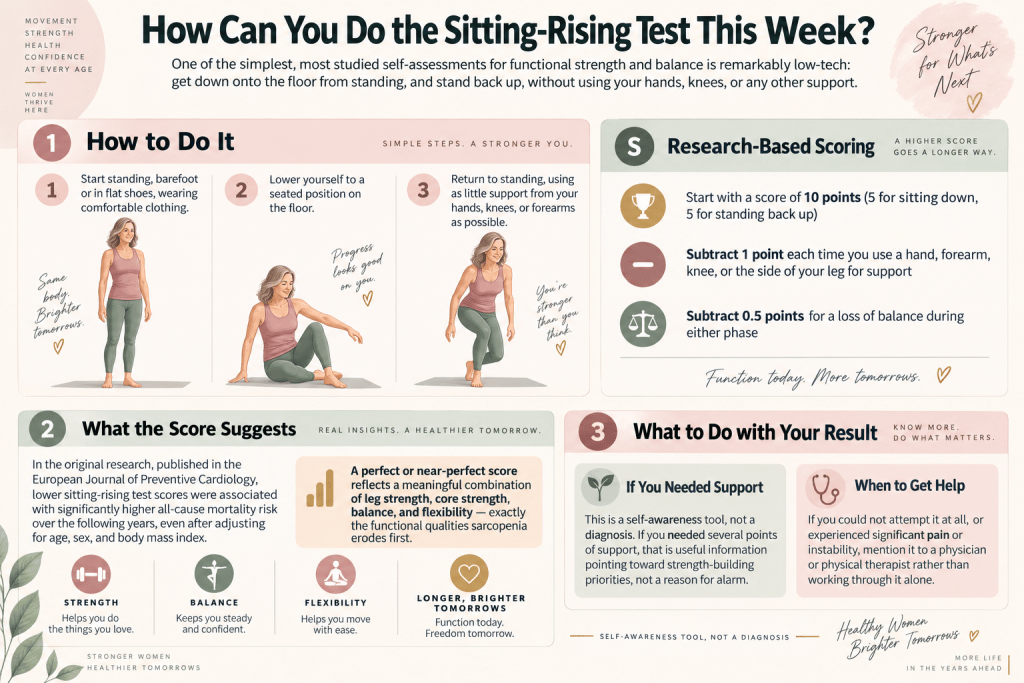
How Can You Do the Sitting-Rising Test This Week?

One of the simplest, most studied self-assessments for functional strength and balance is remarkably low-tech: get down onto the floor from standing, and stand back up, without using your hands, knees, or any other support.


Woman demonstrating the sitting-rising test and scoring guide.

How to Do It

Start standing, barefoot or in flat shoes, wearing comfortable clothing. Lower yourself to a seated position on the floor, then return to standing, using as little support from your hands, knees, or forearms as possible.

A more formal, research-based scoring version, developed by Brazilian physician Dr. Claudio Gil Araújo and colleagues, works like this:

  • Start with a score of 10 points (5 for sitting down, 5 for standing back up)
  • Subtract 1 point each time you use a hand, forearm, knee, or the side of your leg for support
  • Subtract 0.5 points for a loss of balance during either phase

What the Score Suggests

In the original research, published in the European Journal of Preventive Cardiology, lower sitting-rising test scores were associated with significantly higher all-cause mortality risk over the following years, even after adjusting for age, sex, and body mass index.

A perfect or near-perfect score reflects a meaningful combination of leg strength, core strength, balance, and flexibility, exactly the functional qualities sarcopenia erodes first.

What to Do with Your Result

This is a self-awareness tool, not a diagnosis. If you needed several points of support, that is useful information pointing toward the strength-building priorities in Section 11, not a reason for alarm.

If you could not attempt it at all, or experienced significant pain or instability, that is worth mentioning to a physician or physical therapist rather than working through alone.

What Does the Research Show About Midlife Strength and Later Independence?

  • Midlife grip strength predicts later disability: Multiple long-term cohort studies have found that grip strength measured in midlife is a meaningful predictor of disability, hospitalization, and mortality decades later, making it one of the most studied simple biomarkers of overall physiological resilience.
  • Resistance training reverses, not just slows, muscle loss: Unlike many age-related processes, sarcopenia remains highly responsive to intervention at any age, including in adults in their seventies, eighties, and nineties. Studies on resistance training in older adults have documented meaningful increases in muscle mass, strength, and functional capacity, even in very advanced age, which is a fundamentally hopeful finding: this is not a one-way, irreversible decline if addressed with the right intervention.
  • Muscle mass and metabolic health are closely linked: Research connecting skeletal muscle mass to insulin sensitivity and glucose metabolism supports the mechanism described in Section 4, showing that preserving muscle mass has metabolic benefits that extend well beyond strength and mobility alone.
  • The “anabolic resistance” of aging muscle: Research on aging muscle physiology has documented a phenomenon sometimes called anabolic resistance, where aging muscle requires a larger protein stimulus to trigger the same amount of muscle protein synthesis compared to younger muscle. This is part of why the nutrition guidance in Section 12 differs somewhat from general population protein recommendations.
  • Functional decline is not linear, and neither is recovery potential: Longitudinal research on functional decline in aging populations shows that while the trajectory can accelerate over time if unaddressed, intervention at any point, including after a period of decline, produces meaningful functional improvement in the majority of studied populations, reinforcing that midlife action matters, but so does action taken later.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Does Sarcopenia Compound Through the One-Way Ratchet?

Sarcopenia’s most dangerous property is not the muscle loss itself in any single year, but the way it interacts with ordinary life events to compound over time, a pattern sometimes described as a one-way ratchet.

The Illness-Bed Rest-Decline Cycle

As introduced in Section 4, a period of illness or injury draws on the body’s muscle reserve. For someone with adequate reserve, that draw is absorbed and largely recovered from once the illness resolves.

For someone already running a deficit, the same illness can produce a drop in baseline function, reduced walking speed, reduced ability to climb stairs, that does not fully recover, becoming the new normal rather than a temporary dip.

Reduced Activity Following a Functional Drop Reinforces Further Loss

Once climbing stairs or getting up from the floor becomes noticeably harder, the natural response is to do it less, which further accelerates muscle loss, creating a feedback loop that becomes progressively harder to interrupt the longer it continues.

Each Cycle Narrows the Margin for the Next One

This is the ratchet mechanism: each illness-decline cycle leaves a slightly lower baseline than before, meaning the next illness or injury has to overcome less resistance to produce another drop.

Over twenty or thirty years, a series of individually modest declines compounds into the significant frailty that eventually becomes visible and disabling.

The Good News: The Ratchet Can Be Interrupted, Not Just Slowed

Unlike some other age-related processes, this cycle is not purely one-directional if resistance training and adequate nutrition are introduced, which is precisely why the sections ahead focus on concrete action rather than simply describing the problem.

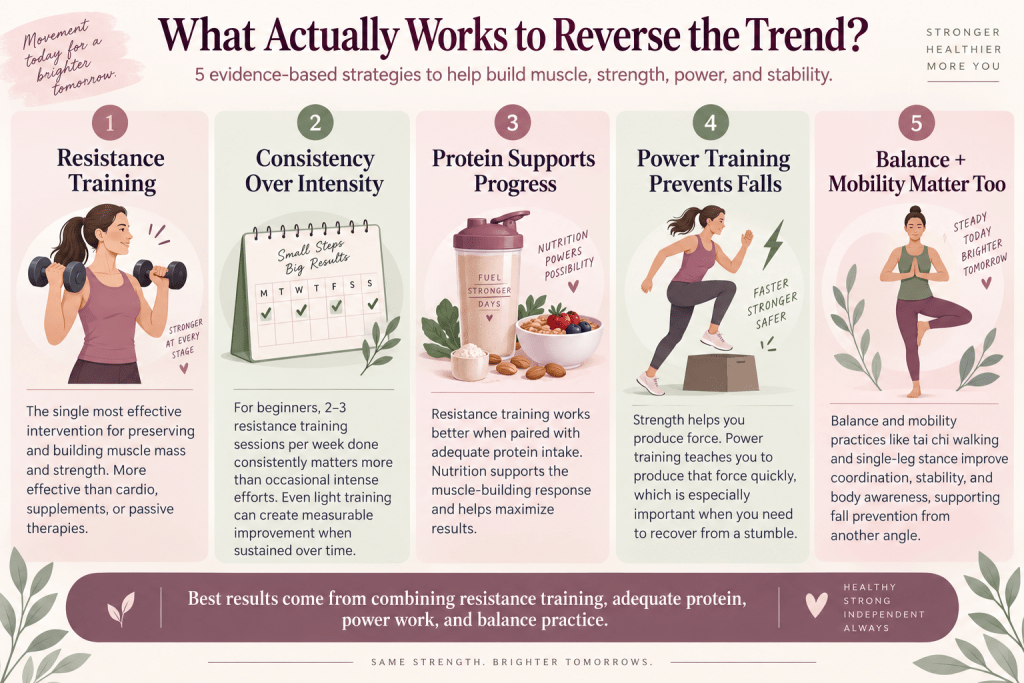
What Actually Works to Reverse the Trend?

Five strategies to reverse muscle loss and improve strength.
  • Resistance training is the single most effective intervention: No other intervention, not cardio exercise, not any supplement, not any passive therapy, comes close to progressive resistance training for building and preserving muscle mass and strength at any age. This is the foundational, non-negotiable piece of addressing sarcopenia.
  • Consistency matters more than intensity for beginners: Two to three resistance training sessions per week, sustained over months and years, produces far more benefit than sporadic, intense efforts. For someone starting from a significant deficit, even light resistance training performed consistently produces measurable improvement.
  • Protein intake must support the training stimulus: As covered in Section 12, resistance training without adequate protein intake produces a smaller muscle-building response than the two combined, making nutrition a genuine partner to training rather than a separate consideration.
  • Power training, not just strength training, matters for fall prevention specifically: Strength helps you produce force, but power training teaches your body to produce that force quickly. That faster response becomes especially important during a stumble, when you need to react immediately to regain your footing rather than simply rely on how much weight you can lift.
  • Balance and mobility work supports the same goal from a different angle: Practices such as tai chi walking train controlled weight shifts, coordination, and body awareness, while the single-leg stance challenges the stability needed to stay upright when your base of support narrows. Together, these skills complement strength and power training by addressing the balance and coordination side of fall prevention.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

How Can You Build a Sarcopenia-Resistant Strength Routine?

  • Frequency: 2 to 3 resistance training sessions per week: targeting all major muscle groups across the week rather than the same muscles every session.
  • Focus on compound movements first: Squats, hip hinges (deadlift variations), presses, and rows recruit multiple muscle groups simultaneously and produce more functional carryover to daily tasks like rising from a chair or carrying groceries than isolated single-muscle exercises.
  • Include the specific movement pattern from Section 7: Practicing controlled sit-to-stand movements, from a chair initially, progressing toward the floor-based version over time, directly trains the exact functional pattern the sitting-rising test measures.
  • Add a power component: A small number of faster, more explosive repetitions (such as a quicker tempo on the upward phase of a squat) trains the fast-twitch muscle fibers most responsible for catching a stumble before it becomes a fall.
  • Progressive overload over time: Gradually increasing resistance, repetitions, or difficulty over weeks and months is what continues to stimulate muscle adaptation; a routine that never becomes more challenging eventually stops producing further improvement.
  • Start wherever you are: For someone new to resistance training or returning after a long break, bodyweight exercises and light resistance are a completely legitimate and effective starting point. The goal is consistent progression over time, not an advanced starting point.

For a more structured approach, a complete strength training framework can help you build a routine around progressive resistance, compound movements, and consistent weekly training.

What Role Does Nutrition Play in Protein and Muscle Preservation?

  • Aging muscle needs more protein per meal, not just more protein overall: As referenced in Section 8, anabolic resistance means older muscle requires a larger protein dose per meal to trigger the same muscle-building response compared to younger muscle, making protein distribution across the day, not just total daily intake, a meaningful consideration.
  • A general target of 25 to 35 grams of high-quality protein per meal: is commonly recommended in the sarcopenia and muscle-aging research literature to help overcome this reduced sensitivity, spread across three or more meals rather than concentrated in a single large dose.
  • Leucine-rich protein sources appear particularly effective at triggering muscle protein synthesis: Leucine, an amino acid found in high concentrations in dairy, eggs, meat, and fish, plays an outsized role in triggering the cellular signaling that initiates muscle protein synthesis.
  • Creatine supplementation has a substantial research base supporting muscle preservation, particularly alongside resistance training: Adding creatine for women over 40 to a consistent strength routine can support muscle strength, training performance, and recovery, with creatine monohydrate remaining the most extensively studied form.
  • Adequate overall energy intake matters: Chronic under-eating, common among midlife women focused on weight management, can undermine muscle preservation efforts even when protein and training are otherwise well managed, since the body needs sufficient overall energy availability to prioritize muscle building rather than survival-mode conservation.

For a more personalized target, the protein calculator for women over 40 can help estimate how much protein you need based on your body, activity level, and goals, giving you a clearer foundation for supporting muscle maintenance and metabolic health.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

What Are the Common Mistakes and Misconceptions About Sarcopenia?

  1. Mistake: Waiting for a diagnosis before taking action. Sarcopenia is rarely formally diagnosed until it has progressed significantly. Waiting for a clinical label before addressing the underlying muscle loss means waiting far too long.
  2. Mistake: Assuming cardio alone is sufficient. Cardiovascular exercise offers genuine, important benefits, but it does not provide the specific mechanical loading stimulus that builds and preserves muscle mass the way resistance training does.
  3. Mistake: Believing muscle loss cannot be reversed at an older age. As covered in Section 8, research consistently shows meaningful muscle and strength gains are achievable even in very advanced age with appropriate resistance training, making “it’s too late” one of the most costly misconceptions on this topic.
  4. Mistake: Underestimating protein needs due to outdated general guidelines. Many people are still working from general population protein recommendations that do not account for the increased needs and anabolic resistance associated with aging muscle.
  5. Mistake: Treating the warning signs in Section 6 as isolated, unrelated inconveniences. As covered throughout this article, the value of recognizing these signs comes from seeing the pattern across several of them, not dismissing each one individually.

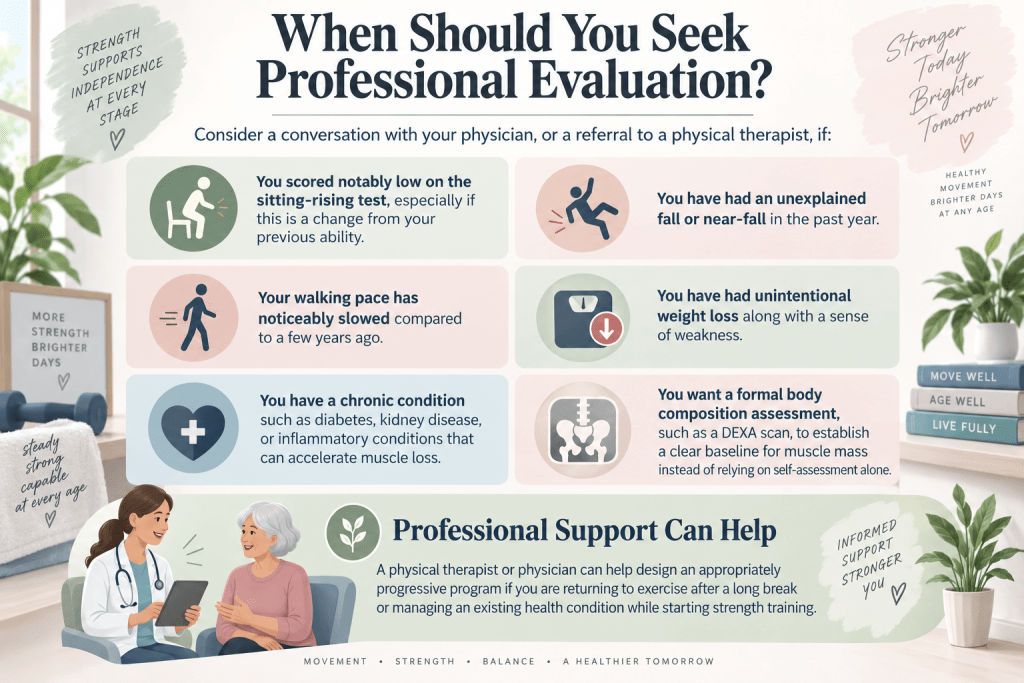
When Should You Seek Professional Evaluation?

Signs to seek professional evaluation

Consider a conversation with your physician, or a referral to a physical therapist, if:

  • You scored notably low on the sitting-rising test in Section 7, particularly if this represents a change from previous ability
  • You have experienced an unexplained fall or near-fall in the past year
  • Your walking pace has noticeably slowed compared to a few years ago
  • You have experienced unintentional weight loss alongside a sense of weakness
  • You have a chronic condition (diabetes, kidney disease, inflammatory conditions) known to accelerate muscle loss
  • You want a formal body composition assessment (such as a DEXA scan) to establish a clear baseline for muscle mass rather than relying on self-assessment alone

A physical therapist or physician can also help design an appropriately progressive program if you are returning to exercise after a long break or managing an existing health condition alongside a new strength training practice.

This article is educational and is not a substitute for professional medical advice. Consult your physician before beginning a new exercise program, particularly if you have an existing health condition.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.

Frequently Asked Questions

What is sarcopenia?

Sarcopenia is the age-related, involuntary loss of skeletal muscle mass, strength, and function. It typically begins around age 40, progresses gradually, and accelerates further after age 60 if not counteracted by resistance training and adequate nutrition.

What are the early symptoms of sarcopenia?

Early signs tend to look like ordinary life adjustments rather than obvious symptoms: avoiding stairs, choosing closer parking, reluctance to get down on the floor, needing extra trips to carry groceries, or a general sense that ordinary physical tasks require more effort than they used to.

Can sarcopenia be reversed?

Yes, at nearly any age. Research consistently shows that resistance training produces meaningful increases in muscle mass, strength, and function even in adults in their seventies, eighties, and nineties, making this a highly responsive condition rather than a fixed, one-way decline.

What is the sitting-rising test?

A simple self-assessment where you lower yourself from standing to sitting on the floor, then stand back up, ideally without using your hands, knees, or other support. Lower scores on validated versions of this test have been associated with higher long-term mortality risk in research studies, making it a useful, low-tech gauge of overall functional strength and balance.

At what age should I start worrying about sarcopenia?

The most useful framing is not worry but action: since muscle loss typically begins around age 40 and the years of easiest prevention are in midlife, starting resistance training and adequate protein intake in your 40s and 50s, well before any noticeable decline, is the most effective window for prevention.

How much protein do I need to prevent sarcopenia?

Research on aging muscle generally supports 25 to 35 grams of high-quality protein per meal, spread across three or more meals daily, higher than general population recommendations, to help overcome the reduced protein sensitivity (anabolic resistance) associated with aging muscle.

Is sarcopenia worse for women than men?

Women face some added risk factors, including accelerated muscle loss during the menopause transition due to declining estrogen, historically lower rates of resistance training participation, and a compounding relationship with menopause-related bone density loss, though sarcopenia affects both sexes.

What exercises are best for preventing sarcopenia?

Progressive resistance training focused on compound movements (squats, hip hinges, presses, rows) 2 to 3 times per week is the most effective intervention, ideally combined with some power-focused training and balance work.

Can I have sarcopenia even if my weight is normal or I’m not underweight?

Yes. Standard body weight and BMI measurements do not distinguish between muscle and fat mass, meaning someone at a stable or even overweight body weight can still be losing significant muscle mass without it being reflected on a scale.

Does cardio exercise prevent sarcopenia?

Cardiovascular exercise offers real, important health benefits, but it does not provide the specific mechanical loading stimulus that resistance training provides for building and preserving muscle mass. Cardio and resistance training address different physiological needs and work best in combination, not as substitutes for each other.

How is sarcopenia diagnosed?

Formal diagnosis typically involves a combination of measures: muscle strength (often grip strength), physical performance (such as walking speed), and, in some settings, muscle mass measurement via DEXA scan or similar imaging. In practice, sarcopenia is often underdiagnosed since these measurements are not part of routine checkups for most midlife adults.

References

  • Rosenberg, I. H. (1997). Sarcopenia: Origins and clinical relevance. The Journal of Nutrition, 127(5), 990S-991S.
  • Cruz-Jentoft, A. J., Bahat, G., Bauer, J., Boirie, Y., Bruyère, O., Cederholm, T., Cooper, C., Landi, F., Rolland, Y., Sayer, A. A., Schneider, S. M., Sieber, C. C., Topinkova, E., Vandewoude, M., Visser, M., Zamboni, M., & the Writing Group for the European Working Group on Sarcopenia in Older People 2 (EWGSOP2). (2019). Sarcopenia: Revised European consensus on definition and diagnosis. Age and Ageing, 48(1), 16-31.
  • Araújo, C. G. S., de Souza e Silva, C. G., Laukkanen, J. A., Fiatarone Singh, M., Kunutsor, S. K., Myers, J., Franca, J. F., & Castro, C. L. (2022). Successful 10-second one-legged stance performance predicts survival in middle-aged and older individuals. British Journal of Sports Medicine, 56(17), 975-980.
  • Brito, L. B. B., Ricardo, D. R., Araújo, D. S. M. S., Ramos, P. S., Myers, J., & Araújo, C. G. S. (2014). Ability to sit and rise from the floor as a predictor of all-cause mortality. European Journal of Preventive Cardiology, 21(7), 892-898.
  • Cruz-Jentoft, A. J., & Sayer, A. A. (2019). Sarcopenia. The Lancet, 393(10191), 2636-2646.
  • Volpi, E., Nazemi, R., & Fujita, S. (2004). Muscle tissue changes with aging. Current Opinion in Clinical Nutrition and Metabolic Care, 7(4), 405-410.
  • Wright, K. E., Skinner, S., & Zhu, S. (2023). The musculoskeletal syndrome of menopause. Climacteric, 26(4), 366-371.
  • Fielding, R. A., Vellas, B., Evans, W. J., Bhasin, S., Morley, J. E., Newman, A. B., Abellan van Kan, G., Andrieu, S., Bauer, J., Breuille, D., Cederholm, T., Chandler, J., De Meynard, C., Donini, L., Harris, T., Kannt, A., Keime Guibert, F., Onder, G., Papanicolaou, D., Rolland, Y., Rooks, D., Sieber, C., Souhami, E., Verlaan, S., & Zamboni, M. (2011). Sarcopenia: An undiagnosed condition in older adults. Journal of the American Medical Directors Association, 12(4), 249-256.
  • Peterson, M. D., Rhea, M. R., Sen, A., & Gordon, P. M. (2010). Resistance exercise for muscular strength in older adults: A meta-analysis. Ageing Research Reviews, 9(3), 226-237.
  • Rubio-Ruiz, M. E., Guarner-Lans, V., Pérez-Torres, I., & Soto, M. E. (2019). Mechanisms underlying metabolic syndrome-related sarcopenia and possible therapeutic measures. International Journal of Molecular Sciences, 20(3), 647.

Disclaimer: This article is educational and does not constitute medical advice, diagnosis, or treatment. Sarcopenia, weakness, balance changes, and loss of physical function can have multiple causes and may require professional evaluation. Resistance and power training should be progressed appropriately for your current strength, mobility, and health status. If you have significant joint or balance problems, cardiovascular concerns, chronic medical conditions, recent injuries or surgery, unexplained weakness or weight loss, or a history of falls, consult a healthcare provider or physical therapist before beginning the exercises, self-tests, or nutrition strategies described in this article.

Free 28-Day Fascia Reset Email Course

Get our Free 28-day email course series to help with 1 or 2 exercises per day to release your fascia. One short lesson per day. Two minutes to read each.